The Core Mechanism of CBT
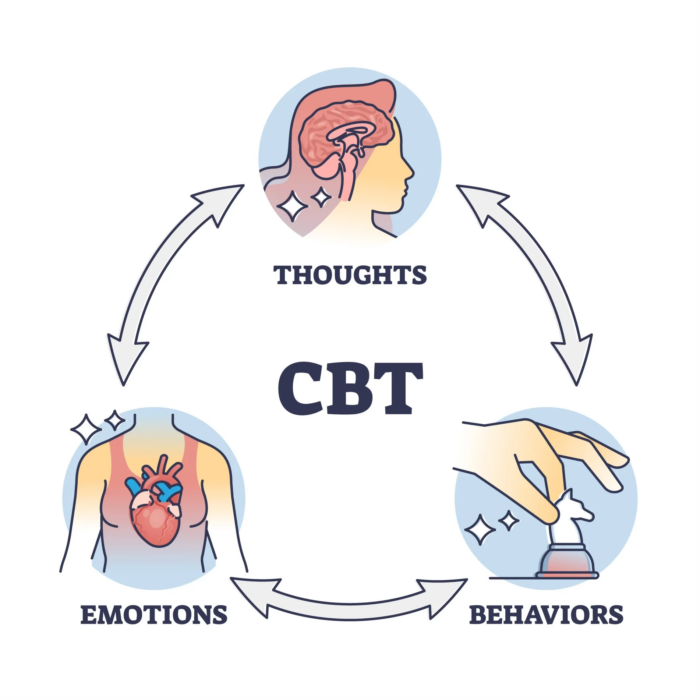
Cognitive behavioral therapy operates on a straightforward principle: your thoughts shape your emotional and behavioral responses. This isn't philosophy. It's measurable. When I worked with clients dealing with severe anxiety disorders, the pattern became clear within three sessions. The person would report a physical panic attack, describe the racing heart and shortness of breath, then trace it back to a specific automatic thought. Usually something like "I'm going to fail" or "Everyone is judging me." The connection between the thought and the physiological response was direct and repeatable. I spent years teaching this model to new therapists. The hardest part wasn't explaining the concept. It was getting people to actually record their thoughts in real time. Most wanted to skip straight to restructuring. They'd say something like "just tell me how to stop thinking negatively." But the method requires patience. You need the data before you can change anything.
What Principle Underlies Cognitive Behavioral Therapy
The fundamental principle is the cognitive model. Thoughts mediate between situations and responses. Not situations themselves. The thoughts about those situations. This distinction matters clinically. Two people can experience the same event and have completely different reactions based on their interpretation. A traffic jam becomes rage for one person, neutral for another. The event didn't change. The appraisal did. Beck developed this framework in the 1960s while studying depression. He noticed patients had rapid, involuntary thoughts before emotional shifts. Called them automatic thoughts. These pop into awareness without conscious effort. You can catch them with training. The standard technique involves thought records. Clients write down the situation, the emotion, the automatic thought, and then evaluate evidence for and against the thought. This process usually takes 10 to 15 minutes per entry. Not quick. Worthwhile. There's a common misconception that CBT is about positive thinking. It's not. The goal is accurate thinking. Sometimes the most adaptive thought is you genuinely might fail at something. Recognizing that possibility reduces catastrophic projections. Hope isn't a clinical strategy. Calibration is.
How the Method Actually Works
Sessions typically run 50 minutes. Frequency is weekly. Duration depends on the disorder. Simple phobias might resolve in six sessions. Complex trauma cases require months. I once worked with a client who had OCD driven by contamination fears. Standard exposure hierarchy would have worked for typical cases. His presentation was atypical. He feared not just germs but the concept of impermanence itself. Cleaning wasn't about hygiene. It was about controlling an uncontrollable reality. We had to modify the protocol. The principle remained the same. Thoughts drive behavior. The application required adjustment. We tracked the automatic thoughts differently. Instead of contamination scenarios, we tracked the underlying existential appraisal. "If I don't clean, everything falls apart." That thought felt true. It wasn't empirically true. Testing it required behavioral experiments over weeks. The client would touch a doorknob and wait. Initially the anxiety spiked to 9 out of 10. Eventually it dropped. Not because the doorknob became clean. Because the predicted catastrophe didn't occur. This is the active ingredient. Not insight. Not catharsis. Disconfirmation. The nervous system learns through experience that certain feared outcomes don't materialize. The cognitive piece provides the framework. The behavioral piece provides the proof. Remove either component and outcomes degrade significantly.
Get the Full Details

I've seen therapists focus too much on the cognitive restructuring. They spend sessions debating thoughts. The client leaves feeling heard but unchanged. The method requires action. Thinking about changing your thinking doesn't change your thinking. Doing something different does. Homework isn't optional. It's the primary vehicle for change.
Pitfalls and Limitations
CBT has boundaries. It assumes adequate cognitive functioning. Severe intellectual disability, acute psychosis, untreated bipolar mania often contraindicate standard protocols. The method also struggles with conditions where thoughts aren't the primary driver. PTSD requires trauma processing that pure cognitive work doesn't provide. Some clinicians try to adapt CBT for complex PTSD. Results are mixed. Evidence favors phase-based treatment. Safety and stabilization first. Trauma processing second. Cognitive restructuring third. The format demands structure. Clients who prefer open-ended exploration often resist the directive style. They want to talk about their childhood. CBT acknowledges history but focuses on maintaining factors. The rationale explanation takes 10 minutes. Compliance depends on buying into that rationale. If the client rejects the model, nothing else follows. Another limitation: thought records create artificial awareness. Some clients report that tracking thoughts increases rumination initially. The monitoring itself becomes a compulsion. I've seen this with obsessive personalities. They started recording thoughts and then analyzing every mental event. The behavior shifted from obsessive cleaning to obsessive journaling. Same underlying pattern. Different symptom expression. The treatment requires ongoing monitoring for iatrogenic effects.
There's also a cultural dimension. The emphasis on individual cognition assumes a certain psychological framework. Collectivist cultures may prioritize relational harmony over personal belief restructuring. Applied uniformly, CBT can pathologize normal cultural variations in thought patterns. A therapist working across cultures needs to distinguish between dysfunctional beliefs and culturally normative appraisals.
Technical Details for Practitioners
The Socratic dialogue technique requires skill. Asking guiding questions instead of providing interpretations. Beginners tend toward interrogating. "What evidence do you have?" comes across as challenging. Skilled practitioners frame it collaboratively. "Let's examine this thought together. What would support it? What might contradict it?" The difference affects engagement. Session length averages 50 minutes. Between-session practice should be specified in writing. Verbal homework assignments have compliance rates around 40 percent. Written assignments rise to 65 percent. Specify the behavior, the context, and the tracking method. Cognitive restructuring follows a sequence. Identify the automatic thought. Evaluate its validity. Generate alternative appraisals. Test the alternative behaviorally. The sequence isn't always linear. Sometimes behavioral testing precedes cognitive work. Exposure without cognitive preparation can trigger dropout. The ratio depends on presentation. Anxiety disorders typically benefit from combined approaches. Depression often responds better to activity scheduling first, then cognitive work. Progress monitoring should use standardized measures. Beck Depression Inventory, Beck Anxiety Inventory, or GAD-7. Baseline, mid-treatment, end-of-treatment. Tracking provides feedback to both therapist and client. Without measurement, progress claims are anecdotal. The data usually shows gradual improvement. Occasional setbacks are normal. A single regression doesn't indicate treatment failure. Look at the trajectory over weeks, not days.
The method works. The mechanism is clear. The application requires technical competence. Training matters. Self-study produces superficial understanding. Supervised practice produces usable skills. The field has enough well-meaning people offering advice based on reading a few books. Clinical work demands more. The principle is simple. The execution isn't.