Understanding Blood Pressure Readings in Practice
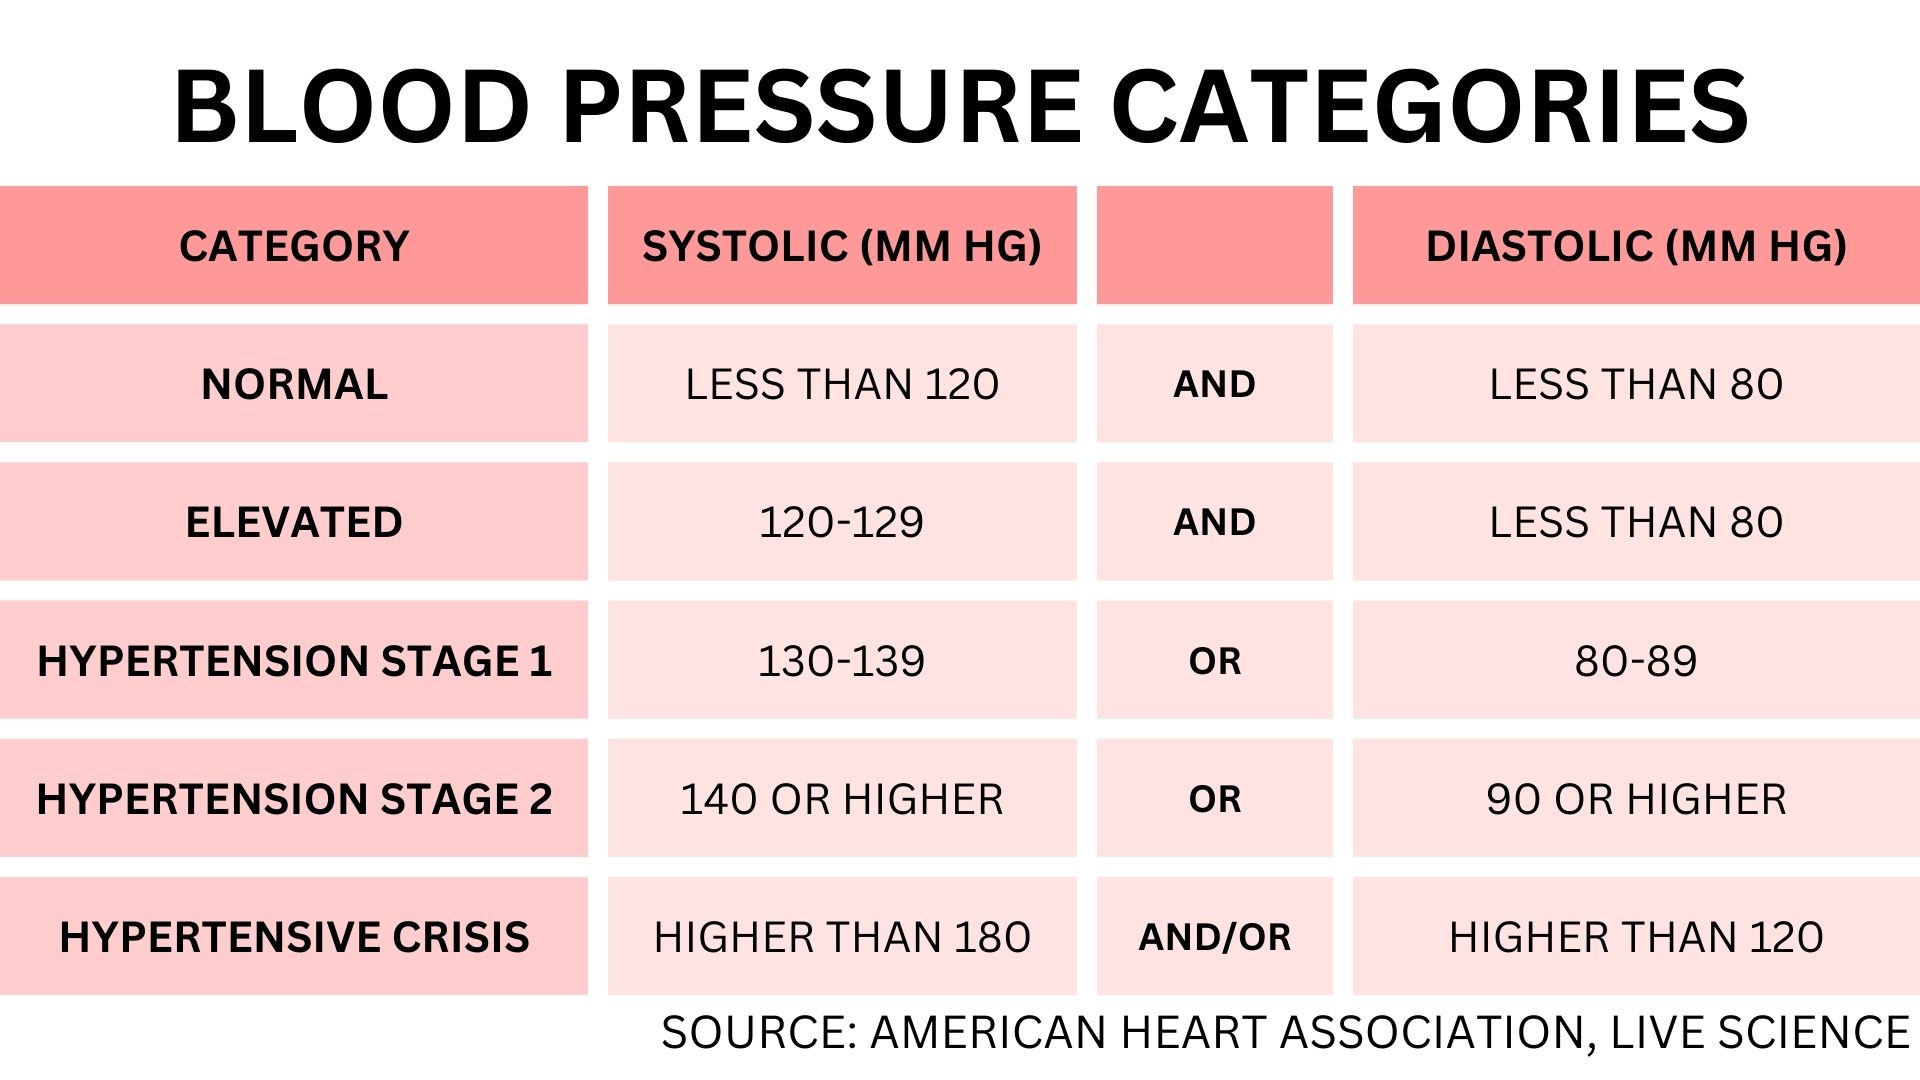
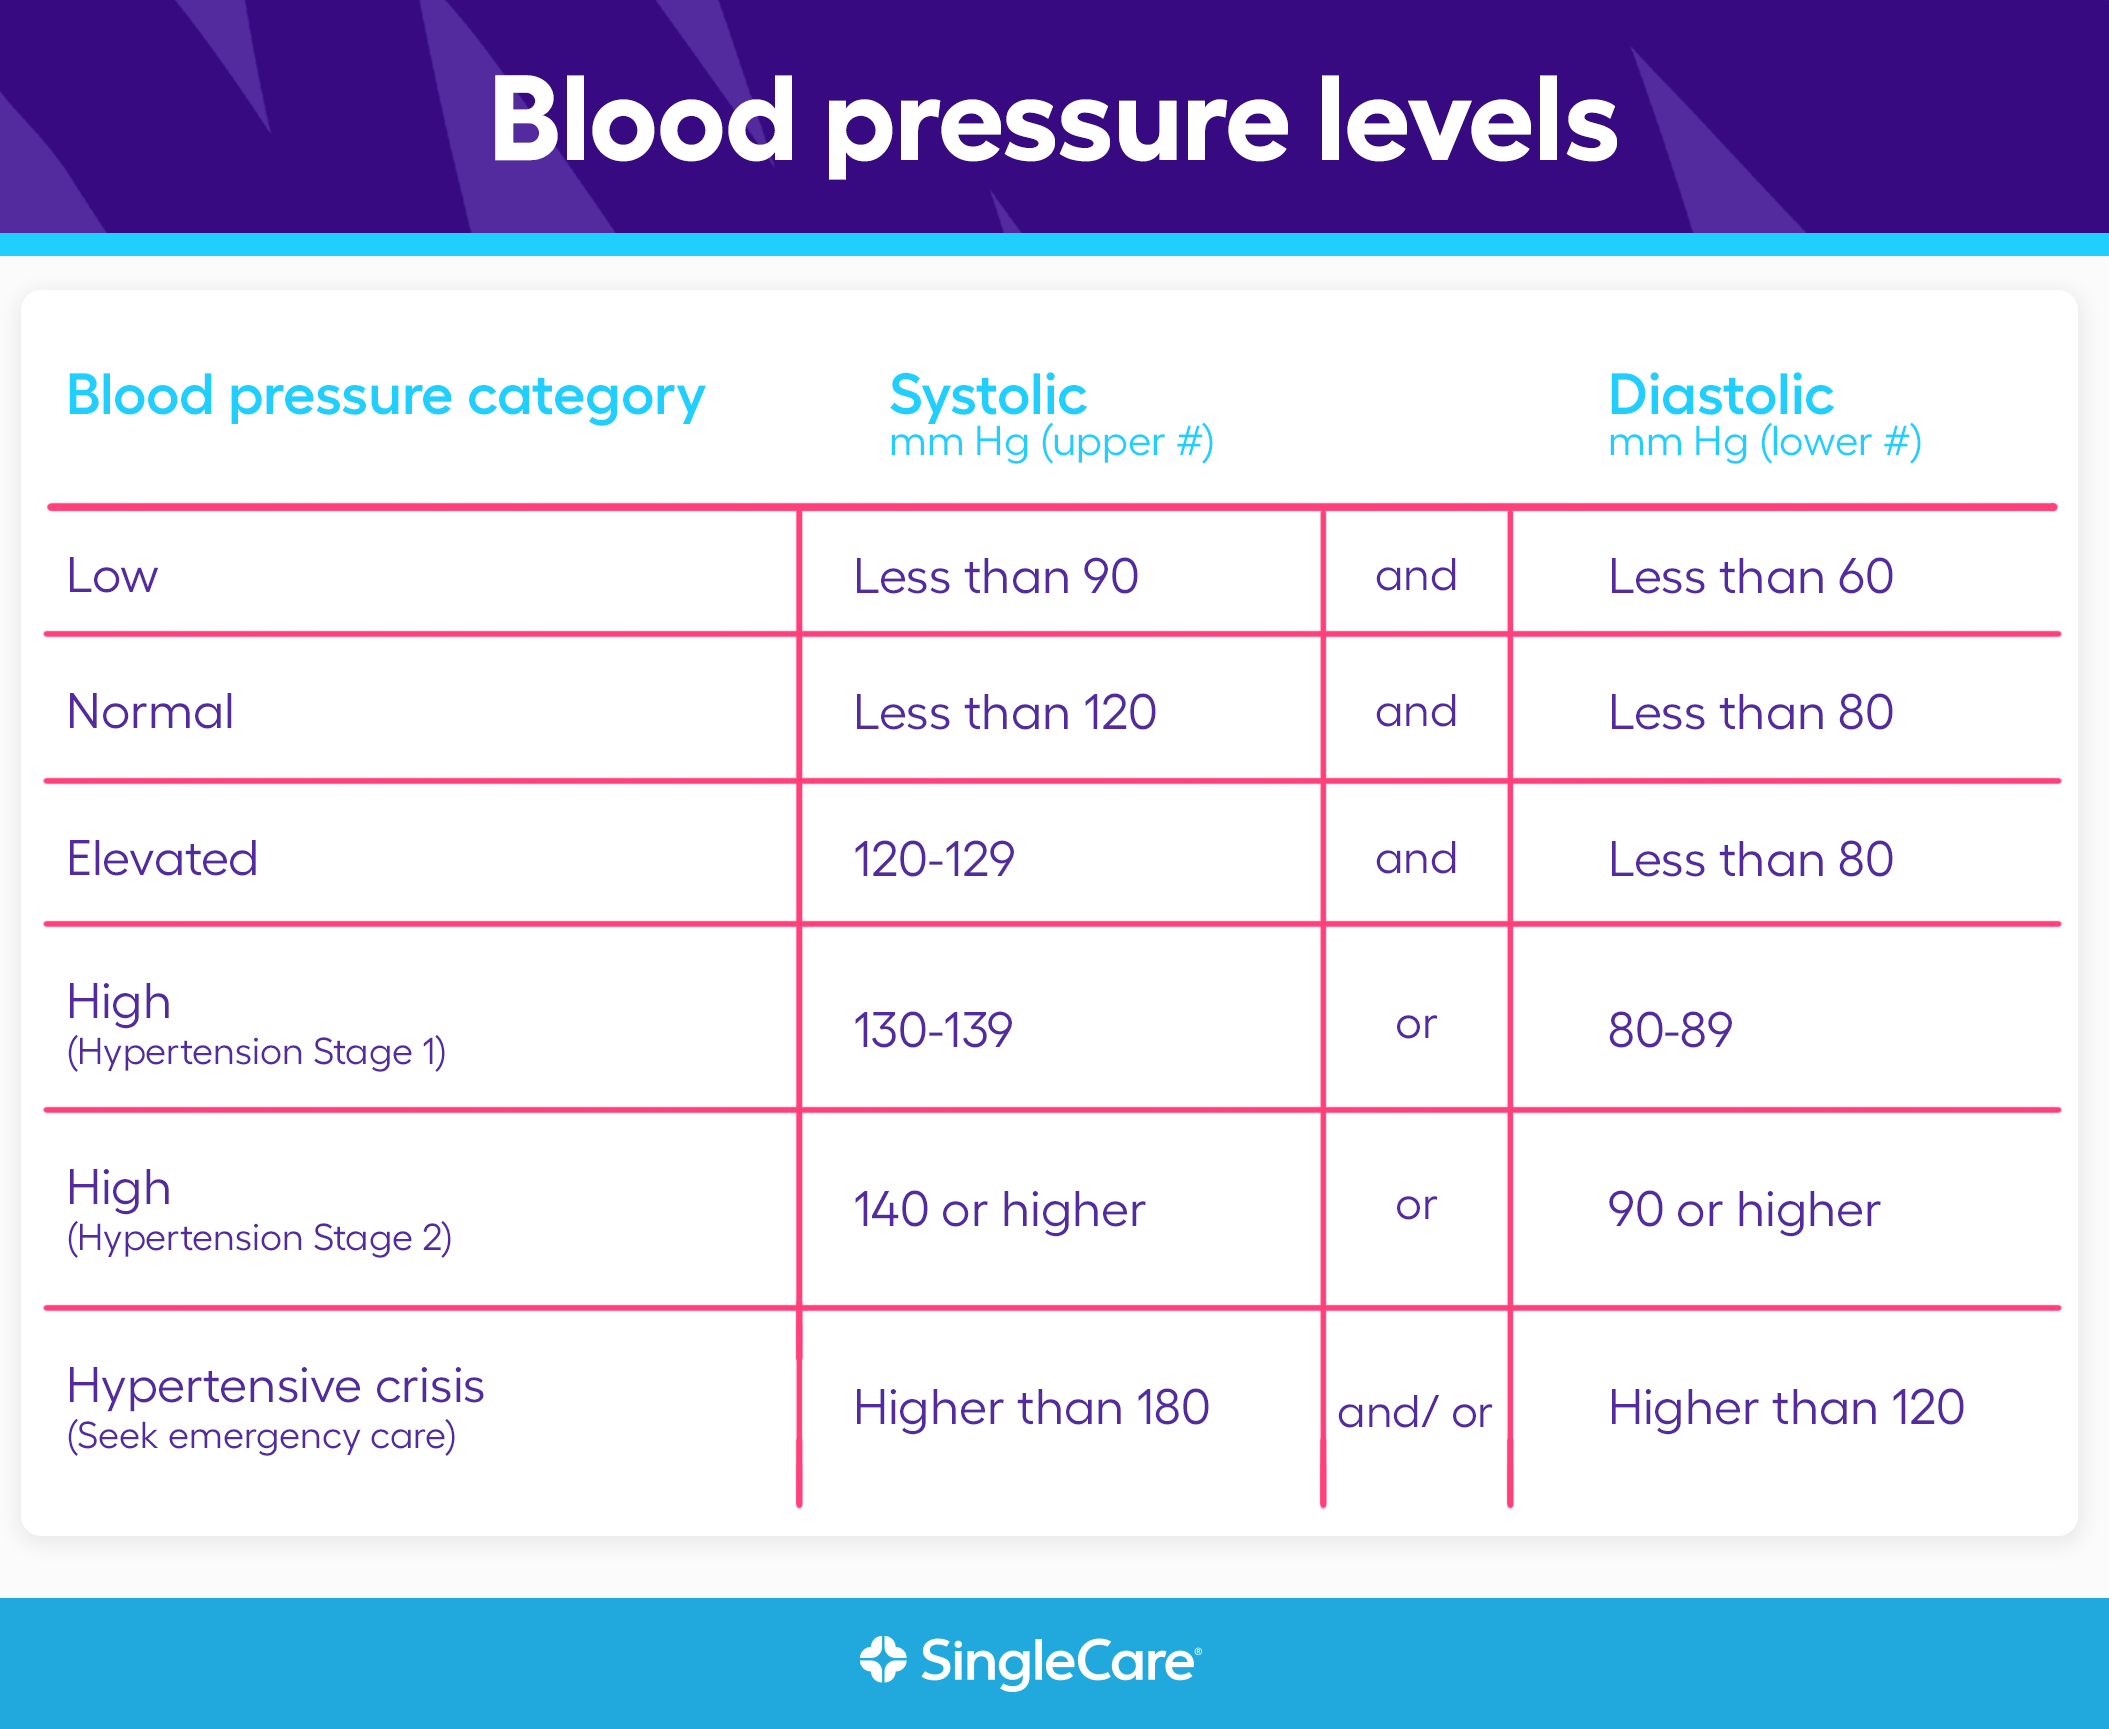
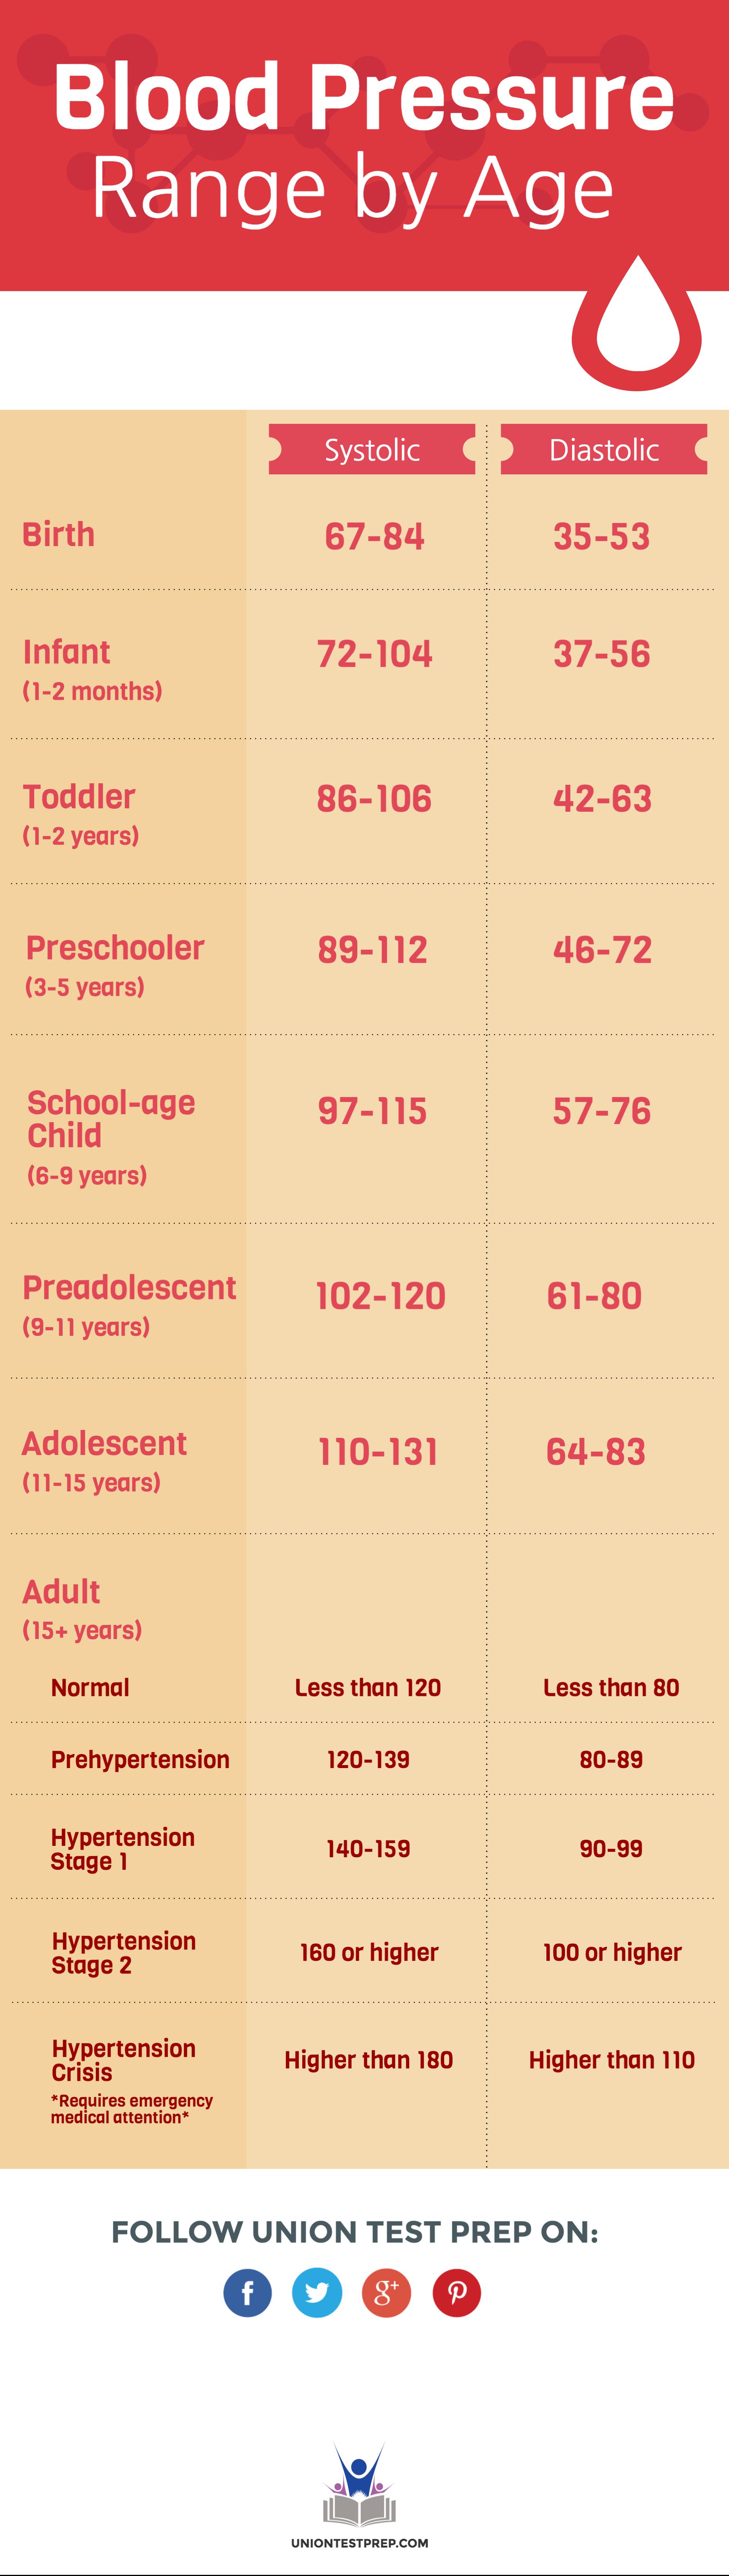
I deal with blood pressure numbers constantly. Every patient who walks through my door gets them checked, and I see a lot of confusion about what those numbers actually mean. The general answer is straightforward: normal blood pressure is below 120/80 mmHg. That's the standard cutoff used by most guidelines globally, though specific thresholds shift depending on which organization you ask and what country you're in. Reading 120/80 is your target, but "normal" isn't a single fixed point. It covers a range. Anything under 120 systolic and under 80 diastolic falls into the normal category. Elevated starts at 120-129 with a diastolic still under 80. Stage 1 hypertension kicks in at 130-139 systolic or 80-89 diastolic. Stage 2 is 140 or higher systolic, or 90 or higher diastolic. A hypertensive crisis is anything over 180/120 and needs immediate attention. These ranges are from the American Heart Association and ACC guidelines, which most US-based clinicians follow. Other regions sometimes use slightly different cutoffs, which is why you might see references to 140/90 as a threshold in some places. The systolic number is the pressure in your arteries when your heart contracts. The diastolic is the pressure when your heart rests between beats. Both matter. In fact, for people over 50, systolic pressure is often considered the more important indicator of cardiovascular risk. That's a detail a lot of patients don't know, and it explains why older adults can have elevated readings even when their diastolic looks fine.
When I measured blood pressure manually for years using a mercury sphygmomanometer, I saw firsthand how much variation exists between people and even within the same person on the same day. Blood pressure fluctuates throughout the day based on stress, activity, caffeine intake, pain, and even bladder fullness. A single reading is almost never enough to make a diagnosis. Most guidelines now recommend at least two or three separate readings on different occasions before labeling someone hypertensive. Home monitoring over several days tends to give a more accurate picture than a single office visit. I once had a patient whose office readings consistently read around 145/92, which would normally qualify as stage 2 hypertension. But when I had them bring in a home monitor and keep a log for a week, their average readings dropped to around 125/78. This was a textbook case of white coat hypertension, where the anxiety of being in a clinical setting artificially inflates the numbers. I've seen the reverse too, where someone looks fine in the office but their home readings tell a different story, which is called masked hypertension and can be just as dangerous since it goes undetected. For anyone wanting to take accurate readings at home, there are a few things that actually matter more than most people realize. Sit quietly for five minutes before measuring. Keep your feet flat on the floor, back supported, and arm resting at heart level. Don't talk during the measurement. Use a validated upper-arm cuff, not a wrist monitor, because wrist devices are significantly less reliable and more sensitive to positioning errors. The cuff size matters too, and I can't stress this enough, a cuff that's too small for your arm will give falsely high readings. If you have larger arms and you're using a standard adult cuff, that's likely skewing your numbers upward without you knowing it.
There are also medications and supplements that can interfere with readings. Decongestants, NSAIDs like ibuprofen, certain antidepressants, and even herbal supplements like ginseng can raise blood pressure. If you're monitoring at home and notice a sudden shift, review what you've been taking recently before jumping to conclusions. One common pitfall I see repeatedly is people taking their blood pressure right after coming in from outside, after smoking, or immediately after a meal. None of these are appropriate conditions for an accurate reading. Wait at least 30 minutes after eating, exercising, smoking, or consuming caffeine before checking. The readings won't be trustworthy otherwise. Another thing worth noting is that the concept of "normal" has shifted over time. The 2017 ACC/AHA guidelines lowered the threshold for hypertension from 140/90 to 130/80, which immediately classified millions more people as hypertensive. Some clinicians argued this was overly aggressive and would lead to unnecessary medication. Others said it reflected better evidence about when cardiovascular risk actually begins to climb. The reality is somewhere in between, and different organizations haven't fully aligned on the new thresholds. If your doctor mentions a diagnosis, it's reasonable to ask which guideline they're using and whether watchful waiting with lifestyle changes might be appropriate before starting medication.
Get the Full Details

There's also the matter of hypotension, or low blood pressure, which gets far less attention but can be just as problematic. Anything below 90/60 is generally considered low, and while some people run naturally low without symptoms, others experience dizziness, fainting, fatigue, or poor concentration. Dehydration is the most common cause of low readings, and it's often overlooked because people associate blood pressure problems only with high numbers. Ultimately, understanding what normal blood pressure is, requires looking at the full context rather than fixating on a single number. If your readings are consistently in the hypertensive range, don't ignore them, but also don't panic over one bad reading. Take multiple measurements across different days under consistent conditions. Bring that data to your doctor. The pattern matters far more than any single data point.