Understanding Your Blood Pressure Readings
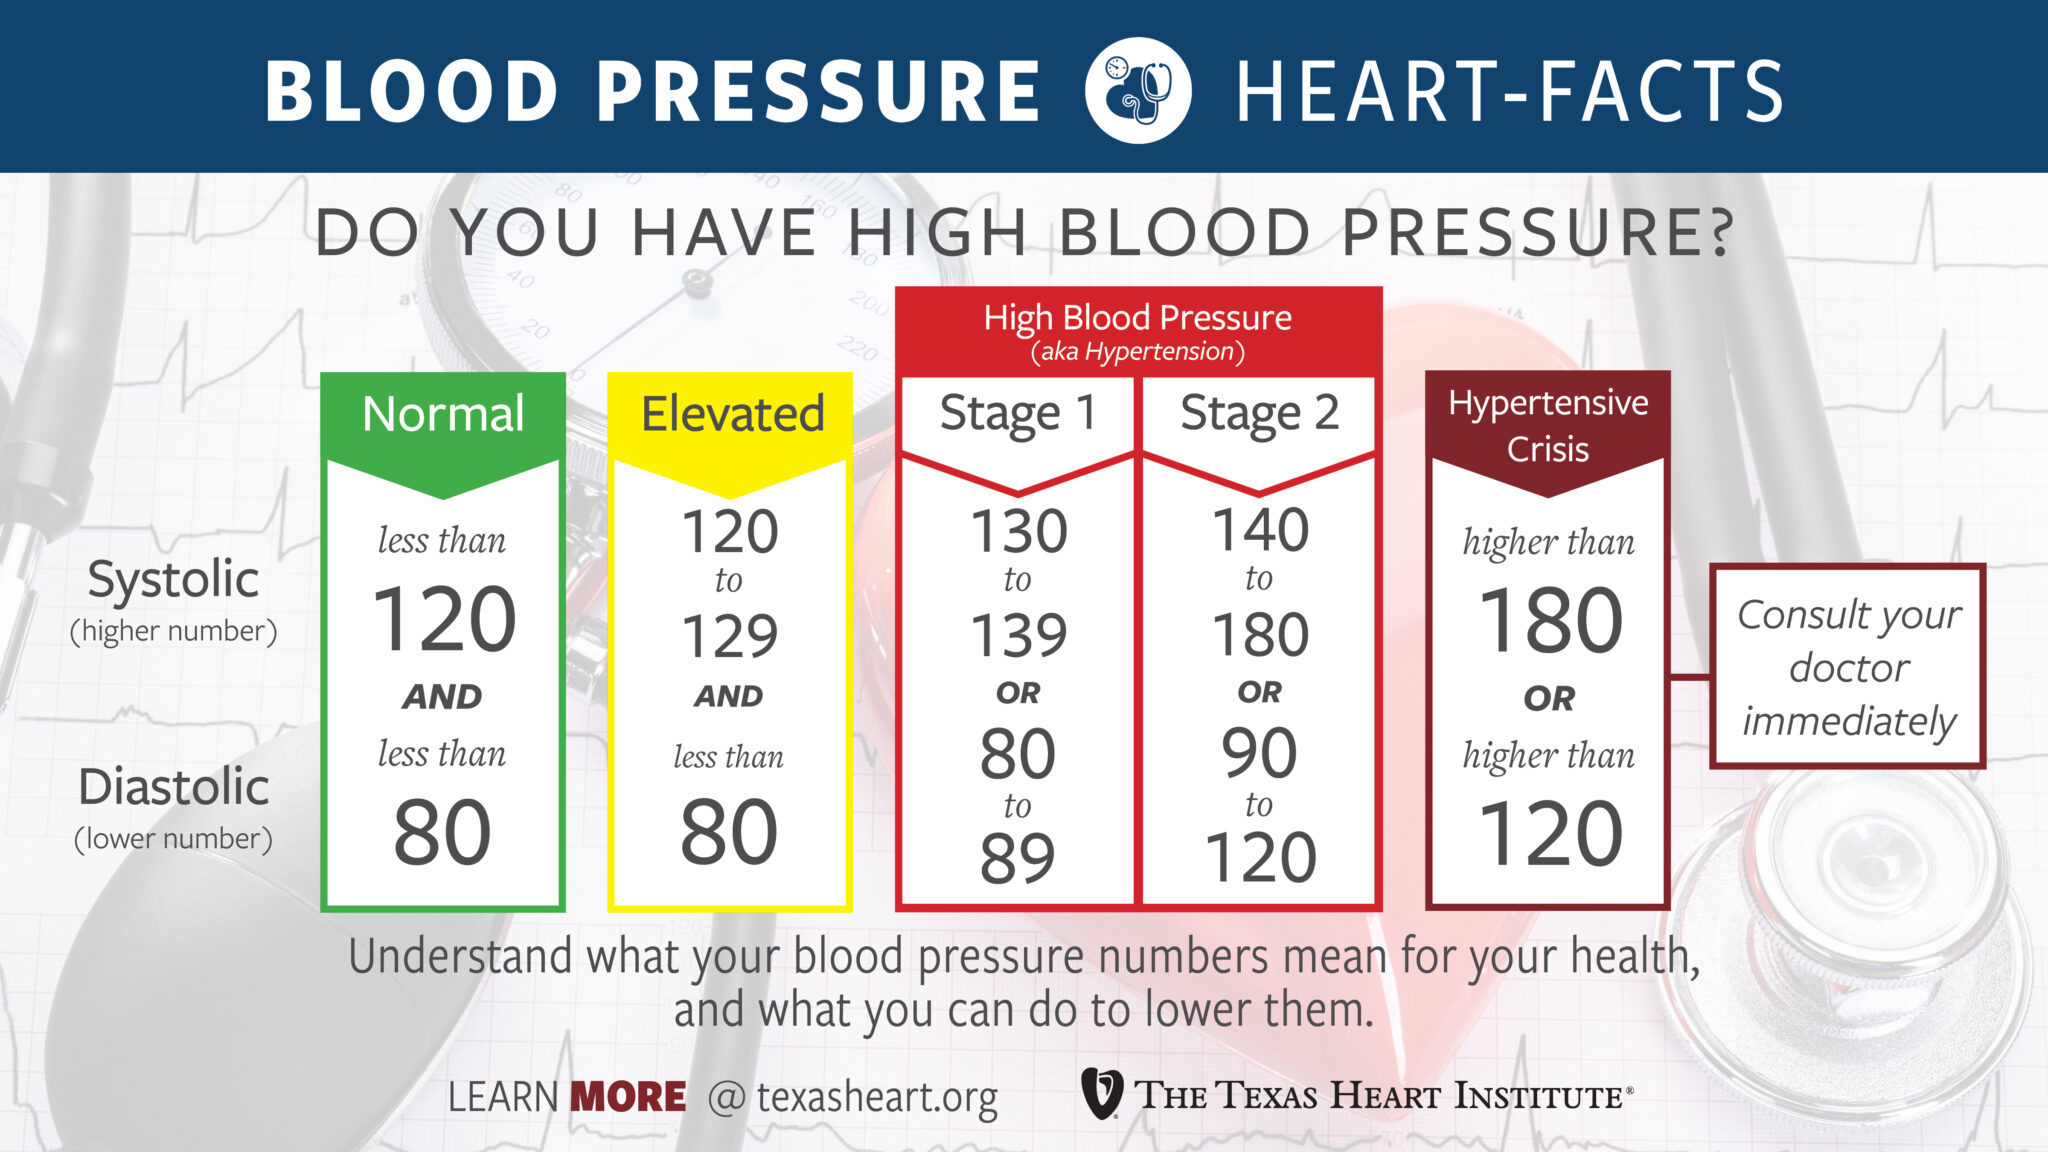
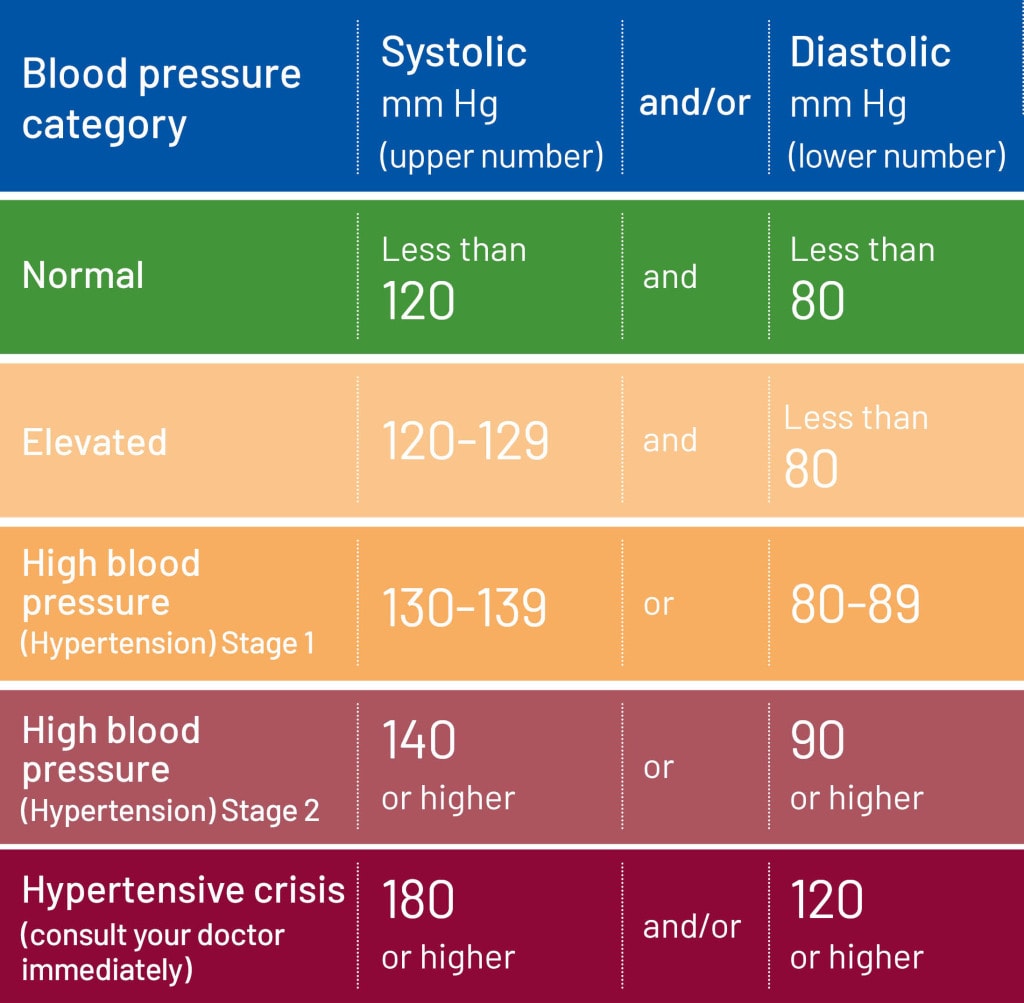
Blood pressure is just the force of blood pushing against artery walls. It changes constantly. When you walk up stairs, it goes up. When you sleep, it drops. Most people get confused because they see wildly different numbers on different days and assume something is wrong. Usually nothing is wrong. The standard categories are straightforward: normal sits below 120 over 80, elevated is 120 to 129 with a diastolic under 80, stage one hypertension ranges from 130 to 139 or 80 to 89, and stage two is 140 plus or 90 plus. These numbers come from the American Heart Association guidelines published in 2017, and they haven't changed much since. The problem isn't the definitions. The problem is how most people measure.
What Should Your Blood Pressure Be
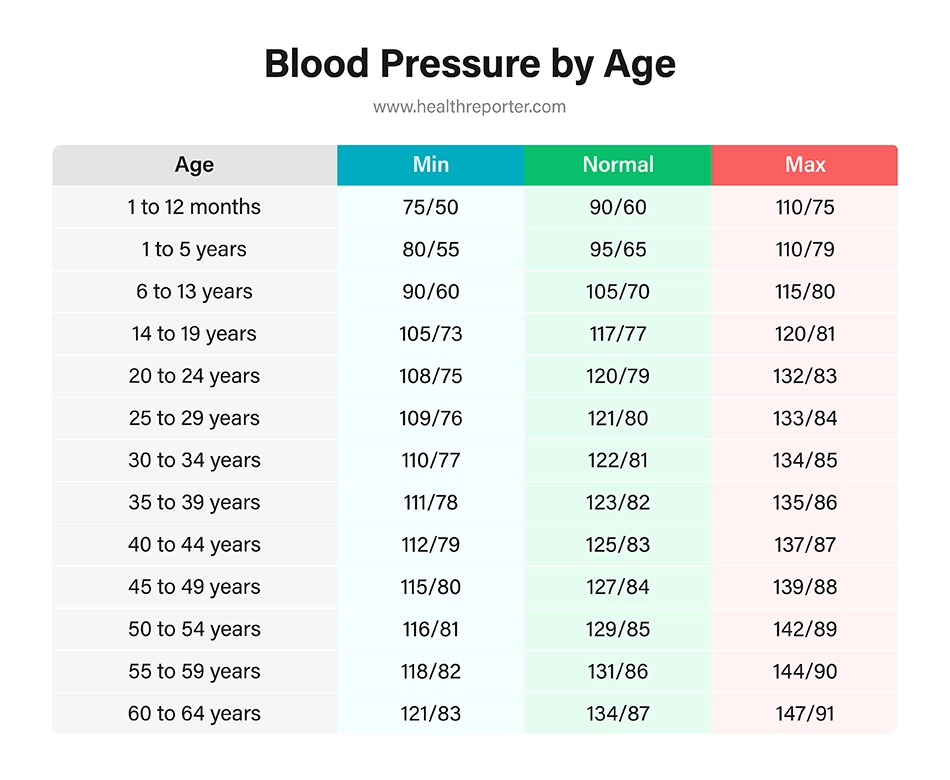
If you're an average adult without existing cardiovascular disease, you're looking at a target below 130 over 80 for treatment purposes. For most people in their fifties and sixties, that's the number clinicians actually care about based on the SPRINT trial data. Going lower isn't always better though. In patients over 80 with significant comorbidities, aggressive blood pressure lowering actually showed increased risk of falls and kidney injury without clear mortality benefit. Here's what nobody tells you about home monitoring: the first reading is almost always wrong. Not wrong as in broken, wrong as in inflated. When you first put the cuff on, your body hasn't settled. Your sympathetic nervous system is still reacting to the process itself. I measured my own blood pressure for a clinic visit once and got 148 over 92 on the first try, then 126 over 78 on the second, then 122 over 76 on the third. My doctor asked me which one to trust. I told him to average the last two. That's the standard protocol. You need to sit for five minutes before taking a reading. Feet flat on the floor. Back supported. Arm resting on a surface at heart level. Don't talk during the measurement. Don't check your phone. The cuff inflation itself triggers a stress response that can add ten to fifteen points to your systolic if you're not careful. I learned this the hard way during a hypertensive urgency workup where my readings bounced between 155 and 175 over 95 and 105 depending on whether the nurse was in the room. Once I had her step out and the automated machine take the reading, it came back at 132 over 81. The white coat effect is real and it's not just psychological, it's physiological.
Another thing people miss: cuff size matters more than almost anything else. A standard adult cuff on a larger arm will give you a falsely low reading by several points. An undersized cuff on a thick arm can add twenty or more to your systolic. I had a patient whose initial readings suggested stage two hypertension, but when we switched to a large adult cuff, his readings dropped into the elevated range. The difference was purely mechanical. Make sure your cuff bladder wraps around at least eighty percent of your upper arm circumference.
Get the Full Details
How to Actually Measure Correctly
Buy an upper arm monitor with a validated listing. Wrist monitors and finger monitors are generally unreliable unless you're in a situation where upper arm measurement is impossible. The British Hypertension Society and the Association for the Advancement of Medical Instrumentation both publish validation lists online. Look for your device on one of those lists before you buy it. Devices that aren't validated systematically overread or underread by enough to change clinical decisions. Take two readings in the morning and two in the evening for seven consecutive days. Discard day one and average the rest. This gives you roughly fourteen data points that filter out random variation and acute stress events. Most people who do this correctly find their actual baseline is significantly lower than their occasional home readings suggest. The few who find it's higher than they expected are the ones who catch problems early. There's a specific edge case that trips people up: atrial fibrillation. If you have an irregular heartbeat, most home monitors will either give you an error or a wildly inaccurate number. I dealt with this personally when my own monitor kept flagging errors during a period of palpitations. The device assumes regular rhythm for its oscillometric measurement algorithm. When the rhythm is irregular, the algorithm breaks. The workaround was switching to a manual sphygmomanometer with a stethoscope at the clinic, which took the readings by auscultation rather than oscillometry. If you have known arrhythmia, don't trust your home monitor for diagnostic purposes. Get periodic manual checks.
Another practical detail: take readings at the same time each day. Cortisol follows a circadian pattern, and blood pressure naturally runs highest in the late morning and earliest morning. Evening readings tend to be lower. Comparing a 7 AM reading to a 7 PM reading from a different day is meaningless. Track consistently and look at trends, not single numbers.
When to Worry and When Not To
A single reading above 180 over 120 with symptoms like chest pain, shortness of breath, neurological changes, or severe headache is an emergency. Go to the hospital. Without those symptoms, a single high reading is not an emergency even if it's in that range. It's called a hypertensive crisis but the actual term clinicians use is severely elevated blood pressure, and the management is almost never immediate admission. It's medication adjustment and follow-up within days. The biggest mistake I see is people starting or stopping medications based on a week of home readings. Blood pressure medication isn't designed to normalize your reading today. It's designed to reduce long-term cardiovascular risk over decades. A good antihypertensive regimen might not bring your numbers down to "normal" on paper but it still dramatically reduces stroke and heart attack risk. Conversely, some medications cause orthostatic hypotension where your pressure drops too much when you stand up. That's more dangerous than a slightly elevated sitting reading, especially in older adults. If you get dizzy when you stand, that's worth mentioning to your doctor even if your sitting numbers look fine. There's also the issue of masked hypertension, where your clinic readings are normal but your home readings are high. It's surprisingly common and it carries similar cardiovascular risk to sustained hypertension. If your office readings are always fine but you have risk factors like diabetes or chronic kidney disease, ask your doctor about ambulatory blood pressure monitoring. That twenty-four hour wrap-around test catches this and it's far more predictive of outcomes than any single office reading.
On the flip side, some people fixate on getting below 120 over 80 and push their medication hard to get there. For most people, the marginal benefit of going from 125 to 115 systolic is small compared to the side effects you accumulate. Your doctor should be managing this tradeoff, not you chasing a number. The goal isn't perfection. The goal is reducing risk without compromising your quality of life. One more thing about lifestyle: salt sensitivity varies enormously between individuals. Some people can eat a pound of salt a day and their blood pressure doesn't budge. Others drop five to ten points just by cutting back to normal sodium levels. There's no cheap at-home test for this. The only way to know is to try a two-week reduced sodium diet and track your average home readings. If they don't change, salt isn't your lever. Move on to exercise, weight management, or alcohol reduction, which affect most people regardless of sodium status.