Proton Therapy Is Everywhere, But That Doesn't Mean It's Accessible
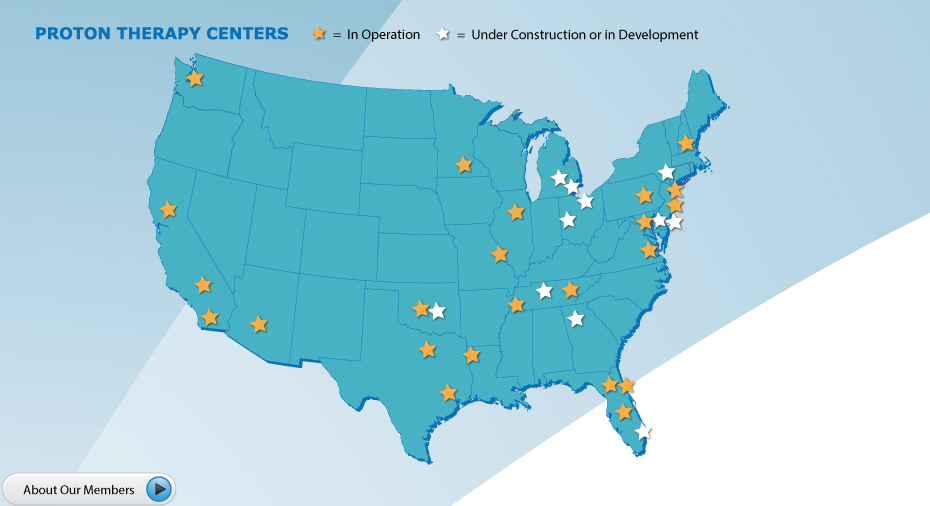
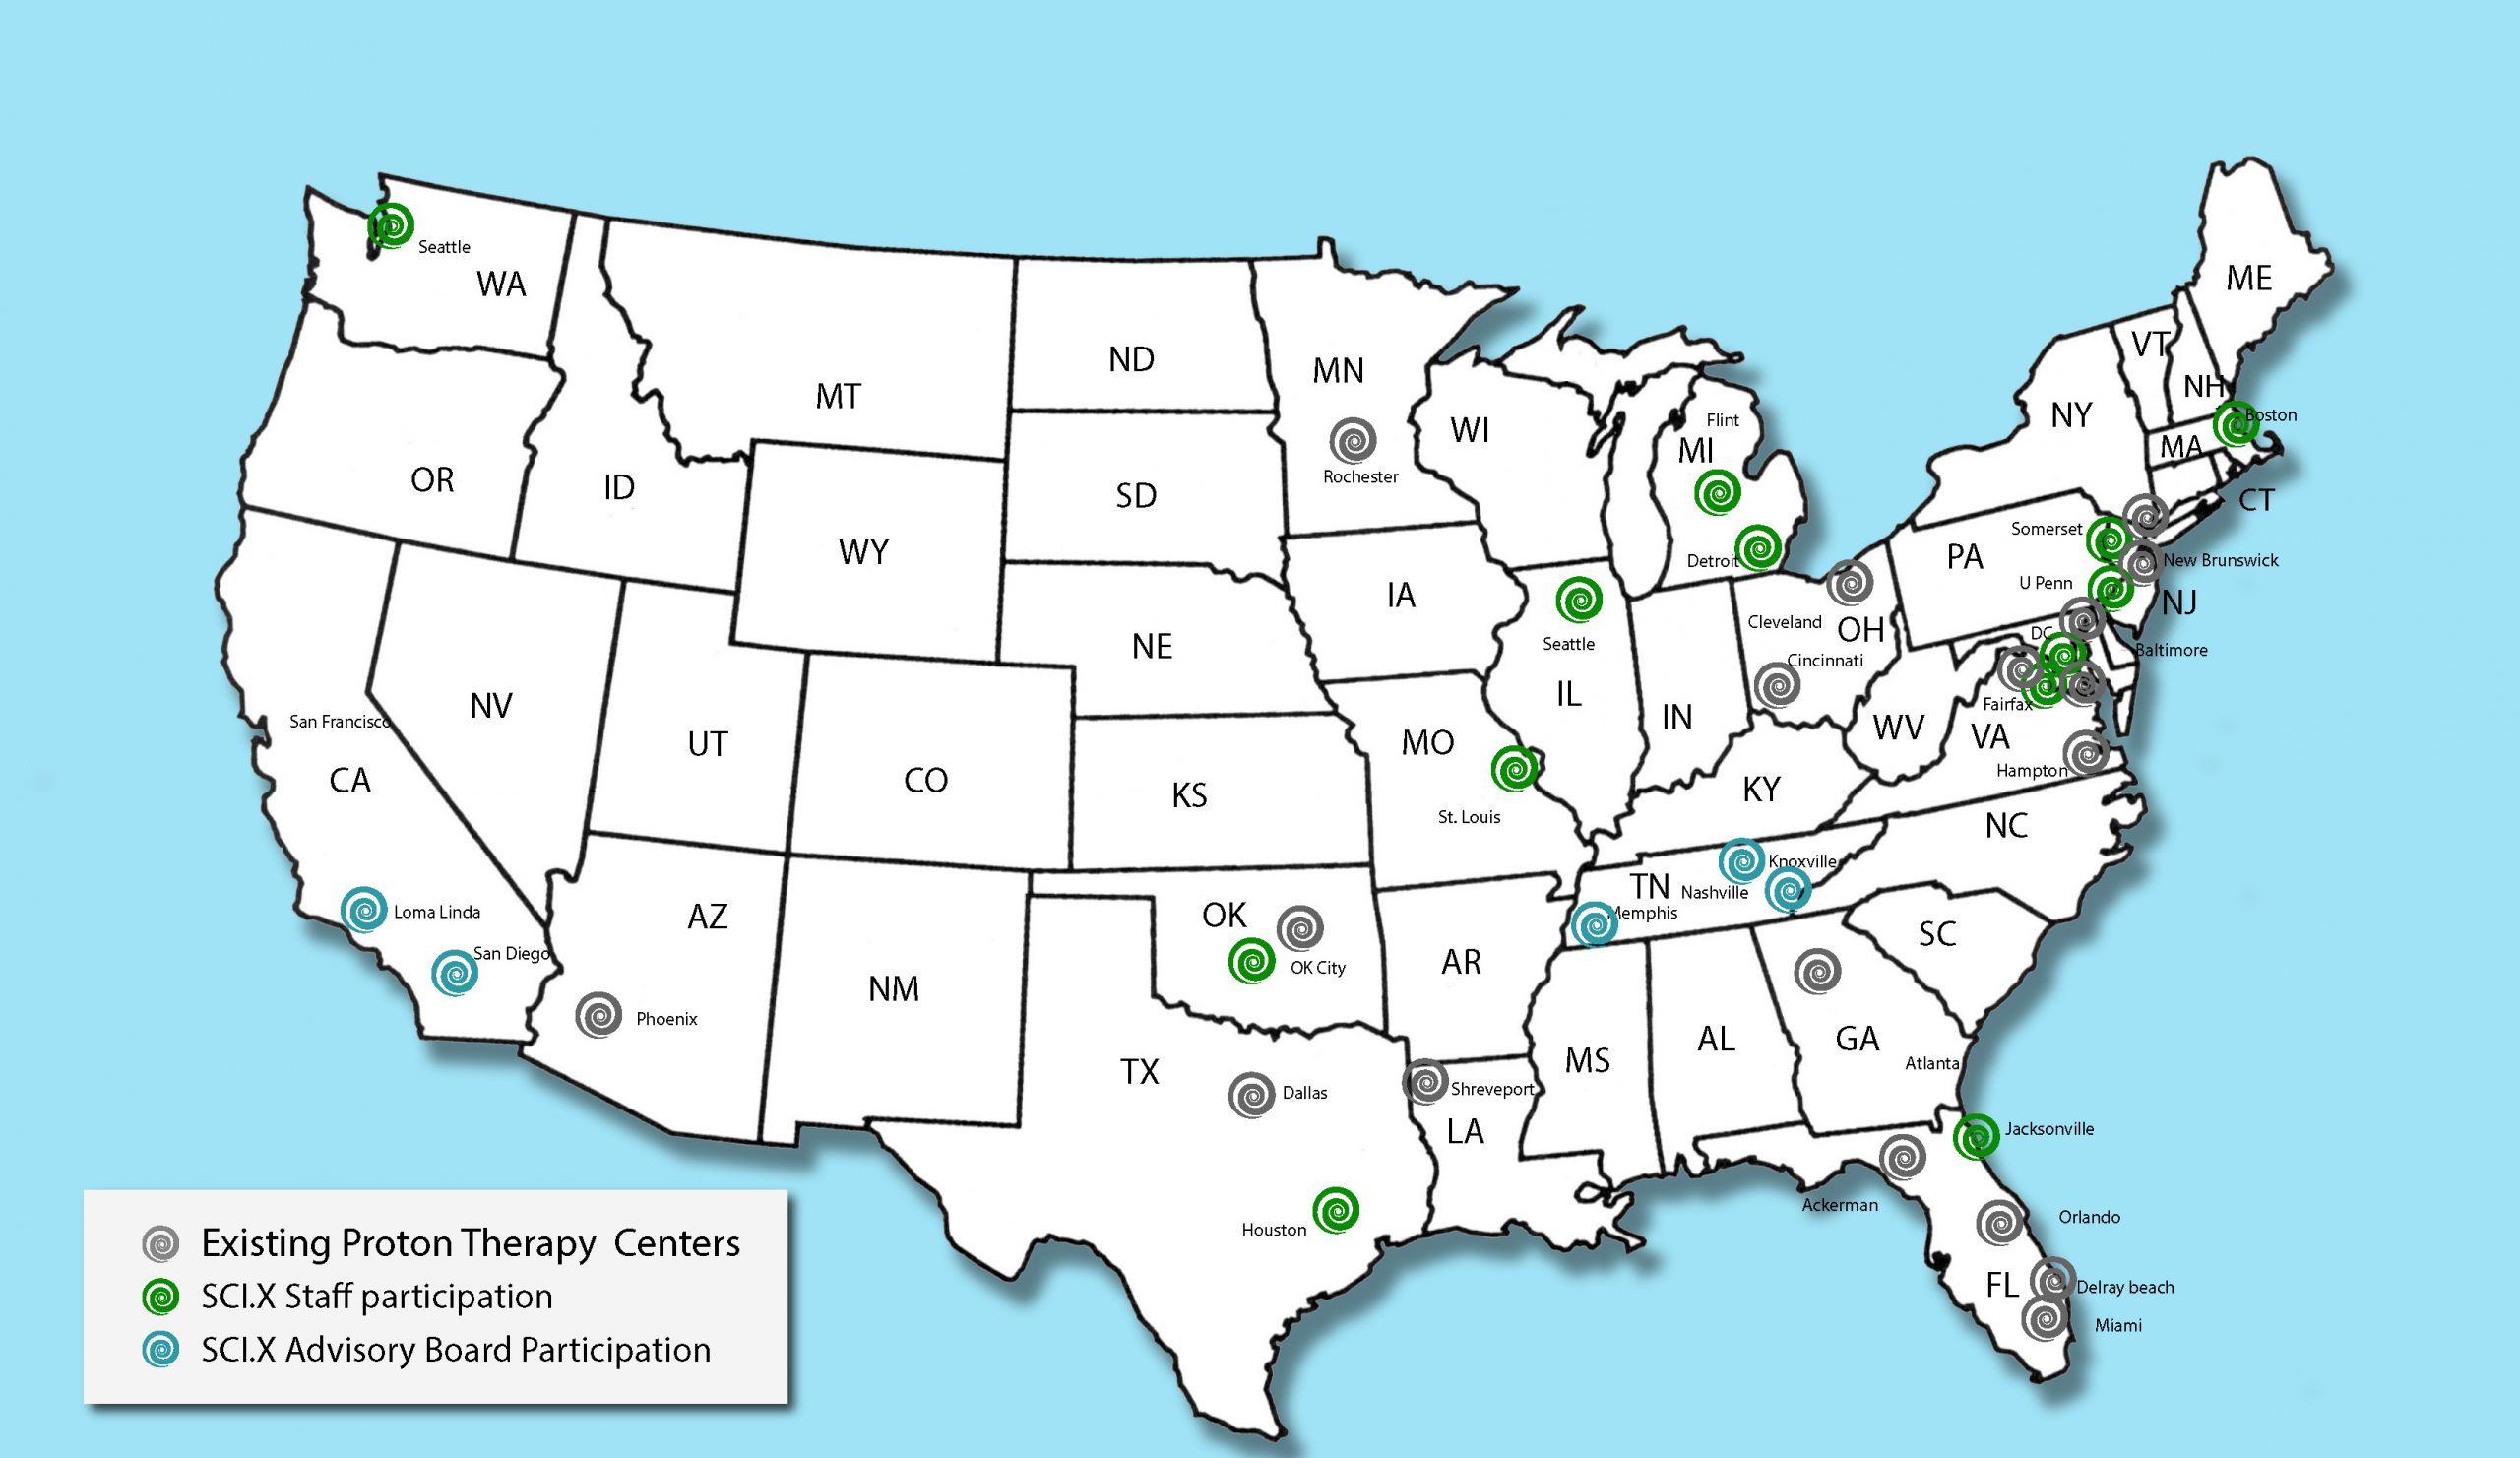
There are over 50 proton therapy centers across the United States, spread across roughly 30 states. The technology has been around long enough that most major cancer care networks have one nearby, but "nearby" is doing a lot of heavy lifting here. The reality of getting treated at one of these centers involves more than just geography. It involves insurance authorization, clinical eligibility, travel logistics, and the fact that many of these machines are booked solid. When people ask what states have proton therapy, they're usually trying to figure out whether they can get it close to home. The honest answer is that it depends on where you live and what kind of cancer you're being treated for. Let me walk through how this actually works in practice, because the brochure version of proton therapy is pretty different from the real-world version.
What States Have Proton Therapy — And Who Actually Uses Them
I've coordinated referrals to proton centers for patients over the years, and the pattern is pretty consistent. The states with the most options tend to be the ones with major academic medical centers: California, Texas, Florida, New York, Pennsylvania, Illinois, Massachusetts, Michigan, and North Carolina all have multiple facilities. But having a center in your state doesn't mean you'll get a slot there next week. The Midwest and parts of the Southeast and Southwest are underserved relative to their populations. If you live in states like Oklahoma, Kansas, Nebraska, or much of the Mountain West, you're likely looking at a multi-state trip for treatment. I've had patients drive four hours each way, twice a day, for six weeks. That's not uncommon in rural areas without a local center. Some centers are part of hospital systems and some are standalone. The standalone ones often have longer wait times because they're dependent on referral volume from external oncologists. Hospital-affiliated centers tend to move faster but may prioritize their own patients first.
How the Referral Process Actually Works
Getting to a proton therapy center starts with a referral from your radiation oncologist. Not every oncologist will make that referral, and that's a problem. Many general radiation oncologists are more comfortable with conventional photon therapy because that's what they trained on and what they use every day. Proton therapy requires a specific justification — usually that the dosimetric advantage is clinically significant for the tumor site. That threshold is higher than patients expect. For certain cancers, the evidence is strong. Pediatric tumors, skull base cancers, ocular melanomas, and some sarcomas have solid data supporting proton use. For prostate cancer, the data is mixed and the cost differential is enormous. For breast cancer, it's mostly relevant for left-sided cases where heart sparing matters, and even then, modern photon techniques have closed the gap significantly. My rule of thumb when evaluating whether a patient should pursue proton is to ask two questions: Is there peer-reviewed literature supporting protons for this specific cancer type and stage? And would avoiding a specific organ at risk change the long-term outcome, not just the short-term side effect profile? If the answer to both is yes, then the referral makes sense. If it's no, you're paying a lot more money for something that may not improve your prognosis.
Get the Full Details

Insurance and Cost Are the Real Bottlenecks
Proton therapy costs roughly twice as much as photon therapy. The machine alone runs somewhere between $100 million and $250 million to install. Operational costs are high too. This gets passed through to insurers, and insurers push back. Prior authorization is not a formality — it's a gate that many patients don't get through on the first try. I've seen insurance companies deny proton therapy for pediatric brain tumors, which seems absurd but happens. The denial letters usually cite "insufficient evidence" or "experimental." You appeal. The appeal requires a letter from the treating physician citing specific studies, sometimes case law, and a dosimetric comparison showing the proton plan versus the photon plan side by side. That dosimetric comparison is something the proton center's physics team generates, and it typically takes 3 to 5 business days. If you're already dealing with an insurance delay, that's another week gone. Medicare covers proton therapy when it meets their criteria, which generally aligns with NCCN guidelines. Commercial insurance varies wildly by plan and by state mandate. Some states require coverage; others don't. If you're self-pay, expect to be quoted $30,000 to $70,000 depending on the treatment site and complexity. Some centers offer financial assistance programs, but they're not advertised prominently.
The Scheduling Problem Nobody Talks About
Even after insurance approves the treatment, getting a start date can take weeks. Proton centers are busy. A single gantry can treat maybe 10 to 15 patients per day, and many centers run two or three gantries at most. During peak seasons, wait times of 4 to 8 weeks are normal. For aggressive tumors, that's a meaningful delay. I ran into this personally last year with a patient who had a recurrent skull base chordoma. The photon re-irradiation window was closing, and the nearest proton center had an 8-week wait. I contacted the center directly, explained the clinical urgency, and asked if they had any cancellations or early openings. They did — a patient had dropped out two weeks in. We moved her up, and the treatment started 3 weeks after approval instead of 8. The workaround here is simple but easily overlooked: call the center's scheduling office directly. Don't rely on your referring oncologist's office to track this down. The referral goes in, and then you're in a queue. Being proactive about scheduling can cut that wait by half.
Travel and Logistics During Treatment
Proton therapy is typically delivered over 1 to 9 weeks depending on the condition, with daily sessions Monday through Friday. If you're traveling from out of state, you need to plan for either temporary housing near the center or very long daily drives. I've seen patients split the difference — they fly in a few days before treatment starts for simulation and setup, stay in nearby Airbnb housing for the duration, and fly back after treatment is complete. The simulation visit is critical. That's when they create the CT scan and the treatment plan. It takes about 1 to 2 hours. You'll get custom immobilization devices — masks, molds, positioning aids — that you'll wear for every treatment session. If you're traveling, make sure you account for this visit carefully because it determines your entire treatment timeline. Some centers offer virtual care follow-ups after treatment concludes, which helps if you're far away. But the initial planning and treatment delivery require in-person visits. There's no remote option for the actual therapy.

When Proton Therapy Doesn't Make Sense
Here's the part that gets less attention. Proton therapy is not automatically better. For many cancers, the clinical outcomes are equivalent between protons and photons. The advantage is in reducing dose to surrounding healthy tissue, which matters most when you're treating near critical structures or when you're treating children whose bodies are still developing and have decades of potential side effects ahead of them. For a localized prostate cancer in a 70-year-old, the difference in long-term toxicity between protons and modern photon techniques like IMRT or VMAT is measured in fractions of a percent. The cost difference is tens of thousands of dollars. I've recommended against proton therapy in these cases more often than I've recommended it, and my patients have generally been glad I did. The data doesn't support spending extra money for marginal benefit. Similarly, if a tumor is far enough from critical organs that photon dose spill-off won't cause problems, protons add cost without meaningfully changing the outcome. The Bragg peak — that's the physics principle behind protons, where they deposit most of their energy at a specific depth and then stop — is beautiful in theory, but in practice, the clinical advantage depends entirely on your anatomy and tumor location.
Practical Steps If You're Considering Proton Therapy
Start by asking your radiation oncologist whether protons are clinically indicated for your specific case. If they're unsure, request a second opinion at a comprehensive cancer center that offers both photon and proton therapy. Having both options available at the same institution means the physicists and dosimetrists can generate comparative plans, and you'll get an objective answer about whether the dosimetric advantage is real for your situation. Check your insurance coverage before you get too far along. Call the number on your card and ask specifically about proton therapy authorization requirements. Get the criteria in writing. Then ask the proton center's financial counselor about their experience with your insurer — some centers have established relationships that make authorization smoother. If you qualify and insurance approves, start thinking about travel and lodging early. Some centers have partnerships with nearby hotels or patient housing programs. The American Society for Radiation Oncology maintains a directory of proton therapy centers, and the Proton Therapy Cooperative Group publishes patient resources that explain what to expect.
The state you live in matters less than you might think. Most people with access to a proton center within a reasonable driving distance will find one. Those who don't have options, the system is slow and expensive and not always transparent about whether the technology will actually help. The best approach is to get an independent second opinion from a center that offers both technologies, ask hard questions about the evidence for your specific cancer, and then make a decision based on clinical benefit rather than technology appeal.