Behavioral Therapy isn't what most people think it is
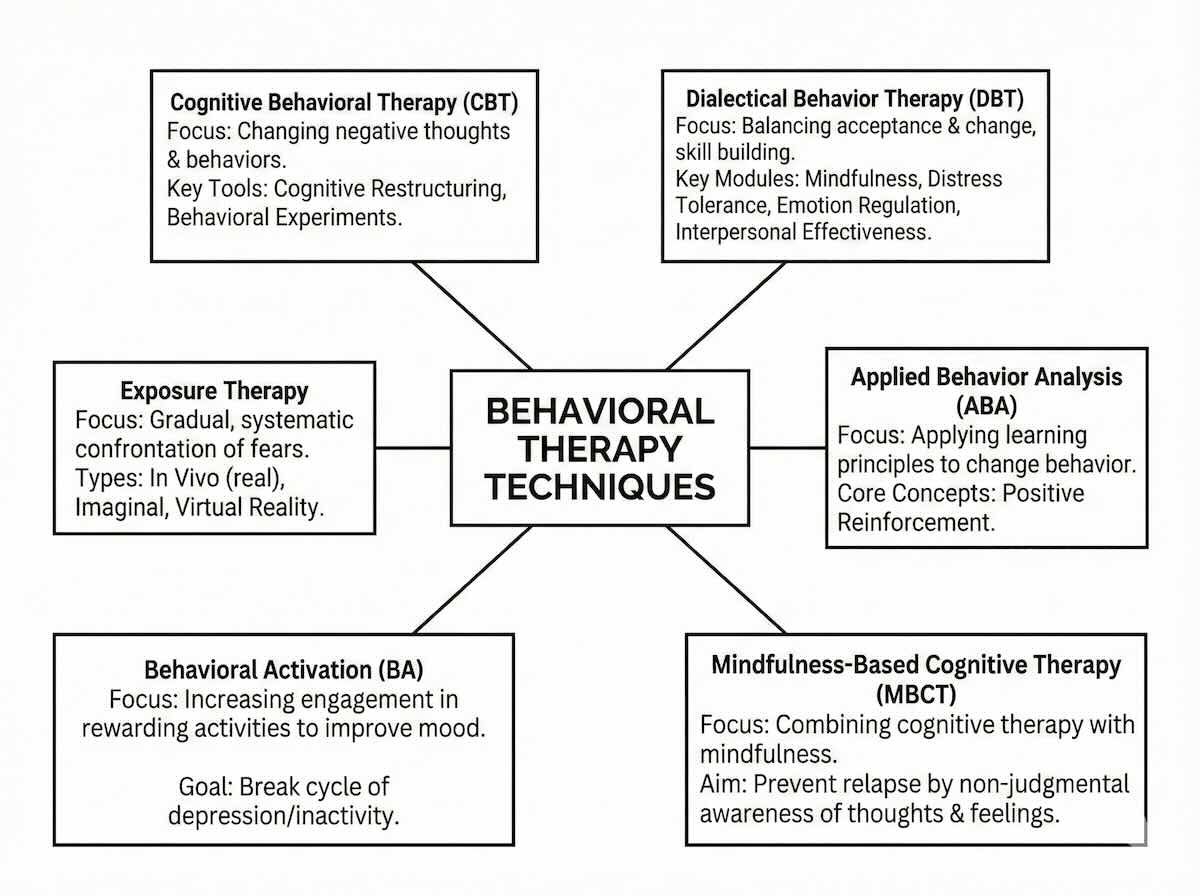
Most folks hear "behavioral therapy" and picture someone gently exploring childhood trauma or reframing thoughts. That's not it. Behavioral therapists don't do much deep-dive into your past or your subconscious. They look at what you're doing, why you're doing it, and how to change the behavior directly. The work is practical, measurable, and usually pretty uncomfortable because you have to actually change your routine, not just talk about changing it. The main toolkit includes exposure therapy, systematic desensitization, cognitive restructuring (though that edges into CBT territory), behavioral activation, skills training, contingency management, and shaping. Let me walk through how these actually work in practice. This is the big one for phobias, OCD, and anxiety disorders. The idea is straightforward: you face whatever triggers your fear or compulsion gradually, repeatedly, until the nervous system habituates. The trick is doing it right. Too slow and it doesn't work. Too fast and you re-traumatize the person. I had a client once who was terrified of elevators after being stuck in one for six hours during a power outage. We did in-vivo exposure starting with just standing near an elevator, then riding it one floor with the therapist, then alone, then building up to multi-floor rides. Standard protocol would suggest starting higher on the ladder, but given the severity of the original trauma, we needed to be methodical. We spent eight weeks on that. Most exposure protocols aim for four to eight sessions for simpler phobias. Trauma-based fears take longer because the conditioning is deeper.
Similar to exposure but paired with relaxation training. You teach the client a relaxation technique first—progressive muscle relaxation, breathing exercises, whatever works—and then gradually expose them to the anxiety-provoking stimulus while they maintain that relaxed state. The principle is counterconditioning: you can't be fully anxious and fully relaxed at the same time. You're essentially overriding the fear response. This was Joseph Wolpe's original work back in the 1950s. It still works for specific phobias but has largely been superseded by direct exposure for many conditions because it takes longer and the results are sometimes less durable. Primarily used for depression. The premise is that depression creates a cycle where you feel bad, so you withdraw, which makes you feel worse. Behavioral activation breaks the cycle by scheduling activities regardless of how you feel. You don't wait for motivation. You act first and let motivation follow. I've seen this work dramatically. A client of mine was bedbound for three weeks during a depressive episode. We started with literally just sitting up in a chair for ten minutes. Then ten minutes walking to the mailbox. Then a five-minute walk around the block. Within six weeks she was back to work. The key is activity scheduling and monitoring. Every single session you review what they did, how they felt doing it, and adjust. Without the monitoring component, it's just someone telling you to get off the couch and it doesn't work. Heavily used in addiction treatment. You structure rewards and consequences to shape behavior. Positive reinforcement for desired behaviors, sometimes negative consequences for unwanted ones. The evidence base here is actually quite strong for substance use disorders. Vouchers for clean drug screens, for example. I worked in a clinic where we ran a contingency management program for opioid use disorder and saw significant reductions in use. The limitation is that maintaining external rewards long-term is expensive and often impractical. Once the voucher system stops, relapse rates climb again. That's why we always paired it with counseling and skills training. Contingency management alone is a bandage, not a cure.
Also called successive approximations. You reinforce small steps toward a target behavior rather than waiting for the whole thing. Used heavily with children, developmental disorders, and behavior modification in general. If a nonverbal child says a single sound toward a word, you reinforce that. Next they say two sounds, you reinforce that. You keep incrementally raising the bar until you reach the goal. It sounds simple and it is simple. But getting the timing right matters a lot. If you reinforce too late or too early, the association breaks. In my experience, the biggest mistake beginners make is moving the criteria up too fast. You want the client succeeding about 80% of the time. If they're failing more than that, you're pushing too hard. Another one people overlook. You modify the environment to reduce triggers for unwanted behavior or add cues for desired behavior. Insomnia treatment uses this heavily—bed is only for sleep, no phones in bedroom, get up if you can't sleep within twenty minutes. Smoking cessation uses it too—remove all ashtrays, lighters, and cigarettes from your environment. It's basically environmental engineering. Simple, cheap, and often underutilized because therapists and clients want to focus on the psychological piece. But half the battle is often just changing what surrounds you. Behavioral therapists use punishment sparingly and usually avoid it entirely for adults. With children it comes up more, but even then the research is clear: punishment suppresses behavior temporarily without teaching replacement skills. You have to pair it with reinforcement of alternative behaviors or it's pointless. Response cost—a fine or loss of privilege—is sometimes used in institutional settings. Token economies in group homes, for example. You earn tokens for desired behaviors and lose them for rule violations. It works in controlled environments but translates poorly to real-world situations where you can't monitor everything.
Get the Full Details

Behavioral therapy is not easy on anyone. The client has to do real work between sessions. That's non-negotiable. Homework assignments aren't optional extras, they're the actual treatment. Dropout rates in behavioral programs are around thirty percent, mostly because people don't want to do the exposure work or the activity scheduling. If you're a therapist, you need to be comfortable being direct and sometimes a little confrontational about compliance. Gentle encouragement doesn't move the needle here. The other thing nobody tells you: behavioral therapy requires precise measurement. You're tracking frequencies, durations, intensities. If you can't measure it, you can't know if your intervention is working. I've seen too many well-meaning therapists skip the tracking because it feels tedious. That's amateur hour. Even a simple daily log of the target behavior changes the quality of your work dramatically. These techniques work best when combined. A typical depression case might include behavioral activation plus stimulus control plus skills training. An anxiety case might involve exposure plus breathing retraining plus cognitive elements. The pure behaviorist approach from the mid-twentieth century is largely historical now. Modern behavioral therapists integrate what works from other traditions while keeping the focus on observable, changeable behavior. That's the short version of what we actually do day to day.