The Actual Path From Fat to Fuel
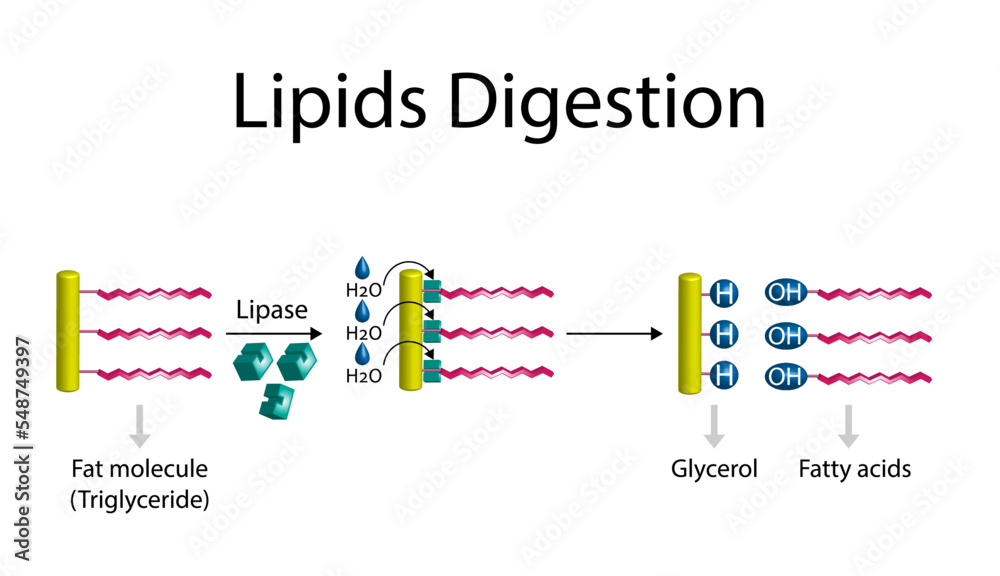
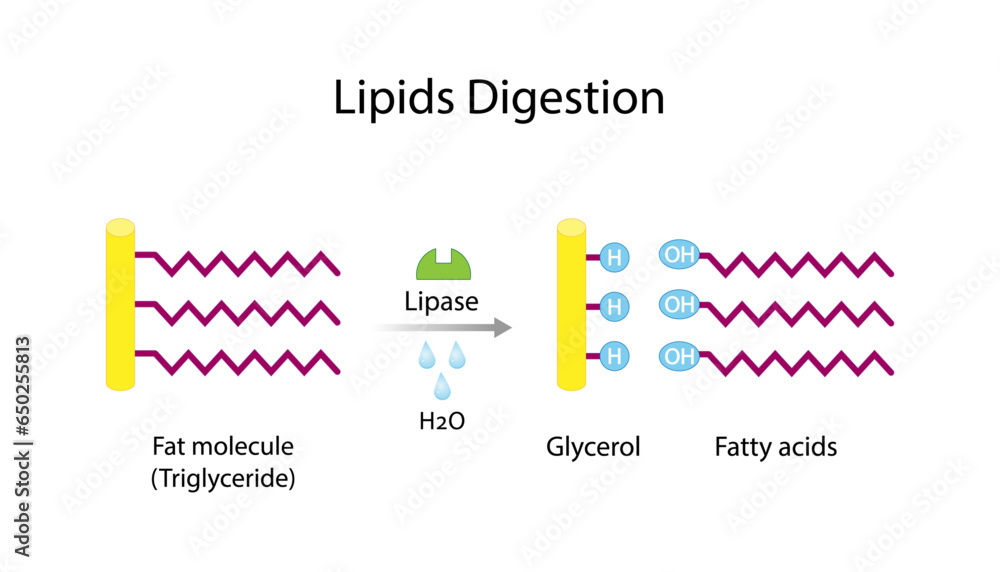
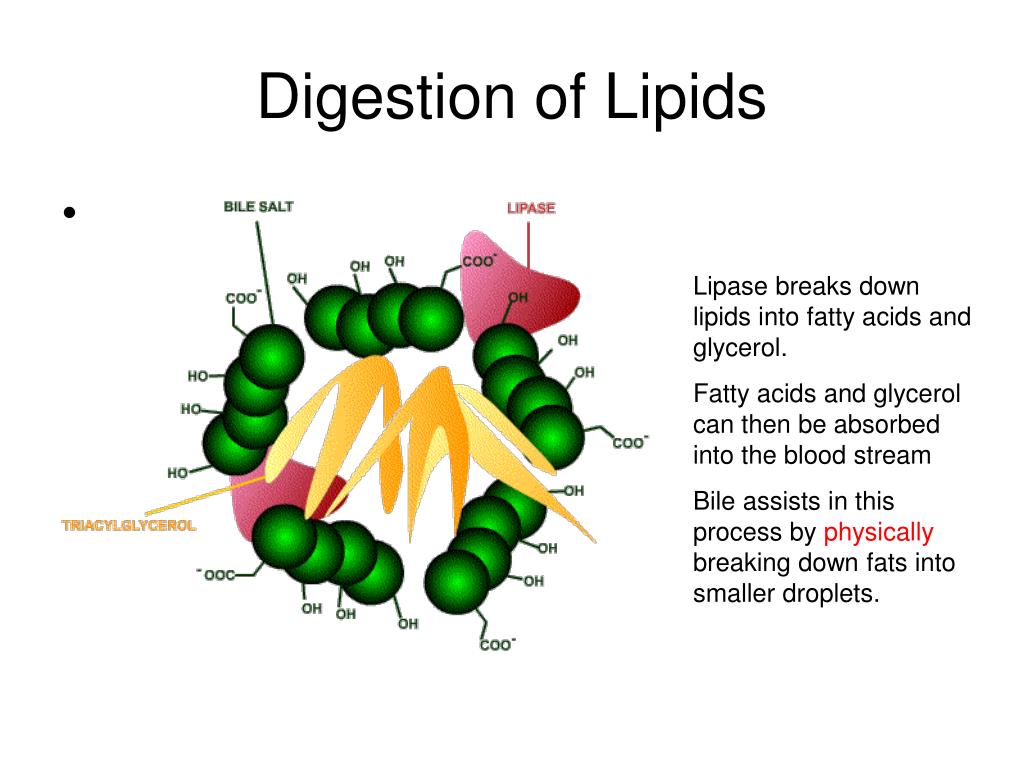
When you eat lipids, your body breaks down triglycerides into free fatty acids and monoglycerides so they can cross the intestinal wall. That's the textbook summary. What happens in practice is messier and more interesting. The process starts in your mouth with lingual lipase, but the real work begins when chyme hits the small intestine. Gastric lipase does some initial breakdown in the stomach, producing partial digests that the pancreas finishes. Pancreatic lipase is the primary enzyme here. It clips fatty acids off the sn-1 and sn-3 positions of the triglyceride backbone. The result is two free fatty acids and one 2-monoglyceride. This doesn't happen in water. It happens at an oil-water interface, which is why bile is essential. Bile salts emulsify the fat globules into tiny micelles. Without that emulsification, pancreatic lipase literally cannot reach the substrate. The surface area problem is the first bottleneck most people miss. A whole fried food item is a single large fat globule. Mechanical breakdown from chewing and gastric mixing helps, but bile does the heavy lifting for emulsification.
I spent weeks troubleshooting a case where a patient had steatorrhea despite normal-looking pancreatic enzyme levels. Turns out the issue wasn't the lipase itself. The patient had compromised bile production due to gallbladder issues. Without adequate bile acids, the triglycerides stayed in large globules and passed through undigested. The workaround was prescription bile acid supplementation taken with meals, which restored emulsification enough to get absorption back to reasonable levels. Pancreatic enzymes alone are not enough if the emulsification step is broken. Once the triglycerides are cleaved into fatty acids and monoglycerides, they get packaged into mixed micelles along with cholesterol and fat-soluble vitamins. These micelles are small enough to diffuse through the unstirred water layer lining the intestinal epithelium. The enterocytes then reassemble those components into chylomicrons inside the smooth endoplasmic reticulum. Here's something beginners consistently overlook. The re-esterification of monoglycerides back into triglycerides inside the enterocyte happens on the SER membrane. This isn't just packaging. It's a necessary step because free fatty acids are membrane-disruptive. If they stayed free inside the cell, they'd compromise lipid bilayer integrity. The body reassembles them into triglycerides specifically to avoid that problem before shipping them out.
Chylomicrons enter the lymphatic system through lacteals, not the bloodstream directly. This is why dietary fats take longer to appear in circulation compared to carbohydrates. The lymph route means they have to travel through the thoracic duct before entering systemic circulation via the subclavian vein. That's roughly a 30 to 90 minute delay depending on the meal composition and individual physiology. Long-chain fatty acids follow the chylomicron pathway. Medium-chain and short-chain fatty acids bypass this entirely. They go straight to the portal vein and travel to the liver without needing emulsification or re-esterification. MCT oil works this way, which is why it's useful in conditions where fat absorption is compromised. But MCTs also hit the liver faster, which means less control over their oxidation rate and a higher chance of gastrointestinal distress if you dose too high too quickly. The practical implication here matters more than the biochemistry trivia. If you're managing blood lipid profiles or dealing with malabsorption issues, the chain length of the fats you consume determines the entire routing system. Standard dietary fats use the lymphatic route. MCTs use direct portal transport. They behave like completely different substances in the body despite both being labeled "fats."
Get the Full Details
Pancreatic lipase has a pH optimum around 8.0. It stops working efficiently in acidic environments. This is why conditions that reduce bicarbonate secretion from the pancreas cause fat malabsorption. The duodenal pH needs to be neutralized before lipase can function. Proton pump inhibitors and other acid-reducing medications can indirectly impair fat digestion by keeping the intestinal environment too acidic for optimal enzyme activity. Gastric bypass surgery changes the fat handling landscape entirely. The reduced stomach size limits mechanical breakdown. More importantly, the bypassed duodenum means less bile mixing and less pancreatic enzyme delivery to the food stream. Patients frequently develop fat-soluble vitamin deficiencies and must supplement aggressively. The anatomical rearrangement makes the normal triglyceride breakdown cascade fundamentally inefficient. Fiber intake also interacts with this process. Soluble fiber can bind bile acids and increase their fecal excretion. When bile acid pools are depleted, less bile is available for emulsification. This can reduce triglyceride digestion efficiency. That's why high-fiber diets sometimes require increased fat intake to compensate, or why adjusting fiber timing relative to meals matters for people managing malabsorption.
The whole system has redundant pathways precisely because fat digestion failures are metabolically expensive. Losing calories through steatorrhea is costly. The body will upregulate bile production, increase lipase secretion, and alter gut motility to prioritize fat absorption when it detects fat malabsorption. But these compensations have limits and come at the expense of other processes. Genetic variations in the PNPLA2 gene affect hormone-sensitive lipase activity, which matters more for intracellular lipid mobilization than dietary triglyceride digestion. Still, the same enzyme class handles both dietary fat processing and adipose tissue breakdown. Some genetic variants that reduce enzyme efficiency show up as both faster weight loss difficulty and slightly reduced fat absorption from food. The clinical significance is debated but the overlap is real. For most people eating a standard diet with normal digestive function, this process works without any conscious adjustment. The system is robust and self-correcting. When it breaks down, identifying which step failed requires looking beyond just pancreatic enzymes. Bile production, intestinal pH, gut motility, and fiber intake all feed into the efficiency of triglyceride breakdown. Pinpointing the actual bottleneck is usually more useful than assuming enzyme supplementation solves everything.