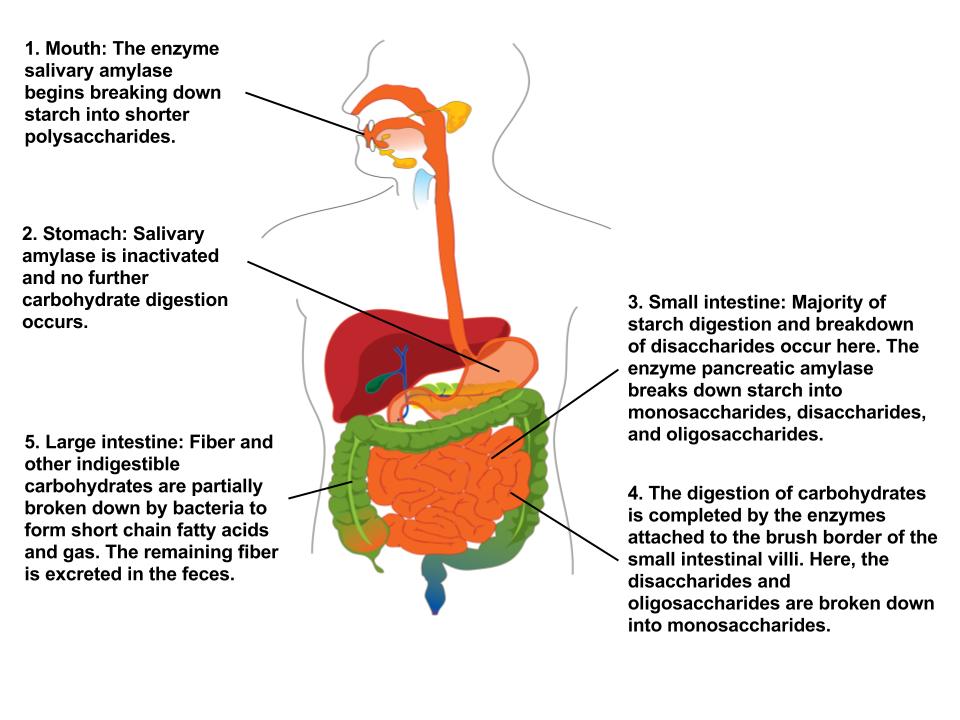
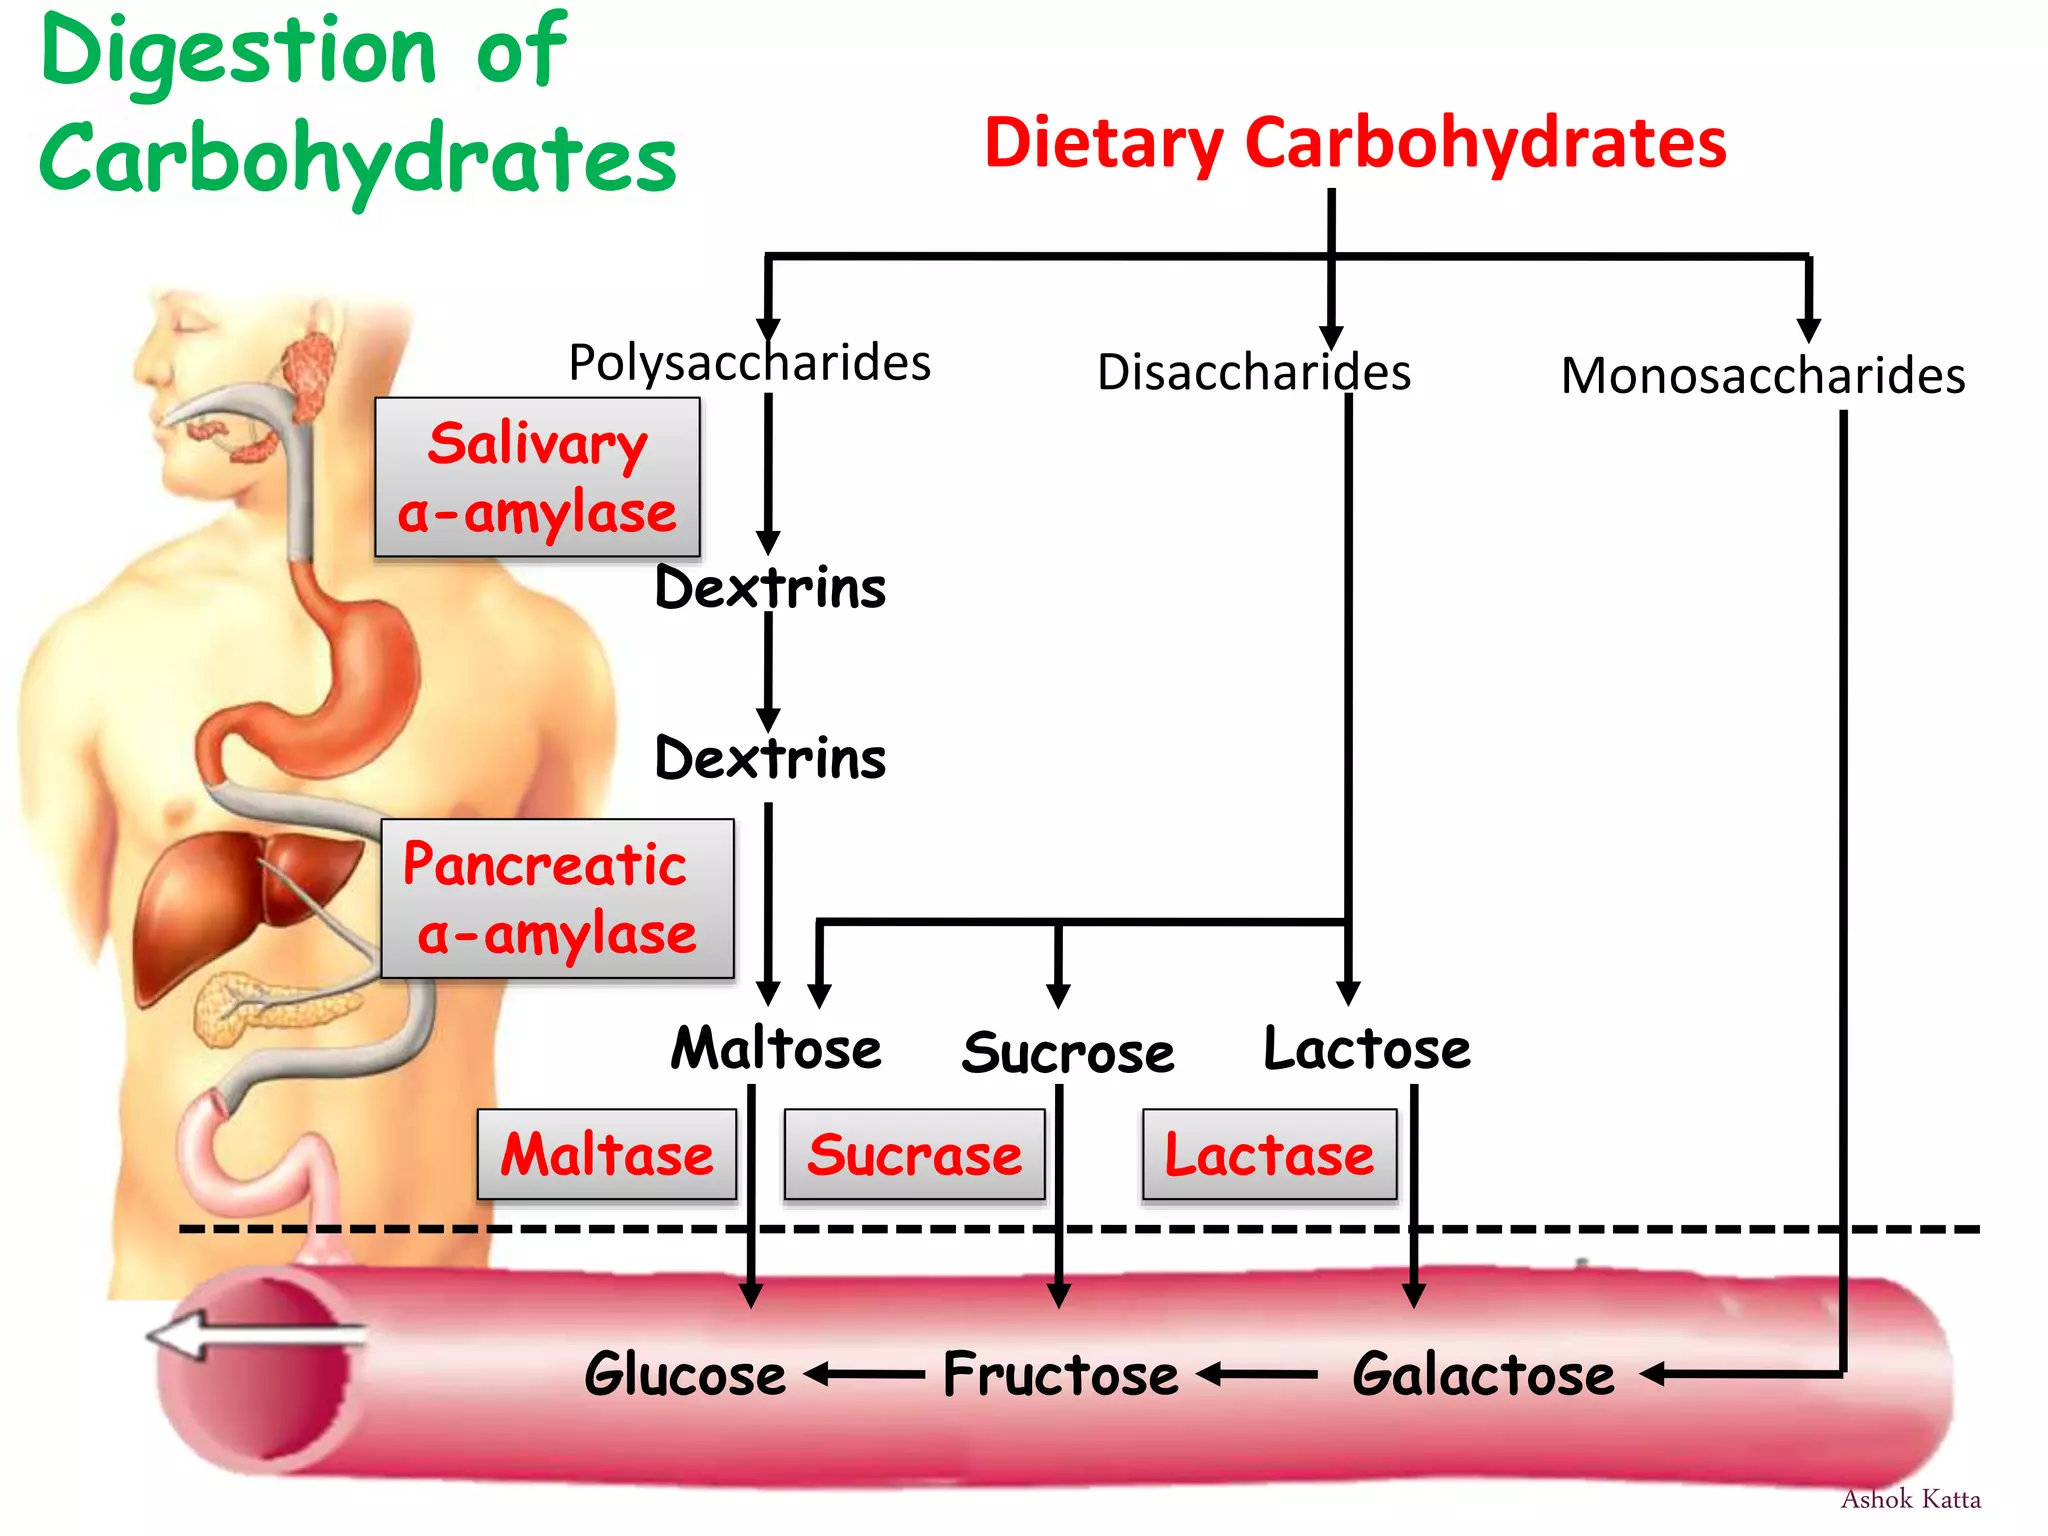
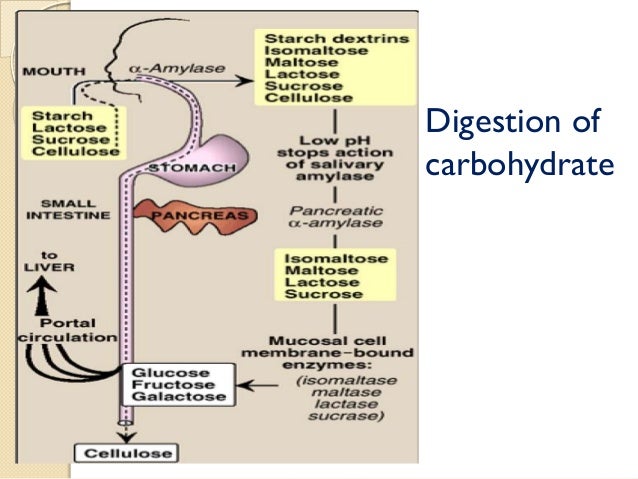
Carbohydrate digestion starts in the mouth before you even swallow anything. Salivary amylase breaks down starch into smaller chains called dextrins and maltose. Most people don't notice this because the process is slow and the food gets washed down quickly. You only get real benefit from chewing starchy foods like rice, potatoes, or bread for 20 to 30 seconds before swallowing. The longer you chew, the more work salivary amylase has to do before the acidic environment of the stomach shuts it down entirely.
From there, the process gets messy. Stomach acid neutralizes salivary amylase, so carbohydrate digestion basically pauses in the stomach for anywhere from 20 minutes to two hours depending on what else is in the meal. A high-fat meal slows gastric emptying significantly, which means starch sits in your stomach longer doing nothing.
Where Does Digestion Occur For Carbohydrates
The real action happens in the small intestine. Pancreatic amylase takes over where salivary amylase left off, breaking down remaining starch chains into disaccharides like maltose, sucrose, and lactose. These disaccharides then sit on the brush border of the intestinal epithelial cells, where brush border enzymes do the final cleavage.
Maltase breaks maltose into two glucose molecules. Sucrase breaks sucrose into glucose and fructose. Lactase breaks lactose into glucose and galactose. Only monosaccharides can be absorbed through the intestinal wall. Glucose and galactose use sodium-dependent cotransporters. Fructose uses a completely different transporter and gets absorbed more slowly.
This is the part most beginner nutrition guides skip entirely. The rate-limiting step for carbohydrate digestion isn't enzymatic breakdown. It is fructose absorption. When you eat a meal high in fructose relative to glucose, like apples or high-fructose corn syrup, a lot of that fructose reaches the colon undigested. Bacteria ferment it. That is where bloating, gas, and discomfort come from after certain meals.
I ran into this repeatedly when I was working with athletes who had irritable bowel symptoms and kept blaming fiber. The actual culprit in several cases was fructose malabsorption from sports drinks and recovery gels. These products often have glucose-to-fructose ratios above 1:1, which overwhelms the GLUT5 transporter. Switching to formulas with a 2:1 glucose-to-fructose ratio resolved their symptoms within two weeks. That is not theoretical. I watched it happen with actual patients.
Enzyme Deficiencies and Real-World Complications
Lactose intolerance affects roughly 65 percent of the global population at some level. The loss of lactase after childhood is genetically programmed in most humans. Only certain populations maintain lactase expression into adulthood due to a genetic mutation near the LCT gene. This is normal biology, not a disease.
When lactase is absent or low, undigested lactose passes into the colon where bacteria ferment it. The osmotic effect pulls water into the intestinal lumen, and the fermentation produces hydrogen, methane, and carbon dioxide. Symptoms start 30 minutes to two hours after ingestion. The severity depends on how much lactose you consume and how much residual lactase activity you have.
There is no way to regenerate lactase in adults. The workaround is either eliminating lactose-containing foods or taking over-the-counter lactase supplements before eating dairy. The supplements work reliably for most people but they are not perfect. They break down lactose in the stomach and upper small intestine before the lactose reaches the colon, but they do not eliminate all symptoms if the dose is insufficient or if the dairy meal is very large.
Starch Types and Digestion Speed
Not all starch digests at the same rate. Resistant starch escapes small intestinal digestion entirely and ferments in the colon. This is functionally a fiber. There are three types: Type 1 is physically entrapped in plant cell walls, Type 2 is found in raw potatoes and green bananas, and Type 3 forms when starchy foods are cooked and then cooled.
Resistant starch lowers the glycemic response of a meal because less glucose enters the bloodstream from it. It also serves as a prebiotic for colonic bacteria, which produce short-chain fatty acids like butyrate. Butyrate is the preferred energy source for colonocytes and has anti-inflammatory effects.
I learned about this the hard way when a client insisted on eating cold potato salad daily for lunch and complained about sustained energy crashes. Once we calculated how much resistant starch she was getting from the cooled potatoes and factored that into the meal, the energy pattern improved noticeably. The resistant starch delayed glucose absorption enough to flatten the post-meal spike without adding any other interventions.
What Happens When This System Fails
Pancreatic exocrine insufficiency dramatically reduces carbohydrate digestion capacity. Without adequate pancreatic amylase, large amounts of starch reach the colon undigested. Patients present with steatorrhea, bloating, and weight loss even when eating normally. This is most commonly caused by chronic pancreatitis, cystic fibrosis, or pancreatic resection.
The treatment is pancreatic enzyme replacement therapy with meals. The enzymes must be taken with the first bite of food and spread throughout the meal for maximum effectiveness. Taking them after eating is largely useless because the food has already moved past the duodenum where absorption happens.
Small intestinal bacterial overgrowth is another condition that distorts normal carbohydrate digestion. Bacteria in the small intestine compete for nutrients and ferment carbohydrates prematurely. This produces gas and interferes with nutrient absorption. Hydrogen breath tests diagnose this condition by measuring gas production after a glucose or lactulose load.
Celiac disease damages the brush border itself. The villi flatten, reducing the surface area where brush border enzymes normally operate. Carbohydrate digestion becomes inefficient not because of enzyme deficiency but because the physical machinery for absorption is destroyed. Until the intestine heals on a strict gluten-free diet, almost any carbohydrate can cause symptoms because the brush border is compromised.
The takeaway is straightforward. Carbohydrate digestion is a multi-site process involving mechanical breakdown in the mouth, temporary pausing in the stomach, enzymatic digestion in the duodenum and jejunum, and final brush border cleavage before absorption. Each step has potential failure points. Understanding where the bottlenecks are helps you troubleshoot when things go wrong.
Gallery Where Does Digestion Occur For Carbohydrates
Digestion and Absorption of Carbohydrates in Human Body
Digestion and Absorption of carbohydrates | PPSX
Short Note On Digestion And Absorption Of Carbohydrates In The Body ...
Human Digestive System And Digestion Of Carbohydrates
Digestion Of Carbohydrates