The Mitochondrial Matrix Isn't Where Most People Think
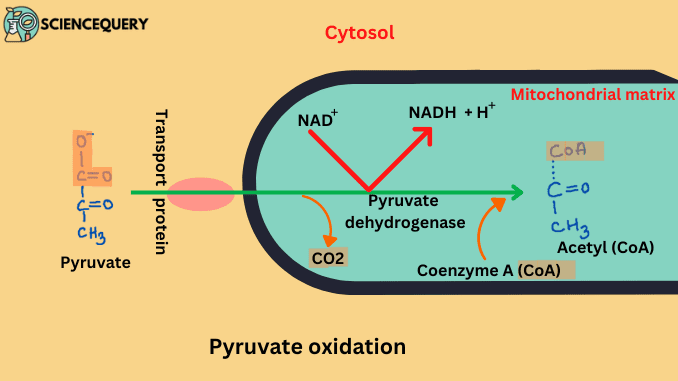
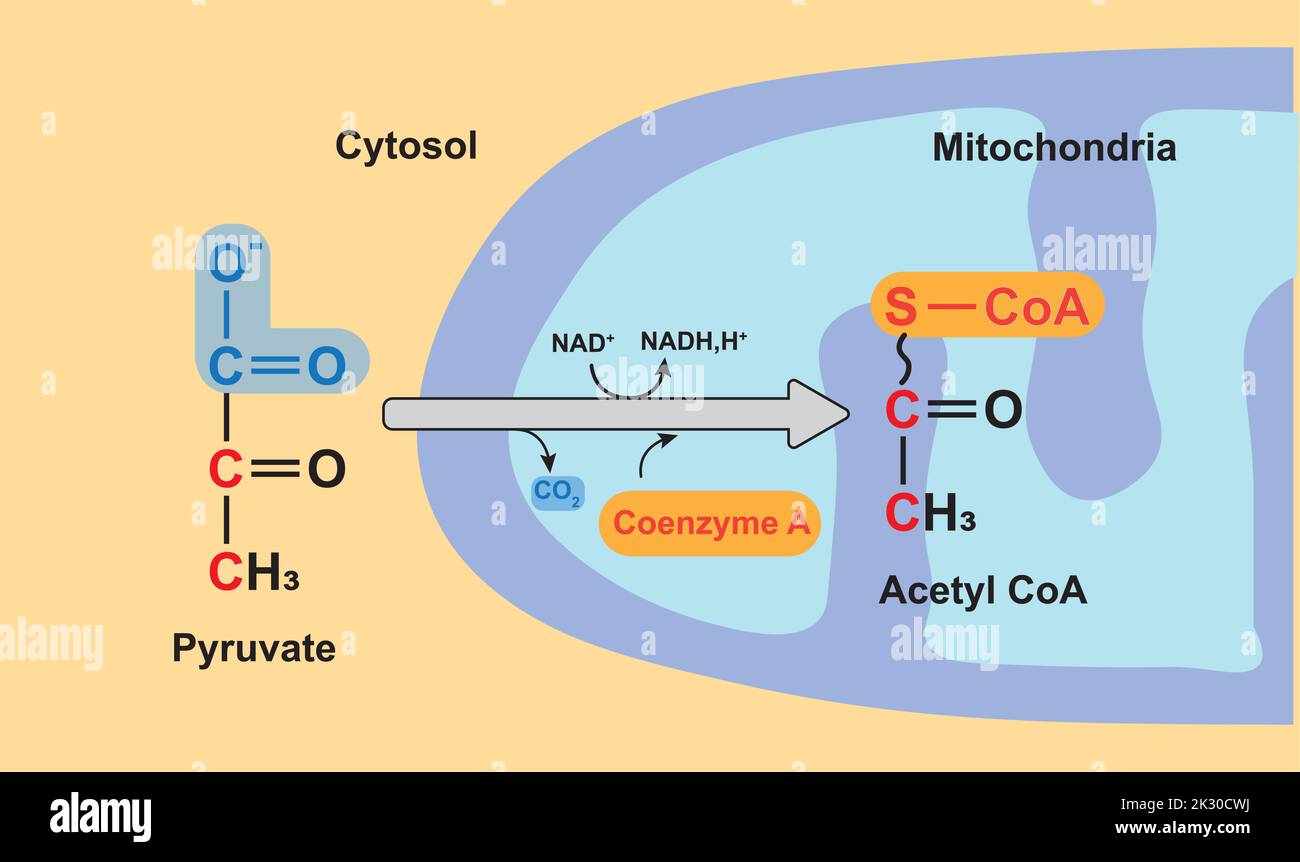
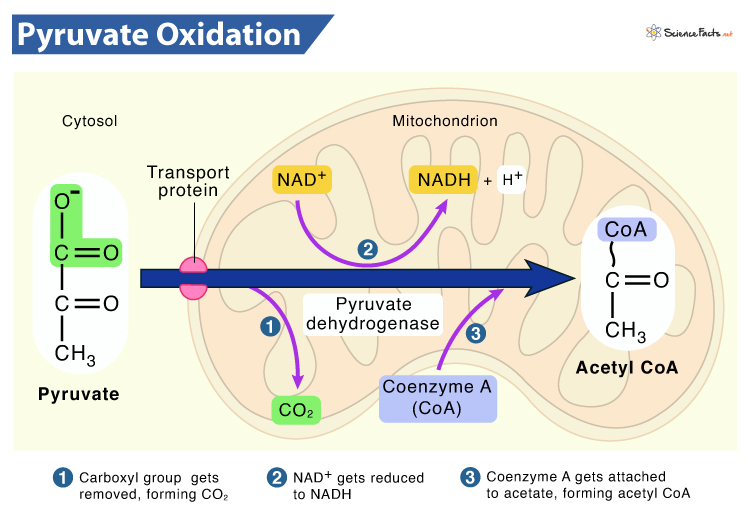
Pyruvate oxidation takes place in the mitochondrial matrix. That's the straightforward answer you'll get from any textbook. But the actual mechanics are a bit more fiddly than that, and if you're working with this in a lab or trying to troubleshoot cellular respiration issues, the simple answer doesn't always help. The pyruvate dehydrogenase complex (PDC) sits in the mitochondrial matrix, and that's where pyruvate gets converted into acetyl-CoA. Pyruvate crosses the inner mitochondrial membrane via the monocarboxylate transporter or MCT1, gets pulled inside by the proton gradient, and then the PDC goes to work. Three enzymatic subunits do the heavy lifting: E1 is pyruvate dehydrogenase, E2 is dihydrolipoyl transacetylase, and E3 is dihydrolipoyl dehydrogenase. Five cofactors are required—thiamine pyrophosphate (B1), lipoic acid, CoA (B5), FAD (B2), and NAD+ (B3). Miss one and the whole thing stalls. I ran into a problem a while back where cells were still producing lactate despite adequate oxygen, which pointed to a PDC bottleneck rather than anything hypoxic. The lab had optimized glucose uptake and checked the electron transport chain, so the answer was hiding in the pyruvate oxidation step itself. We measured PDH activity directly using a spectrophotometric NADH production assay, and found the E1 subunit had been phosphorylated into inactivity by hyperactive PDK4. The workaround was suppressing PDK4 expression with shRNA and confirming rescue with a PDK inhibitor like dichloroacetate. That fixed the lactate leak and restored normal acetyl-CoA flux through the TCA cycle.
Here's something beginners routinely miss: pyruvate oxidation isn't a standalone reaction. It's the bridge between glycolysis and the TCA cycle, and it's tightly regulated by product inhibition and covalent modification. Acetyl-CoA and NADH both feed back and slow the complex down. When the cell has plenty of energy, the PDC gets turned off by PDH kinase. When energy is needed, PDH phosphatase dephosphorylates it and brings it back online. That's calcium-sensitive, which is why muscle contraction actually ramps up pyruvate oxidation through calcium release from the sarcoplasmic reticulum. Another counter-intuitive point: in certain cancer cells and under hypoxic conditions, the PDC can become a liability rather than an asset. Warburg-effect tumors often have upregulated PDK expression, which keeps the complex phosphorylated and inactive even when oxygen is present. That's why dichloroacetate is being investigated as an anti-cancer agent—it forces the PDC open and pushes metabolism back toward oxidative phosphorylation. The downside is that it doesn't discriminate well between tumor and healthy tissue, so systemic toxicity is a real concern. You'll see dose-dependent peripheral neuropathy in clinical trials because neurons also depend on functional PDC. If you're working with isolated mitochondria, be aware that the inner membrane integrity matters more than most protocols account for. Swollen or ruptured mitochondria will still show some PDC activity in a buffer, but the proton gradient driving pyruvate uptake is gone. You'll get artifactual results that look like normal oxidation rates until you try to couple it to ATP production. Always run a state 3 respiration check in parallel—oligomycin-sensitive respiration is your quality control for whether the PDC output is actually being used or just dissipating.
There's also a tissue-level variation worth noting. Cardiac and skeletal muscle PDC has a higher Vmax than hepatic PDC, which makes sense given that heart muscle runs almost exclusively on oxidative metabolism. Liver PDC is more sensitive to hormonal regulation because the liver needs to switch between glucose production and consumption. If you're pulling data from mixed-tissue samples without accounting for this, your numbers will be misleading. The same is true for brain versus kidney versus adipose tissue—each has a different PDC isoform composition and regulatory profile. The practical upshot is that where pyruvate oxidation occurs is technically simple, but how it behaves in any given context depends on cofactor availability, phosphorylation state, substrate supply, and the energetic demands of the specific cell type. If you're troubleshooting unexpected lactate accumulation or suspecting a metabolic block, measuring the PDC directly—rather than inferring from downstream TCA cycle intermediates—is usually the faster path to an answer.
Get the Full Details