Understanding Areolar Connective Tissue and Its Distribution
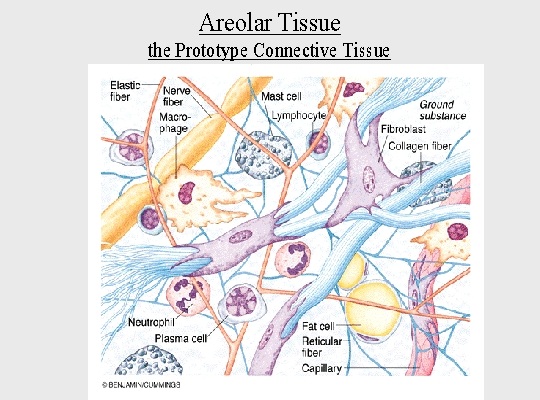
Areolar connective tissue is the most common type of loose connective tissue in the human body. It serves as a packing material between organs, provides structural support, and acts as a medium for nutrient and waste exchange. Despite its ubiquity, the tissue is often misunderstood or overlooked in both academic and clinical settings. The tissue consists of a loose arrangement of collagen fibers, elastic fibers, and reticular fibers suspended in a gel-like ground substance rich in proteoglycans and hyaluronic acid. The main cell types include fibroblasts, macrophages, mast cells, and occasionally adipocytes. This composition gives it both flexibility and tensile strength while maintaining permeability for fluid movement.
Where Is Areolar Connective Tissue Found In The Body
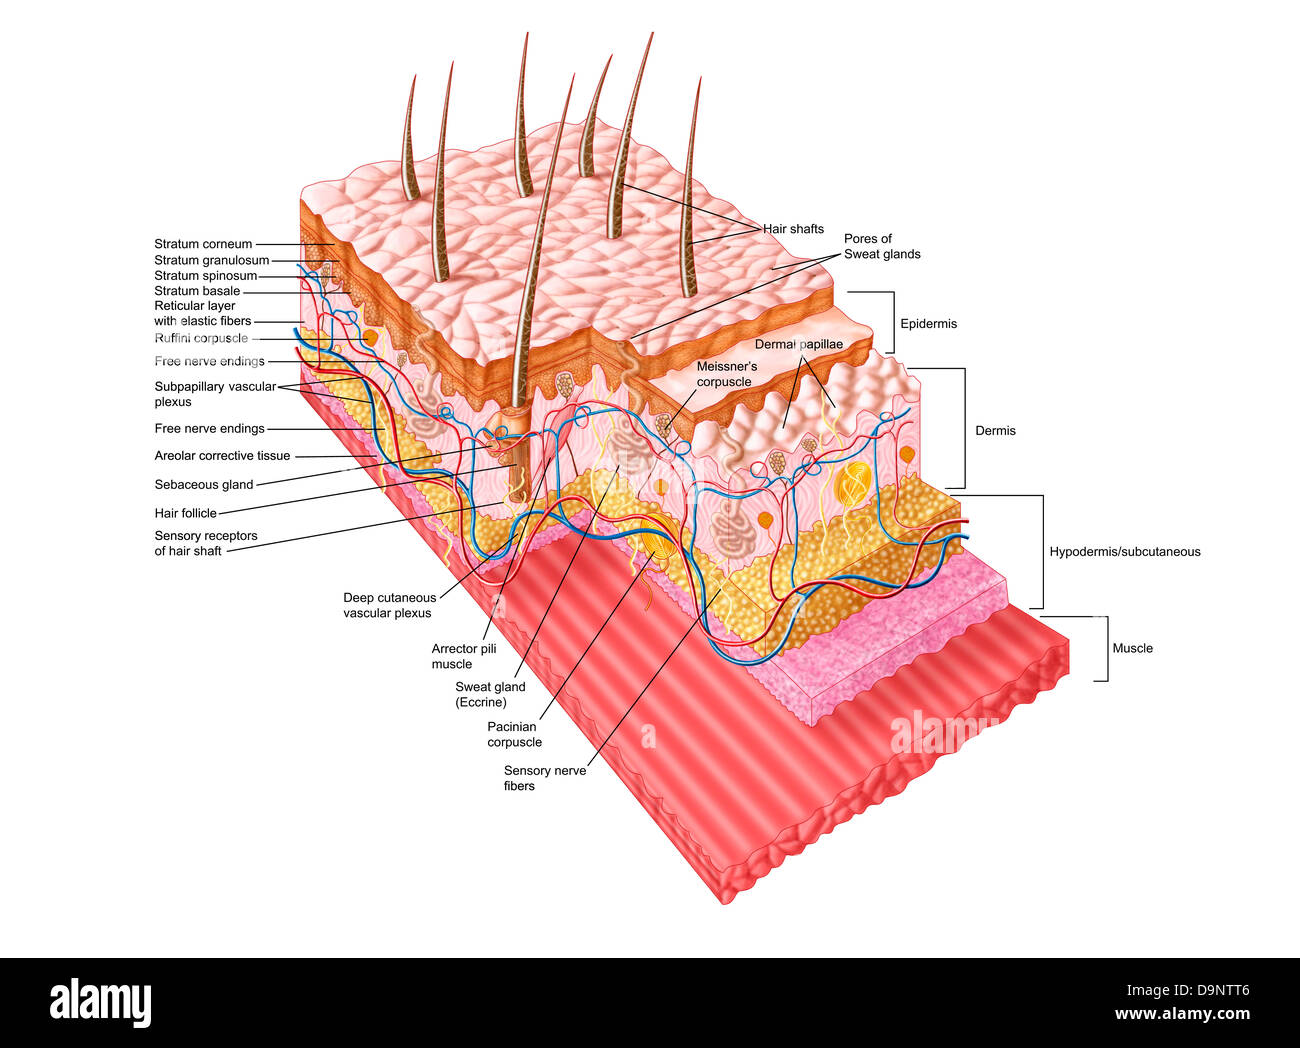
This tissue is distributed widely throughout the body, and knowing exactly where it sits matters more than most textbooks suggest. It is found directly beneath the dermis of the skin, forming the superficial fascia layer. From there it extends into the submucosa of the gastrointestinal tract, surrounding blood vessels and nerves throughout the entire vascular and nervous systems. It fills the spaces between skeletal muscles, envelopes the kidneys and other retroperitoneal organs, and lines the abdominal and pelvic cavities as part of the mesenteries. It is also present in the eyelids, the mucous membranes of the nose and mouth, the tonsils, the lymph nodes, and the tissue surrounding the eyes and teeth. In the breast, areolar tissue makes up a significant portion of the stromal framework. Around joints, it contributes to the synovial membranes. Even the lamina propria of many epithelial linings contains a thin layer of this tissue. The reason it appears almost everywhere comes down to its functional versatility. It binds surfaces together without restricting movement. It allows immune cells to patrol freely. It provides a pathway for lymph and blood vessels to reach tissues. These are not minor functions. They are foundational to how the body maintains homeostasis and responds to injury.
How It Actually Works Under Practical Conditions
In a lab or clinical dissection, areolar tissue can be identified by its open, web-like appearance. It lacks the dense, tightly packed fiber arrangement seen in dense regular or irregular connective tissues. Under a microscope at 100x magnification, you will see scattered fibroblast nuclei, wavy collagen bundles, and clear spaces where the ground substance occupies volume. Staining with hematoxylin and eosin will show the collagen fibers pink and the cell nuclei purple, but elastic fibers require a special stain like Verhoeff-Van Gieson to become clearly visible. I spent considerable time studying histological slides early in my career and kept making the same mistake. I confused areolar tissue with adipose tissue in sections where fat cells were sparse. The workaround was straightforward once I learned to look for the specific nuclear morphology of fibroblasts — elongated and flattened rather than the signet-ring appearance of adipocytes — and to check for the presence of scattered mast cells, which are nearly always found in areolar tissue but absent in pure adipose depots. One edge case that trips people up involves the submucosa of the esophagus. The areolar tissue there is relatively thin compared to the rest of the GI tract, and in fixed specimens it can appear almost compressed. If you are examining a slide and struggle to distinguish the submucosal layer from the muscularis externa, look for the presence of mucous-secreting glands. Their location within the loose connective tissue is a reliable landmark.
Get the Full Details
Functional Nuances That Beginners Miss
Most introductory texts describe areolar tissue as simply a "packing material," which is accurate but incomplete. The tissue actively participates in immune surveillance through its resident macrophages and mast cells. Macrophages in areolar tissue are not static; they migrate along the fiber network and respond rapidly to localized injury or infection. Mast cells degranulate in response to tissue damage, releasing histamine and other mediators that increase vascular permeability and recruit additional immune cells. Another counter-intuitive point is that areolar tissue is not equally abundant everywhere. In areas subject to high mechanical stress, such as the dermis of the back or the palms, the loose arrangement shifts toward denser irregular connective tissue. The transition is gradual, not abrupt, which means interpreting histological sections from these regions requires attention to fiber density and orientation rather than expecting a clean categorical boundary. The ground substance composition also varies by location. In areas near inflammatory sites, the hyaluronic acid content increases, making the tissue more hydrated and less structurally rigid. This is a dynamic property, not a fixed one, and it has implications for wound healing and scar formation.
Limitations and What Happens When Things Go Wrong
Areolar tissue is resilient but not invulnerable. One significant limitation is its susceptibility to edema. Because the ground substance is highly hydrophilic, any increase in capillary permeability or lymphatic obstruction causes fluid to accumulate rapidly within the tissue. This is why periorbital swelling is often one of the first visible signs of systemic fluid imbalance — the areolar tissue in the eyelids holds water readily and shows it visibly. Another practical concern is that areolar tissue does not regenerate well after significant surgical trauma. When it is disrupted during procedures like mastectomies or abdominoplasties, the healing response relies on fibroblast proliferation and collagen deposition, which produces scar tissue rather than restoring the original loose architecture. This has functional consequences for lymphatic drainage and tissue mobility in the affected area. In conditions like scleroderma, the loose areolar matrix becomes increasingly fibrotic and hardened. The normal flexibility is lost, and the tissue functions more like dense irregular connective tissue. This transition is progressive and largely irreversible, which underscores the importance of early detection in patients presenting with skin thickening and reduced tissue pliability.
Clinical and Practical Takeaways
If you are studying histology, focus on the cell types and fiber arrangement rather than memorizing every location. The pattern is consistent across distributions. Fibroblasts are the structural engineers. Macrophages and mast cells are the immune sentries. The three fiber types provide the scaffold. Once you recognize that framework, identifying areolar tissue in any region becomes routine. If you are working in a clinical or surgical context, understand that areolar tissue planes are often the natural pathways of least resistance during dissection. Many procedures rely on separating along these planes rather than cutting through dense structures. This reduces bleeding and preserves function. However, in patients with chronic inflammation or prior radiation, these planes may be obliterated by fibrosis, making dissection significantly more difficult and increasing the risk of collateral damage. The tissue itself does not require special handling or preservation beyond standard histological protocols. Formalin fixation followed by paraffin embedding and H&E staining is sufficient for routine identification. For specialized studies involving elastic fibers or glycosaminoglycans, additional staining protocols are necessary.


