The Short Answer
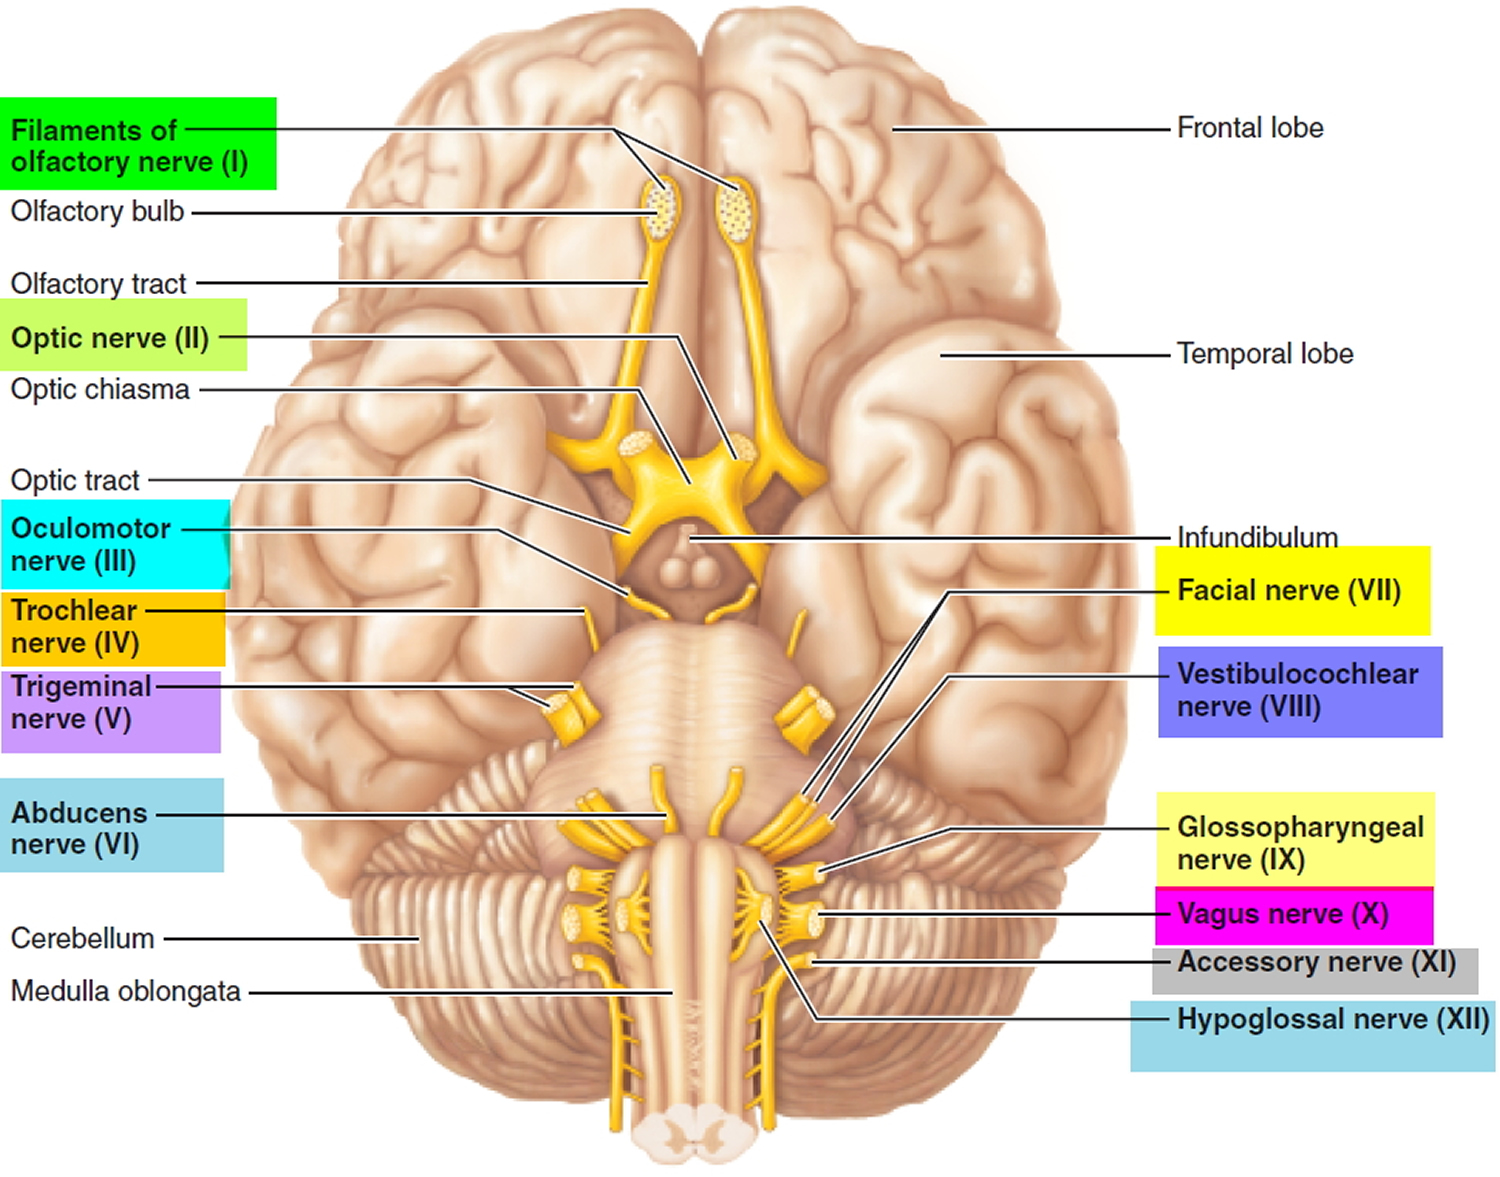
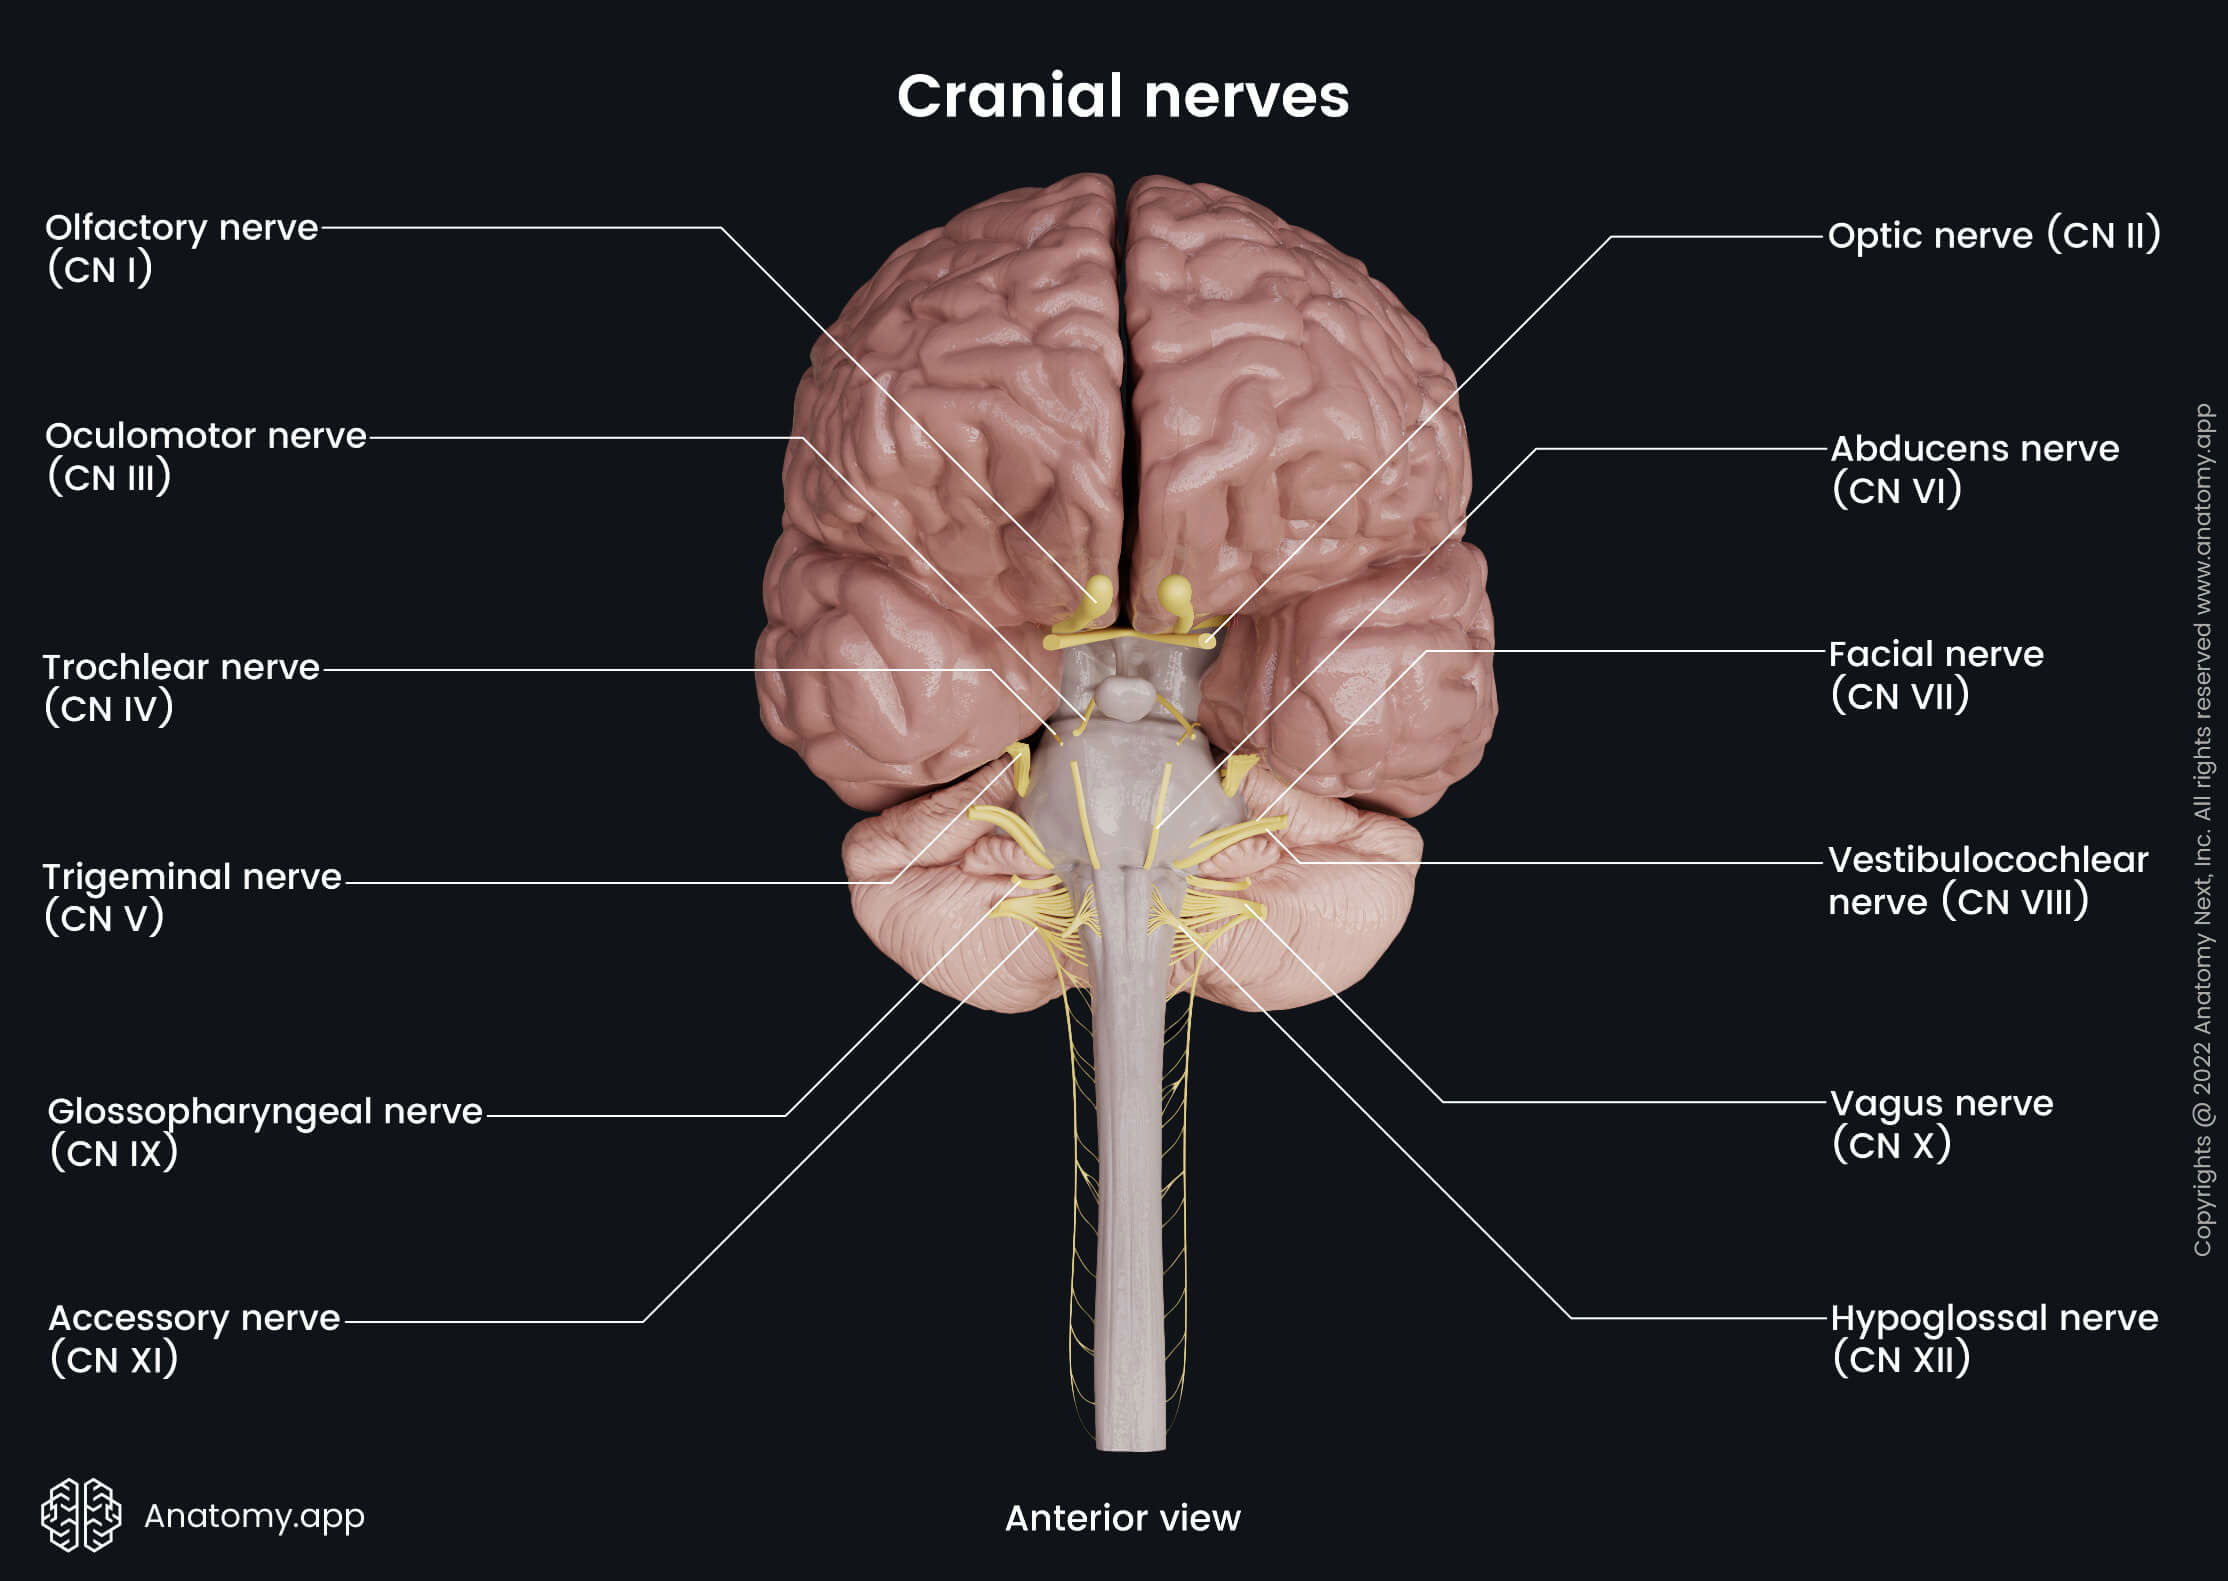
The vagus nerve (cranial nerve X) is responsible for innervating the majority of the visceral organs in your body. It's the longest cranial nerve, extending from the brainstem all the way down through the neck, chest, and abdomen. It provides parasympathetic output to the heart, lungs, esophagus, stomach, liver, gallbladder, pancreas, small intestine, and most of the large intestine up to the splenic flexure. That covers roughly eight0% of the organs where you'd look for autonomic control. The vagus works mainly as a communication highway between your gut and your brain. It sends sensory signals up about what's happening in your digestive tract and it sends motor commands back down to regulate things like heart rate, peristalsis, and glandular secretion.
I've spent enough years dealing with this in clinical settings that I can tell you the vagus nerve is one of those things that looks simple on a diagram but is annoyingly complex in practice. For example, when a patient presents with unexplained bradycardia and GI dysmotility after a viral illness, I immediately think about postviral vagal neuropathy. The standard workup misses it until you specifically test heart rate variability and consider the vagus as the common link. Here's the thing most textbooks don't emphasize enough. The vagus nerve isn't purely parasympathetic in function. About eighty percent of its fibers are actually afferent, carrying sensory information back to the nucleus tractus solitarius in the brainstem. The efferent motor and parasympathetic fibers make up only a minority of the total bundle. So when you damage the vagus, you're not just losing automatic organ control, you're also disrupting a massive amount of visceral sensation. Another counter-intuitive point people miss. The vagus doesn't actually innervate the entire large intestine. It stops around the proximal two-thirds, and the distal colon and rectum get their parasympathetic supply from the pelvic splanchnic nerves coming out of S2 through S4. So if you're studying for boards and the question says "most" visceral organs, that's the key word. The pelvic splanchnics do a significant portion of the lower GI tract independently.
In practice, vagal function is tricky to assess directly. I've found that testing baroreflex sensitivity and respiratory sinus arrhythmia gives you a functional readout of vagal tone that's more reliable than waiting for clinical symptoms like gastroparesis to appear. By the time someone has obvious vagal dysfunction affecting their organs, there's usually been silent damage for months. The downside of relying on the vagus as the primary parasympathetic route is that it's vulnerable at multiple points. Surgical procedures in the neck or chest can inadvertently damage branches. Compression by tumors, aneurysms, or even fibrous bands can cause isolated vagal palsies that present with hoarseness, swallowing difficulty, or cardiac symptoms without any GI complaints initially. These cases are easy to misdiagnose because the presentation is so variable depending on which branch is affected. If you need a quick reference for exam purposes, remember: vagus nerve, CN X, dorsal motor nucleus and nucleus ambiguus are the main central origins, and it exits the skull through the jugular foramen along with CN IX and XI. That's enough to get you through most situations.
Get the Full Details