Understanding Scleral Jaundice
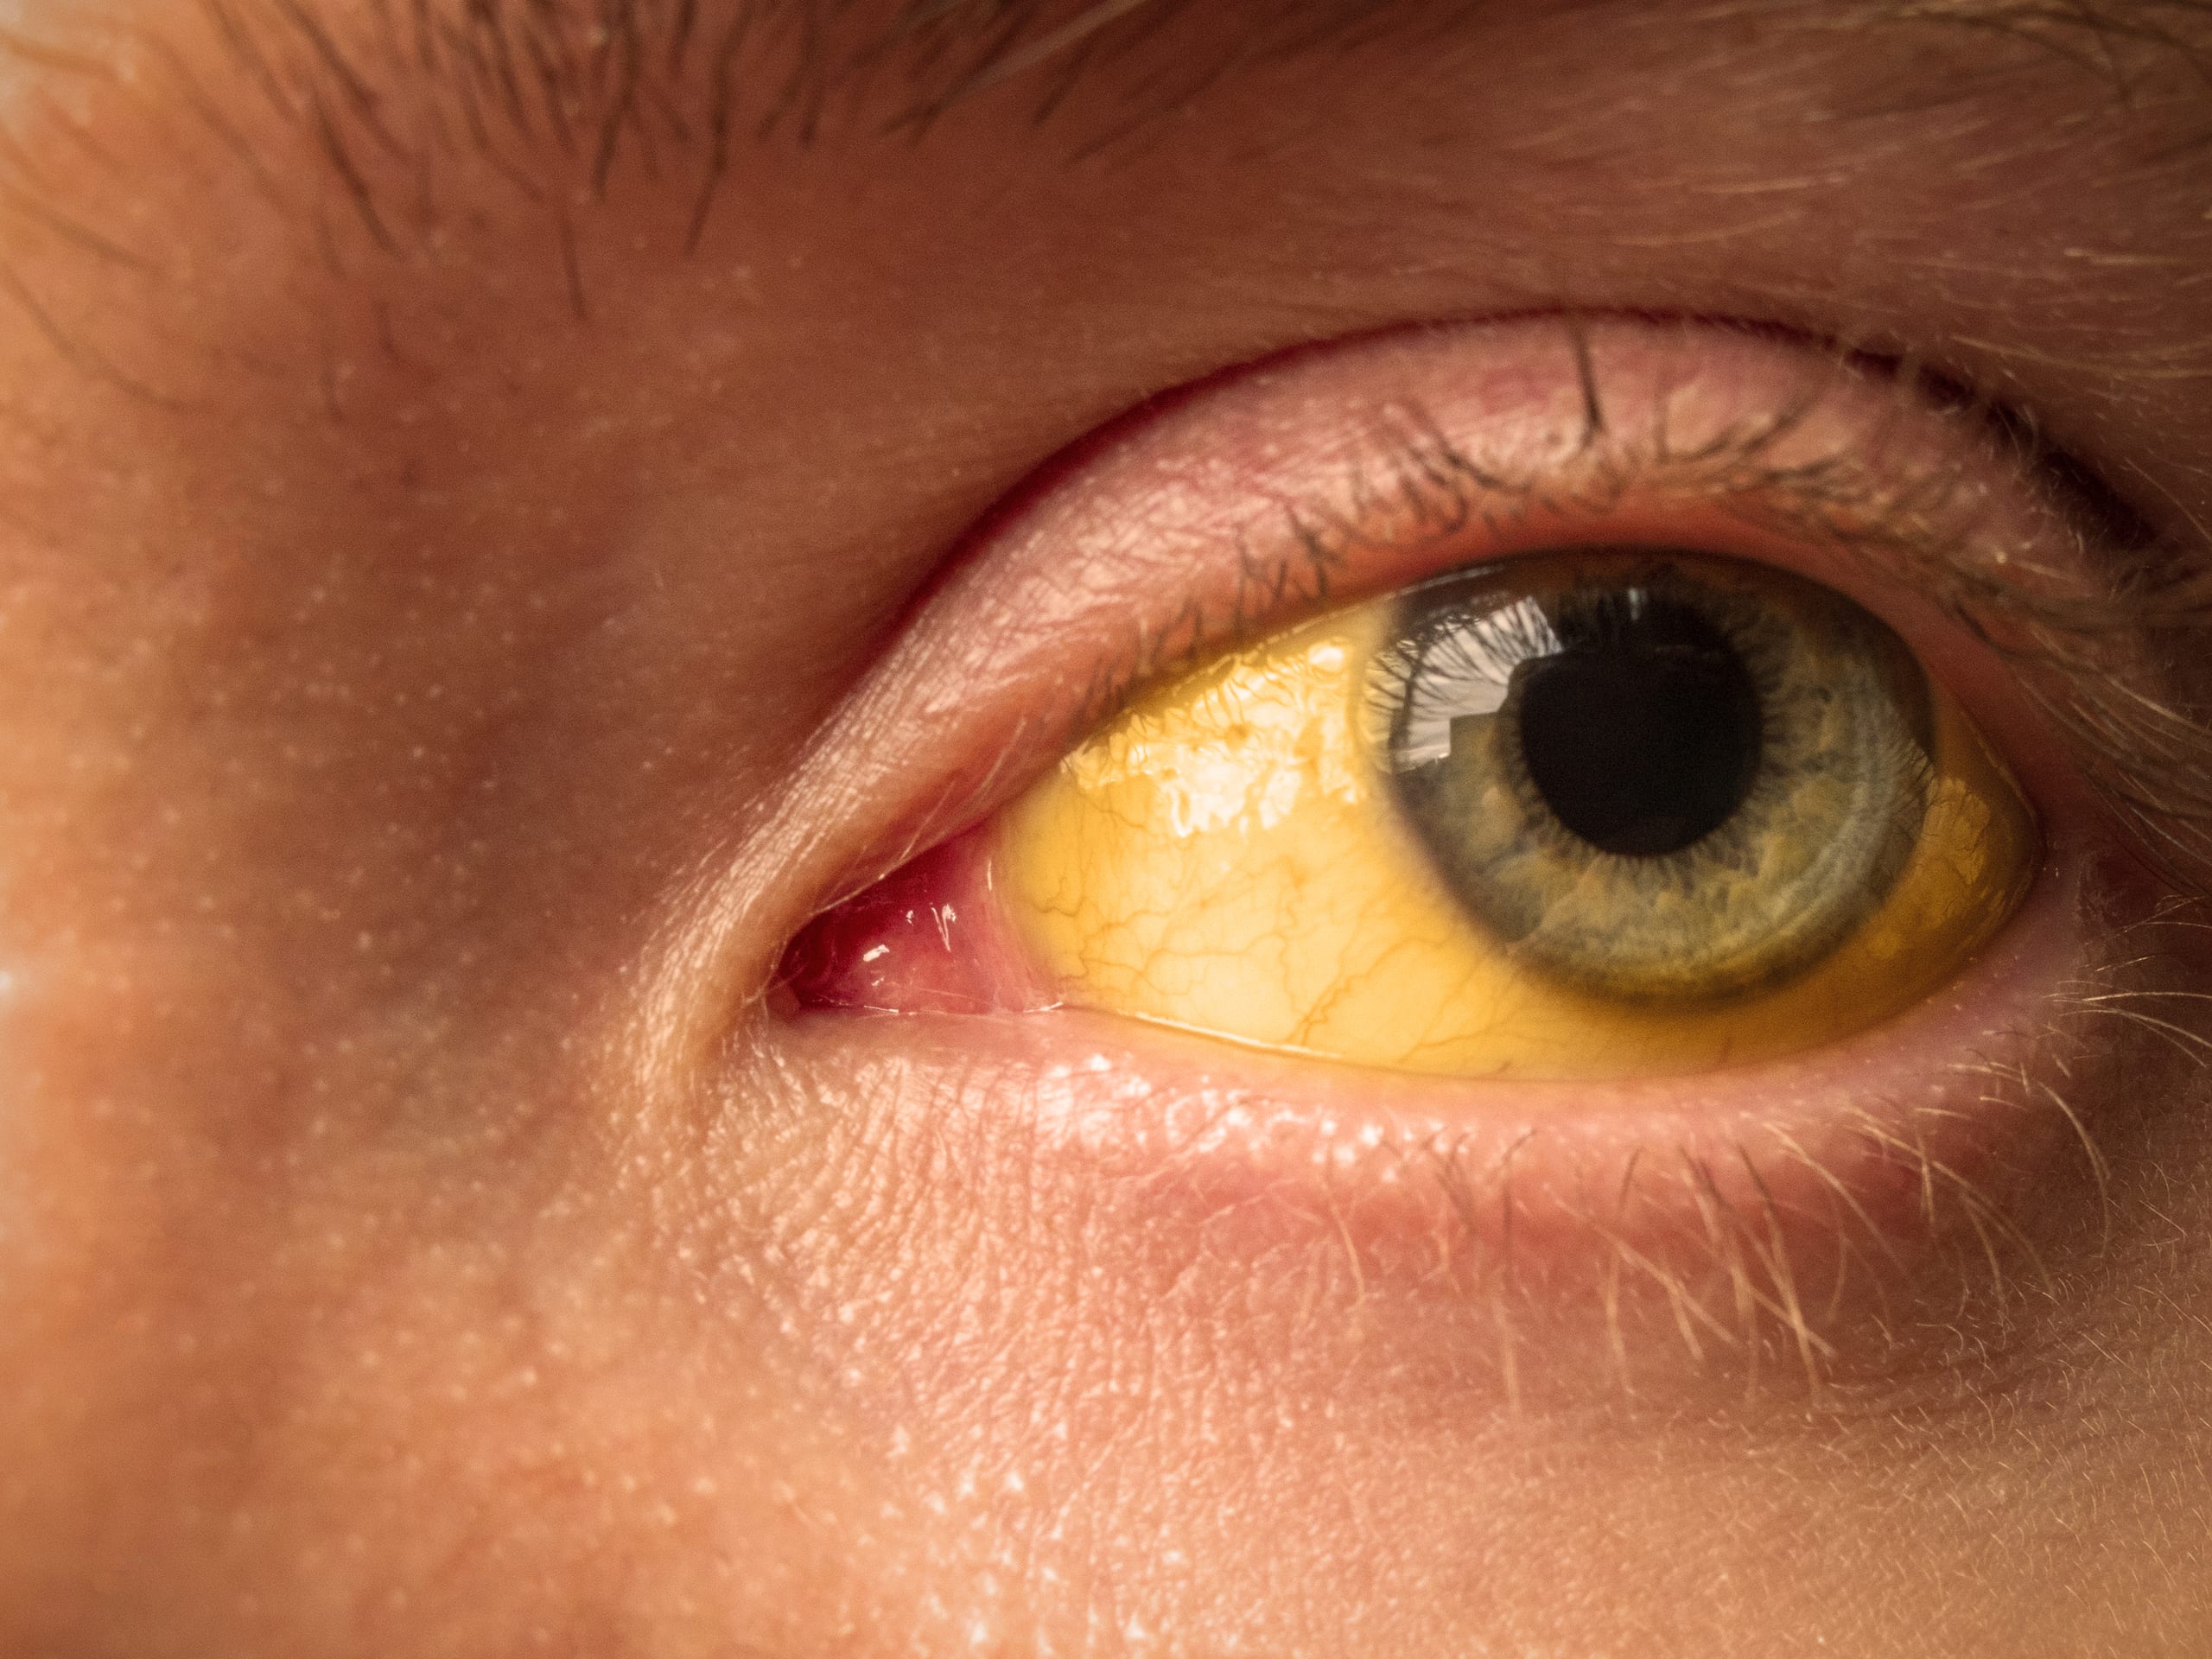
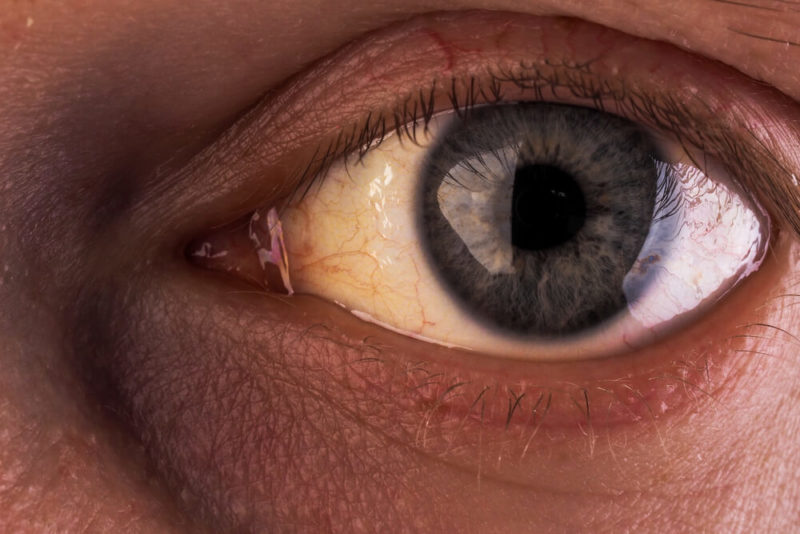
Yellowing of the eyes happens when there's too much bilirubin in the blood. Bilirubin is a waste product from broken-down red blood cells, and your liver normally processes it. When that system gets backed up, the yellow pigment shows up in tissues with high elastic content. The whites of the eyes are one of those places, and they tend to be the first visible sign before the skin shows any change. The term for this medically is scleral icterus, though most people just call it jaundice. The yellow color comes from conjugated and unconjugated bilirubin depositing in the sclera. There are three main categories of what causes it, and knowing which category applies matters because the urgency varies wildly between them. The first category is pre-hepatic, meaning the problem is happening before the liver even gets involved. This usually involves excessive breakdown of red blood cells, like in hemolytic anemias or reactions to certain medications. The liver itself is fine, but it gets overwhelmed by the volume of bilirubin coming at it. Gilbert's syndrome is a mild version of this that a lot of people have without knowing. It's essentially a genetic variant in the UDP-glucuronosyltransferase enzyme that handles bilirubin conjugation. Under normal circumstances people with Gilbert's are totally asymptomatic, but during periods of fasting, dehydration, or illness the bilirubin can spike enough to notice in the eyes. I've seen this repeatedly in my practice where someone comes in panicking about yellow eyes, and after basic labs we find an unconjugated hyperbilirubinemia with completely normal liver enzymes. It's not dangerous, but it does require ruling out the other stuff first.
The second category is hepatic, meaning the liver itself has a problem processing or excreting bilirubin. This is where things get more serious. Hepatitis of any cause, alcoholic liver disease, cirrhosis, drug-induced liver injury from things like acetaminophen overdose or certain herbal supplements, and genetic conditions like Dubin-Johnson or Rotor syndrome all fall here. The distinction between conjugated and unconjugated bilirubin on a lab test points you in the right direction. Conjugated hyperbilirubinemia suggests the liver processed the bilirubin but can't get it out, which typically means bile duct issues or hepatocellular damage. The third category is post-hepatic, which is obstructive jaundice. Something is blocking the bile flow after it leaves the liver. Gallstones are by far the most common cause, followed by tumors of the pancreas or biliary tree. With obstruction, you're usually looking at conjugated hyperbilirubinemia and the person will often have dark urine and pale stools because the bilirubin can't reach the intestines. This is the category where timing matters most. A stone stuck in the common bile duct can lead to cholangitis within days, and that's a life-threatening infection. I dealt with a case a few years back that highlighted how tricky this can be. A patient in their sixties came in with what looked like straightforward jaundice and no other symptoms beyond fatigue. No pain, no fever, no recent medication changes. The obvious move would have been to look for gallstones, so we ordered an ultrasound. It was negative. But the alkaline phosphatase was elevated and the direct bilirubin was high. We ended up doing an MRCP which revealed a small pancreatic head mass that was too early to see on the ultrasound. If we'd stopped at the negative ultrasound, we would have missed it by months. That's the thing about painless jaundice in older adults, it sounds benign but it's actually the red flag scenario until proven otherwise.
When to Worry vs. When to Wait
Not every instance of yellow eyes is an emergency, but distinguishing between the two scenarios requires looking at the full picture. If the yellowing appeared gradually over weeks with no other symptoms and you have a known history of Gilbert's syndrome, it might just be another episode triggered by stress or skipping meals. But if it came on suddenly, if you have abdominal pain especially on the right side, if your urine is the color of tea, or if you're vomiting and febrile, you need medical evaluation within hours not days. One thing people miss is that yellowing of the eyes isn't always bilirubin. There are conditions that can discolor the sclera without any metabolic problem. Carotenemia from eating massive amounts of carrots or sweet potatoes turns the skin orange but deliberately spares the eyes, which is one of the few reliable ways to distinguish it from true jaundice. Then there are benign conditions like pinguecula or fatty deposits on the eye that can look yellowish but are localized spots rather than a diffuse scleral color change. If only one eye is affected or if it's a discrete patch rather than the whole white portion, it's probably not systemic. Another oversight I see regularly is people attributing yellow eyes to alcohol without getting any testing. Yes, alcohol can damage the liver, but the yellowing itself isn't from the ethanol it's from the accumulated bilirubin. Someone could be drinking heavily and have perfectly normal liver function, or they could have had hepatitis C for twenty years and only now be presenting with jaundice. The symptom doesn't tell you the cause, which is why labs are non-negotiable.
Get the Full Details

What Testing Actually Looks Like
A basic workup starts with a comprehensive metabolic panel focusing on the bilirubin fractionation, liver enzymes, and kidney function. A complete blood count will show if there's hemolysis happening. The pattern of results narrows the differential significantly. Elevated AST and ALT with a ratio where ALT is higher than AST points toward viral hepatitis or non-alcoholic fatty liver disease. AST higher than ALT is the classic alcoholic hepatitis pattern, though that's not absolute. If both are in the hundreds or thousands, think acute hepatitis, ischemic hepatitis, or toxin exposure. If the alkaline phosphatase and GGT are disproportionately elevated compared to the transaminases, you're looking at a cholestatic pattern which suggests bile duct obstruction or primary biliary cholangitis. The GGT helps confirm that an elevated alkaline phosphatase is actually hepatic in origin rather than from bone. From there you'd typically move to imaging, usually starting with an abdominal ultrasound. It's fast, non-invasive, and picks up gallstones, bile duct dilation, and obvious liver abnormalities. If that's inconclusive, CT or MRI follows. For suspected small duct pathology or pancreatic lesions that ultrasound might miss, an MRCP or endoscopic ultrasound gives you the detail you need. In cases where hemolysis is suspected, a reticulocyte count, haptoglobin, LDH, and a peripheral blood smear help confirm it.
There's no real shortcut through this. I had a colleague who insisted on skipping the fractionated bilirubin and jumping straight to imaging, which made the imaging harder to interpret because you don't know whether you're looking for hepatocellular disease or biliary obstruction. The labs guide the imaging, not the other way around. Getting the order right cuts the total time to diagnosis from something like a week of back-and-forth testing down to maybe two days if you're efficient about it.
Treatment Depends Entirely on the Cause
There is no single treatment for yellow eyes because the yellowing itself is a symptom, not a disease. You treat the underlying problem. Gilbert's syndrome needs no treatment at all, just reassurance and avoidance of triggers like prolonged fasting. Hemolytic anemia requires addressing whatever is destroying the red blood cells, which could mean stopping a medication, treating an underlying autoimmune condition, or managing a genetic disorder. Hepatitis management varies by type. Viral hepatitis A is self-limiting and supportive care is all you provide. Hepatitis B might need antiviral medication depending on the phase of infection. Hepatitis C is now curable with direct-acting antivirals in almost all cases, though the timeline from diagnosis to clearance is usually eight to twelve weeks. Alcoholic hepatitis requires complete abstinence and nutritional support, and in severe cases short-course corticosteroids might be considered. Drug-induced liver injury means stopping the offending agent immediately and monitoring until function recovers, which can take weeks to months depending on severity. Biliary obstruction is a mechanical problem that usually needs a mechanical solution. ERCP with sphincterotomy and stone removal is the standard for common bile duct stones. Malignant obstruction might require stent placement for palliation or surgical resection if the tumor is resectable. The outcomes here depend heavily on how early you catch it, which circles back to why persistent unexplained jaundice should never be ignored.

The one scenario where you can do something directly for the symptom itself is neonatal jaundice, which is completely different from adult jaundice and handled with phototherapy. That's not relevant to anyone asking about their own yellow eyes, but it's the only common context where treatment targets the bilirubin level directly rather than the underlying cause.
Common Mistakes People Make
The biggest mistake is assuming the yellowing will go away on its own without figuring out why it's there. Some causes are self-limiting, like a brief viral hepatitis or a Gilbert's flare, but you can't know which you have without testing. Waiting two weeks to see if it improves is reasonable if you're otherwise well and the yellowing is mild and gradual. Waiting two weeks if you have dark urine, abdominal pain, or fever is dangerous. Another mistake is trying to self-diagnose based on internet searches. Jaundice has a huge differential, and the overlap in symptoms between benign and life-threatening causes is extensive. Both alcoholic hepatitis and acute hepatitis B can present with fatigue, nausea, and yellow eyes. The lab patterns and treatment are completely different. You can't reliably tell them apart without blood work. A third mistake is fixingate on diet or detox protocols. No amount of lemon water, milk thistle, or fasting will clear obstructive jaundice from a blocked bile duct. Milk thistle has weak evidence for mild liver protection at best and zero evidence for treating established jaundice. These approaches might buy time psychologically while the actual problem progresses, which is worse than doing nothing because they create false reassurance. If you're going to try complementary approaches, do it alongside medical evaluation not instead of it.
Finally, there's the tendency to minimize yellow eyes because they don't hurt. Pain is a useful signal, but the absence of pain doesn't mean absence of disease. Pancreatic cancer and cholangiocarcinoma both commonly present with painless jaundice precisely because they grow in locations that don't stimulate pain receptors until they're advanced. The lack of discomfort is actually the warning sign here, not the reassurance.
What You Can Do Right Now
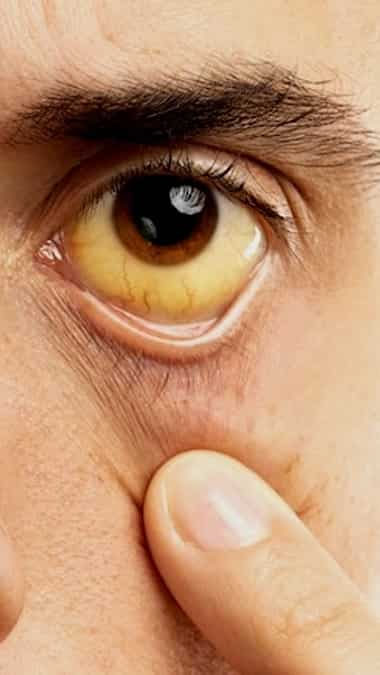
If your eyes look yellow, schedule a medical appointment. The standard blood work a primary care provider can order gives you enough information to determine whether this is urgent or can wait. Avoid alcohol completely until you know what's going on, since any additional liver stress compounds whatever damage might already be happening. Stay hydrated. Don't start any new supplements or medications without discussing them with a doctor, because some over-the-counter products can worsen liver injury. If you take prescription medications, don't stop them abruptly without consulting your prescriber, but do flag the yellowing as a concern. If you develop additional symptoms like confusion, severe abdominal pain, persistent vomiting, easy bruising, or bleeding, seek emergency care immediately. Those suggest the liver is failing to perform basic functions and the situation has moved beyond diagnostic uncertainty into active decompensation. The yellowing itself won't resolve until the underlying issue is addressed. You won't find a cream or supplement that selectively clears bilirubin from the sclera. The color fades as the bilirubin level normalizes, which happens when whatever is causing the backup is treated. In Gilbert's syndrome it might return after a stressor passes. In obstructive jaundice it persists until the obstruction is relieved. Understanding that mechanism helps set realistic expectations about timeline rather than looking for a quick fix.