The Surface Explanation and the Actual One
The standard textbook answer is that a longer tube means more surface area for absorbing nutrients before the contents reach the colon. That part is correct. The thing that actually matters is how that length translates into functional absorptive capacity, which involves things most people never consider. The adult human small intestine runs roughly 6 meters in length when measured during surgery. It doesn't measure that way on imaging, and it doesn't measure that way postmortem either. After death, the smooth muscle loses tone and the bowel relaxes to something closer to 8 meters. During life, there is constant low-level muscular tone keeping it somewhat compacted within the abdominal cavity. If you pulled it straight on a table after a procedure, it would span most of a hallway. That's not useful information for understanding function though. What matters is the surface area amplification that happens inside.
Why Is The Small Intestine So Long
A flat tube of 6 meters with a diameter of about 3 centimeters would offer maybe 0.05 square meters of surface area. That's not nearly enough to absorb the 8 to 10 liters of fluid and the various nutrients the gut processes daily. The folding solutions inside are what make the length worthwhile. There are three structural levels of amplification. First you have the circular folds called plicae circulares, which are permanent mucosal and submucosal ridges that spiral around the lumen. These appear throughout the jejunum most prominently and cut the effective diameter of the tube down significantly. Second, each fold is covered in finger-like projections called villi. Each centimeter of intestinal lining has about 20 to 40 of these. Third, each epithelial cell on the surface of a villus is studded with microvilli, forming the brush border. The final effective surface area comes out to somewhere between 200 and 300 square meters. That's the area of a badminton court packed inside a coiled tube that fits under your ribs. The length exists because the chemical breakdown of food is incomplete by the time it leaves the stomach. Gastric acid denatures proteins but doesn't fully digest them. Fats are barely touched by stomach action at all. Carbohydrates only get surface-level amylase exposure. So everything passes into the duodenum mostly intact, and the next several meters are where bile salts emulsify lipids, pancreatic enzymes chop proteins and starches into absorbable units, and the enterocytes actually pull those units across the epithelial barrier. You can't compress that reaction chain into 2 meters. The transit time through the small intestine is roughly 3 to 5 hours in a healthy adult, and that window is what allows the absorption kinetics to work. Speed it up and you get malabsorption. Slow it down and you get bacterial overgrowth. The length is a compromise between those two failure modes.
I ran into this exact problem last year while troubleshooting a case of unexplained B12 deficiency in a patient who had no obvious malabsorption on standard workup. Celiac serology was negative. Intrinsic factor antibodies came back normal. Fecal elastase was fine. We did an upper endoscopy and the duodenum and proximal jejunum looked completely normal, so the biopsy came back as trivial. But the B12 was still dropping. The issue turned out to be a very short segment of jejunal resection from a prior surgery years earlier, and the remaining bowel had adapted by extending the transit time in the distal segments, which isn't enough to compensate for B12 absorption that normally happens in the proximal jejunum. The workaround was straightforward once we knew what to look for: parenteral B12 supplementation while we accepted that the remaining small bowel length was simply insufficient for enteral absorption in that specific nutrient. It's a good reminder that the "normal" 6 meters figure is an average, and people can function fine with 3 or 4 meters if the adaptation is adequate, but the margin for error shrinks dramatically when you lose specific segments. There's a common misconception that the small intestine's length is fixed and identical across all humans. It isn't. There's significant variation. Some people run closer to 4 meters. Some run past 7. The ileum tends to be the more flexible portion. When surgeons resect bowel, they try to preserve at least 100 centimeters of ileum whenever possible because that's where bile acid reabsorption happens. Lose too much and you get bile acid malabsorption, which causes a very specific type of chronic diarrhea that doesn't respond to the usual antidiarrheals. It responds to bile acid sequestrants like cholestyramine, but that's a separate problem from the length question. Another counter-intuitive point is that length isn't the primary determinant of absorptive efficiency in most clinical scenarios. Surface area architecture matters more. Someone with celiac disease who has significant villous blunting can have a fully intact 6-meter intestine and still be severely malnourished because the functional surface area has collapsed. The tube is long but the interior is essentially smooth. Conversely, patients who've had substantial small bowel resections often adapt over months. The remaining bowel undergoes compensatory hyperplasia. The villi lengthen. The plicae circulares become more pronounced. Transit time slows in the remaining segments. I've seen patients maintain reasonable nutritional status on oral intake alone after losing 70 percent of their small bowel, though they required careful monitoring and sometimes supplemental trace elements. The bowel adapts in ways that aren't well represented in textbook diagrams.
Get the Full Details

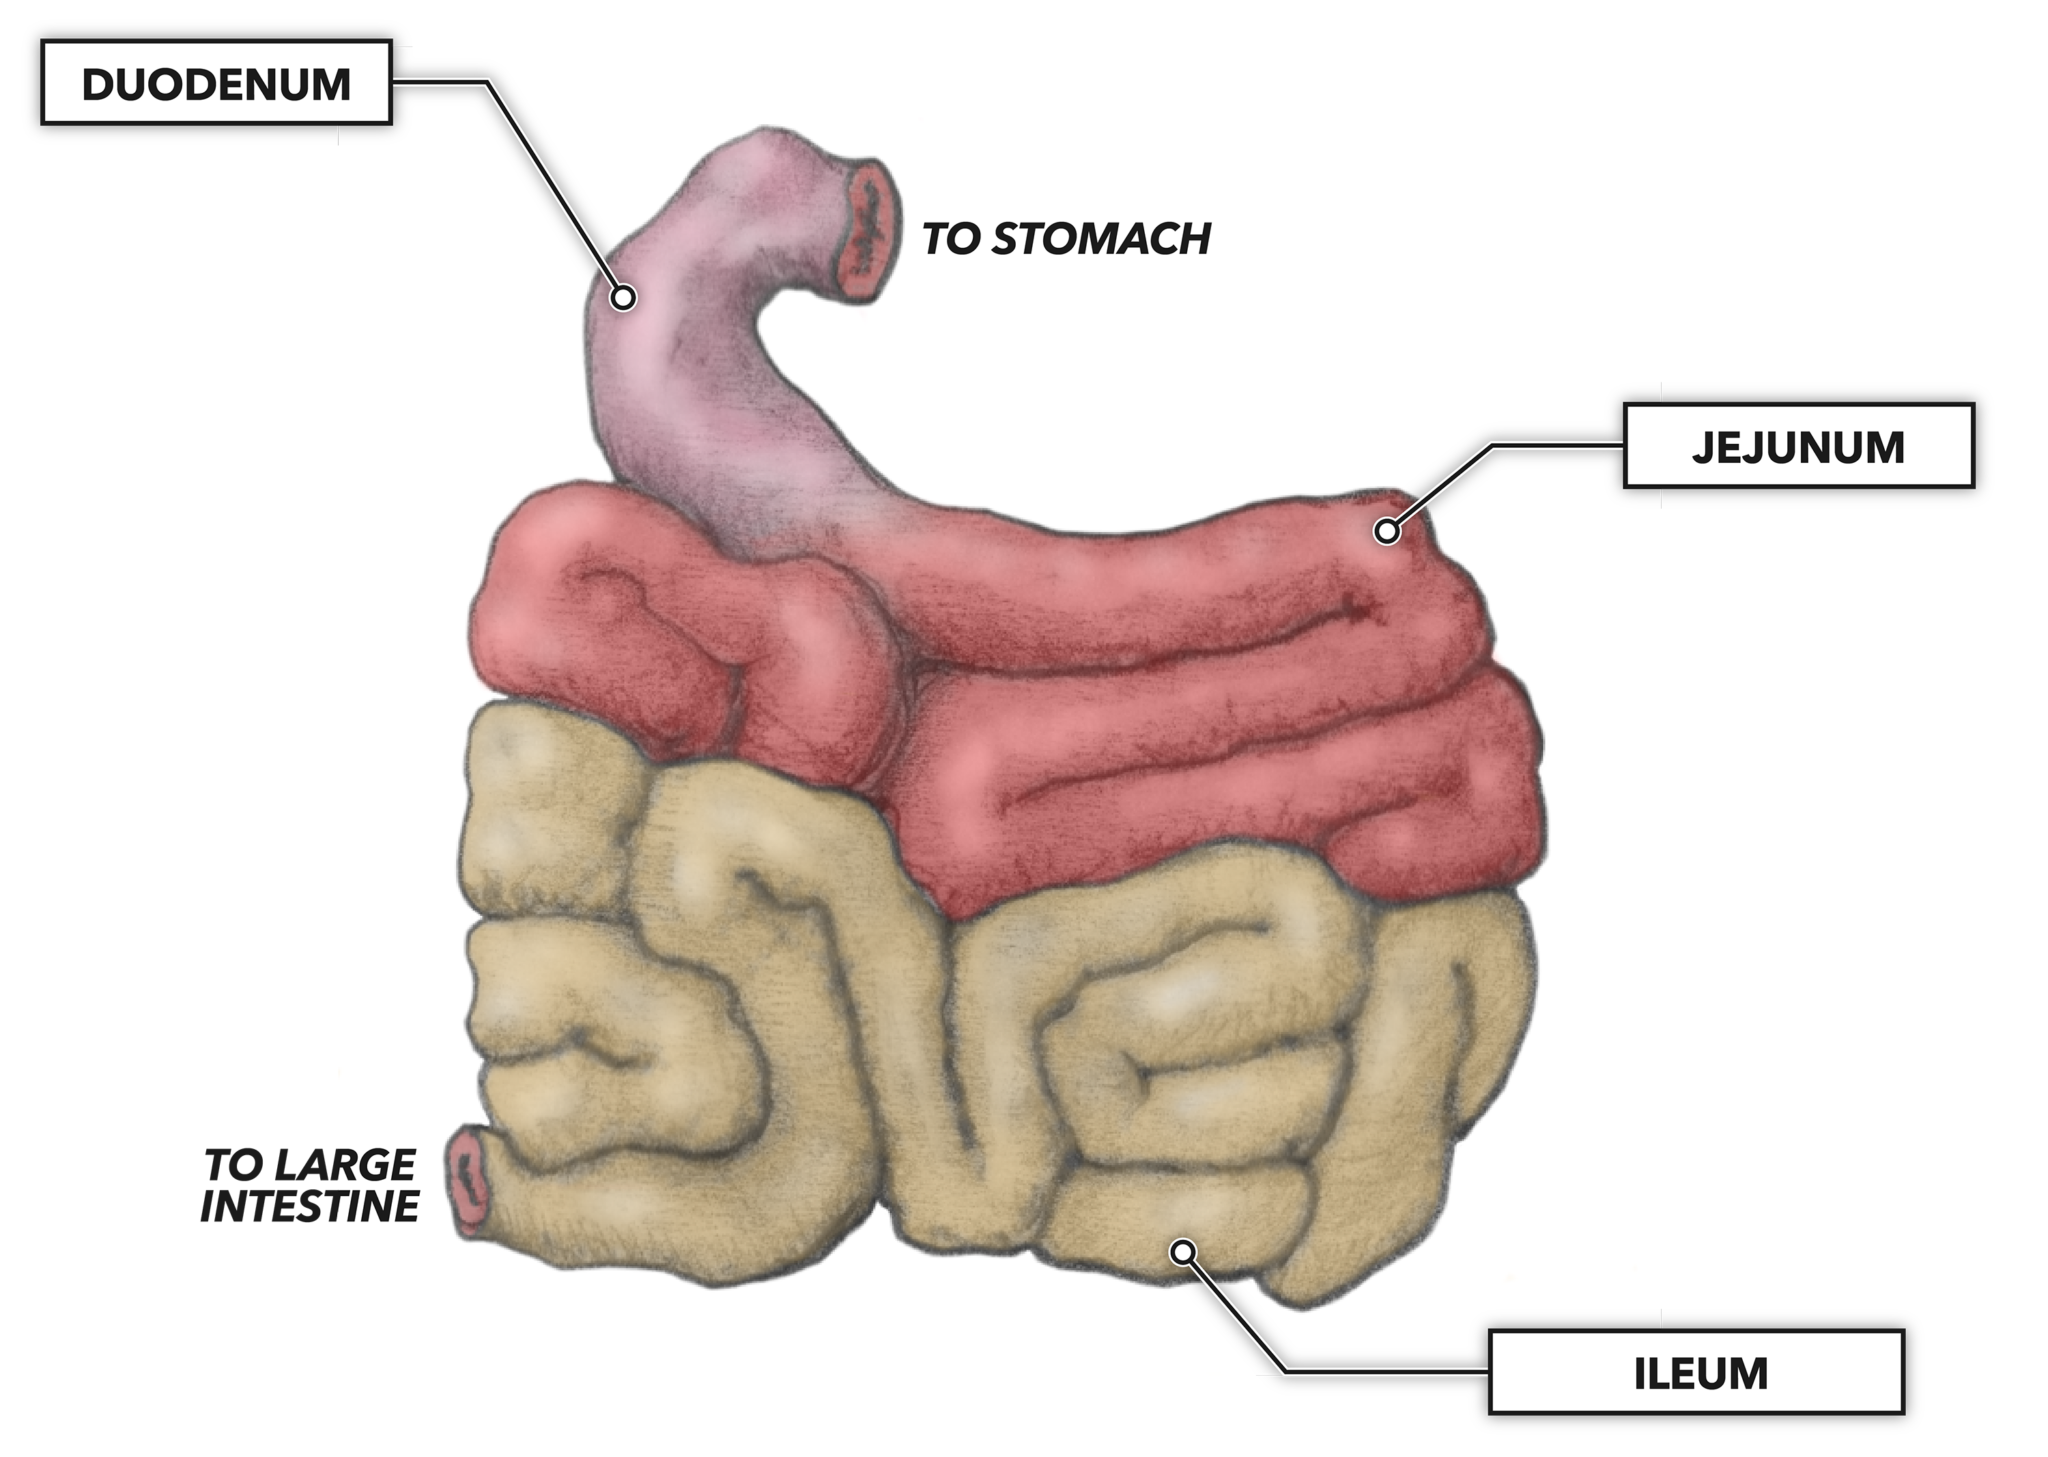
The evolutionary angle is also less dramatic than people assume. Primates generally have shorter small intestines relative to body size compared to herbivores, which makes sense because meat and cooked food are easier to break down than cellulose. Humans fall somewhere in between. Our small intestine length reflects an omnivorous diet with a heavy reliance on cooked starches, which are relatively easy to digest but still require significant surface area and time to absorb efficiently. The colon in humans is actually proportionally smaller than in most other primates, which suggests that our digestive strategy shifted toward investing more in small intestinal capacity rather than colonic fermentation. That's a broader evolutionary story but it's relevant because it explains why the small intestine takes up the bulk of the digestive labor in humans rather than sharing it with the large intestine. If you're looking at this from a clinical angle, the main takeaway is that the length serves a purpose that isn't immediately obvious from casual observation. It provides residence time for enzymatic reactions and creates enough physical distance for the stepwise absorption of different nutrients at different segments. The duodenum handles iron and calcium. The jejunum handles most macronutrients. The ileum handles B12 and bile acids. Compress the system too much and those segmental specializations lose their effectiveness. The length is essentially a delivery mechanism that spaces out these processes in time and space. That's it. There isn't a deeper mystery unless you start factoring in things like the gut-brain axis or the microbiome, which are real but separate conversations.