What Wire Guided Lumpectomy Actually Looks Like in Practice
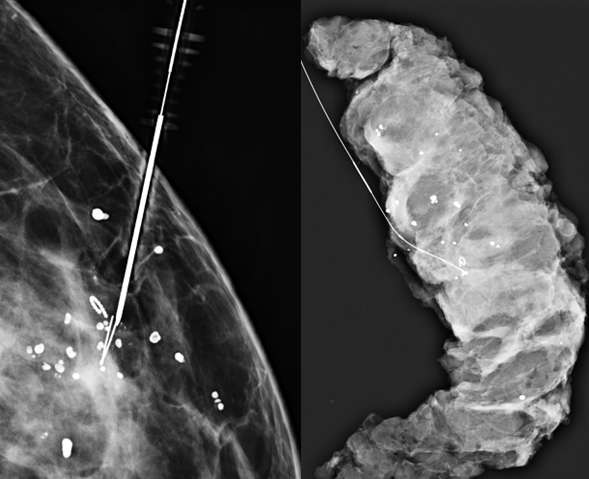
A Wire Guided Lumpectomy Video is essentially the recorded footage of a surgical navigation procedure where a thin metallic guide wire is placed under imaging guidance into or near a breast lesion before the surgeon removes it. The wire acts as a tactile landmark during the operation. What you see on screen is usually a mix of pre-op imaging localization and sometimes intraoperative fluoroscopy showing the wire tip sitting right at the target coordinates. It is not glamorous. It is functional. The video documentation exists primarily for educational purposes, quality assurance, and sometimes patient education. When I first started working with breast localization workflows, the videos my department archived looked nothing like the polished ones you see floating around professional forums. They were grainy, poorly lit, missing key labels, and often captured from angles that made it impossible to see where the wire tip actually ended up. The problem was not the equipment. It was that nobody had established a consistent filming protocol. We fixed that by mounting a small camera rig to the imaging gantry at a fixed angle and setting up a dedicated recording workflow that captured both the needle insertion sequence and the final wire position confirmation.
What to Look for in a Good Wire Guided Lumpectomy Video
Not every recording is worth keeping. A useful video needs to show specific things clearly: the imaging modality being used, the entry point on the skin, the trajectory of the wire advance, the confirmed tip location relative to the lesion, and the final stabilization of the wire before the patient is transferred to the operating room. Audio commentary from the radiologist or technologist describing each step adds significant value but is rarely present in most publicly available recordings. If you are evaluating or producing these videos, pay attention to whether the lesion is actually visible before the wire goes in. If the target cannot be seen on the imaging being used, the localization is blind and the entire procedure becomes less reliable. Magnetic seed localization has been replacing wire guidance in many centers for exactly this reason, but wires remain the standard in facilities without access to those systems. I ran into a specific issue last year where a series of our recordings kept coming back with the wire tip location ambiguous on the final spot image. The problem turned out to be that our compression paddle was slightly obstructing the lower portion of the detector field of view on certain patient builds. Patients with denser or larger breast tissue required a different paddle positioning than we had been using. We adjusted the protocol to always confirm the tip was fully within the imaged area before finalizing the wire placement, and the ambiguous recordings dropped to nearly zero after that change.
The Technical Workflow Behind These Videos
The standard approach involves mammographic or ultrasound guidance depending on the lesion characteristics. For calcifications or masses visible on mammography, stereotactic breast biopsy systems are used. The patient lies prone on the stereo table, the lesion is localized using two angled radiographic images, and the coordinates are calculated by the system. The needle is then advanced along those coordinates and the wire is threaded through the needle tract. For ultrasound-visible lesions, the procedure is performed in a supine position with real-time ultrasound guidance. The whole localization typically takes between 15 and 30 minutes. The wire has a hooked or coiled end that anchors into the breast tissue once deployed. Surgeons rely on feeling that hook during the lumpectomy to locate and excise the targeted area with clear margins. The video documentation usually captures the stereotactic coordinate readout, the needle advancement, wire deployment, and a confirmatory radiograph showing the final wire position. One thing most people do not realize is that the choice of wire type matters more than it gets credited for. The common wires like the ProTek or the Gladius have different profile sizes and deployment mechanisms. A thinner wire tracks more easily through dense fibroglandular tissue but can migrate slightly more during surgical handling. A thicker wire stays put better but may cause more tissue trauma on insertion. Selecting the wrong wire for a particular breast composition is a mistake I have seen lead to repositioning intraoperatively, which is not something you want happening after the patient is already anesthetized.
Get the Full Details

Limitations You Should Know About
Wire guided localization has real drawbacks that videos rarely highlight because they tend to focus on successful cases. The wire can migrate before surgery. This happens more often than most clinicians admit, especially in loose or ptotic breast tissue. Migration rates in the literature range from around 2 to 8 percent depending on the study and the population. When migration occurs, the surgeon may find the wire tip nowhere near where it was supposed to be, and the procedure may require re-localization or a broader excision to compensate. Another practical limitation is that wire localization requires the patient to remain still in a potentially uncomfortable position for the duration of the procedure. Stereotactic tables require prone positioning, which not all patients tolerate well. There is also a small risk of pneumothorax if the wire is advanced too deeply near the chest wall. It is rare but serious. Proper imaging confirmation of the final wire tip depth before the patient leaves the imaging suite is non-negotiable. If your facility is dealing with high migration rates or frequently localizes lesions in challenging anatomical locations, switching to magnetic seed localization or radioactive seed localization may be worth the investment. These alternatives eliminate the external wire that can migrate and provide more stable intraoperative guidance. The initial setup cost is higher but the reduction in re-operation rates for positive margins can offset it over time.
Recording and Archiving Best Practices
Quality video documentation requires consistency. Set up your recording device at the same position for every case. Make sure the patient identification, procedure date, and imaging parameters are visible in the frame or at least logged alongside the recording. Save the videos in a format that preserves diagnostic clarity rather than compressing them into something unrecognizable. We store ours in DICOM-compatible video format whenever possible so they can be linked directly to the patient record. For training purposes, I always recommend including both the pre-localization imaging that identifies the target and the post-deployment confirmation image in the same recording. Having them split across separate clips makes it harder for trainees to connect the planning phase with the execution phase. One continuous take, even if it runs 10 or 15 minutes, teaches more than three edited highlights. The video content available online varies wildly in quality. Some are professional productions from device manufacturers that look clean but skip over the complications. Others are raw clinical recordings that are messy but far more honest about what actually happens in a typical localization. The most educational ones I have encountered combine both approaches: a clear walkthrough of the standard technique followed by a segment showing a problematic case and how it was resolved.