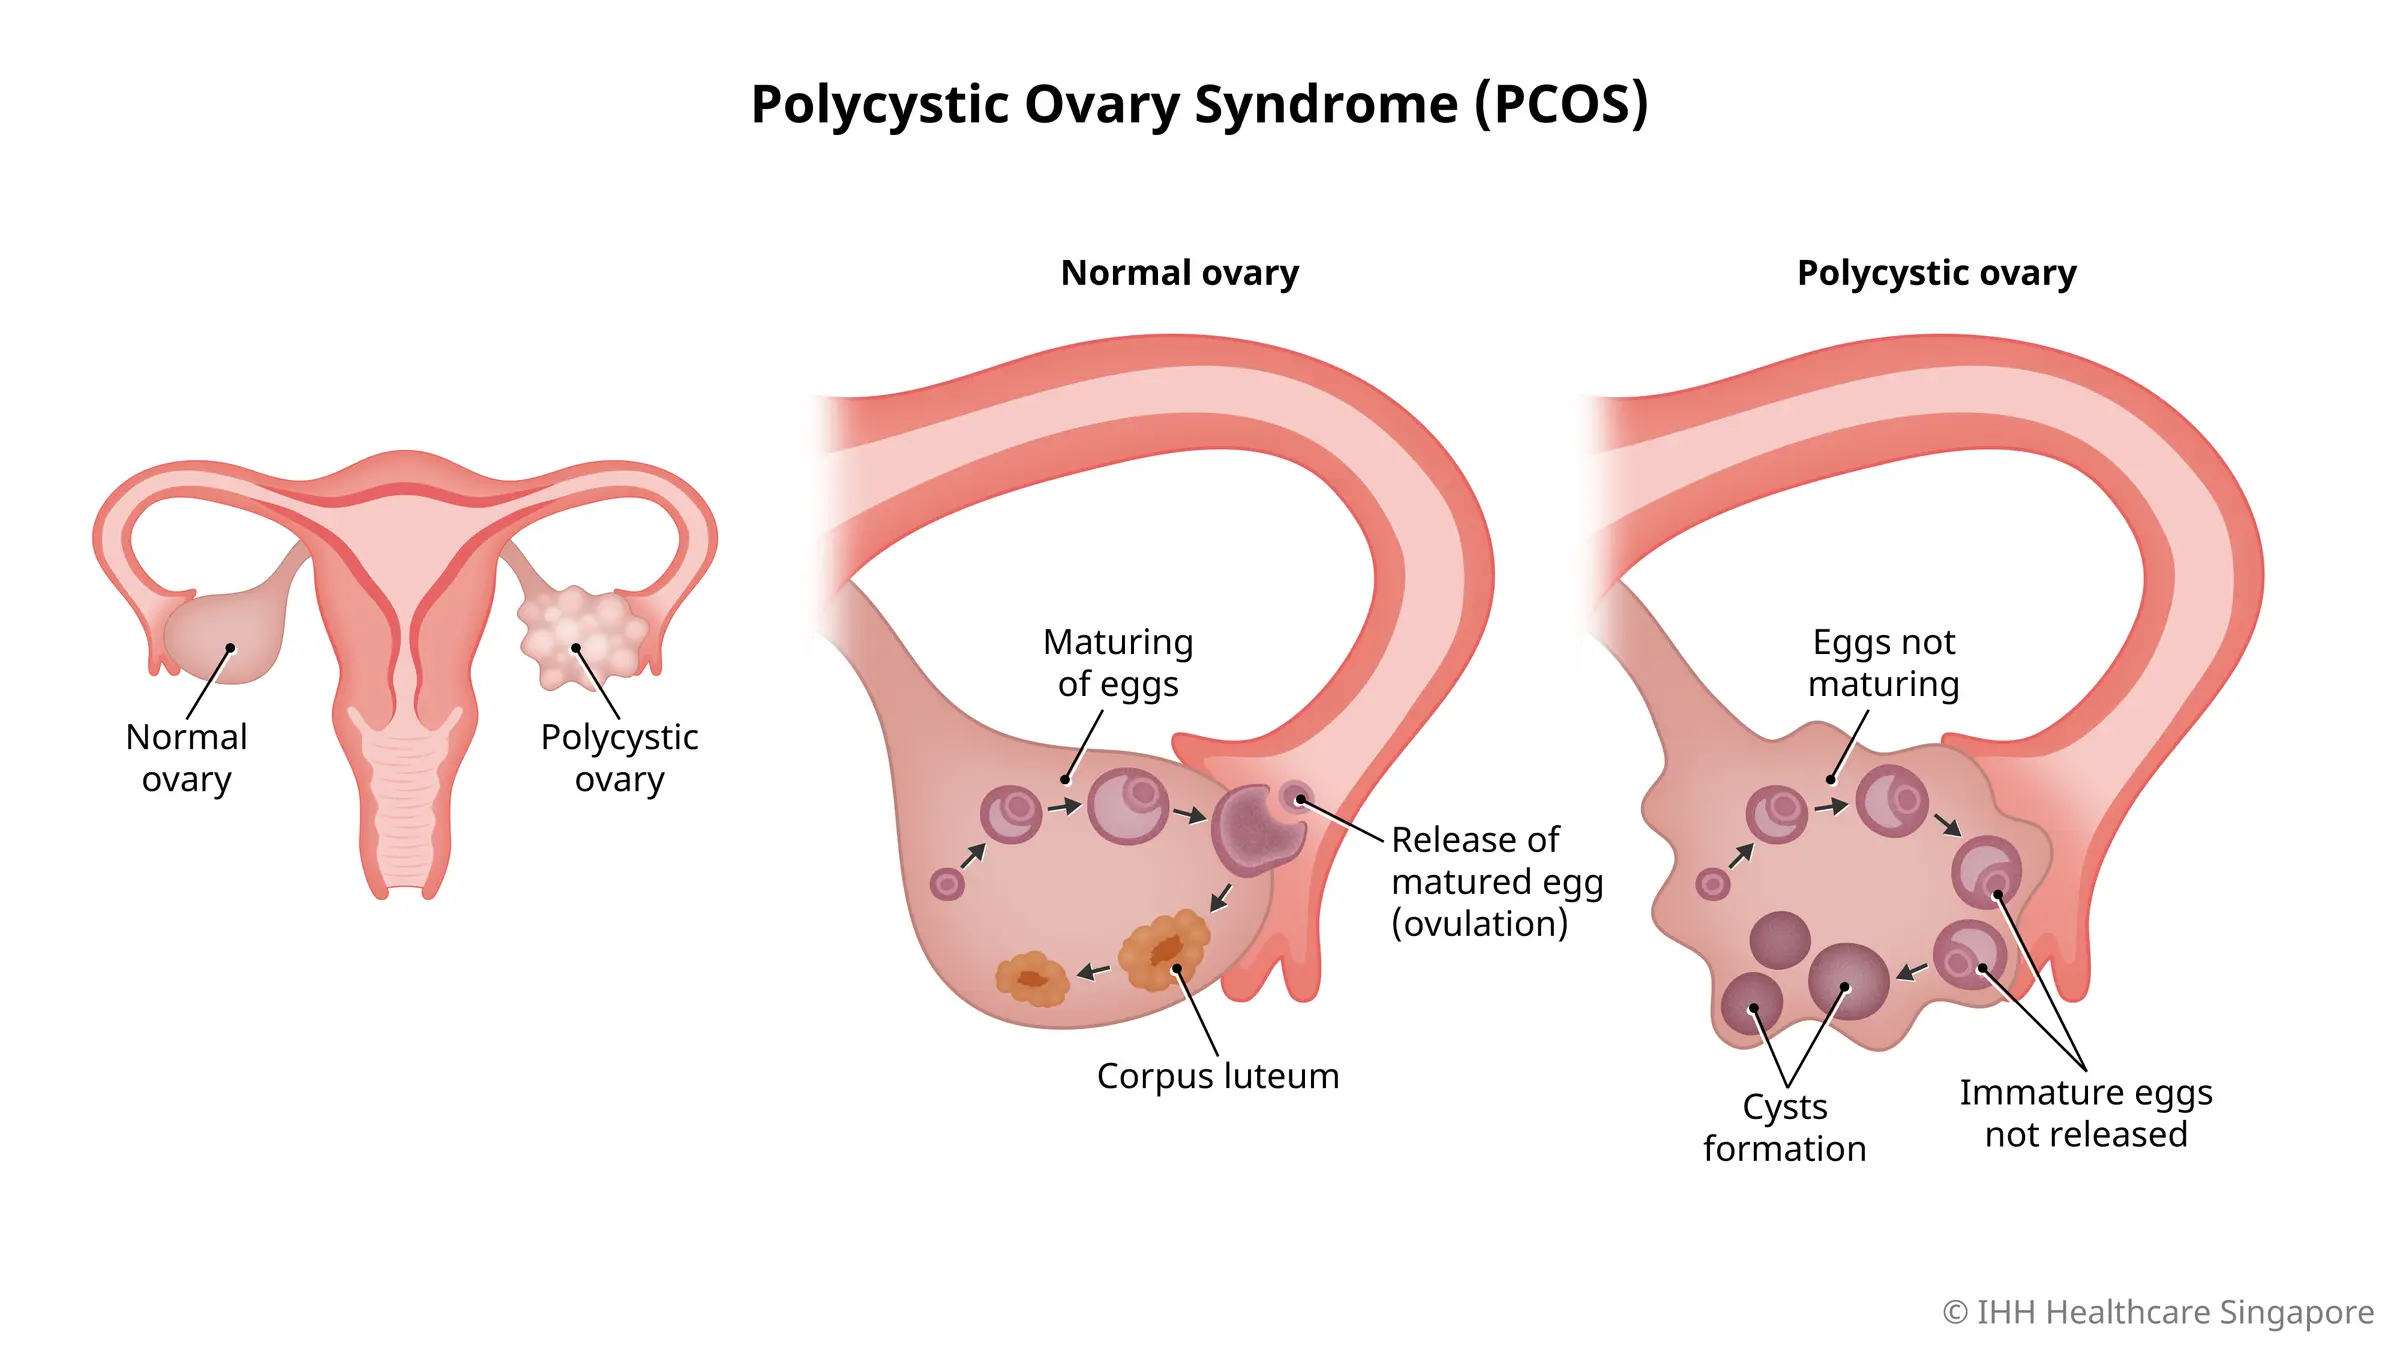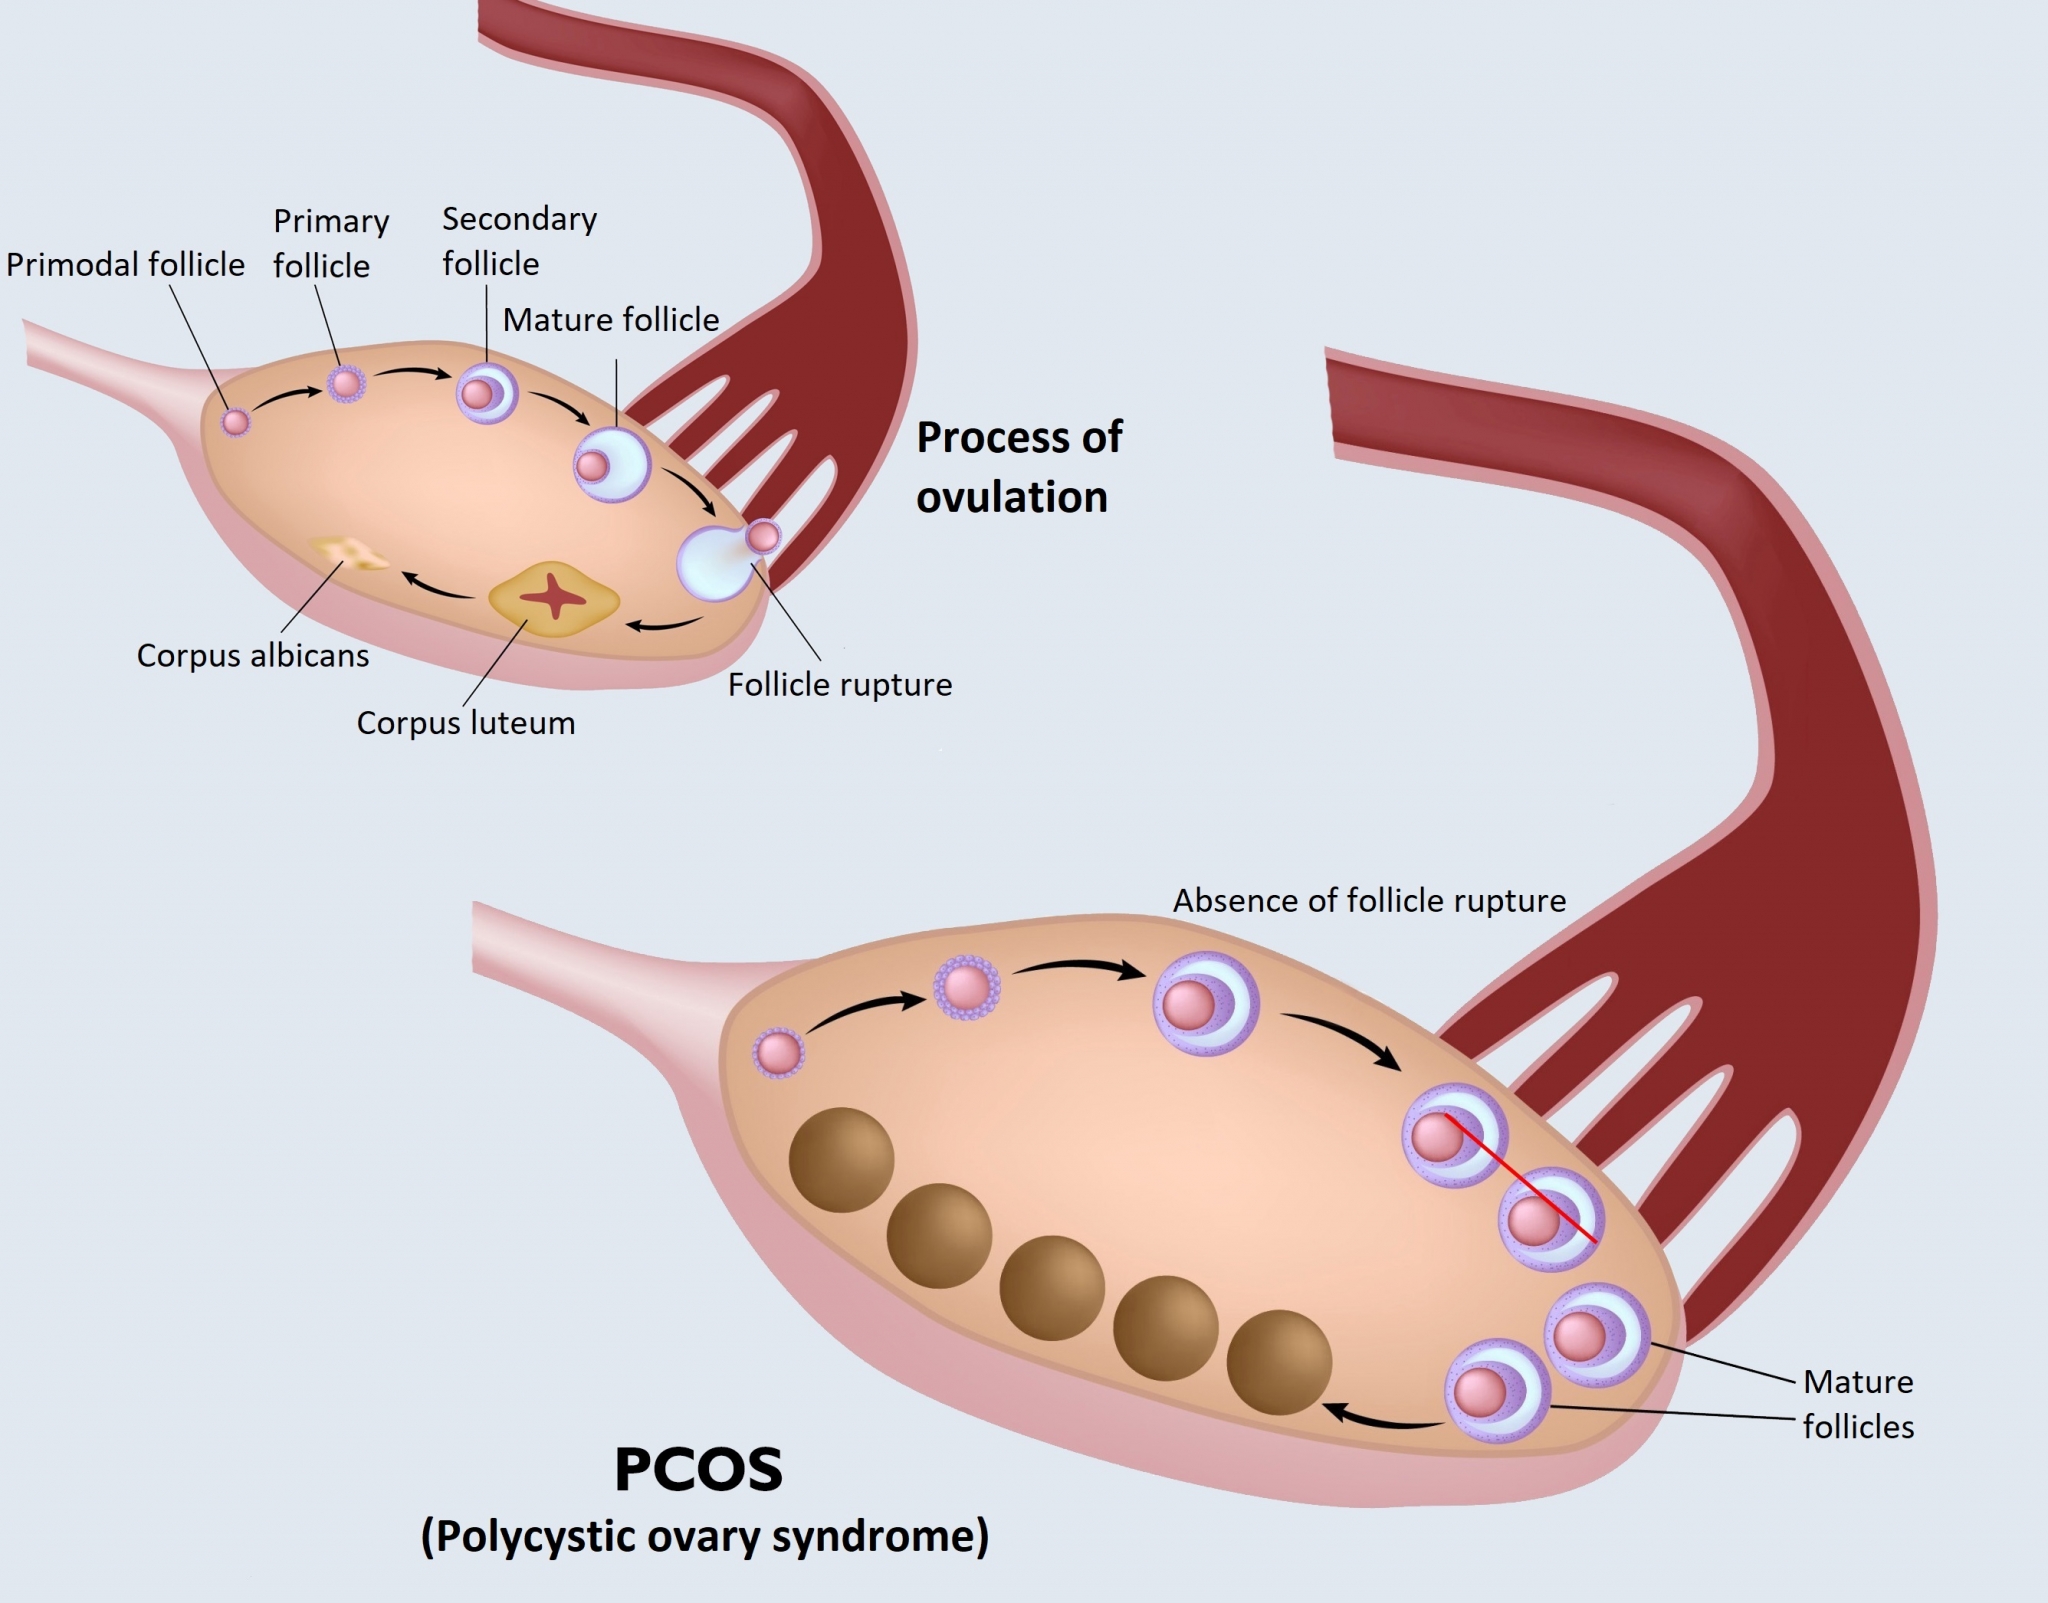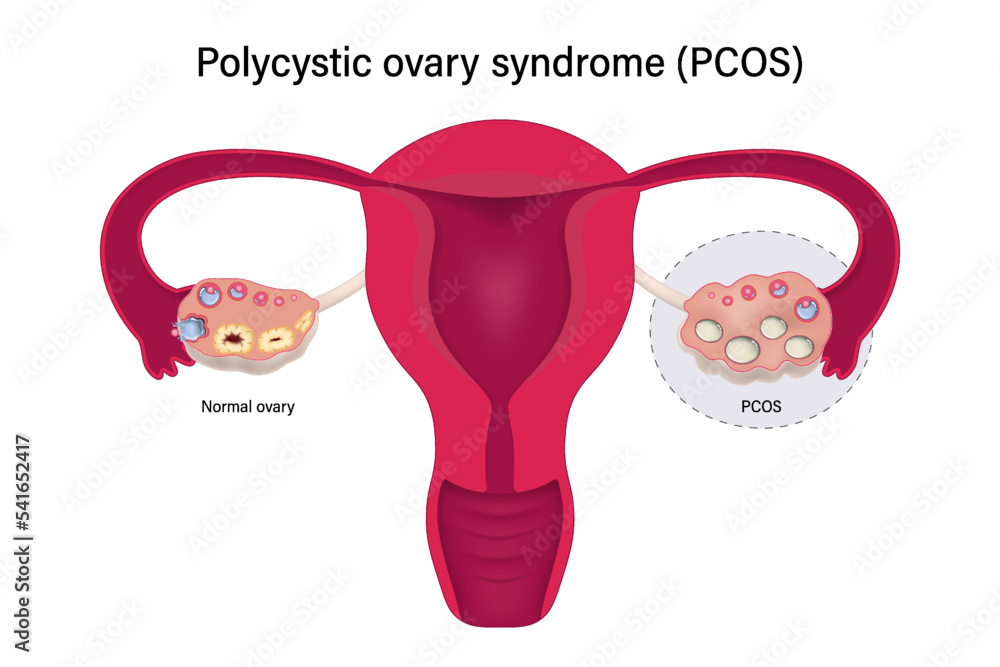
What Actually Happens When You Have PCOS
Most people get told their ovaries have "cysts" and that's that. The reality is messier than that one word implies. Polycystic ovary syndrome is an endocrine disorder where your body produces more androgens than it should, which throws off ovulation, messes with your cycle, and creates a cascade of metabolic effects that have nothing to do with your reproductive organs alone. I spent years watching patients and myself navigate this because I have it. Not the textbook version. The version where your doctor says "just track your cycle" and you try to track a cycle that hasn't shown up consistently in eleven months. Here is how to actually work with it instead of against it.
Diagnosing With Pcos Polycystic Ovary Syndrome
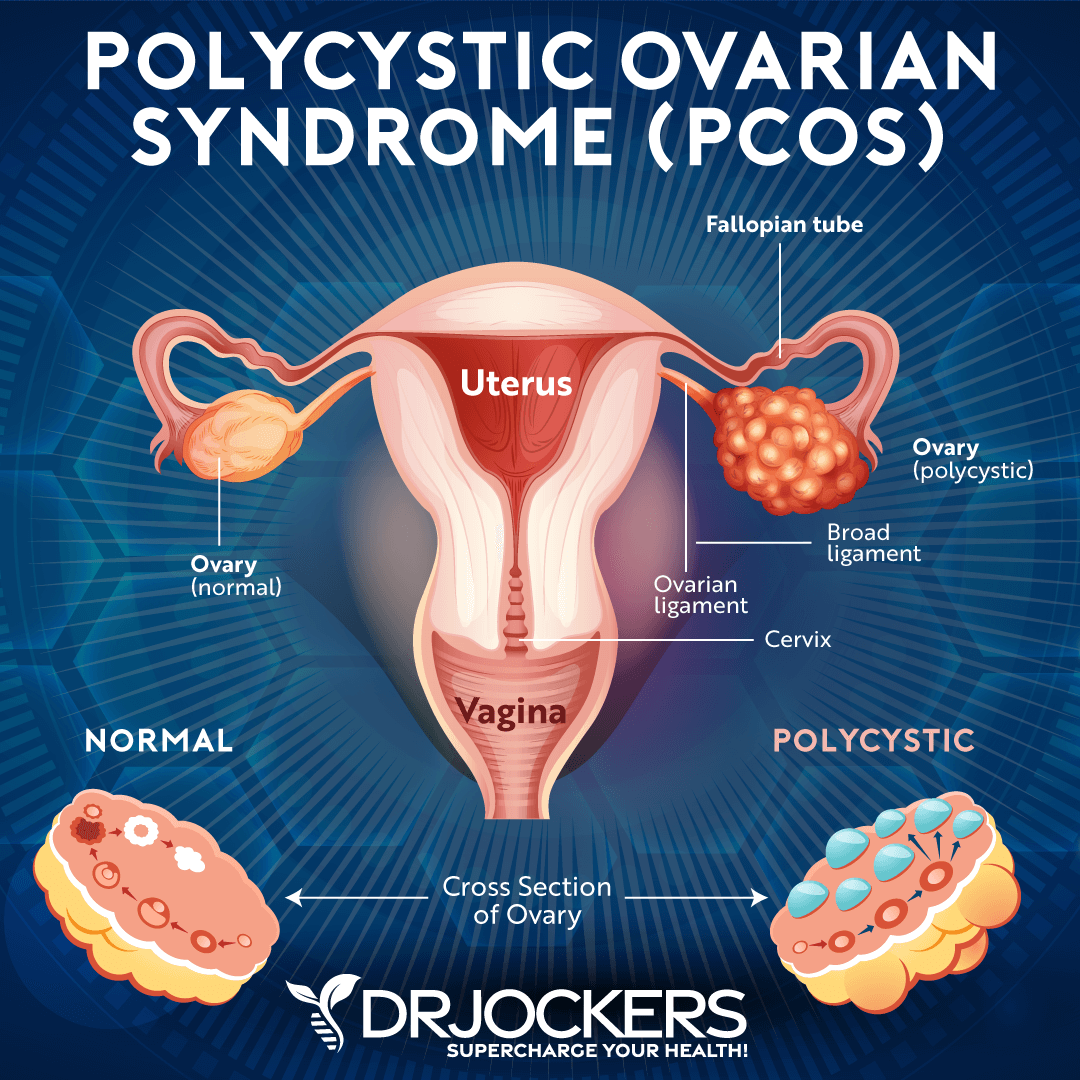
The Rotterdam criteria require two out of three: irregular or absent ovulation, clinical or biochemical signs of high androgens, and polycystic ovarian morphology on ultrasound. The third one is the most misunderstood. Up to twenty percent of women without PCOS also have polycystic-appearing ovaries on ultrasound. Finding follicles on a scan does not confirm the syndrome by itself. You need the other two markers present. The thing nobody tells you during your first appointment is that ultrasound timing matters. If you do get scanned mid-cycle when you actually are ovulating occasionally, the follicles can look normal. That does not mean the polycystic appearance was a false reading earlier. It means ovulation happened to align with the scan window. For anyone in this situation, I recommend requesting the ultrasound be scheduled specifically in the early follicular phase, days three through five of a bleed, even if that bleed is weeks late compared to what a calendar would predict.
Why the Bloodwork Matters More Than the Scan
When you actually go get labs drawn, ask for a full androgen panel. Total testosterone is useful but incomplete. Free testosterone, SHBG, and androstenedione give you a much clearer picture of what is actually circulating in your system. SHBG gets suppressed by insulin resistance, which is the engine driving most of the androgen excess in PCOS. Low SHBG means more free testosterone floating around doing things like triggering hirsutism and scalp hair thinning. I once had a patient whose total testosterone came back perfectly normal, but her free testosterone was elevated and her SHBG was at the low end of the reference range. She had significant acne and hair loss. If we had only looked at total testosterone, we would have missed the problem entirely and sent her home with nothing to do. This is a common enough blind spot that it bears repeating. Always push for free testosterone and SHBG alongside the standard panel.
Get the Full Details
Managing It Without Obsessing Over Perfection
The standard advice is weight loss and diet changes. That advice is correct but incomplete and often delivered in a way that makes people feel like the problem is purely behavioral. Insulin resistance is the core driver for roughly seventy percent of people with PCOS, regardless of body size. Even lean PCOS involves some degree of insulin dysregulation. Metformin is a first-line medication for this reason. It improves insulin sensitivity, which indirectly lowers androgen production from the ovaries. I prescribe or support metformin use in the majority of cases I work with, but I also tell people upfront that it is not a magic switch. It typically takes three to four months to see meaningful cycle regularization. Side effects like gastrointestinal discomfort are common in the first few weeks unless you start low and titrate slowly. Extended-release formulations help significantly with that. If you cannot tolerate metformin, myo-inositol at two grams twice daily has decent evidence behind it for improving ovulation frequency and insulin sensitivity, though the effect size is smaller than pharmaceutical options. Dietarily, the most practical approach is not cutting carbs to near zero. It is reducing glycemic load and prioritizing protein and fiber at every meal. A study published in the Journal of Clinical Endocrinology and Metabolism showed that a moderate carbohydrate reduction combined with resistance training improved menstrual cyclicity more effectively than diet alone over a six-month period. The resistance training part is not optional fluff. Muscle tissue is a major site for glucose disposal, and increasing lean mass directly improves insulin sensitivity independent of weight change.
The Cycle Tracking Trap
If you have irregular cycles, standard period tracking apps will frustrate you. They predict based on historical averages that do not exist. You will get a prediction for a period that arrives three weeks early or six weeks late, and you will lose trust in the tool. I stopped using prediction-based apps entirely and switched to symptoms-only logging. I track basal body temperature and cervical mucus to detect whether ovulation actually occurred, rather than relying on an algorithm to guess when it should happen. This approach takes more effort upfront. You need a basal thermometer and about ten minutes each morning before getting out of bed. But it gives you actual data instead of false confidence. After three months of this, you will know whether you are ovulating at all, roughly how long your follicular phase is when it does happen, and whether your luteal phase is adequate. That information is genuinely useful for deciding whether to seek fertility support or adjust treatment.
Fertility Considerations
PCOS is the leading cause of anovulatory infertility. If you are trying to conceive, letrozole is now the first-line ovulation induction agent, not clomiphene citrate. The legault and subsequent trials showed higher live birth rates and lower multiple pregnancy rates with letrozole compared to clomiphene. Clomiphene is still used, but it has anti-estrogenic effects on the endometrium that can thin the uterine lining and reduce implantation success even when ovulation occurs. If you respond to clomiphene but do not conceive after three to four cycles, switching to letrozole is a reasonable next step. I also want to mention a practical issue that comes up repeatedly. Women with PCOS often have more available follicles at baseline, which means they respond robustly to ovulation induction. That is good until it is not. Monitoring is essential. Without ultrasound monitoring, you risk ovarian hyperstimulation or multiple follicular development, which increases the risk of multiples and complicates the cycle unnecessarily. A single monitored cycle with letrozole and an ultrasound at day twelve or thirteen is worth far more than three unmonitored cycles.

Long-term Health Beyond Fertility
PCOS increases risk for type two diabetes, cardiovascular disease, endometrial hyperplasia, and depression. The endometrial risk is often overlooked. Without regular progesterone exposure from ovulation, the uterine lining builds up unchecked. This is why inducing a bleed every one to three months with progesterone is standard care for anyone not trying to conceive, even if they do not mind irregular bleeding. It is not about convenience. It is about cancer prevention. Screening should include fasting glucose or HbA1c at diagnosis and then every one to three years depending on results. Lipid panels should be checked as well. A simple transvaginal ultrasound once to establish baseline ovarian morphology is reasonable, but repeating it annually is unnecessary unless clinical status changes significantly. Insurance companies sometimes push back on this, so document the diagnostic criteria clearly when ordering. The mental health component deserves more attention than it gets. The hormonal fluctuations, the visible symptoms like hair growth and acne, the fertility struggles, and the chronic uncertainty all contribute to higher rates of anxiety and depression. Screening for mood disorders should be routine, not something you bring up only after a crisis. I have found that acknowledging this openly with patients reduces the isolation factor substantially, even if the underlying biology remains unchanged.