
What Actually Happens When You Lose Your Gallbladder
Most people come to this topic because surgery is already over or scheduled and the doctor said something vague like "watch your fat intake" and then went back to reading charts. The gallbladder stores bile and releases it in concentrated bursts when you eat a fatty meal. Without it, bile drips continuously from the liver into your small intestine. That changes how your body handles fat, fiber, and even certain sugars. It's not a disaster, but it's also not nothing. I've sat across from enough patients post-cholecystectomy to know the difference between what the pamphlet says works and what actually works when you're at the grocery store at 7pm on a Tuesday. The good news is your liver doesn't stop working. It keeps making bile. The bad news is that continuous drip is optimized for steady, small fat loads, not for a slice of deep-dish pizza that would've triggered a massive bile dump before surgery. So you adjust. Not forever necessarily, but for a while, and in some cases long-term if your bowel has adapted poorly.
Without A Gallbladder Diet: The Practical Framework
I don't use fancy acronyms or phased programs. The core principle is simple: control fat quantity per sitting, increase soluble fiber gradually, and watch for triggers that are individual-specific. Fat per meal should generally stay under 10 to 15 grams initially. That's not a hard rule forever, but it's where most people start. You rebuild tolerance slowly. Soluble fiber is useful because it binds to excess bile acids in the intestine and reduces the dumping that causes urgency and diarrhea. Oats, peeled apples, psyllium husk, and chia seeds soaked in liquid are common tools. I had a patient once who swore by a tablespoon of psyllium mixed into water 20 minutes before lunch. She reported a noticeable drop in post-meal cramping within a week. It wasn't magic. It was physics: more gel-forming fiber, less free bile acid sliding through to irritate her colon. Insoluble fiber is a different story early on. Raw vegetables, bran, skins of fruits, nuts, and seeds can be abrasive to an already sensitive gut. I usually recommend cooking vegetables thoroughly and peeling them for the first several weeks. Roasted carrots and zucchini are fine. A raw salad with kernels of corn and unpopped popcorn on the side is a rough idea for day three post-op.
Small meals beat large meals. Three a day works for some people, but splitting into four or five smaller feedings reduces the bile demand at any single point in time. That's probably the single easiest adjustment with the highest return on effort.
Get the Full Details

Common Triggers and What to Avoid Early On
Fried foods are obvious. Processed meats like bacon, sausage, and pepperoni carry concentrated fat with zero redeeming fiber. Full-fat dairy can be problematic for the first month or two. Heavy creams, butter-loaded sauces, and creamy soups are common sources of unexpected fat spikes. I've seen people get blindsided by a seemingly healthy smoothie that had a quarter cup of nut butter and half a avocado thrown in. That's easily 30 grams of fat in one drink. Your new digestive system is not going to handle that well. Sugar alcohols deserve mention. Sorbitol, mannitol, and xylitol, found in sugar-free gum, protein bars, and diet candies, pull water into the gut and can cause severe gas and loose stools. Post-gallbladder, that effect is amplified. I learned this the hard way with a patient who thought switching to sugar-free products was a smart dietary swap. Within 48 hours she was dealing with cramping so bad she considered going back to the surgeon's office. The workaround was straightforward: eliminate sugar alcohols entirely for a few weeks, then reintroduce one at a time to find her personal threshold. Most people never get comfortable above half a gram per sitting. Caffeine is another thing that surprises people. It stimulates gallbladder contraction in people who still have one, and it stimulates colonic motility in everyone. Without a gallbladder, the result is often just faster transit and looser stools, especially with coffee on an empty stomach. Black coffee in the morning is fine for some. An extra-large vanilla latte with whole milk is not. My recommendation is to track caffeine timing separately from meals for a week and see if your bowel patterns change.
High-fat dairy substitutions like coconut cream or excessive olive oil in smoothies are also traps. Just because it's plant-based doesn't mean it's gentle. Coconut oil is nearly pure fat. A single tablespoon adds about 14 grams. Two tablespoons in a green smoothie puts you past the initial daily tolerance many people need to respect.
What Actually Helps Beyond the Basics
Bile acid sequestrants like cholestyramine or colesevelam are prescription options for people who develop chronic bile acid diarrhea after surgery. If you're passing loose stools daily and standard dietary tweaks aren't touching it, talk to your doctor about this. It's not a first-line intervention, but it's highly effective for the right patient. I had someone who tried every diet variation and finally got relief on a low dose of cholestyramine taken with dinner. She described it as life-changing in a way that made me glad we'd exhausted food modifications first. Mediterranean-style eating patterns tend to align well with post-cholecystectomy needs without being extreme. Lean proteins like chicken breast, fish, and tofu. Olive oil used sparingly as a finish rather than a cooking medium. Well-cooked grains. Plenty of cooked vegetables. It's not a trend. It's just food that happens to be lower in concentrated fat and higher in soluble fiber, which is roughly what your system is asking for. Hydration matters more than people realize. Bile acids in the colon draw water into the lumen. If you're not replacing fluids, you can tip into dehydration while also dealing with frequent bowel movements. Water, broth, and electrolyte solutions without sugar alcohols are reasonable choices. I've told patients to keep a bottle of diluted electrolyte mix at their desk or in their car on days when they know they'll be eating out.
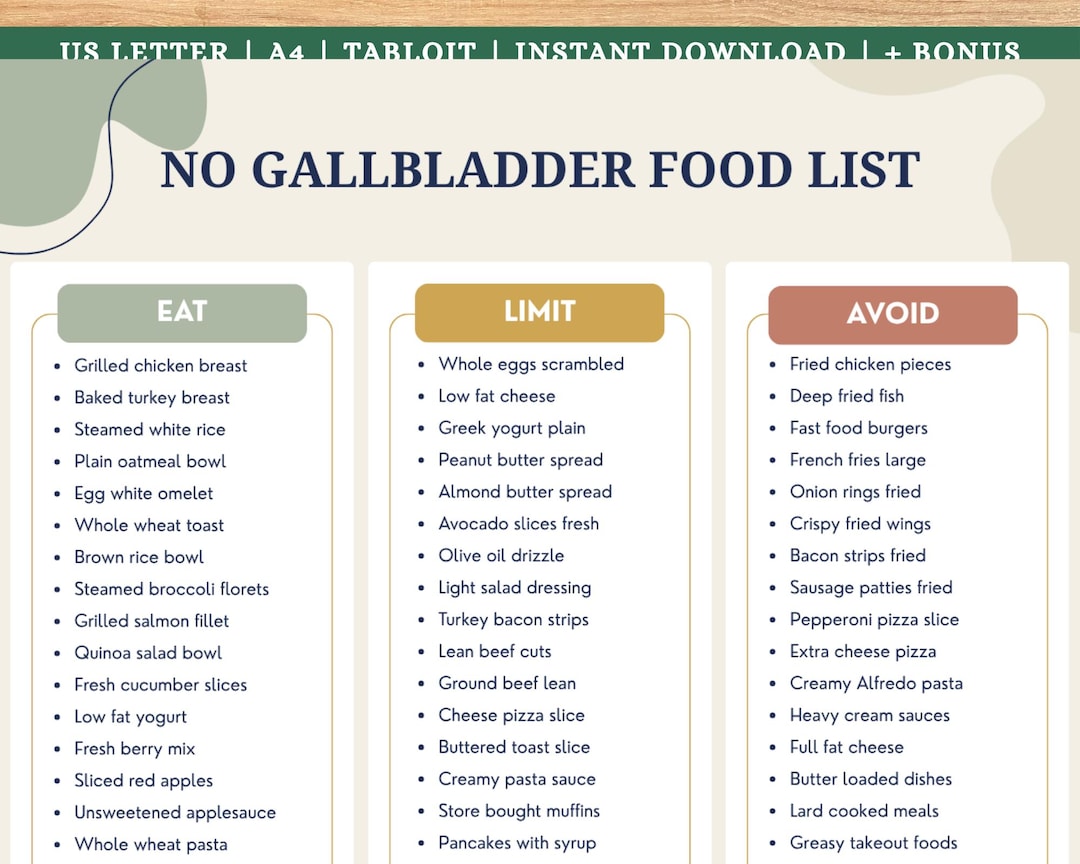
Lean protein sources are your foundation. Eggs are tricky because the yolk is almost entirely fat. Some people tolerate one yolk fine. Others can't manage half. I recommend testing a single yolk on an empty stomach during a low-stress day, not after a long drive or before a meeting. Same with egg whites, which are safe for almost everyone. Skinless poultry, white fish, lentils, and tofu are reliable staples. Ground turkey that's labeled 93 percent lean still has enough fat to bother some people, so check the label and prepare accordingly.
A Few Things Nobody Warns You About
The first few weeks after surgery, your appetite may be weird. Some people lose interest in food entirely. Others crave things that sound awful in retrospect. Both are normal. Don't force large meals. Graze on safe foods. Crackers, plain rice, bananas, and toast are boring for a reason. They work. Gas and bloating can linger longer than diarrhea for some people. Bile acid changes alter your gut microbiome composition temporarily. That shift can produce extra gas as bacteria adjust. Probiotic yogurt with live cultures may help, but again, watch the fat content. Some probiotic supplements are taken on an empty stomach and won't add fat to the equation. Worth trying if bloating is your main complaint. Alcohol is another thing people forget to factor in. It irritates the stomach lining and can speed up gut transit. A glass of wine with a carefully prepared meal is fine for most. A night of tequila shots after surgery is a recipe for waking up in distress. I've seen it.
There's no universal timeline. Some people feel back to normal within a month. Others take six months or longer to find their baseline. A small number never fully adapt and need long-term management of bile acid diarrhea or fat intolerance. That's the part doctors sometimes gloss over. Most people improve. Not everyone returns to exactly what they were before. Setting realistic expectations now saves frustration later.

When to Call the Doctor Instead of Tweaking Dinner
Severe abdominal pain that doesn't pass with bowel movement, yellowing of the skin or eyes, persistent vomiting, fever with chills, or blood in stool are not diet problems. Those are medical issues that need evaluation. Dietary adjustments won't fix a retained stone in the bile duct or an infection. If any of those show up, stop reading and seek care. For everything else, keep a simple log. Food, time, symptoms, severity on a scale of one to ten. Do it for two weeks. Patterns emerge faster than you'd expect. I've had people discover that their trigger wasn't fat at all but rather eating too fast, or that dairy was the culprit, not the avocado they blamed for everything. The log cuts through the noise. There's also value in working with a registered dietitian who has actual experience with post-surgical GI changes, not just one who follows a generic template. They can help you design a plan that fits your schedule, your budget, and your specific symptoms instead of handing you a handout that assumes you have time to cook from scratch every night. If that's available through your insurance or hospital system, use it. It's not a luxury in most cases.


