How to Use a Women Bmi Chart Without Misreading It
Most people look at a BMI chart and think they understand what it says. They do not, really. The chart gives you a number and a category. That is where understanding usually stops, and that is where mistakes start. A BMI is weight in kilograms divided by height in meters squared. The formula is trivial. The interpretation is where things get messy, especially when you are looking at a Women Bmi Chart rather than the generic one printed on health pamphlets. Women and men carry weight differently. The same BMI value can mean something fairly different between the two, which is why some charts split them out.
Where to Find a Women Bmi Chart
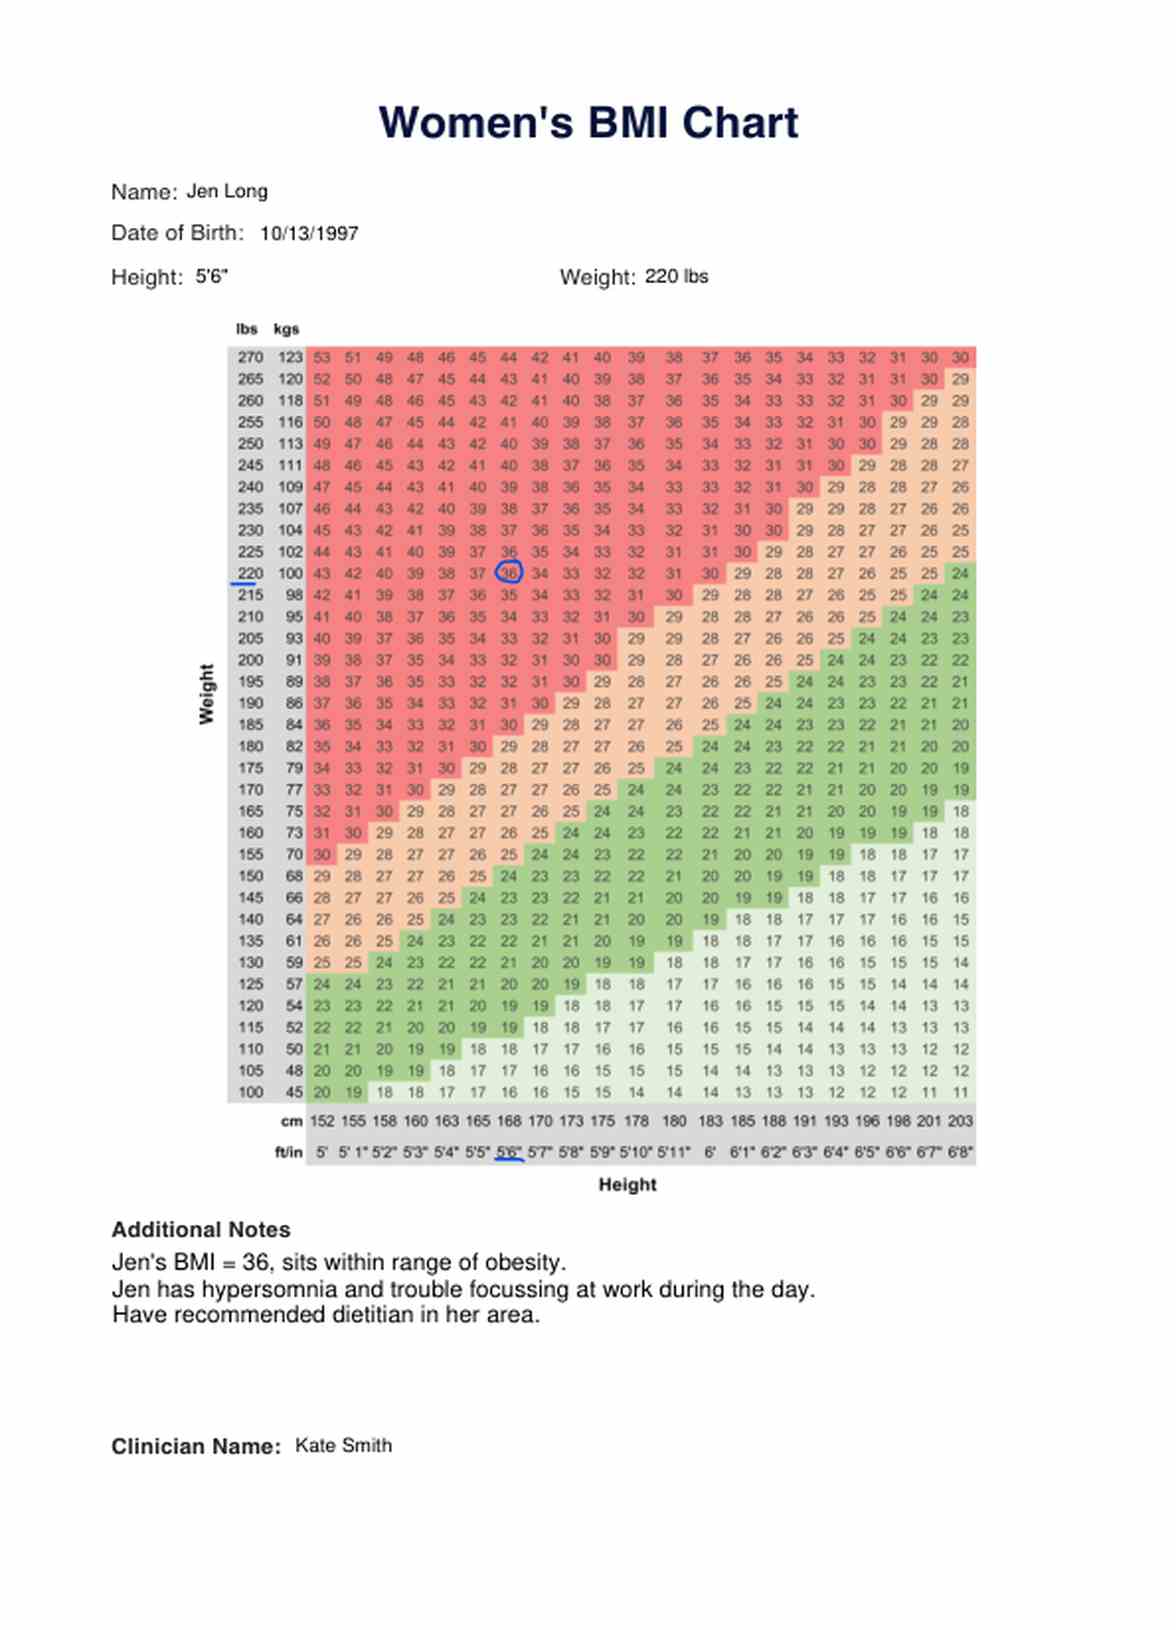
You can grab one from the CDC website or WHO documentation pages. The CDC ones are the ones most people actually use in clinical and research settings in the United States. They publish downloadable PDF tables that map BMI values to categories for adult women by age group as well. I tend to bookmark the 2000 CDC growth reference charts page because it has the raw numbers you need without all the browser bloat. Search for "CDC BMI tables for girls and women" and you will find the direct links. Save the PDF. It will save you time later when you need to look up a precise cutoff without opening a browser. Start with your height and weight. Convert to metric if you need to. A woman who is 1.68 meters tall and weighs 72 kilograms has a BMI of about 25.5. On a standard women's chart, that lands in the overweight range. The categories are underweight below 18.5, normal weight from 18.5 to 24.9, overweight from 25 to 29.9, and obese at 30 and above. Those are the cutoffs most charts use. They come from WHO definitions and have been adopted broadly. Here is the thing most people miss. The chart does not tell you body composition. It does not distinguish muscle from fat. A woman who lifts weights regularly and has a higher lean mass can sit at a BMI of 27 and be metabolically healthy, while another woman at a BMI of 23 with low muscle mass and high visceral fat can have worse metabolic markers. I learned this the hard way when I was reviewing intake forms for a small clinic run. A patient was flagged as overweight by the chart, but her blood work and blood pressure were completely normal. She was a competitive rower. I recommended we add waist circumference and body fat percentage measurements to the intake so we stop treating the BMI number like a diagnosis.
A Practical Problem I Faced
One edge case that comes up a lot involves pregnancy. Standard BMI charts do not account for it. A pregnant woman will gain weight, and her BMI will rise. If you plot her on a regular chart during the second or third trimester, the result is meaningless. The workaround is to calculate BMI using pre-pregnancy weight, or to use the pregnancy-specific weight gain guidelines from the Institute of Medicine instead. I started noting the pregnancy status on forms and recalculating based on pre-pregnancy weight when needed. It took about thirty seconds and prevented a lot of confusion. Another edge case is older women. As women age, they tend to lose height due to spinal compression and bone density changes. If you use a current height measurement that is slightly lower than their actual adult height, the BMI goes up artificially. I encountered this when a woman in her late seventies came in with a recorded height that was about four centimeters shorter than her documented adult height. Her BMI spiked into the obese range on paper, but it was just a measurement error. I suggest keeping a record of adult height and using that for BMI calculations whenever possible, especially for patients over sixty.
Get the Full Details

What the Chart Leaves Out
BMI was designed as a population-level screening tool. It was never meant to be a precise individual health assessment. It correlates reasonably well with body fat at a group level, but the correlation is not tight enough to use as a standalone diagnostic. For women, the issues are slightly more pronounced because fat distribution patterns vary widely. Some women store fat subcutaneously, especially around the hips and thighs. Others store it viscerally, around the organs. Visceral fat is the more dangerous kind metabolically, and BMI cannot tell you which pattern a person has. Waist-to-hip ratio is a better signal for that, and it is easy to measure. I always add it to my notes when I am doing health screening. There is also the issue of ethnic variation. BMI cutoffs were largely based on Caucasian and European datasets. For women of South Asian or East Asian descent, the risk of metabolic disease at a given BMI tends to be higher. The WHO and some national health bodies have suggested lower cutoffs for certain ethnic groups, like using 23 as the overweight threshold and 27.5 as the obesity threshold for South Asian populations. If you are working with diverse populations, you should be aware of these adjustments and use them when appropriate.
When to Stop Using It
There are moments when BMI simply does not work. People with eating disorders often get flagged incorrectly because the chart cannot differentiate between a low weight caused by illness and one caused by habit or athleticism. Amputees throw off the calculation too since the weight is reduced but the height stays the same. Bodybuilders and athletes in weight-class sports are the most common case where the number is misleading. In those situations, you need a different tool. DEXA scans, hydrostatic weighing, or even simple skinfold measurements will give you a clearer picture. I stopped relying on BMI alone for any client who trains resistance sports and switched to tracking body fat percentage and strength metrics instead. Use the chart as a starting point, not a verdict. The number on the page is data, not destiny. Pair it with other measurements, ask questions, and remember that a single number was never going to capture the whole story of a person's health.