Understanding the Practical Layout of Female Reproductive Anatomy
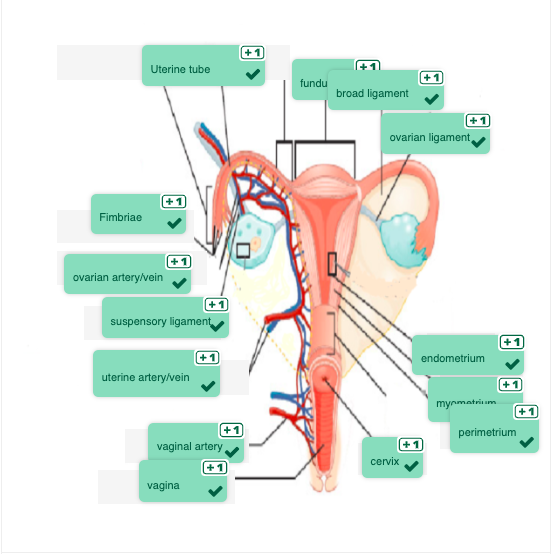
The female reproductive system is a collection of internal and external organs that work together for reproduction, hormonal regulation, and menstrual function. If you are studying this for clinical practice, ultrasound work, or patient education, memorizing labels from a textbook diagram will get you only so far. The real challenge is understanding spatial relationships in three dimensions and knowing which structures show up where on imaging or during examination. The external structures, collectively called the vulva, include the mons pubis, labia majora, labia minora, clitoris, vestibular bulbs, and greater vestibular glands. The clitoris is often underemphasized in basic anatomy courses, but it has internal crus structures that extend roughly 9 centimeters along the pelvic sidewall. This matters clinically because lesions or pain in that region can radiate along paths that are not obvious on surface inspection alone. Internally, the key organs are the vagina, cervix, uterus, fallopian tubes, and ovaries. The uterus sits in the midline of the pelvis between the bladder anteriorly and the rectum posteriorly. Its position varies significantly between individuals. A retroverted uterus, present in roughly 20 to 25 percent of women, sits tilted backward toward the spine rather than forward toward the bladder. This is a normal anatomical variant, but it changes how you approach pelvic exams and where you expect to feel the cervix during bimanual palpation. If you are new to pelvic exams, you will feel this immediately. The cervical tip is harder to reach anteriorly when the uterus is retroverted, and the usual landmark orientation flips.
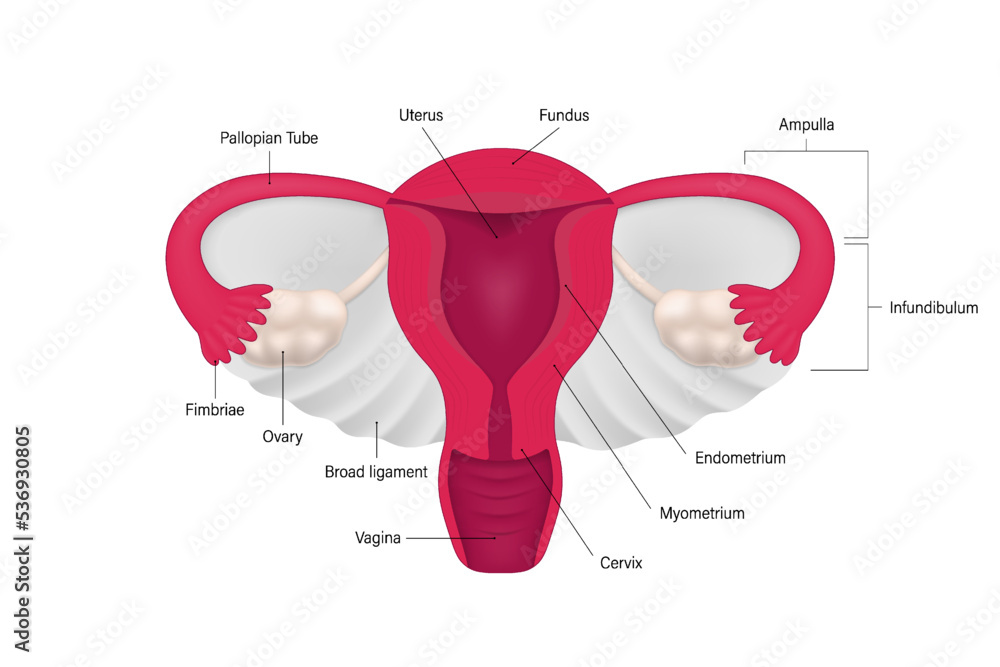
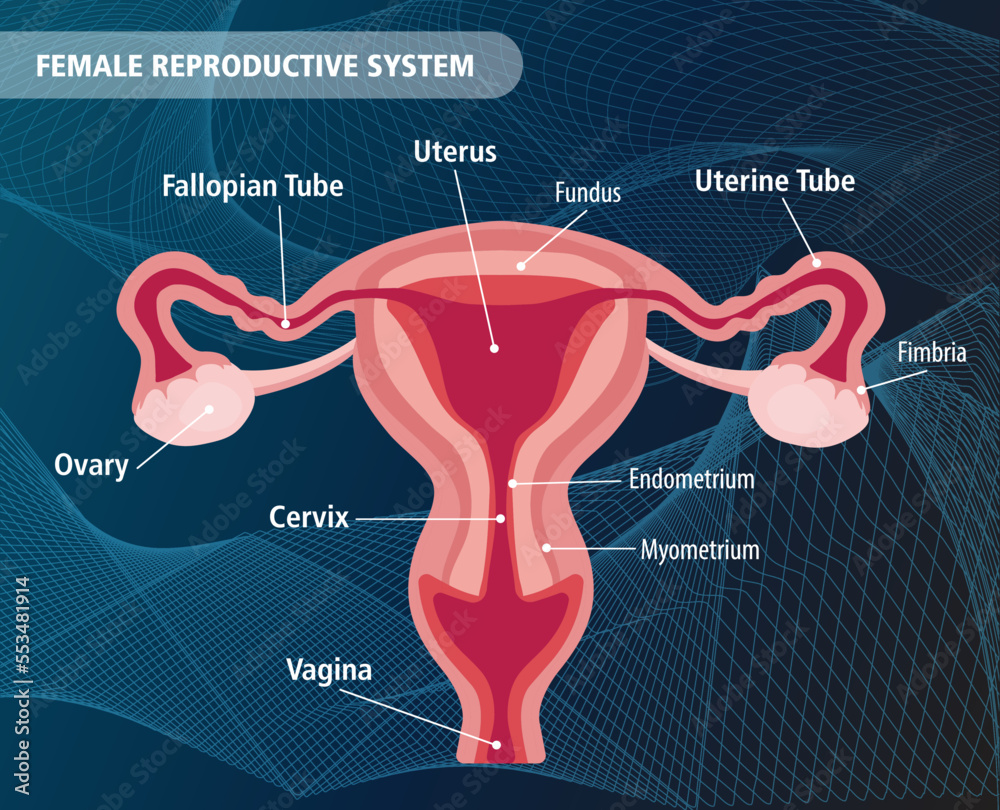
The ovaries are not fixed in place the way many people assume. They sit in the ovarian fossa against the lateral pelvic wall, near the external iliac vessels and the ureter. The relationship between the ovary, the ureter, and the uterine artery is surgically critical. The uterine artery crosses over the ureter superiorly in what is colloquially called the water under the bridge. During a hysterectomy or deep pelvic surgery, this relationship is where ureteral injury most commonly occurs. I learned this the hard way during my first year assisting in gynecologic surgery. The resident was doing a laparoscopic pelvic lymph node dissection and nearly transected a ureter because the tissue planes were obscured by adhesions from prior endometriosis. We converted to open surgery, identified the ureter by its peristalsis, and placed a stent. That experience fundamentally changed how I approach any case with a history of pelvic surgery or endometriosis. Now I always map the ureteral path preoperatively on cross-sectional imaging before I touch a scalpel. The fallopian tubes extend from the uterine cornua to the ovaries. Each tube has four regions: the interstitial portion within the uterine wall, the isthmus, the ampulla, and the infundibulum with its fimbriae. The ampulla is the most common site for fertilization and also the most common site for ectopic pregnancy. The fimbriae do not physically grasp the ovary. They create fluid currents that guide the oocyte into the tubal lumen. This is a detail that basic diagrams completely miss, and it explains why proximal tubal occlusion behaves differently from distal disease. The vaginal canal extends from the vulva to the cervix, roughly 7 to 10 centimeters in length. It is lined with stratified squamous epithelium and maintains an acidic pH through lactobacilli dominance. The vaginal walls are collapsed against each other under normal conditions, which is why they appear as a potential space on ultrasound rather than an open tube. The anterior vaginal wall shares a fibrous septum with the posterior bladder wall and urethra, while the posterior wall abuts the rectum through the rectovaginal septum.
How to Approach This System Practically
If you are trying to learn this for clinical purposes, start with cross-sectional anatomy. Coronal and sagittal pelvic ultrasound views will teach you more than any static diagram because they show the actual spatial relationships you will encounter. Transvaginal ultrasound gives you resolution down to about 1 millimeter for ovarian and endometrial structures. Transabdominal ultrasound is useful for larger masses but lacks the detail needed for early pregnancy or subtle endometrial pathology. MRI of the pelvis with thin slices through the uterus and adnexa is the gold standard for mapping complex anatomy. I use it routinely before surgery on patients with suspected adenomyosis or deep infiltrating endometriosis. The difference between adenomyosis and a leiomyoma on MRI can determine whether you attempt conservative excision or need a hysterectomy. On T2-weighted images, adenomyosis appears as a heterogeneous junctional zone thicker than 12 millimeters, while fibroids are well-circumscribed hypointense masses. Confusing the two intraoperatively leads to incomplete resection or unnecessary tissue damage. For self-examination and awareness, the main thing to understand is that normal varies enormously. Ovarian size fluctuates throughout the cycle. A dominant follicle can reach 20 to 24 millimeters before ovulation, and a corpus luteum after ovulation can look like a complex cyst on ultrasound. These are normal findings, not pathology. The cervix also changes position and consistency throughout the cycle. It is lowest and firmest in the luteal phase and highest and softest around ovulation. If you are tracking your cycle manually, this is a reliable marker, but it is not a contraceptive method on its own.
Get the Full Details
Clinical palpation follows a specific sequence. External inspection comes first, noting any skin changes, lesions, or asymmetry. Speculum examination allows visualization of the cervix and vaginal walls. Bimanual examination assesses uterine size, position, mobility, and tenderness, then palpates the adnexa for masses or tenderness. The key is to press slowly and ask the patient to report pain location precisely. Adnexal tenderness localized to one side points to ovarian or tubal pathology on that side. Midline suprapubic tenderness usually indicates bladder or uterine source.
Common Misunderstandings and What to Watch For
One persistent misconception is that the ovaries produce estrogen and progesterone continuously at steady levels. They do not. Follicular development during the first half of the cycle produces increasing estradiol, peaking just before ovulation. After ovulation, the corpus luteum produces progesterone predominantly, with estradiol at a moderate secondary peak. If progesterone levels are adequate in the luteal phase but estradiol is low in the follicular phase, you get symptoms like irregular bleeding and poor endometrial proliferation even though the ovaries are technically functioning. This pattern shows up frequently in patients who are told their hormone levels are normal based on a single day of testing. Another misconception involves the clitoris. The visible glans is only a small portion of the organ. The complete structure includes the glans, body, two crura, and vestibular bulbs, spanning roughly 11 centimeters internally. The crura attach to the ischiopubic rami on either side of the vaginal opening. Pain conditions like clitorodynia or vestibulodynia are often misdiagnosed because the external glans looks normal. The pathology is in the deeper structures or at the neurovascular bundle near the crura. Topical treatments that target surface inflammation alone usually fail because the issue is neuropathic or muscular, not dermatologic. The cervix is another structure people misunderstand. It is not a solid plug. The external os is a small opening that varies in size depending on parity and cycle phase. Nulliparous women typically have a pinpoint os, while parous women have a transverse slit. The cervical canal itself is lined with columnar epithelium that is sensitive to pH changes and prone to metaplasia when exposed to the acidic vaginal environment. This squamocolumnar junction is the exact region where cervical dysplasia develops, which is why Pap smear sampling targets that transition zone specifically. Sampling too high into the endocervical canal or too low on the ectocervix misses the area of greatest risk.
Pitfalls in Imaging and Diagnosis
Pelvic ultrasound has real limitations that beginners often underestimate. Body habitus significantly degrades transabdominal image quality. Patients with higher BMI may require transvaginal imaging exclusively, and even then, ovarian visualization can be limited by bowel gas or dense adhesions. I had a patient whose ovarian mass was completely missed on three transabdominal scans because a loop of sigmoid colon was interposed between the probe and the ovary. The transvaginal scan four days later showed a 6-centimeter dermoid cyst immediately. Always confirm a negative transabdominal finding with transvaginal imaging if ovarian pathology is suspected. MRI is powerful but expensive and not universally available. CT scans of the pelvis are poor for evaluating uterine and ovarian pathology because they lack soft tissue contrast resolution for these structures. I see patients brought in with CT reports that describe a normal pelvis, only to find significant adenomyosis or endometriosis on subsequent MRI. If you need to evaluate the myometrium, endometrium, or superficial endometriosis, order MRI with dedicated pelvic protocol, not CT. Lab interpretation requires cycle timing awareness. Basal hormone panels for ovarian reserve assessment must be drawn on cycle days 2 through 5. Progesterone for ovulation confirmation should be checked roughly 7 days before expected menses, which is day 21 in a 28-day cycle but shifts dramatically in longer or shorter cycles. A single random progesterone level is essentially uninterpretable without knowing where the patient is in her cycle. I once saw a case where a patient was told she was anovulatory based on a mid-cycle progesterone level that was actually normal for the follicular phase. She ovulated normally; the test was just misinterpreted.
When to Seek Clinical Evaluation
Most vaginal discharge is normal and varies in consistency and amount throughout the cycle. Ovulatory discharge is typically clear and stretchy. Luteal phase discharge is thicker and white. Odor, color changes to yellow or green, itching, or burning are indicators that something else is occurring. Postmenopausal bleeding is never normal and always requires evaluation for endometrial pathology. Heavy menstrual bleeding defined as soaking through a pad or tampon every one to two hours for several consecutive hours warrants investigation for structural causes like fibroids or polyps, or non-structural causes like coagulopathy or adenomyosis. Pelvic pain that is cyclical and predictable is often endometriosis or adenomyosis until proven otherwise. Pelvic pain that is constant and unrelated to the cycle may indicate adhesions, chronic pelvic inflammatory disease, or pelvic floor dysfunction. The distinction matters because the diagnostic workup and treatment paths are completely different. Endometriosis requires laparoscopic visualization for definitive diagnosis, while pelvic floor dysfunction responds to physical therapy. Treating one as the other wastes time and delays effective management.