Describing Physical Suffering Without Sounding Like A Romance Novel
I spent three weeks trying to write a character who had a broken rib. Every draft came back sounding either melodramatic or medically inaccurate. The problem wasn't finding words for pain. It was finding words that readers would accept as believable in fiction. Most writers reach for "agony," "torment," or "unbearable" within the first hundred words. These words fail because they tell rather than show. They're abstract labels for experience you haven't earned yet. When your reader encounters "she felt intense pain," their brain stops engaging. The word is too vague to create an image.
How I Actually Approach Words To Describe Pain In Writing
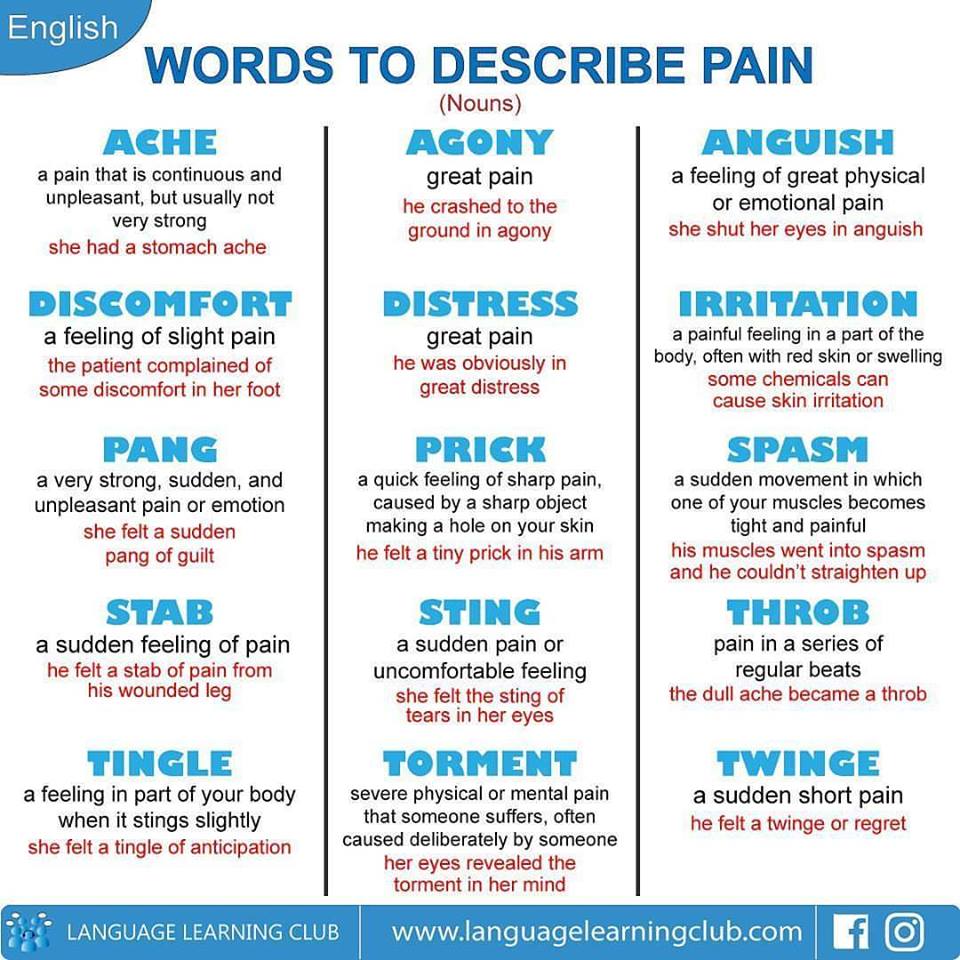
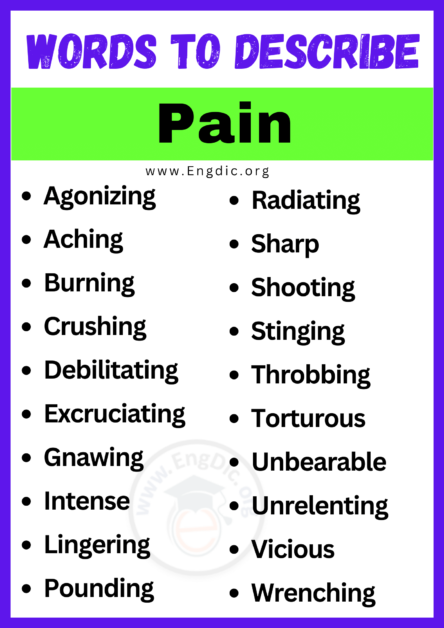
The method I use starts with specificity. Before choosing any adjective, I identify what kind of pain we're describing. Sharp, dull, throbbing, burning, aching, stinging, shooting, gnawing, crushing, piercing — each word activates a different sensory memory in the reader. A knife wound isn't described the same way as a stomach flu. I keep a running document of pain descriptions pulled from medical journals, patient forums, and actually reading case histories where people describe injuries in detail. The language is clinical but strangely poetic. "The fracture produced a deep, grinding sensation that radiated down my tibia" gives you more information than "it hurt terribly." The workaround I developed after my third failed draft was to describe the pain indirectly. Instead of saying the character experienced pain, I describe what the pain prevented them from doing. They couldn't stand without gripping the counter. Their breathing became shallow and controlled. They counted ceiling tiles to distract themselves. This approach takes more words but creates stronger immersion.
Here's what most people miss when learning Words To Describe Pain In Writing: pain changes over time. Acute pain feels different from chronic pain. The first hour after injury involves adrenaline masking symptoms. Three days later, inflammation makes everything worse. A character who still describes their wound as "fresh and sharp" on day four has never observed healing. Common pitfall number one is overusing intensifiers. Words like "extreme," "severe," "excruciating," and "intense" actually weaken your description. They tell the reader how hard to feel without providing evidence. Trust the noun and verb choices to carry the weight. "His knee throbbed" works better than "he experienced excruciating knee pain." Pain also varies by individual. A construction worker who's broken bones before describes injury differently than someone who's never been injured. Age, tolerance, personality, and context all shape how pain is perceived and expressed. A soldier in combat experiences pain differently than someone lying in bed alone at 2am. One is distracted by survival. The other has nothing but the feeling.
Get the Full Details

Advanced technique: layer multiple sensations. Real pain is rarely monolithic. A gunshot wound involves sharp penetration, then burning heat, then throbbing pulse, then numbness as shock sets in. Describing this progression shows you understand physiology rather than just picking dramatic words. The bottleneck in this approach is timing. Describing pain accurately requires research or personal experience. Reading medical textbooks helps, but they lack emotional truth. I found that watching real surgery videos and reading patient recovery blogs gave me the specific details needed for believable fiction. The vocabulary becomes clinical but strangely poetic.
Words That Actually Work
Sharp, stabbing, piercing, cutting — these describe acute, localized pain. Use them for wounds, fractures, and sudden injuries. Dull, aching, throbbing, grinding — these fit chronic conditions, inflammation, and deep tissue damage. Burning, stinging, searing — these describe chemical irritation, friction, or nerve damage.
Gnawing, crampping, twisting — these convey internal discomfort, organ distress, or muscle spasms. The problem with categories like these is they're too neat. Real pain often combines multiple qualities. A migraine might feel like "a hot wire being pulled around my skull" one moment and "everything moving underwater" the next. Don't force your description into a single box. Another counter-intuitive insight: sometimes the absence of description works best. A character who doesn't react to pain might confuse readers more than someone who screams. Silence can communicate shock, bravery, or dissociation. The reader fills in the blanks with their own fear.
When This Method Completely Fails
Describing pain realistically has limitations. Readers have different pain thresholds and experiences. What sounds believable to one person might seem exaggerated to another. A scene that works for a war novel might fail in domestic fiction where characters are expected to handle discomfort quietly. Another issue is cultural differences. Some cultures express pain dramatically. Others emphasize stoicism. Your audience's expectations shape what feels authentic. Research matters more than intuition here. If you're struggling with pain description, consider an alternative approach: focus on the aftermath. Describe the swelling, bruising, limited mobility, sleep disruption, and emotional impact. These consequences are often more relatable than the pain itself. Readers understand exhaustion better than agony.
The technical term you should know is "alloesthesia" — when pain is perceived in an area distant from the actual injury. Nerve damage can cause this. Describing it adds realism but requires careful handling. Most readers haven't experienced it and might find it confusing. My biggest mistake early on was describing pain without context. A character clutching their stomach could have appendicitis, heartburn, or a bad oyster. The surrounding situation determines which word choices make sense. Always anchor pain description to plot and character. For quick reference when working on Words To Describe Pain In Writing, I categorize by mechanism: mechanical (cuts, bruises, fractures), thermal (burns, frostbite), chemical (toxins, acids), neurological (nerve damage, migraines), and inflammatory (infection, autoimmune). Each category has distinct vocabulary and progression patterns.
The process usually cuts drafting time from several hours to about forty-five minutes once you have your reference list organized. Setup takes longer initially, but the returns compound with each project.



