A Practical Guide to Integrating Work In Therapy Into Your Practice
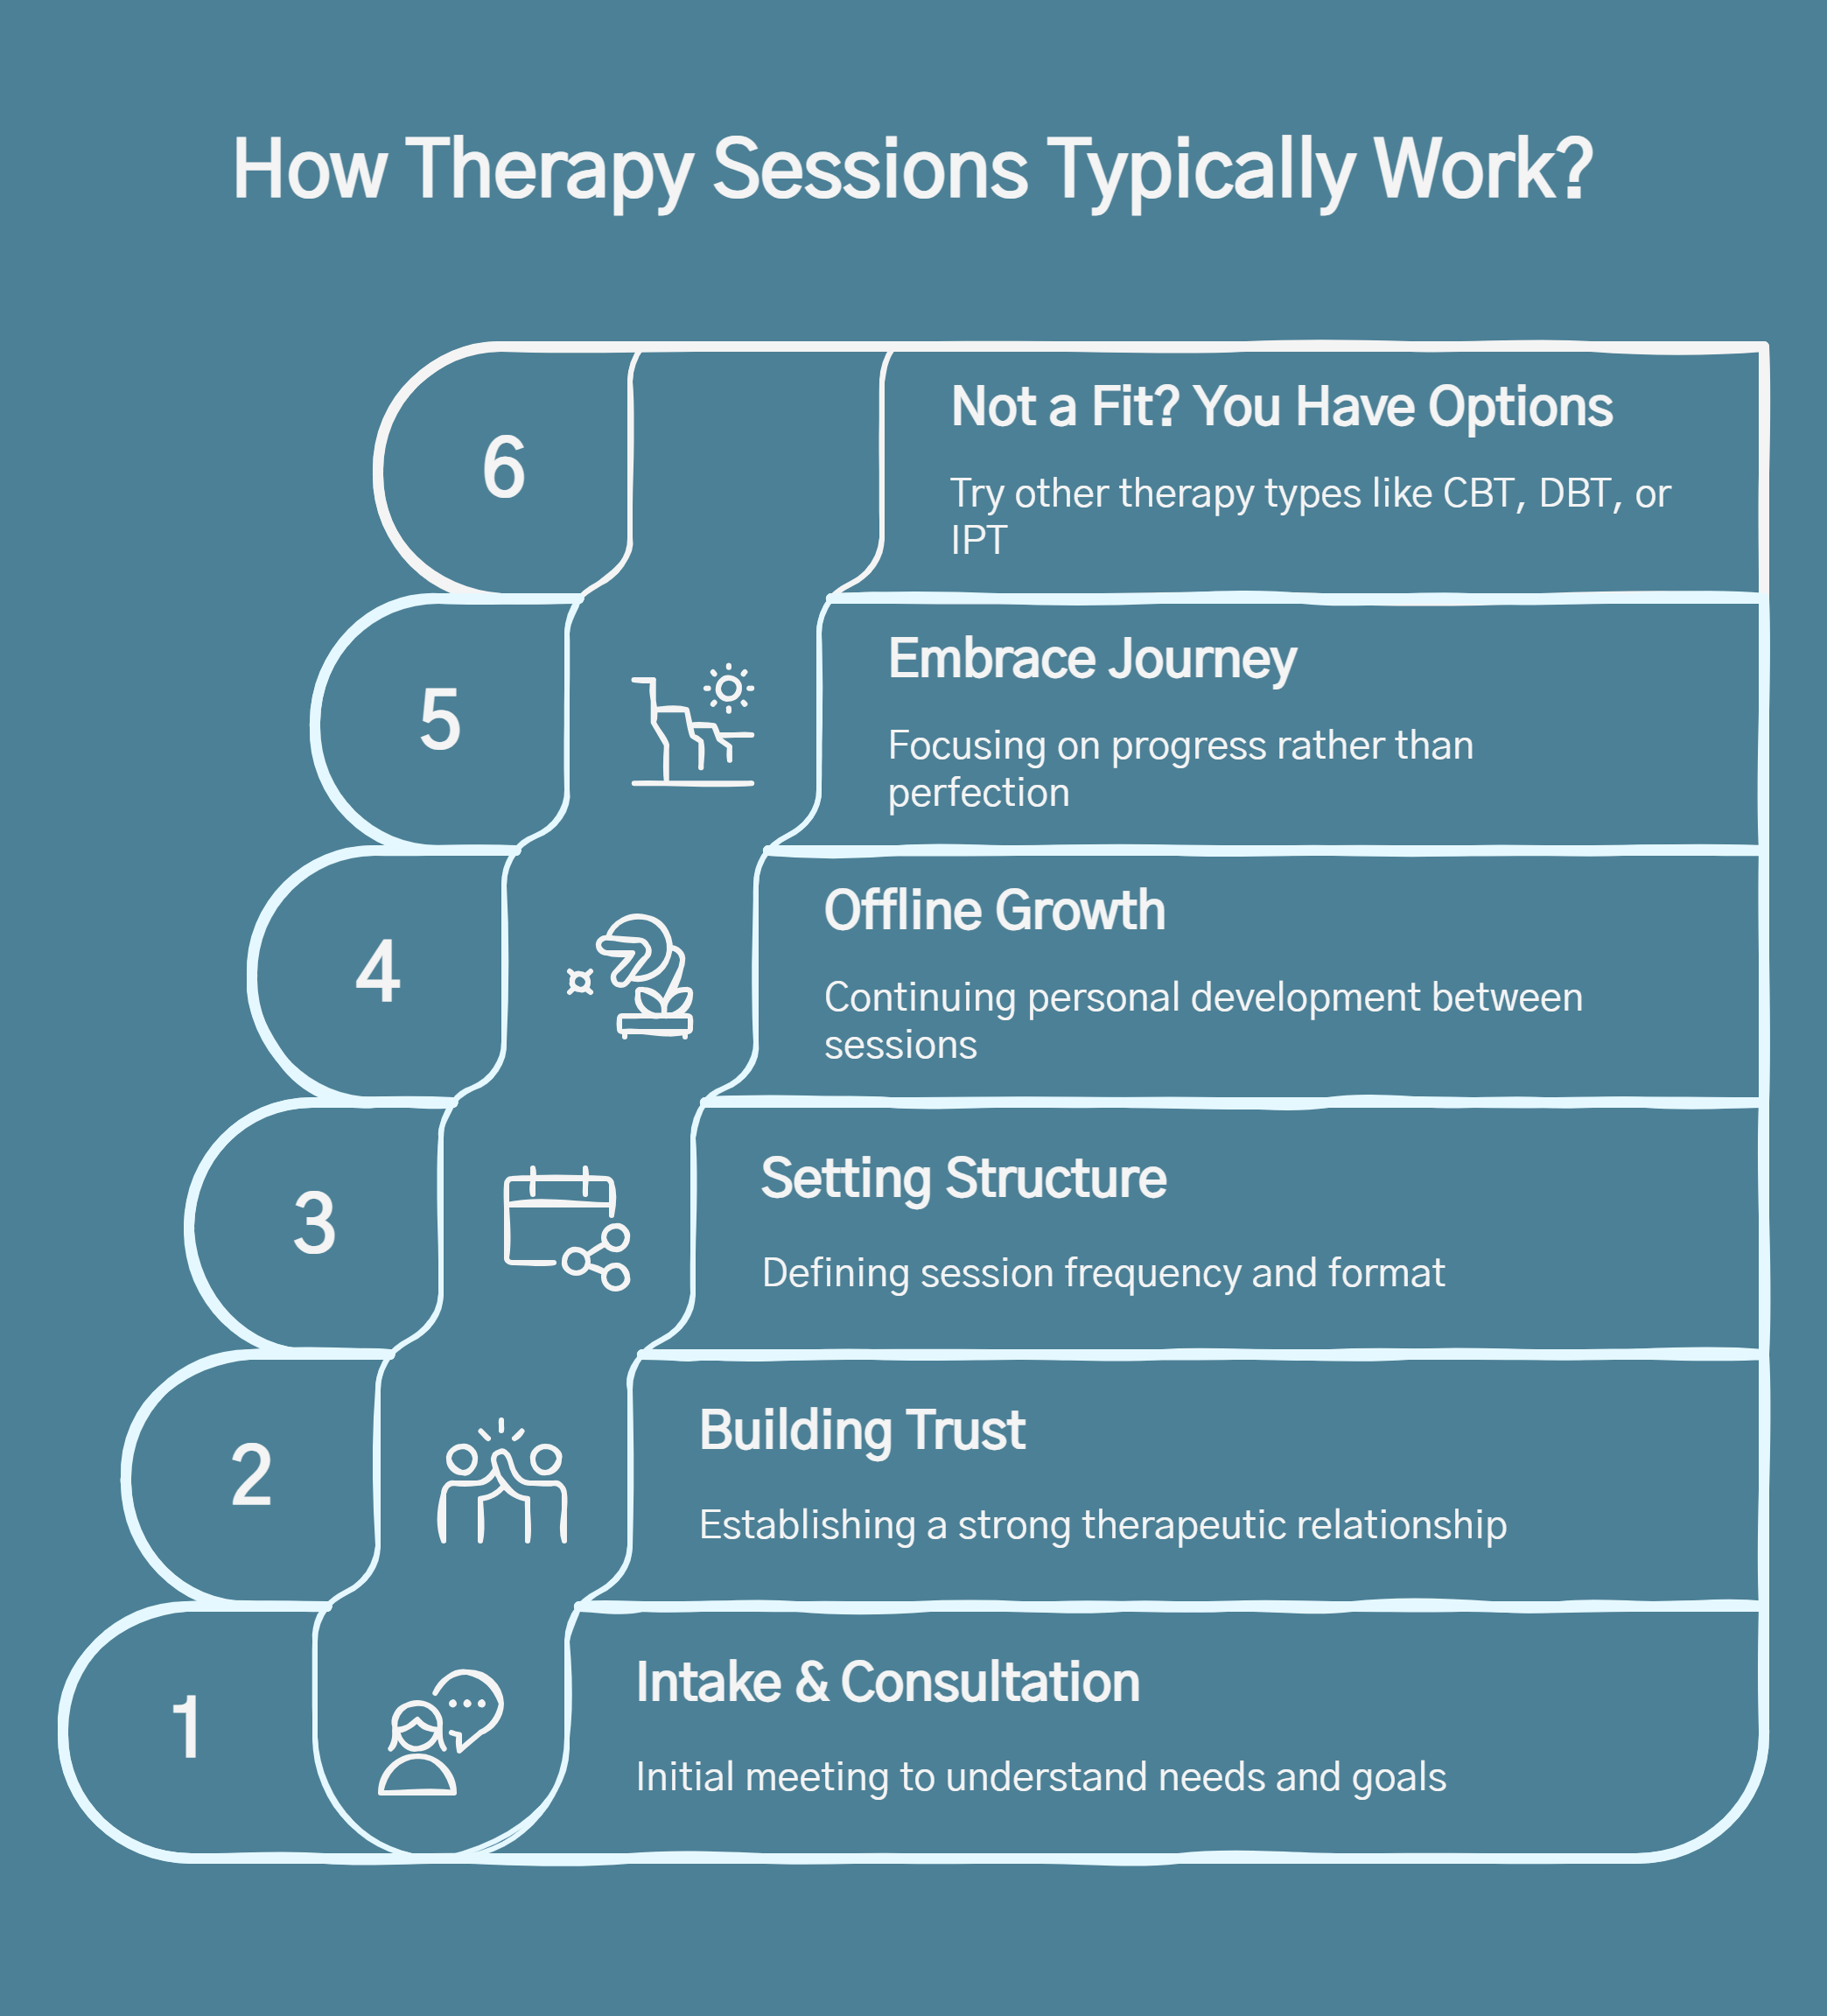
I used to struggle with keeping patients engaged between sessions. We would have good minutes on the couch and then nothing carried over. That changed once I started working with structured Work In Therapy frameworks. It is not magic, but it does help patients bridge the gap between sessions in ways that actually move treatment forward. Work In Therapy refers to structured tasks or interventions that a patient completes outside of the session room. The therapist assigns them. They are not homework in the old-fashioned sense where someone fills out worksheets and brings them back. They are experiential assignments designed to practice skills, build awareness, or process material that comes up during sessions. Think of them as in vivo practice for the work you are doing together. The key distinction is that the assignment itself becomes therapeutic material. You discuss it at the start of the next session. You analyze what happened. You adjust. This creates a feedback loop that most traditional talk therapy lacks entirely.
How to Implement It Step By Step
Start small. I used to hand off heavy reading assignments and wonder why patients never did them. It was a rookie mistake. Instead, begin with something that takes ten minutes at most. A breathing exercise before bed. A brief journal entry about one specific emotion. A behavioral experiment where they say no to something small. Whatever it is, it should be something the patient can realistically do without it becoming another source of stress. The assignment needs to be specific enough that the patient knows exactly what to do but flexible enough that it does not feel rigid. Vague instructions like "pay attention to your emotions" produce vague results. "Notice one moment today when you feel your shoulders tighten and write down what triggered it" gives the patient a concrete action and a clear focus. Discuss the assignment during the session itself before sending it out. Make sure the patient understands the purpose behind it. If they do not see why it matters, they will not do it. I learned this the hard way. Early on I assigned a thought record to a client who was already overwhelmed. She never completed it. When we talked about it, she admitted she did not understand why she needed to write down automatic thoughts when she could barely get out of bed. We recalibrated and simplified the task. That single adjustment changed the trajectory of that particular phase of treatment.
At the beginning of the next session, debrief. Ask what happened. What was easy. What was hard. Where did it fit or not fit into their actual life. This debrief is often more valuable than the assignment itself because it reveals obstacles and patterns you would never see from the couch alone.
Get the Full Details

Common Pitfalls and How to Avoid Them
The biggest problem I see is when therapists treat the work as compliance rather than collaboration. If the patient completes every assignment perfectly but does not actually engage with the underlying material, you are managing behavior not facilitating change. Watch for this. Perfection in completing the work can sometimes indicate avoidance disguised as diligence. Another issue is assigning work that is too advanced for the patient's current capacity. A grounding exercise is appropriate for someone in crisis. A cognitive restructuring assignment is not. Match the intervention to the stage of treatment. I once had a client in acute grief try to complete a full thought record and ended up having a panic attack instead. We had to step back and return to basic stabilization first. The work should challenge without overwhelming. Scheduling is also a factor that gets overlooked. If you assign something that requires twenty uninterrupted minutes and your patient works two jobs, it is not going to happen. Consider their actual daily reality when designing the task. I now keep a running mental inventory of each patient's available time and energy before I suggest anything.
Work In Therapy Across Different Modalities
Different approaches use this concept differently but the principle stays the same. CBT tends toward structured worksheets and thought records. Psychodynamic work might involve free association prompts or dream journals. Somatic approaches use body scans or movement practices. ACT assigns values-based action steps. The framework adapts but the core idea does not change. Assign something meaningful. Discuss it. Adjust. One thing beginners often miss is that the work does not always need to happen between sessions. Sometimes the "work" is done during the session itself as an in-vivo exercise that extends past the typical hour. A patient might practice a skill for ten minutes at the end of a session and then apply it that evening. The distinction between in-session and out-of-session is somewhat arbitrary. What matters is that there is deliberate practice happening.
Measuring Whether It Is Working
Track outcomes. Not just whether the patient completed the assignment but whether completion correlates with progress. I use a simple scale: did this assignment lead to a new insight? Did it shift the patient's behavior even slightly? Did it reveal something we had not seen before? If the answer is consistently no across multiple assignments, the framework might not be the right fit for that particular patient or that particular phase of treatment. Sometimes Work In Therapy simply does not work for certain populations. Patients with significant executive function challenges, active substance use, or severe depression may not have the cognitive or emotional bandwidth for structured between-session work. In those cases, reducing session frequency or shifting to a more supportive model is often more effective than pushing assignments that will likely go unfinished. No amount of structured work compensates for a lack of the basic capacity to engage with it. The best therapists I know treat the work as one tool among many. It is not required for therapy to be effective. It is not a litmus test for commitment. It is a method for deepening practice and expanding the therapeutic space beyond the confines of the scheduled hour. Use it when it fits. Drop it when it does not. That is the practice.