Why Most Psychosocial Assessments Fall Flat
I spent seven years conducting psychosocial assessments for workplace reintegration cases, and I still see people struggle with the same mistakes. The documents are usually too generic to be useful, or they bury the actual findings under so much bureaucratic language that nobody on the receiving end knows what they're reading. The real problem isn't that assessments don't exist. It's that people treat them like checkbox exercises instead of functional tools for decision-making.Work Psychosocial Assessment Examples That Actually Work
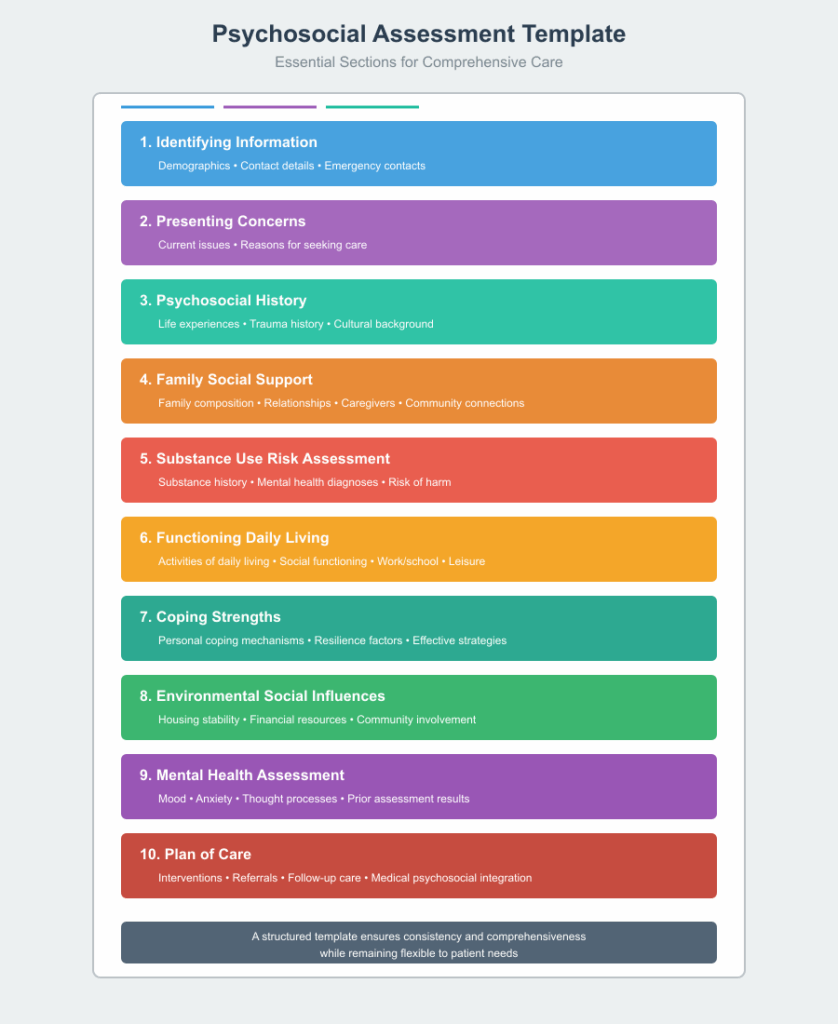
When you sit down to create one of these assessments, start with the purpose. Who is going to read this document and what decision will they make based on it? A case manager needs different information than a medical panel. A rehabilitation coordinator needs something different from both. I used to get assessments handed to me where the assessor had clearly written for a medical audience, and the rehabilitation team couldn't figure out which functional limitations actually mattered for return-to-work planning. The assessment needs to connect clinical observations to functional outcomes. Not "the patient reports anxiety" but "the patient exhibits measurable avoidance behaviors in group settings, which would preclude participation in team-based work environments for approximately six months." That's the difference between a document that means something and one that collects dust.Structure matters more than volume. I've seen 40-page assessments that said less than two well-organized pages. The format I settled on after trial and error breaks into five sections: presenting concerns, social and occupational history, mental status findings, functional capacity evaluation, and recommendations. Every section answers a specific question the reader needs answered. The social history section is where most assessors cut corners. They list employment dates and family structure but miss the patterns that actually matter. I learned this the hard way when I reviewed an assessment for a client with chronic low back pain. The assessor noted he had worked as a forklift operator for twelve years but didn't ask about shift patterns, overtime frequency, or physical demands. The client was actually working two jobs with rotating schedules, and that context changed the entire treatment approach. Don't just collect data. Look for the data that changes decisions.
The Functional Capacity Piece
This is the part people get wrong most often. Psychosocial assessments are not medical diagnoses. They are evaluations of how a person functions in their environment. The gap between diagnosis and functional limitation is where the real work happens. You need to describe what the person can and cannot do, with enough specificity that someone can build a plan around it. Vague statements like "the patient has difficulty with social interaction" are useless. "The patient avoids eye contact, speaks in monosyllables during structured interviews, and becomes non-verbal when asked to describe group dynamics" gives someone something to work with.I once dealt with an edge case involving a claimant who presented as highly functional in one-on-one settings but completely shut down in group evaluations. The standard assessment format would have recorded this as inconsistent behavior or possible malingering. Instead, I documented the discrepancy separately and recommended a modified assessment approach for future evaluations. The treating team missed it initially because the assessor was so focused on scoring that they didn't notice the behavioral shift. That discrepancy turned out to be clinically significant and changed the entire prognosis. Timing is also important. A psychosocial assessment conducted during an acute crisis will look very different from one conducted six months later. I stopped doing assessments during the first two weeks of a crisis unless absolutely necessary because the data wasn't stable enough to build decisions on. People's functioning changes rapidly in that window, and basing a work plan on unstable data leads to plans that fail within weeks. Presenting concerns: 45-year-old male referred for psychosocial evaluation following workplace injury sustained 14 months ago. Self-reported ongoing lower back pain with associated fear-avoidance behaviors. History of two prior back surgeries. Currently employed part-time in administrative role since month 8 post-injury.
Occupational history: 20 years in warehousing with progressive increase in physical demands. Last full-time position involved lifting up to 50 pounds repeatedly throughout 12-hour shifts. No documented accommodation requests prior to injury. Previous employer willing to consider phased return with modified duties. Functional findings: Patient demonstrates intact cognitive functioning on screening measures. Affective presentation consistent with Adjustment Disorder with mixed anxiety and depressed mood. Significant fear-avoidance behavior noted during movement assessment, including exaggerated pain expressions disproportionate to observable tissue damage. Patient unable to tolerate simulated lifting tasks despite adequate strength on manual muscle testing. Recommendations: Continue current part-time administrative work with no restrictions. Graded exposure therapy for fear-avoidance behaviors, 12 sessions over 8 weeks. Re-evaluate functional capacity in 12 weeks. No return to warehousing duties anticipated within next 6 months without significant intervention.
Get the Full Details
The Tools and Frameworks
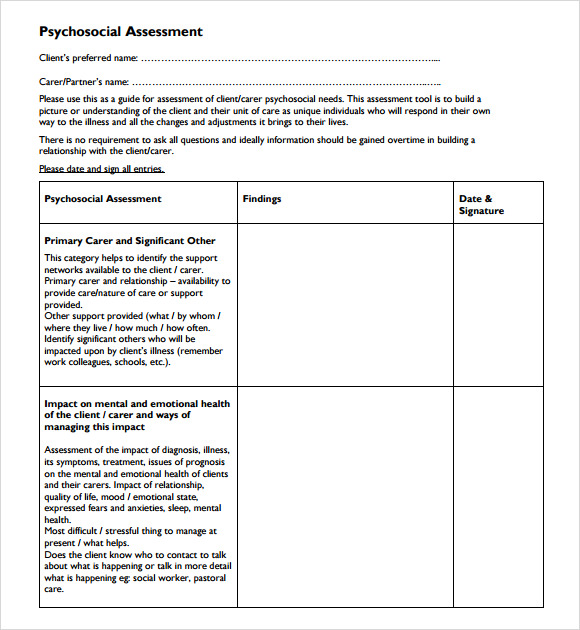
There are established frameworks you can reference. The International Classification of Functioning, Disability and Health (ICF) provides a standardized vocabulary for describing functioning across body, individual, and environmental domains. The DSM-5 includes functional assessment guidelines, though they're fairly general. For occupational contexts, the Workplace Functional Capacity Evaluation model adapts clinical tools for workplace-specific questions. None of these are mandatory, but using a recognized framework makes your assessment credible to other professionals. I've had assessments rejected by panels because the language didn't map to standard classification systems. It's not fair, but it's reality in managed care and workers' compensation contexts.The documentation itself should be clean and scannable. Use headings, bullet points where appropriate, and avoid long blocks of narrative text. The people reading these documents are often managing dozens of cases simultaneously. Make it easy for them to find the information they need without wading through paragraphs of prose.