Wound Bed Assessment and Recording Practices
I've been doing wound care documentation for going on fifteen years, and I still see the same mistakes over and over again. Most people treat it like paperwork, but the records actually determine whether a wound heals or stalls. The difference between a productive chart entry and a useless one usually comes down to specificity and consistency. When I started out, my supervisors told me to "document everything." That turned into three-page narratives that nobody read. Now I write exactly what I need to know when I come back in two days. If I can't tell whether progress is happening from my own notes, the documentation failed.
Wound Care Documentation Example
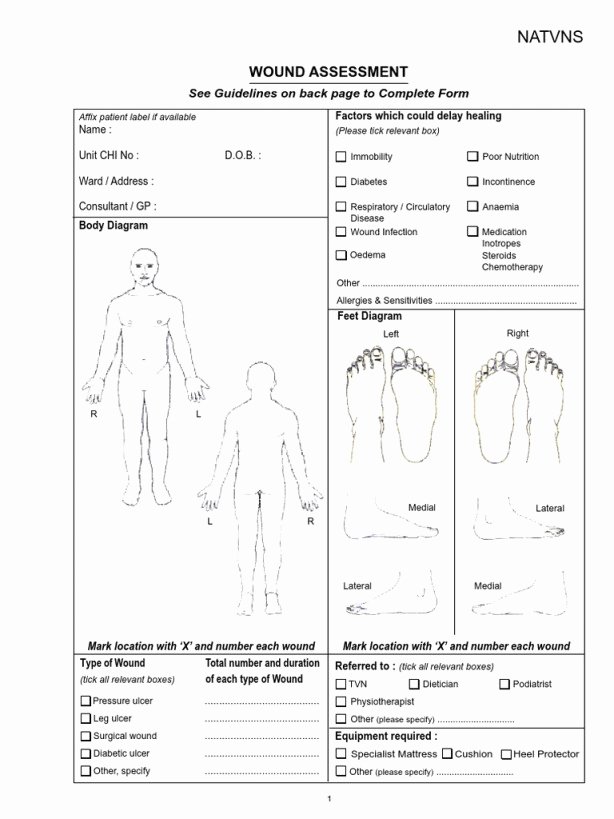
Here's how I actually structure a wound assessment note, and why each element matters clinically: Date and time of assessment: 2024-03-15 14:30. This isn't just administrative. Wound measurements change throughout the day based on patient positioning and edema fluctuations. Morning assessments on dependent extremities will show different measurements than afternoon ones unless the limb was elevated. I always note the position—sitting, supine, standing—because it contextualizes the numbers. Location and anatomical landmarks: I measure from fixed bony prominences, not from the wound edge itself. A 3cm sacral pressure injury measured from the posterior superior iliac spine is reproducible. Measured from the wound border is nonsense because the wound changes shape. I include a simple diagram with the assessment. Yes, even as an experienced clinician. Two months from now when I'm reviewing this with a new wound care nurse, that diagram saves ten minutes of reconstructing the geometry from text alone.
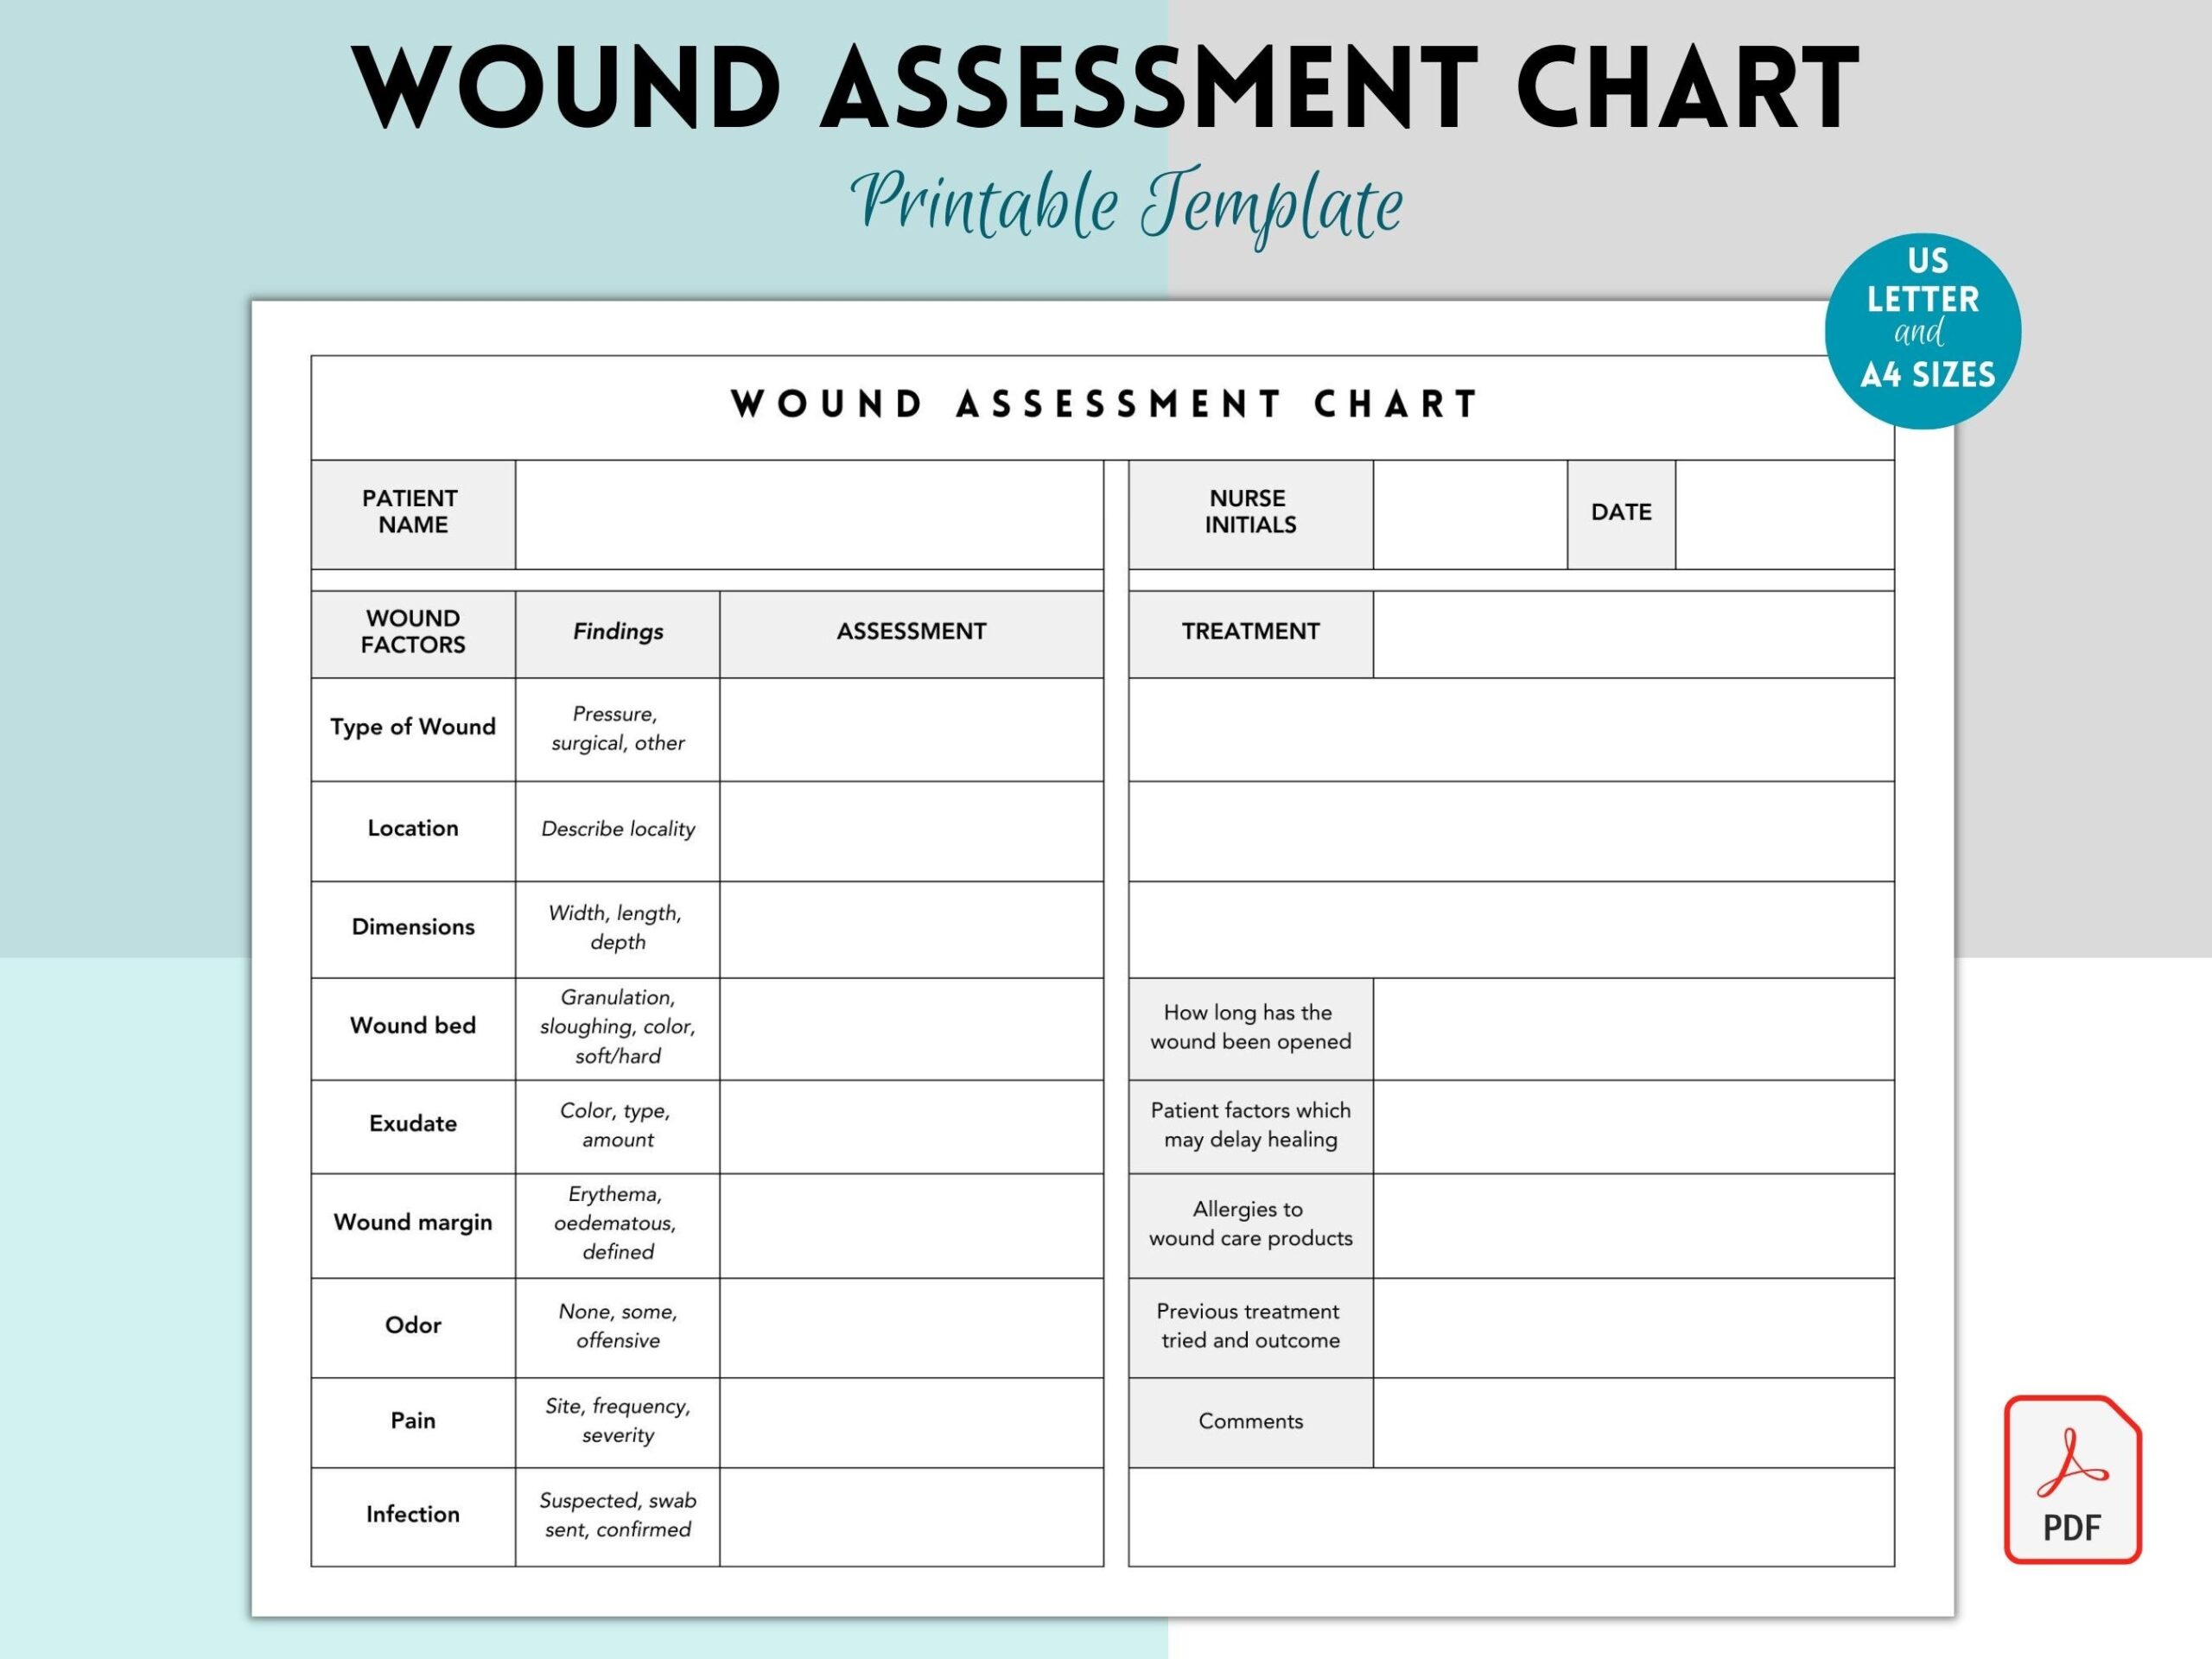
Wound dimensions: length, width, depth. I use the clock face method consistently—12 o'clock always points toward the patient's head, no exceptions. Depth goes in centimeters using a sterile cotton-tipped applicator inserted gently into the deepest portion. Undermining and tunneling get measured separately with a second applicator, noting direction and depth. A 2cm tunnel at 3 o'clock is clinically different from a 2cm tunnel at 9 o'clock, and mixing them up creates problems down the road. Tissue type and percentage: I describe granulation, slough, and eschar as percentages of total wound bed area. Granulation tissue at 80% with 15% slough and 5% eschar tells a clear story. "Mixed tissue" is so vague it's essentially worthless documentation. I use standardized color coding when possible—pink to red for healthy granulation, yellow to tan for slough, black to brown for eschar. Dark red granulation can indicate hyperemia versus early undermining, and that distinction matters for treatment decisions. Exudate characteristics: amount, type, color, and odor. Light, moderate, heavy—I use the amount that saturates the dressing within the scheduled change interval as my baseline. Serous is clear and watery. Serosanguinous is pink-tinged. Purulent is opaque and yellow-green. I note color changes because they can signal infection before systemic signs appear. Odor is documented objectively—"no notable odor" or "moderate odor present" rather than subjective judgments. Foul-smelling wounds need different dressings and potentially more aggressive debridement strategies.
Get the Full Details

Periwound skin assessment: I check for maceration, erythema, induration, and temperature changes. Macerated skin around a wound with heavy exudate needs a different barrier strategy than intact periwound tissue. Erythema extending beyond 2cm from the wound margin suggests cellulitis. I photograph peririound changes when they're significant—documentation is stronger with visual evidence, though I always get patient consent first and follow privacy protocols. Pain assessment: I rate pain before and after dressing changes separately. A wound that's 7/10 before debridement and 2/10 afterward tells me the procedure was effective. A wound that stays at 6/10 through both time points suggests inadequate analgesia or an underlying issue I should investigate. I document the pain scale I'm using too—numerical, faces, verbal descriptor—because they're not interchangeable across patient populations.
Common Pitfalls I See Regularly
Inconsistent measurement techniques destroy longitudinal data. If I switch from a disposable ruler to a digital caliper halfway through a treatment episode, the apparent size change might be artifact rather than biology. I stick with the same instrument type throughout a wound's healing trajectory whenever possible. Subjective language creeps in everywhere. "Promising granulation" means nothing. "Granulation tissue covering 60 percent of the wound bed, beefy red and bleed-resistant to gentle contact" means everything. Be descriptive, not evaluative. The evaluation belongs in the plan section, not mixed into the assessment findings. I learned the hard way about missing tunneling. I once documented a sacral wound as 8 by 5 centimeters with no complications. Two weeks later, a colleague found a 4-centimeter tunnel beneath the apparent wound margin that we'd completely missed. I measure for undermining and tunneling in every direction now, not just the visually obvious ones. It adds thirty seconds to the assessment and prevents exactly this kind of error.
Advanced Considerations
Photography and measurement accuracy require standardization. I use a scale marker in every wound photo—usually a dedicated medical ruler placed beside the wound, never inside it where it distorts the anatomy. Lighting should be consistent. Natural daylight or standard clinical room lighting works better than the warm overheads in some exam rooms, which distort color assessment of tissue and exudate. When documenting negative pressure wound therapy cases, I record canister output volume and character separately from wound exudate. Suction can concentrate drainage, making 50ml of output represent significantly more wound exudate than the volume suggests. I've seen clinicians miss rising infection markers because they trusted the canister volume without considering the concentration effect. For lymphedema patients with wounds, measurements taken without accounting for compression garment removal timing are unreliable. I always note whether the compression has been off for at least thirty minutes before assessment. Untreated dependent edema can make a wound appear larger simply because the surrounding tissue is fluid-loaded. The wound isn't growing—the measurements are just wrong.

I also track concurrent health factors that affect healing. A patient's albumin level, glycemic control in diabetics, smoking status, and medications like corticosteroids all influence wound progression. A diabetic with an HbA1c of 9.2 percent will heal slower than a well-controlled peer regardless of dressing quality. Documenting these factors helps justify treatment plans and sets realistic expectations.
Practical Tips That Actually Help
Create a template you use consistently. I have a standard form that covers every element above, and I fill in only what's relevant. Blank fields get crossed through rather than left empty, so there's no ambiguity about whether I forgot something or intentionally skipped it. Record before changing the dressing when possible. Removing an adherent dressing can disrupt granulation tissue and change the wound appearance. If I assess first, then remove, then document, my measurements reflect the wound's true state rather than post-debridement artifact. This matters most for fragile wounds that bleed easily. Include patient-reported outcomes. A wound that looks clinically stable but the patient says is increasingly painful deserves attention. Pain pattern changes often precede visual deterioration by days. I ask about pain at rest, with movement, and during dressing changes separately because they reveal different information.
Communication between disciplines matters. When I refer to a wound care specialist or collaborator, my documentation should stand alone. Include the full assessment history, not just the current snapshot. A reader encountering the wound for the first time needs enough context to make independent judgments without calling me back for basic information. Review previous entries before documenting new ones. I always pull up the last assessment to compare measurements and tissue progression. Patterns emerge quickly when you're looking at sequential data. A wound that measured 12 percent slough last visit and 25 percent this visit needs explanation, regardless of whether the treatment protocol changed. Most documentation systems support template customization. I recommend building one that matches your clinical workflow rather than fighting a generic form. The time you spend wrestling with mismatched fields adds up across hundreds of assessments. A well-designed template makes thorough documentation the easy path instead of the exception.

I've found that the best wound care documentation doesn't try to capture everything—it captures the right things consistently. A concise but complete assessment done the same way every time beats a comprehensive but variable narrative. Your future self and any covering clinician will thank you for the discipline. The reality is that wound documentation is both a clinical tool and a legal record. It serves both purposes adequately only when it's accurate, specific, and consistent. Skip any of those qualities and you compromise both patient care and your own professional protection. I'd rather spend an extra minute being precise than an extra hour explaining ambiguity later.