Understanding Stomach Acid Neutralization
The stomach maintains a pH around 1 to 2 thanks to hydrochloric acid (HCl) produced by parietal cells. This highly acidic environment serves multiple purposes: it denatures proteins, activates pepsinogen into pepsin for digestion, and destroys most ingested pathogens. However, the acidic contents occasionally need to be neutralized or buffered, whether naturally during digestion or through pharmaceutical intervention. Writing the neutralization equations involves tracking what compounds enter the stomach and how they react with HCl. I spent years working in a pharmacology lab studying antacid formulations, and one thing I learned the hard way is that not all neutralization reactions are straightforward. You might think baking soda (sodium bicarbonate) is just a simple base that neutralizes stomach acid. It is. But the moment you account for the carbon dioxide produced and the buffering capacity of the stomach's mucus layer, the picture gets more complicated. I once spent three weeks trying to reconcile in vitro results with in vivo data, only to realize the stomach's constant acid secretion was undermining every measurement. The workaround was switching to a continuous pH-stat titration setup that maintained steady conditions.
Write The Neutralization Equations That Take Place In The Stomach
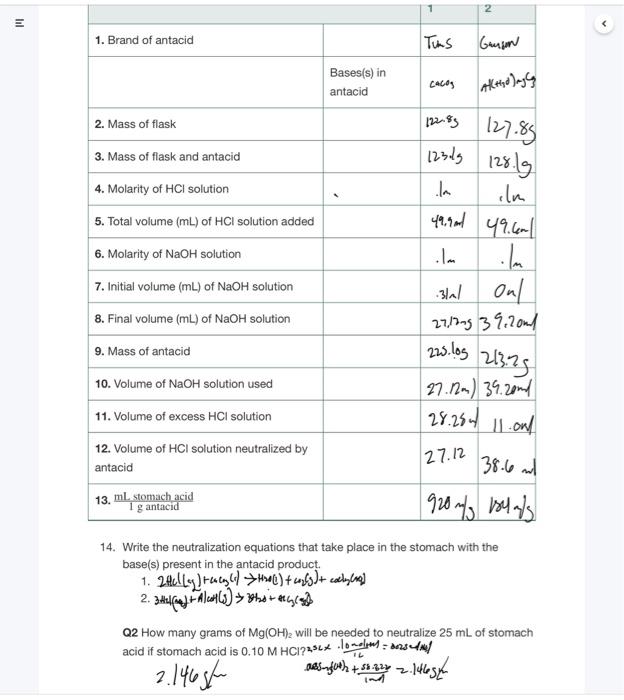
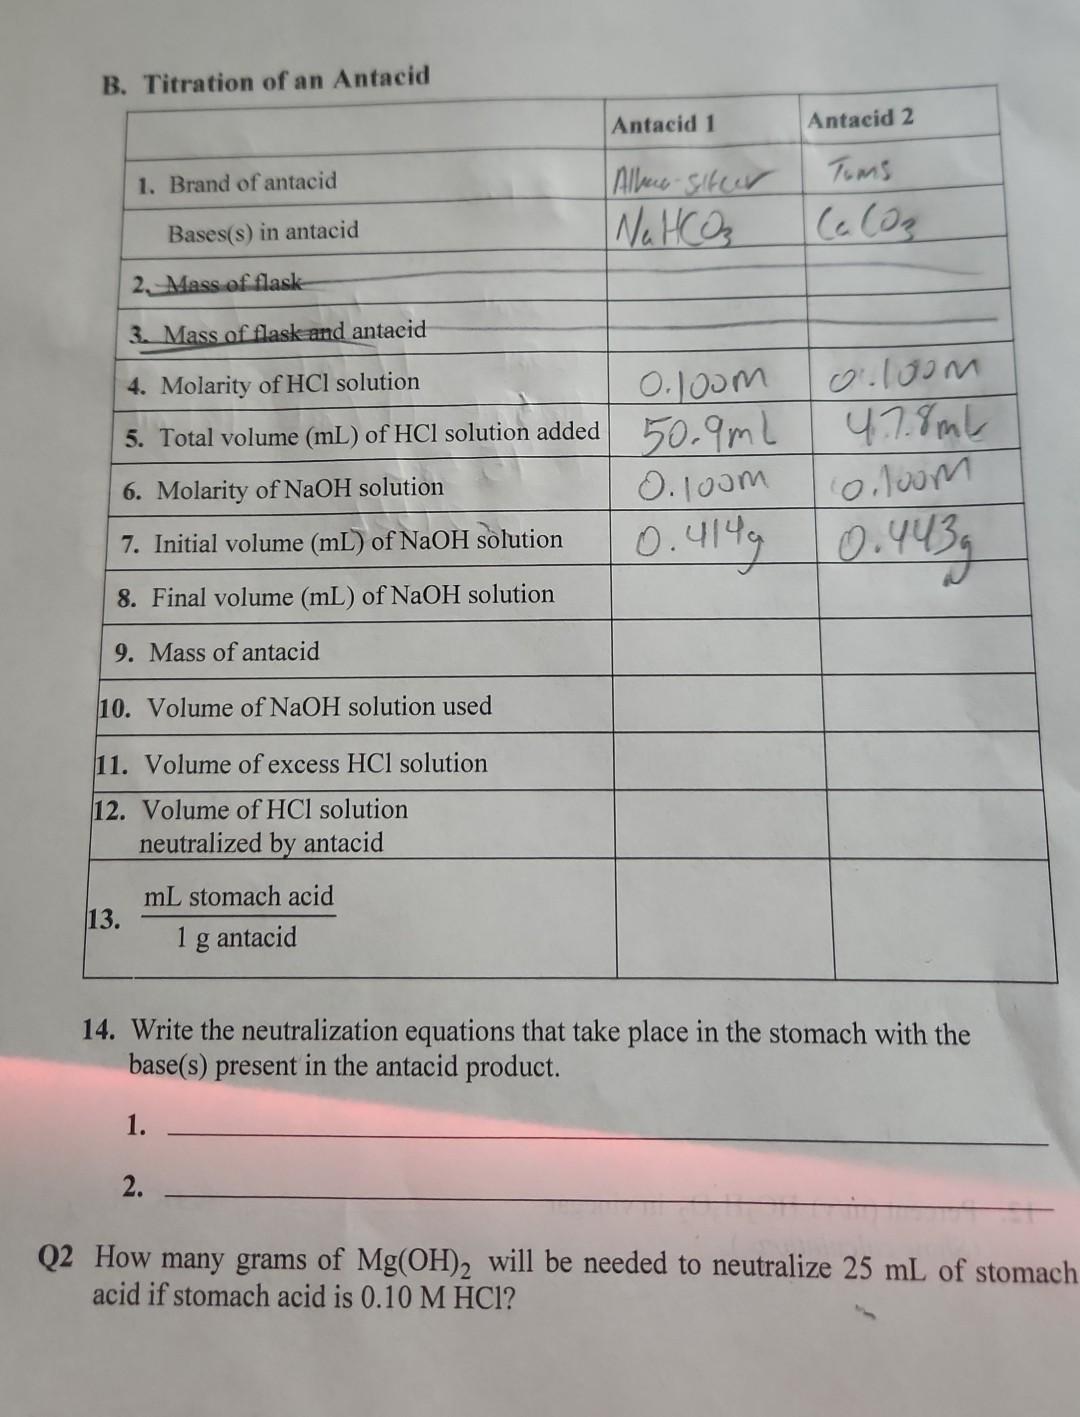
The core reaction everyone starts with is HCl reacting with a base. Here are the primary equations, written with proper state symbols: HCl(aq) + NaHCO(aq) NaCl(aq) + HO(l) + CO(g) This is the classic baking soda neutralization. One mole of hydrochloric acid reacts with one mole of sodium bicarbonate to produce salt, water, and carbon dioxide gas. The CO is what causes the burping after taking an antacid tablet. In practice, this reaction is fast but short-lived because the bicarbonate gets consumed quickly and the stomach resumes acid secretion.
Aluminum hydroxide works differently: 3HCl(aq) + Al(OH)(s) AlCl(aq) + 3HO(l) This one produces no gas. The solid aluminum hydroxide dissolves as it neutralizes acid, and the reaction is slower but more sustained. A common pitfall here is assuming the stoichiometry is 1:1. It's actually 3:1. If you're calculating dosing, getting this wrong means either underdosing or exposing someone to excess aluminum. I've seen this mistake in undergrad lab manuals where the equation is accidentally written as HCl + Al(OH) AlCl + HO without balancing.
Get the Full Details

Magnesium hydroxide follows a similar pattern: 2HCl(aq) + Mg(OH)(s) MgCl(aq) + 2HO(l) Again, the stoichiometry matters. Two moles of HCl per mole of Mg(OH). This compound is the active ingredient in milk of magnesia. The resulting magnesium chloride is osmotically active, which is why excessive use can cause diarrhea. That's a practical side effect worth noting when choosing between aluminum and magnesium based antacids.
Calcium carbonate is another common neutralizing agent: 2HCl(aq) + CaCO(s) CaCl(aq) + HO(l) + CO(g) This one produces both water and carbon dioxide, similar to bicarbonate but with a different cation. Calcium carbonate has a high neutralizing capacity per gram, but it can cause acid rebound. After the initial neutralization, the drop in acidity triggers the stomach to secrete even more HCl. I learned about this during a clinical observation where a patient switched from an H2 blocker to chewable Tums and reported worse heartburn after a week. The rebound effect was real and measurable.
There's also a natural neutralization happening inside the stomach itself. When food enters, it buffers the acid temporarily. Bicarbonate secreted by the pancreas later enters the duodenum and neutralizes chyme, but before that, gastric mucous cells secrete a bicarbonate-rich layer that protects the stomach lining: HCl(aq) + HCO(aq) HO(l) + CO(g) This isn't a complete neutralization—it's a protective buffer. The mucus-bicarbonate barrier maintains a near-neutral pH right at the epithelial surface while the lumen remains strongly acidic. Without this, the stomach would digest itself.
One counter-intuitive detail that most textbooks skip: the stomach doesn't just passively neutralize acid. It actively pumps H ions against a massive concentration gradient using the H/K ATPase pump. This means neutralization is always fighting an uphill battle. Any antacid you take is dealing with a system that is continuously generating more acid. The equations above represent snapshots, not the full dynamic picture. In a real stomach, you're measuring a moving target where acid secretion can reach up to 150 mmol/hour during peak stimulation. Another nuance people miss is that the chloride ion from HCl doesn't just disappear. It ends up as various metal chlorides depending on what neutralizing agent is used. Aluminum chloride, magnesium chloride, calcium chloride, sodium chloride—these are all byproducts. In healthy individuals, the kidneys handle the excess ions. But in patients with renal impairment, aluminum and magnesium accumulation becomes a serious concern. I once reviewed a case study where a chronic kidney disease patient on long-term aluminum hydroxide antacids developed. The equation on paper looked benign. In practice, it was dangerous.
Practical Application
If you need to write these equations for a class or lab report, here's the quick reference: Strong acid-base neutralization (bicarbonate): HCl + NaHCO NaCl + HO + CO Insoluble hydroxide neutralization (aluminum): 3HCl + Al(OH) AlCl + 3HO
Insoluble hydroxide neutralization (magnesium): 2HCl + Mg(OH) MgCl + 2HO Carbonate neutralization (calcium): 2HCl + CaCO CaCl + HO + CO Bicarbonate buffer protection: HCl + HCO HO + CO
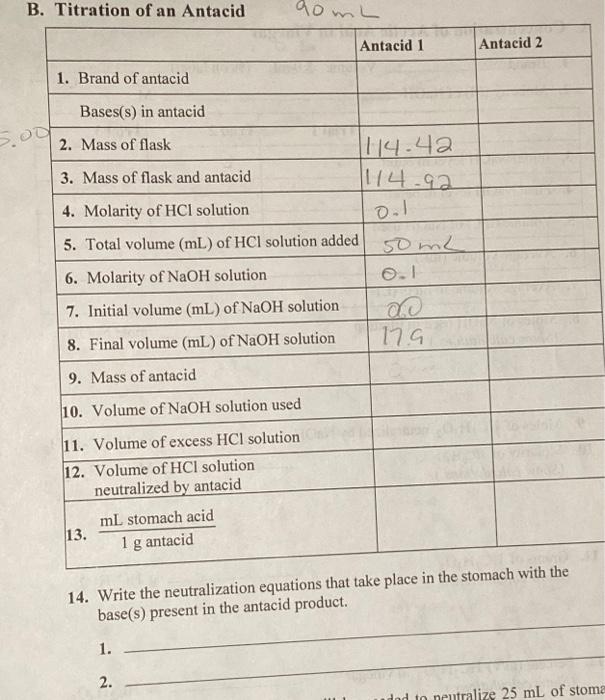
Make sure your equations are balanced and include state symbols. That's usually where points get deducted. And remember that these are simplified representations. The actual stomach environment contains pepsin, mucus, food particles, and ongoing acid secretion, so the kinetics and equilibrium are far more complex than what any single equation shows.