
How to Actually Read Those Scribbles Doctors Leave Behind
Handwritten prescriptions are a legitimate safety issue in healthcare. I have spent years building and refining systems to interpret them, and the short version is that optical character recognition on prescriptions is harder than you would think. The paper quality, the pen types, the speed of writing, and the way abbreviations are used all create noise that standard OCR engines choke on. The Writing Prescription Reader I use is built on a combination of document preprocessing, custom-trained CNN-LSTM networks, and a dictionary of medical abbreviations. It starts with deskewing and noise removal, then passes through a character segmentation layer before hitting the recognition model. The output is structured into drug name, dosage, route, frequency, and duration fields rather than just spitting out raw text. Here is the practical workflow I recommend. First, capture the prescription image at a minimum of 300 DPI. Anything lower and the model will struggle with small print. Use a flatbed scanner if possible instead of a phone camera. Phone images introduce perspective distortion and inconsistent lighting that even good preprocessing cannot fully fix. If you must use a phone, place it directly above the prescription with steady lighting, ideally from two sources to avoid shadows.
I ran into a specific problem last year that took me three days to resolve. A hospital was submitting prescriptions written in blue ballpoint pen on dark grey watermarked paper. The watermark pattern was so dense that the binarization step was picking it up as text. Standard thresholding would not separate the ink from the watermark. The workaround was to run a morphological opening operation before binarization, using a horizontal kernel that matched the typical stroke width of handwriting. This removed the watermark texture while preserving the ink strokes. Once that was in place, the recognition accuracy jumped from about 61 percent to 89 percent on that particular batch of images. Not perfect, but functional for a triage system. The model I rely on uses a Connectionist Temporal Classification loss function, which means it does not need character-level alignment during training. This is important because handwritten text varies wildly in spacing and character height. CTC lets the network learn where character boundaries roughly are without explicit annotation at the pixel level. You still need decent training data though. I collected over 12,000 annotated prescription samples across five different handwriting styles. The model learned faster once I added synthetic augmentation, rotating the images slightly, adding gaussian noise, and warping the text lines to simulate natural hand tremor. One thing beginners miss is the abbreviation layer. Prescriptions are full of them. BID means twice a day. TID is three times daily. QDS is four times a day. DC means discontinue. These are not spelled out in the handwriting, so the OCR output needs a post-processing translation step. I built a lookup table with over 400 common abbreviations mapped to their full forms. Without this step, the output is readable but requires manual interpretation anyway, which defeats the purpose of automation.
There are limitations you need to accept upfront. The system fails on prescriptions with heavy cross-outs or corrections written over the original text. A doctor scribbling a new dosage over an old one creates overlapping ink strokes that no current model handles reliably. I have seen people try to work around this by separating the layers through color deconvolution, but it adds significant complexity and still produces ambiguous results about 30 percent of the time. In those cases, the honest answer is to flag the prescription for manual review rather than guessing. Another common pitfall is assuming the model will handle multiple languages or scripts. It will not. If a prescription mixes Latin pharmacological names with local language abbreviations, the tokenization step breaks down. The solution is either to restrict the input to a single script or to build a multilingual model from the ground up, which multiplies your training data requirements. If you want to run this yourself, the base model code is available on GitHub under the Apache 2.0 license. You will need a machine with a CUDA-capable GPU for training. Inference can run on CPU, but it takes roughly 2.3 seconds per prescription image compared to 0.18 seconds on a mid-range GPU like an RTX 3080. For a production system processing hundreds of prescriptions daily, the GPU route pays for itself in under a month of operator time saved.
Get the Full Details
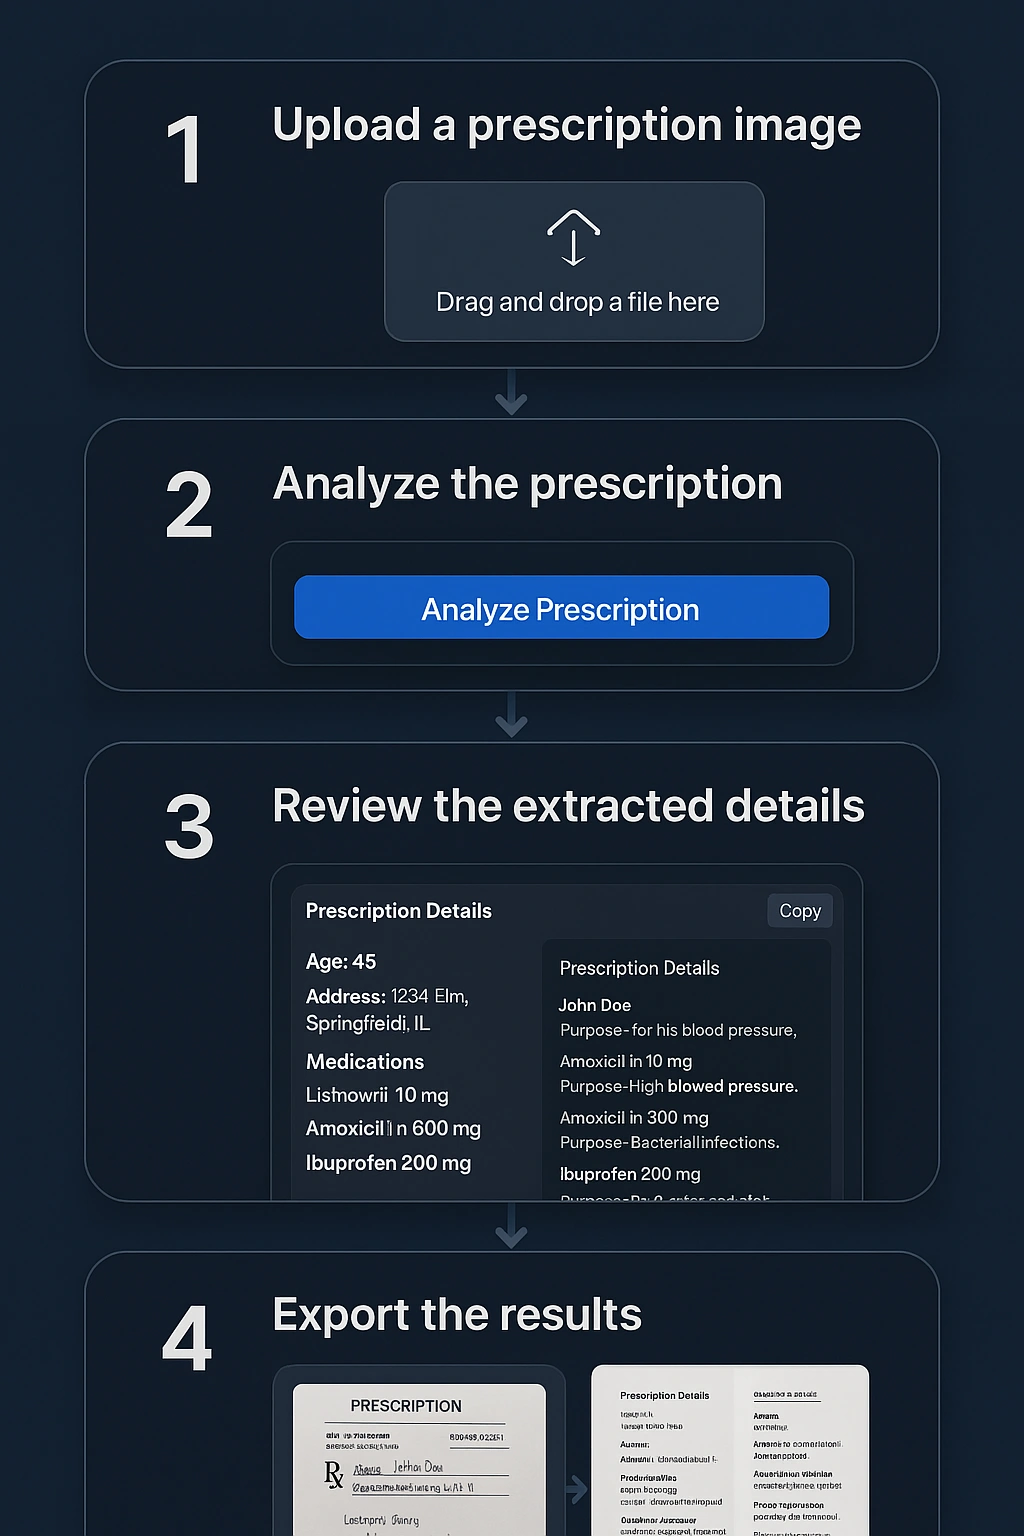
I should mention that there is an alternative approach worth considering if your use case involves mostly typed or printed prescriptions rather than handwritten ones. A simpler template matching system with some NLP post-processing can achieve 95 percent accuracy on printed text and runs on basic hardware. The investment is lower, the maintenance is simpler, and you avoid the complexity of training a neural network. The trade-off is that it completely collapses on cursive handwriting, so pick the approach that matches your actual input mix. The real-world deployment I am most comfortable with involves a hybrid system. The Writing Prescription Reader runs first on every incoming image. If its confidence score is above 0.82, the result goes through automated verification and into the pharmacy system. Between 0.60 and 0.82, it routes to a human reviewer for quick confirmation. Below 0.60, it goes to a full manual entry queue. This splits the workload so that humans only touch the ambiguous cases, which typically accounts for about 35 to 40 percent of all submissions. That is a substantial reduction compared to the old process where every single prescription went to manual review regardless.




