Reading X-Linked Recessive Pedigrees Without Losing Your Mind
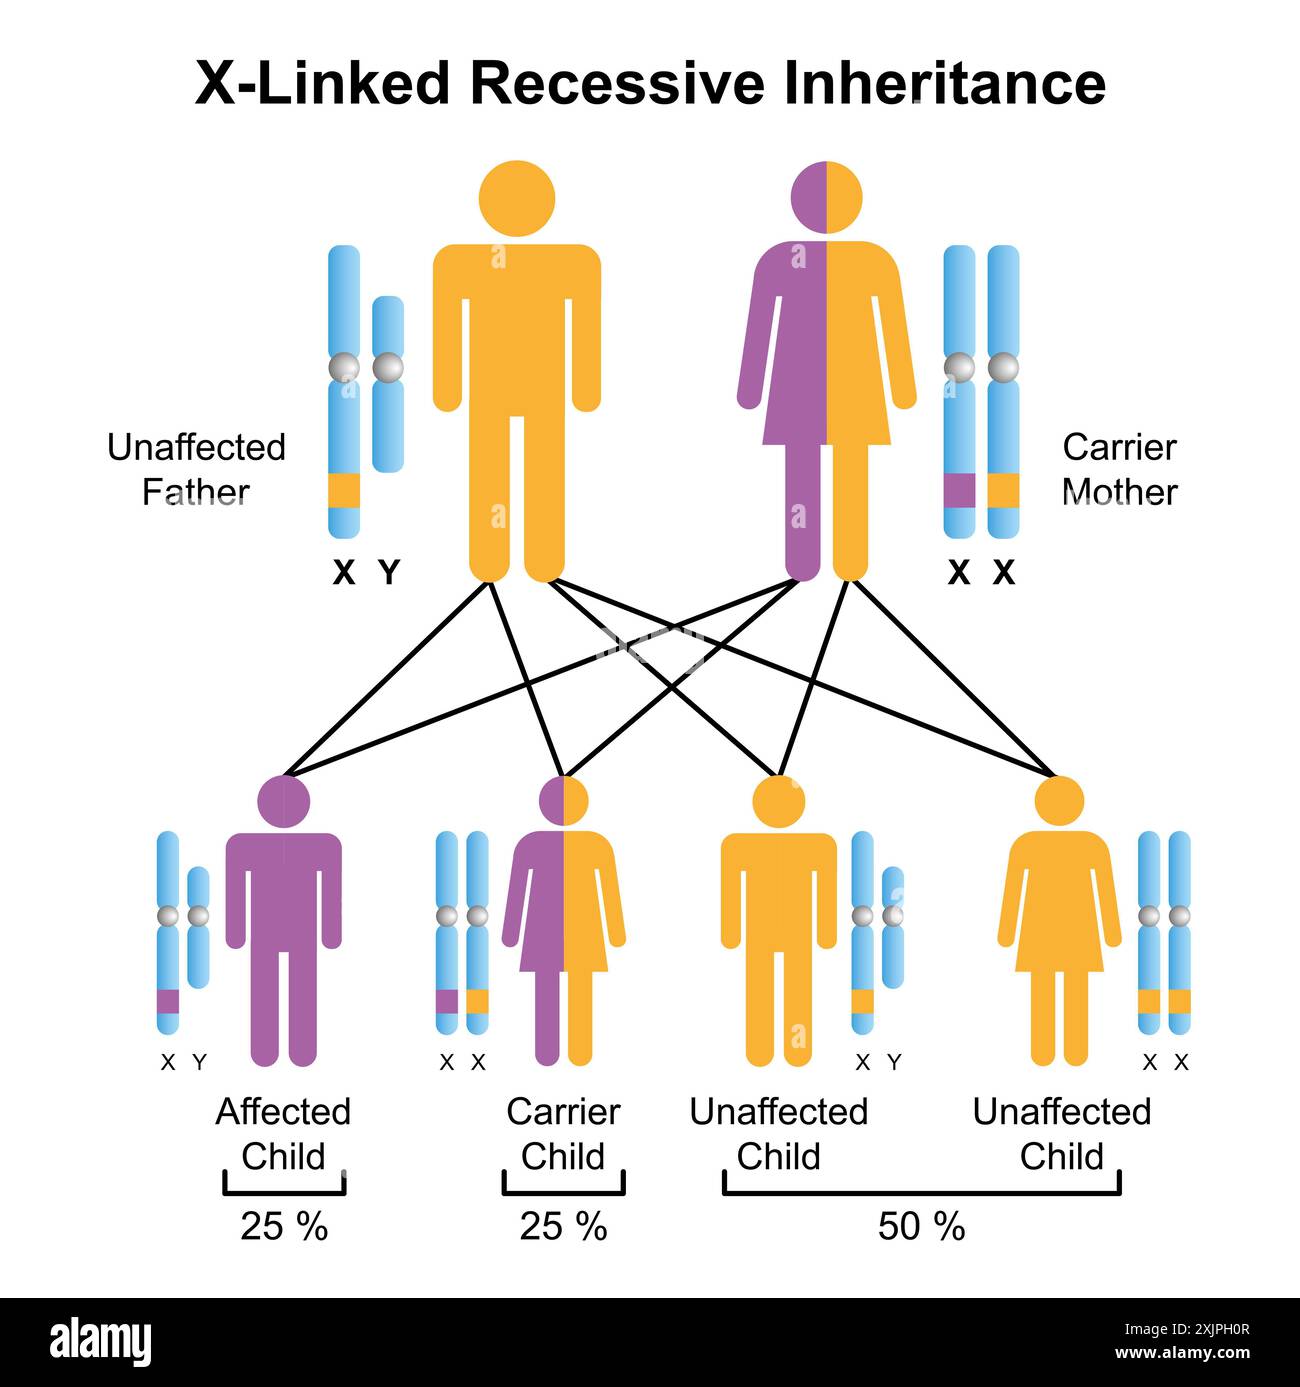
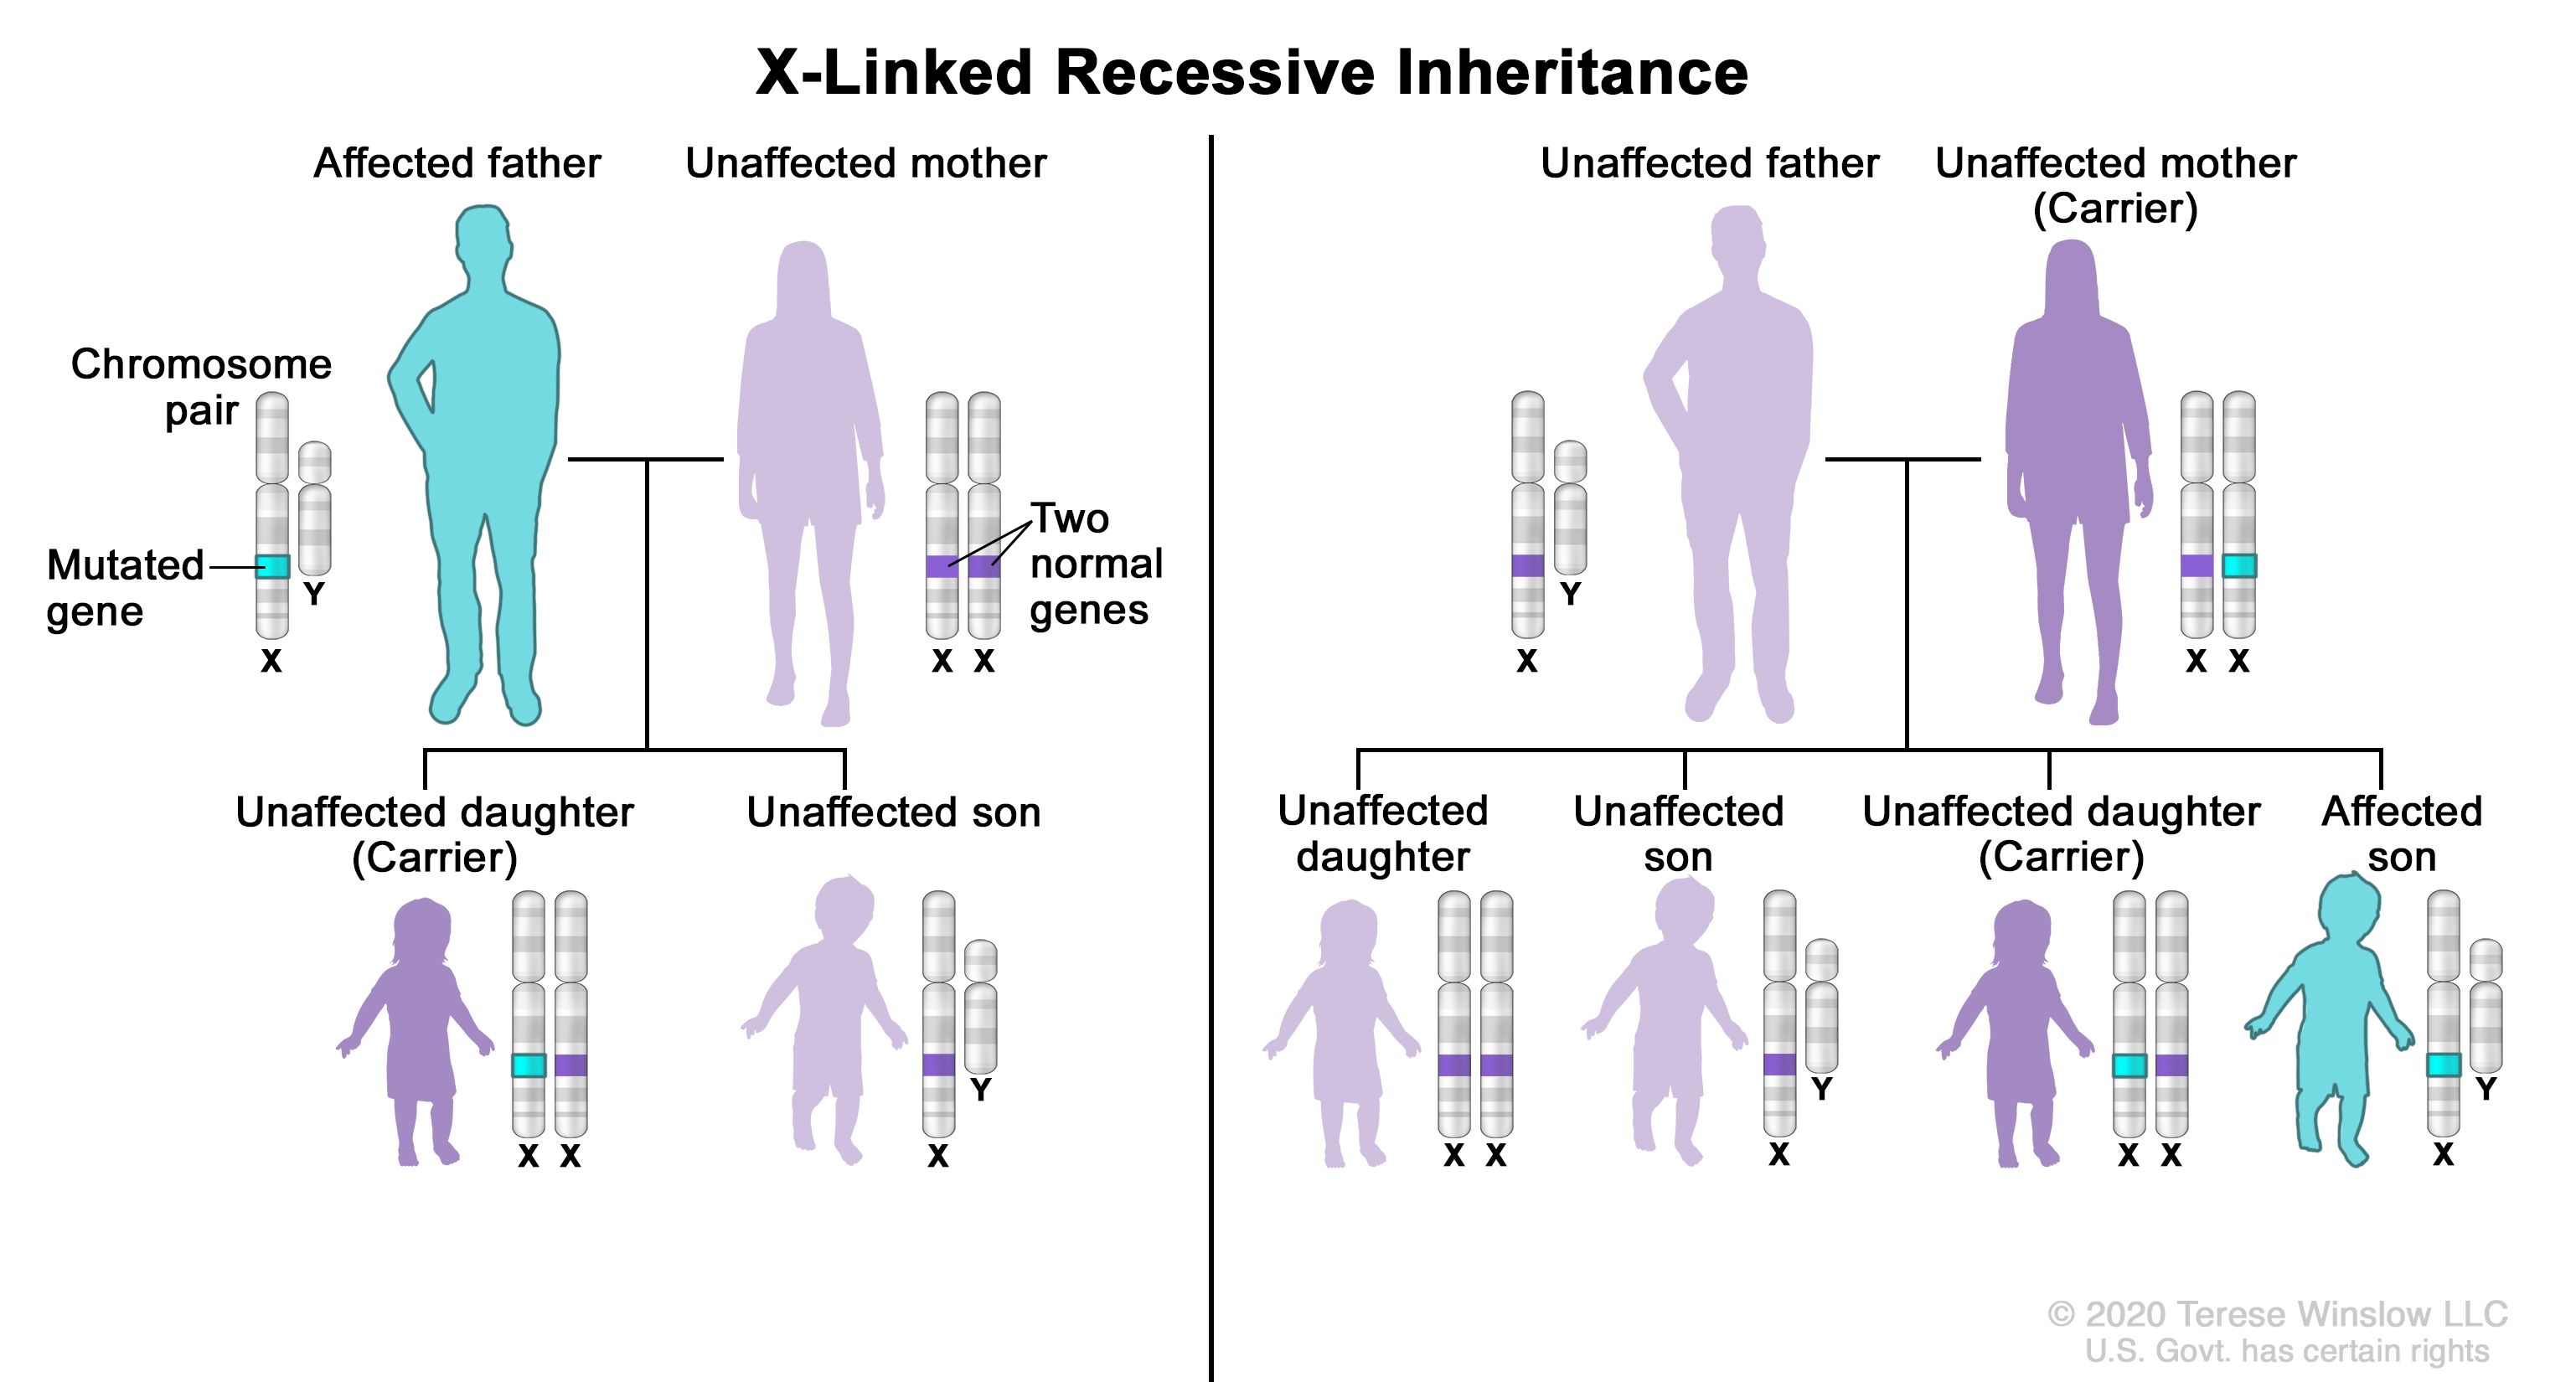
Most people mess up X-linked recessive pedigrees because they try to memorize rules instead of understanding what's actually happening to the chromosomes each generation. I've been doing this for long enough that I still catch myself second-guessing when something doesn't add up, but the mistakes usually come from overlooking one specific detail rather than any fundamental misunderstanding. Males have one X and one Y. Females have two Xs. That is the entire mechanism. Everything else is just applying that simple fact across multiple generations while tracking which sex got which parental chromosome. When a father passes his X to a daughter, she receives it along with a normal X from her mother. She is now a carrier if his X carried the recessive allele. He cannot pass that X to a son because sons get the Y from dad. This is the single most important observation and it eliminates entire branches of a pedigree from having the trait passed father-to-son.
Females pass one of their two Xs randomly to each child. If a carrier mother has a 50 percent chance of passing the affected X to each son, those sons will be affected because they have no second X to compensate. Daughters who receive that affected X become carriers, assuming the father contributes a normal X.
How to Actually Draw and Read the Pedigree
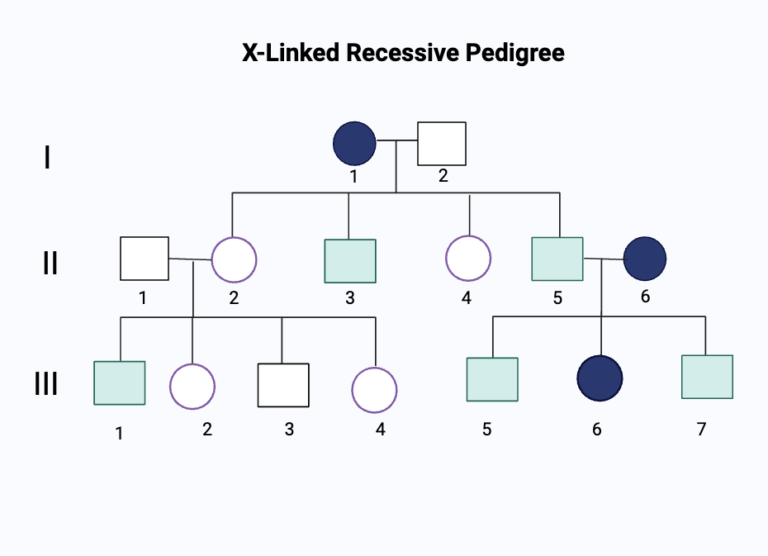
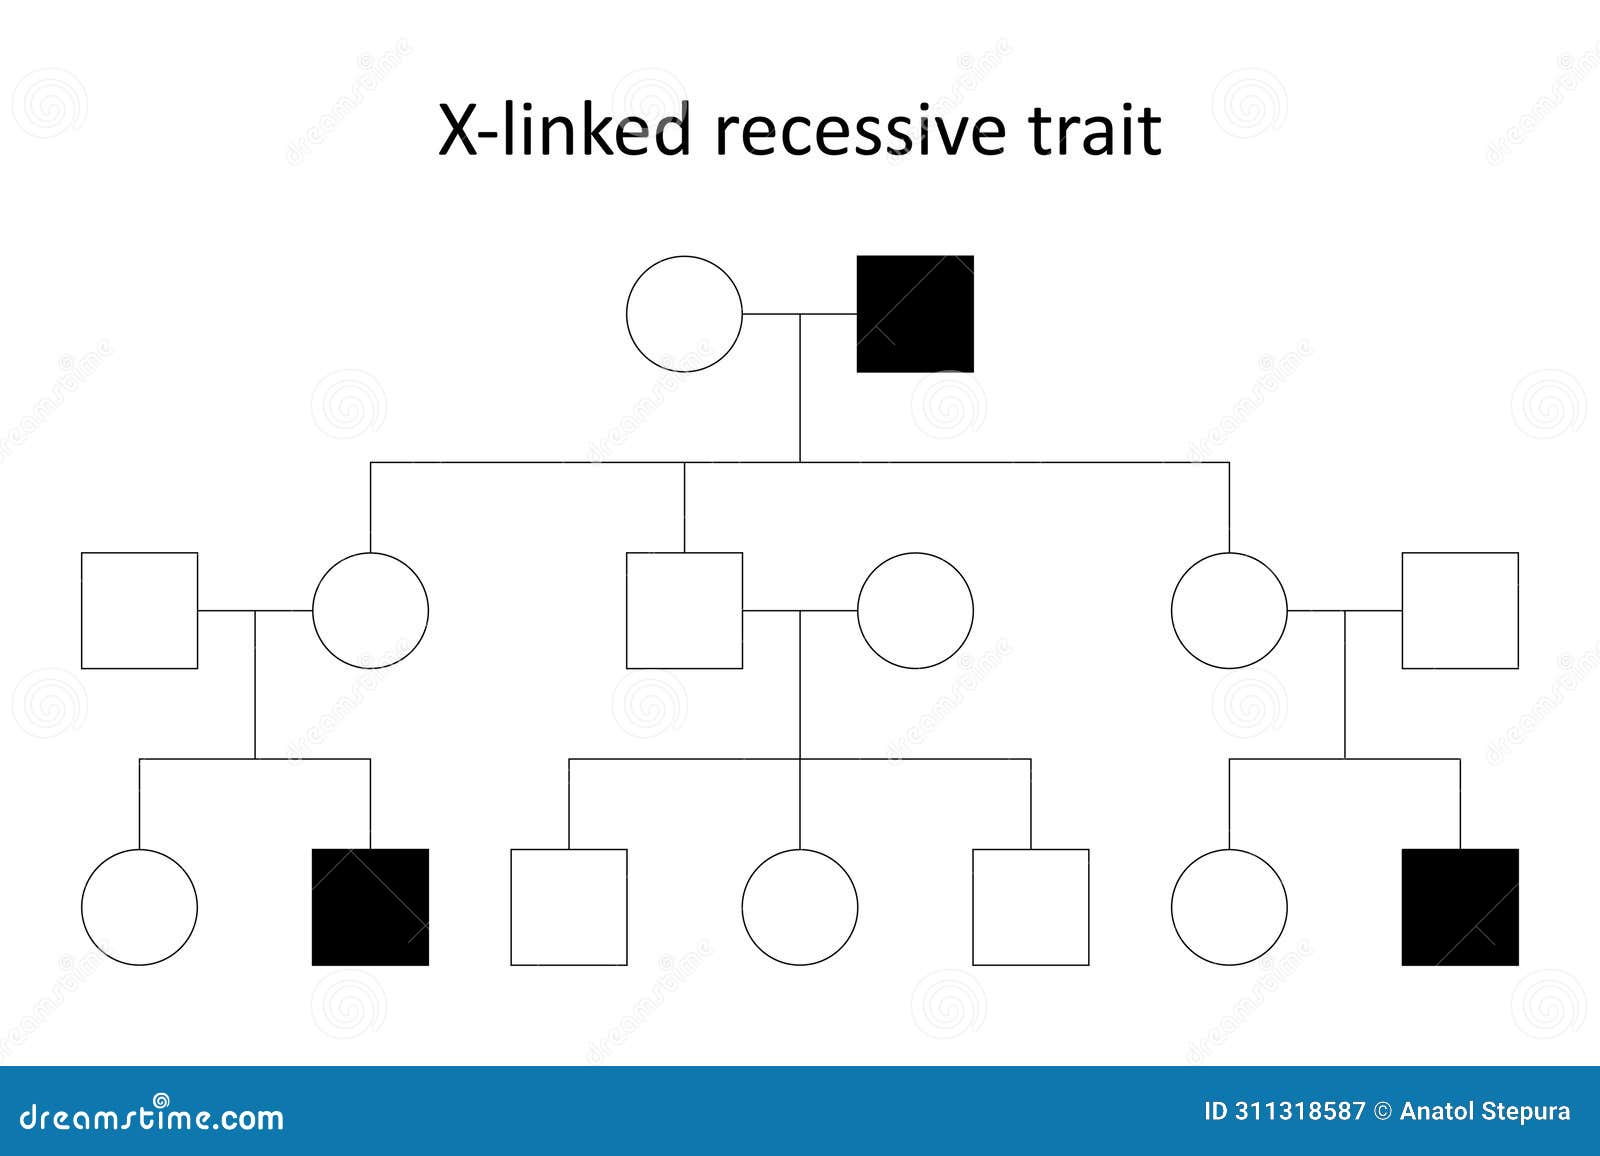
Start by filling in every known carrier possibility before worrying about predictions. The standard notation uses squares for males, circles for females, and shaded symbols for affected individuals. Half-shading indicates carriers, though many textbooks and clinical reports omit carrier shading entirely, which causes confusion when you're working from incomplete family histories. I work through these pedigrees in a specific order because skipping steps leads to errors. First, I mark every affected individual. Then I work backward to identify mandatory carriers—daughters of affected fathers who show no symptoms are always carriers. This step alone resolves about forty percent of what would otherwise look like a contradiction. After that, I assign probable carrier status to mothers of affected sons when the father is unaffected. The math is straightforward: an affected son must have received the recessive allele from his mother since fathers give Y chromosomes to sons. If the mother is not a known carrier from a previous generation, she is assumed to be a new carrier.
Get the Full Details
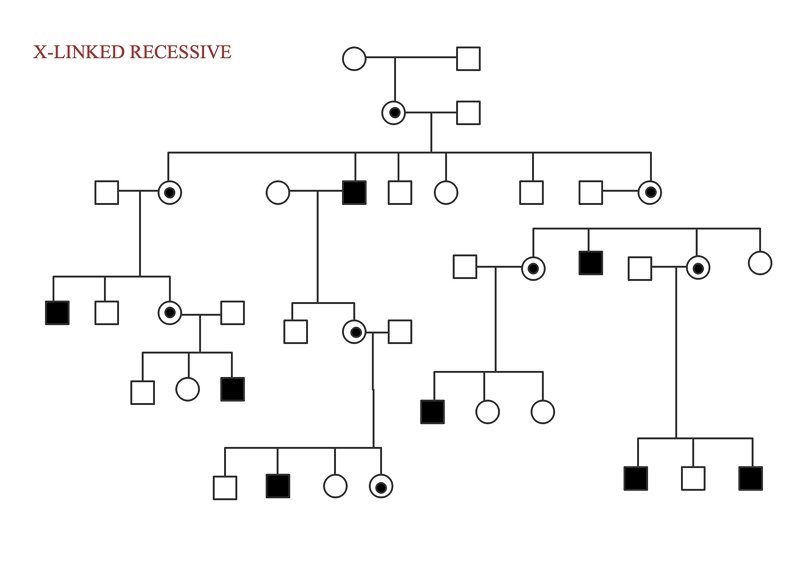
The trickiest part is handling families with limited information. I once spent two hours on a pedigree that looked like it contradicted X-linked recessive inheritance until I realized the consulting family had only reported three generations when four were relevant. The affected grandmother's sister was the true carrier who passed the trait through to multiple branches, and her absence from the chart made the pattern look sporadic rather than inherited.
X Linked Recessive Pedigree Patterns You Need to Recognize
These conditions show up repeatedly and knowing the pattern saves time. Hemophilia A and B are the classic examples. Duchenne muscular dystrophy, red-green color blindness, G6PD deficiency, and fragile X syndrome all follow this pattern. Some conditions like ornithine transcarbamylase deficiency can appear in heterozygous females due to skewed X-inactivation, which complicates the simple carrier model. When you see a pedigree where affected males appear on the maternal side through multiple generations with no father-to-son transmission, that is your primary signal. The trait may seem to skip a generation when it passes through carrier females, but that skipping is not true skipping. The allele is present in the carrier mother; it is only not expressed because she has a second normal copy.
A counter-intuitive detail that trips people up involves X-inactivation. Carrier females are not always completely asymptomatic. In conditions like X-linked adrenoleukodystrophy, skewed inactivation can produce significant symptoms in heterozygous females, making the pedigree look more complex than a simple recessive model predicts. I have seen several pedigrees dismissed as autosomal recessive when the female carriers were actually mildly affected but undiagnosed.
Common Pitfalls and Where the Method Falls Apart
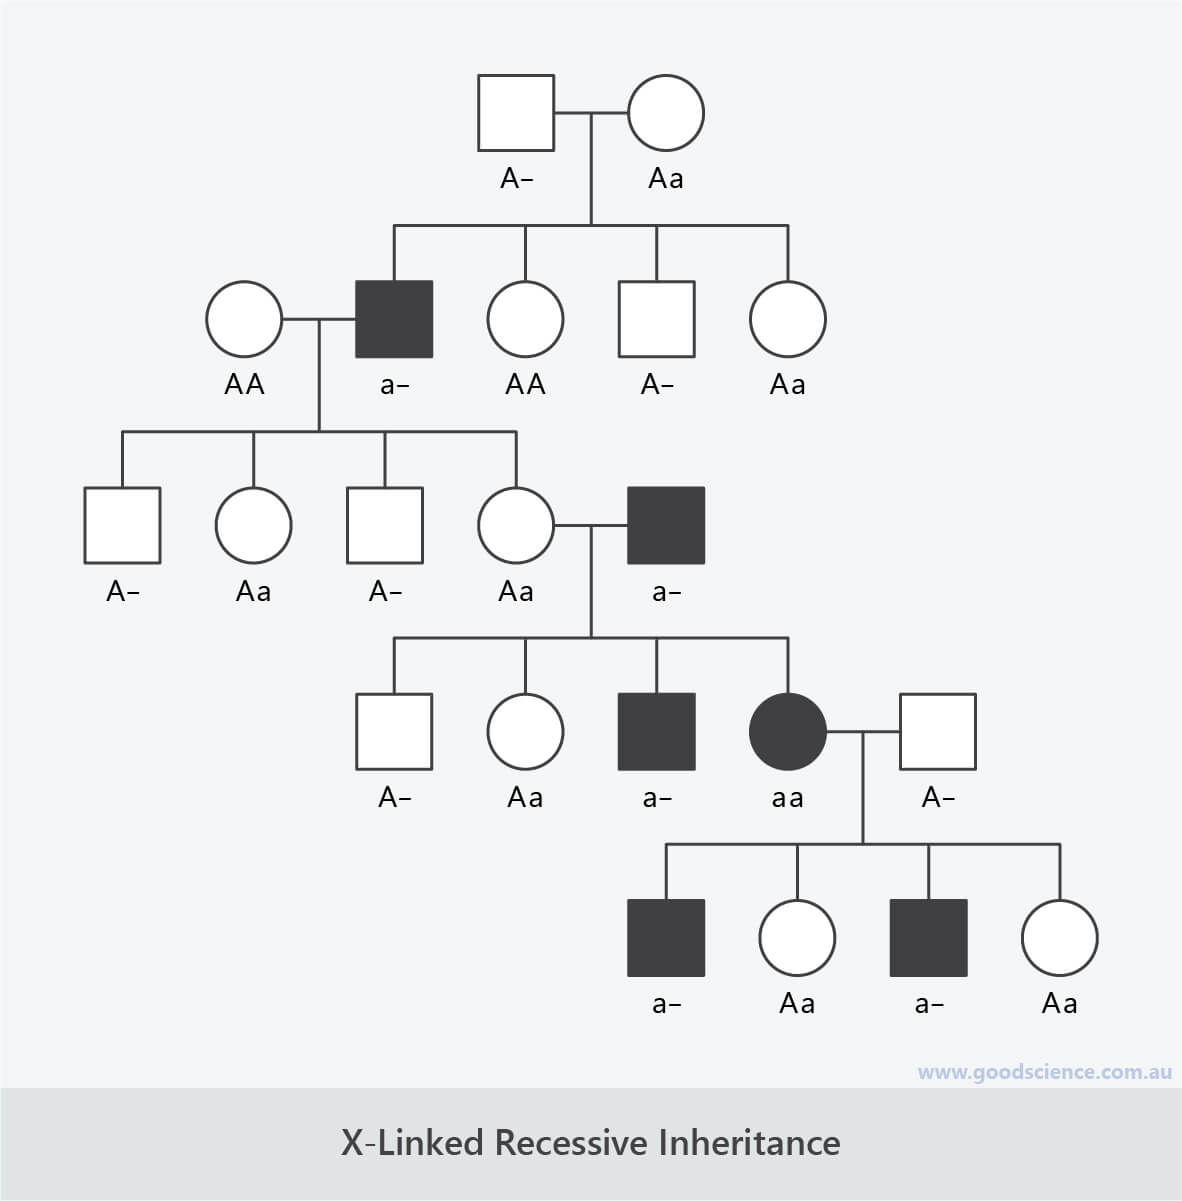
Pedigree analysis alone cannot definitively prove X-linked recessive inheritance. It can be consistent with it, but autosomal recessive traits can mimic the same pattern when the carrier frequency in the population is high enough. The only way to confirm is molecular testing of the specific gene. I have retracted pedigree conclusions multiple times after genetic testing revealed a different inheritance pattern than the family tree suggested. De novo mutations complicate everything. Approximately thirty percent of Duchenne muscular dystrophy cases result from new mutations with no family history. A pedigree showing a single affected boy with no carrier mother in the available family tree is often assumed to be a new mutation, but modern testing usually reveals that the mother carries the mutation in a mosaic state or at low levels that standard carrier screening missed. Another frequent error involves assuming that all daughters of affected males must be carriers. This is true unless the mother also carries the recessive allele, in which case a daughter could be affected. I have seen this scenario overlooked when both parents happen to carry the same X-linked allele, which occurs in communities with high consanguinity or founder effects.
Practical Workflow for Real Cases
When I receive a pedigree, I do it in roughly fifteen minutes for straightforward cases. The bottleneck is always incomplete family information. I ask for at minimum three generations of sex and disease status for both sides of the family. Without that, probability calculations become guesses rather than analysis. For risk calculation, I use Punnett squares for each mating pair rather than trying to estimate mentally. It seems slow at first but prevents arithmetic errors that require redoing half the pedigree. Carrier probability for an unaffected sister of an affected male is fifty percent, assuming the mother is a confirmed carrier. If the mother's carrier status is uncertain, the probability drops based on prior probability calculations that incorporate the family history. When dealing with prenatal counseling scenarios, I separate the questions clearly. The question of whether a woman is a carrier is different from the question of whether a male fetus is affected, and conflating them leads to incorrect risk estimates. Carrier testing should come first. If the mother is not a carrier, the recurrence risk for future pregnancies is essentially population-level unless a new mutation is suspected.
The biggest frustration with this type of analysis is that incomplete pedigrees are the norm rather than the exception. Adoption, small families, and relatives who refuse to discuss medical history all reduce the usefulness of the chart. In those situations, molecular carrier testing of the woman in question is often more informative than extending the pedigree analysis further.