Reading the fracture lines on a hand X ray
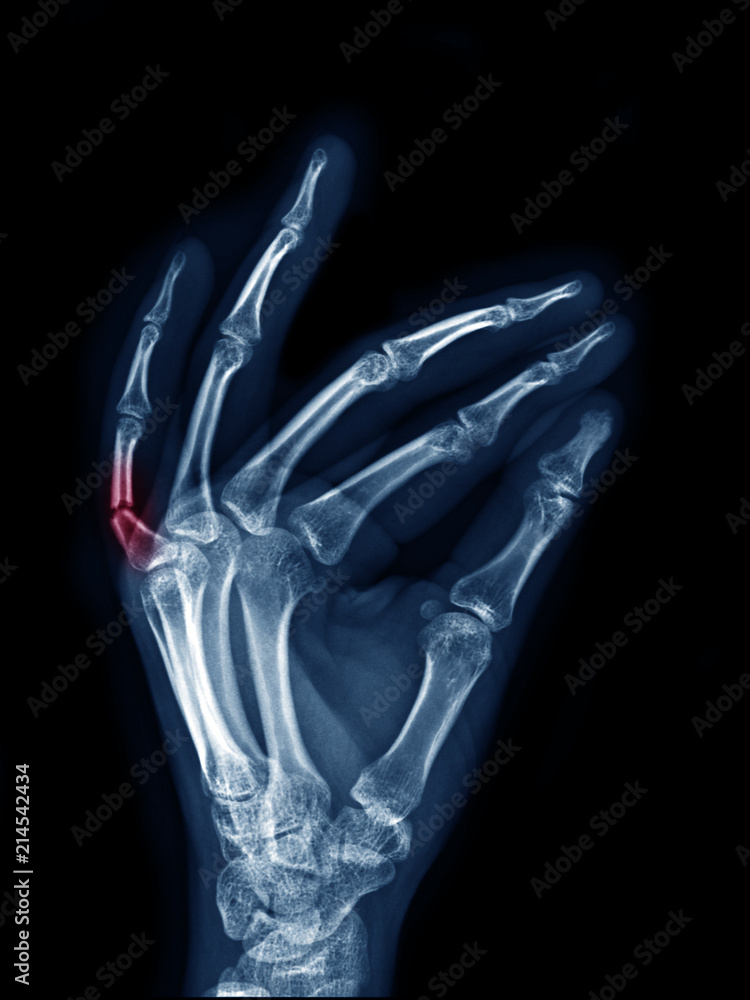
Most people think you need a radiology fellowship to understand a fractured hand on film. You don't. What you need is to know where to look and what to ignore. The tricky part isn't seeing the break; it's deciding whether that lucency is real or just superimposition of two bones on top of each other. I spent seven years in the emergency department reading hand films before moving to musculoskeletal radiology. The hardest lesson was learning to stop trusting my first impression. A hairline fracture along the base of the proximal phalanx can look identical to a growth plate remnant in a young adult. One gets you surgery; the other gets you dismissed. Both are visible on a standard PA view if you squint hard enough.
X Ray Of Fractured Hand imaging protocol
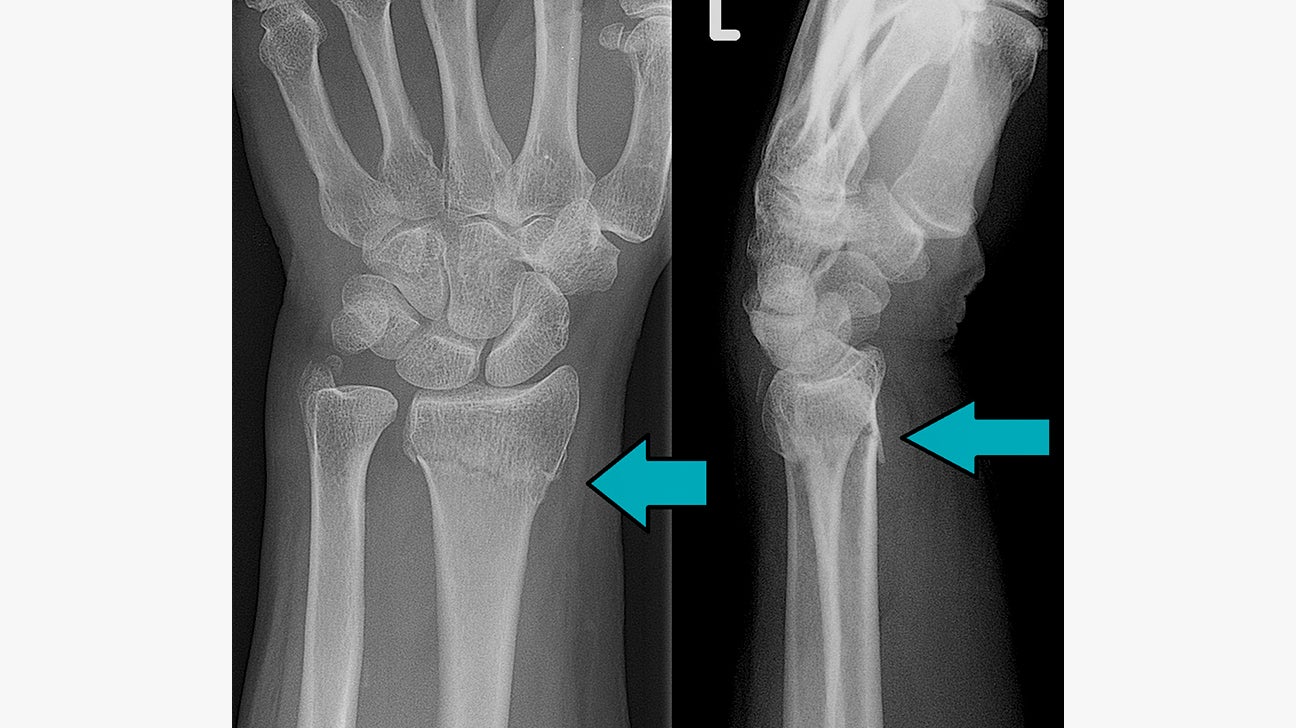
Standard hand series is three views: PA, lateral, and oblique. That's it. Don't ask for more unless something doesn't add up. Each view tells you something different about the fracture pattern. The PA view shows you comminution and shortening. You're looking at whether the metacarpal has shortened, rotated, or angulated. The lateral view reveals dorsal or volar angulation, which is the difference between a manageable fracture and one that needs reduction. The oblique view separates overlapping structures so you can actually see the cortex. Here's where beginners mess up. They look at the PA first and assume they've got the whole picture. But a transverse fracture through the neck of the fifth metacarpal, the classic boxer's fracture, often hides on the PA view. It becomes obvious only on the lateral. I had a case last year where a surgeon marked a patient forORIF based on the PA alone, then rotated the hand and realized the fracture line was missing. The rotation changed the plane of the x-ray beam relative to the fracture, and suddenly the line appeared like it was drawn with a marker.
Cortical step-off versus normal anatomy
One thing I learned the hard way: normal hand anatomy has more variability than textbooks admit. The distal radius metaphysis can have subtle ridges and grooves that look suspicious if you don't know better. Same with the carpals. The lunate and triquetrum have articular facets that sometimes appear as lucent lines on certain angles. A cortical step-off greater than one millimeter is usually significant. That's the benchmark most attending radiologists use. Less than that and you're probably looking at superimposition artifact or a normal variant. But here's the catch: step-off alone doesn't dictate management. A two-millimeter step-off in the second metacarpal neck might be fine because the second ray is fixed by its neighbors. The same step-off in the fifth metacarpal could cause functional problems because the fifth ray moves freely during grip. I've seen orthopedic residents get hung up on measurements while missing the actual fracture line because they were too busy using calipers on the PACS workstation. The fracture was there, visible on every view, but they were so focused on quantifying displacement that they stopped looking for the actual break. Take your time with the images. Walk away from the screen, stare at the bone, then come back and look again. It sounds obvious, but the second look usually finds what the first one missed.
Get the Full Details
Rotation and how to spot it
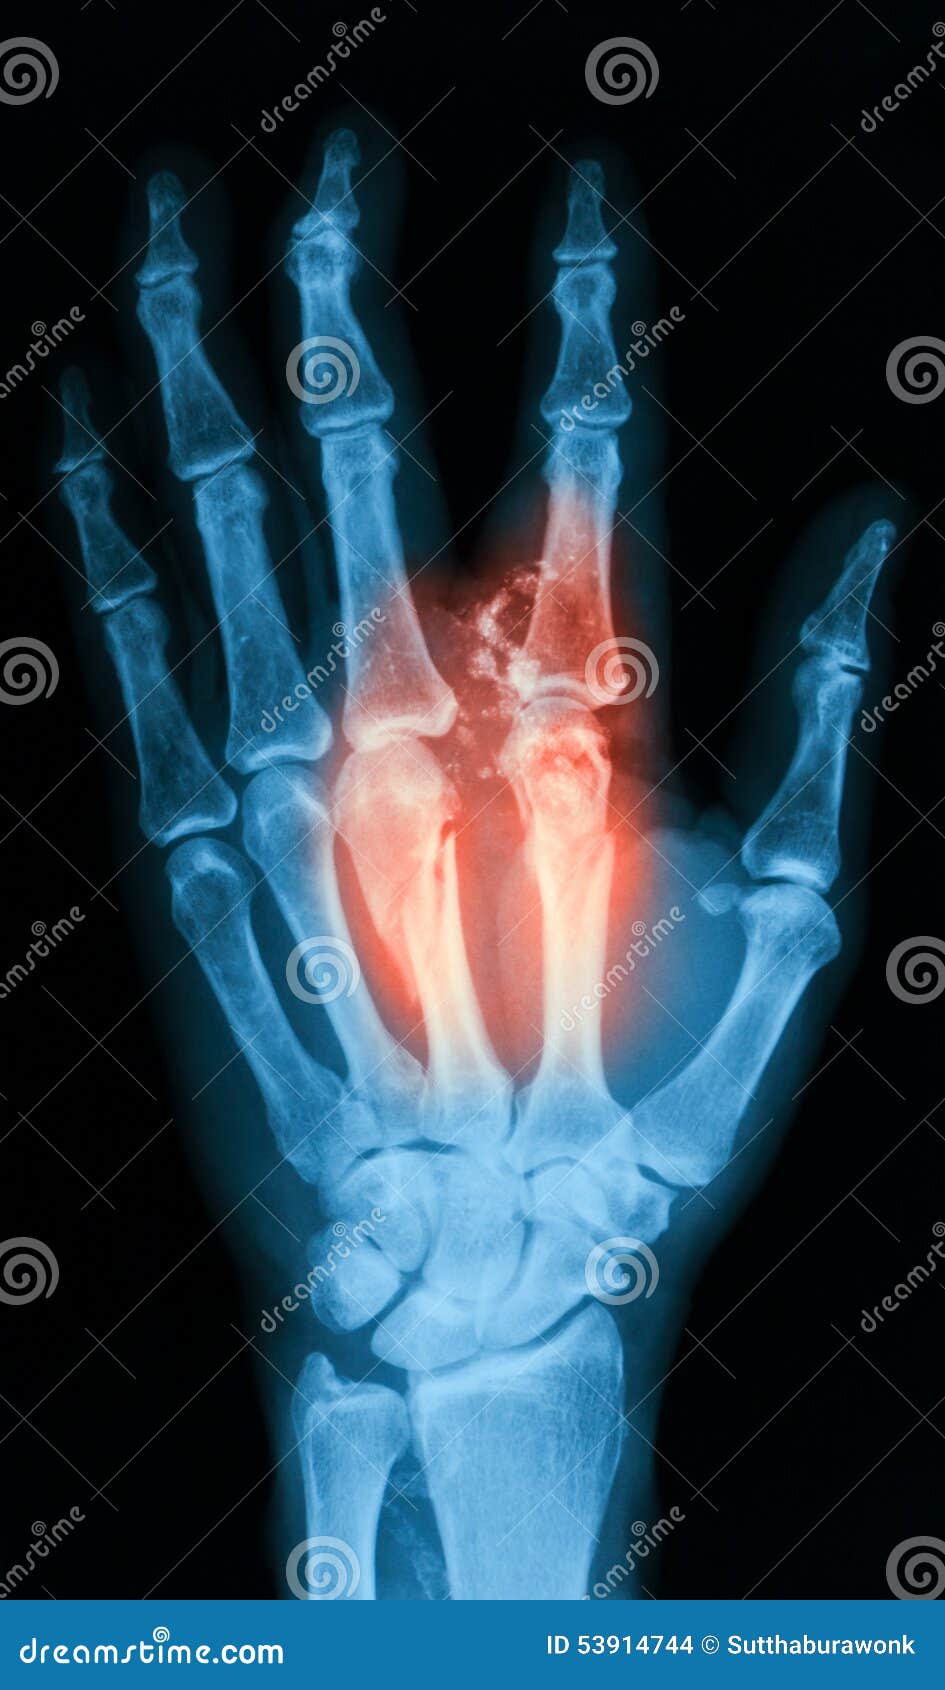
Rotational malalignment is the most common complication of hand fractures that people try to treat conservatively. When fingers flex, they should all point toward the scaphoid tubercle. If one finger crosses over another when the hand makes a fist, that's rotational deformity, usually from spiral fracture of a metacarpal shaft. You can assess rotation clinically without a x-ray, but confirmation on imaging helps. On the PA view, look at the overlap of the radial and ulnar margins of the metacarpal shafts. When a bone is rotated, those margins become asymmetric. Normally they should be roughly parallel and symmetric. When one side looks wider and the other narrower compared to the adjacent bone, something is off-axis. I remember a case where a patient came in with a suspected fifth metacarpal fracture. The PA view showed nothing dramatic. The lateral showed minimal angulation. But on the oblique, the cortex was clearly disrupted with a small floating fragment. The fracture was occult on the first two views because the beam was parallel to the fracture plane. Three-dimensional CT would have shown it immediately, but at that point I already had enough information to proceed with ORIF, so we saved the patient radiation and cost.
When X ray misses the fracture
Sometimes the x-ray is clean and the patient is still in pain. This happens more often than you'd think with scaphoid fractures and stress fractures of the metatarsals and metacarpals. The initial film can be completely normal for up to two weeks after injury because the bone hasn't resorbed enough at the fracture site to create visible lucency. The workaround is straightforward. You splint the patient based on clinical suspicion, not the negative x-ray, and repeat imaging in ten to fourteen days. By then, callus formation or resorption makes the fracture visible. If you need earlier confirmation, MRI is the gold standard for occult fractures. It shows bone marrow edema within days of injury, which is way earlier than x-ray can detect anything meaningful. I once read a follow-up series where the original scout film was dismissed as normal, but the lateral view of the same hand showed a faint but definite fracture line through the waist of the scaphoid. The PA and lateral were taken thirty seconds apart, probably by the same tech without any adjustment to the beam angle. What looked invisible on one projection was perfectly clear on the other because the fracture line ran in a different plane relative to the x-ray beam. This is why positioning matters more than equipment quality.
Metacarpal fracture patterns that matter
Not all hand fractures are created equal. A non-displaced fracture of the second metacarpal shaft is managed completely differently from a displaced fracture of the fifth metacarpal neck. The second and third rays form the fixed central column of the hand. They don't tolerate much angulation or shortening before grip function suffers. The fourth and fifth rays are mobile. They can tolerate more deformity because they move during grasp. Jones fracture of the fifth metatarsal gets all the attention, but avulsion fractures of the fifth metacarpal base are common and often confused with Jones. The blood supply differs between the two, which affects healing potential. A Jones fracture has a relatively avascular zone near the fracture site and carries a higher nonunion risk. A base avulsion from the dorsal ligaments usually heals fine with immobilization alone. On imaging, the Jones fracture appears through the metaphyseal-diaphyseal junction, about fifteen millimeters distal to the tuberosity. The avulsion fracture is more proximal, right at the base. But this measurement is approximate and individual anatomy varies. What matters more is the morphology. Jones fractures tend to be transverse or slightly oblique with a gap. Avulsion fractures are often smaller fragments with cortical continuity.
Practical limits of plain film
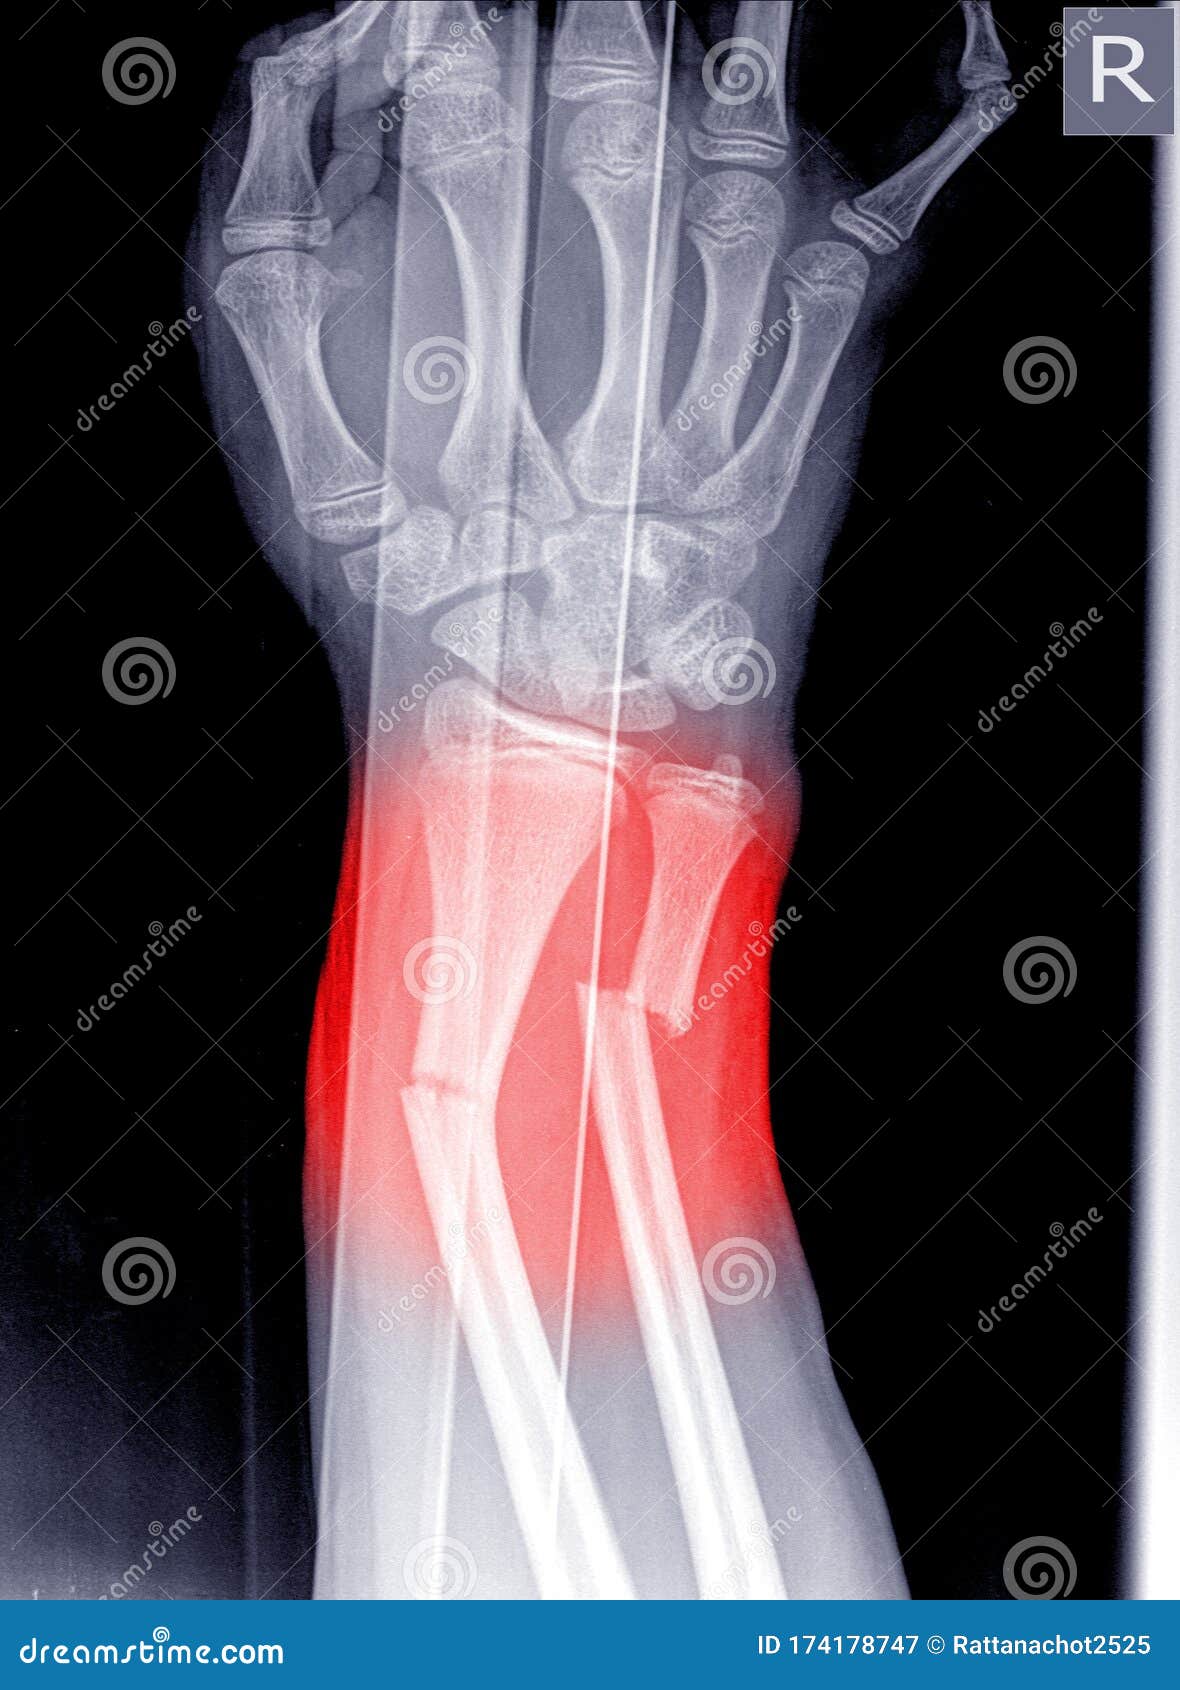
X ray Of Fractured Hand assessment has real limitations. It's a two-dimensional representation of three-dimensional structures. Overlapping bones create shadows that can hide fractures or mimic them. Superimposition of normal anatomy is responsible for most false positives I see in practice. CT adds information but introduces radiation and cost. For most metacarpal and phalangeal fractures, CT is overkill unless you're planning surgery and need to understand the exact fragment configuration. Intraoperative fluoroscopy or preoperative CT becomes relevant for comminuted intra-articular fractures where screw trajectory matters. Ultrasound is emerging as a practical alternative for detecting hairline fractures in children and for guiding injections around fracture sites. It doesn't show bone detail as well as x-ray, but it can visualize fracture callus formation earlier and assess surrounding soft tissue damage. I use it selectively, mostly for follow-up of pediatric fractures where radiation exposure is a legitimate concern.
The bottom line is that x-ray remains the first-line imaging modality for hand fractures because it's fast, cheap, and usually diagnostic. But it requires proper technique, adequate views, and clinical correlation. A good film with no fracture found is infinitely more valuable than a perfect film showing nothing because the acquisition was rushed or the patient was poorly positioned.