
Reading abdominal radiographs for small bowel obstruction
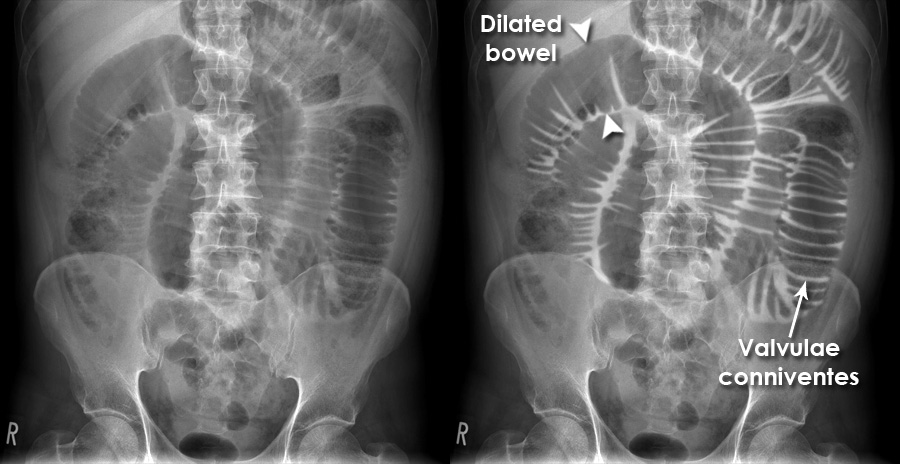
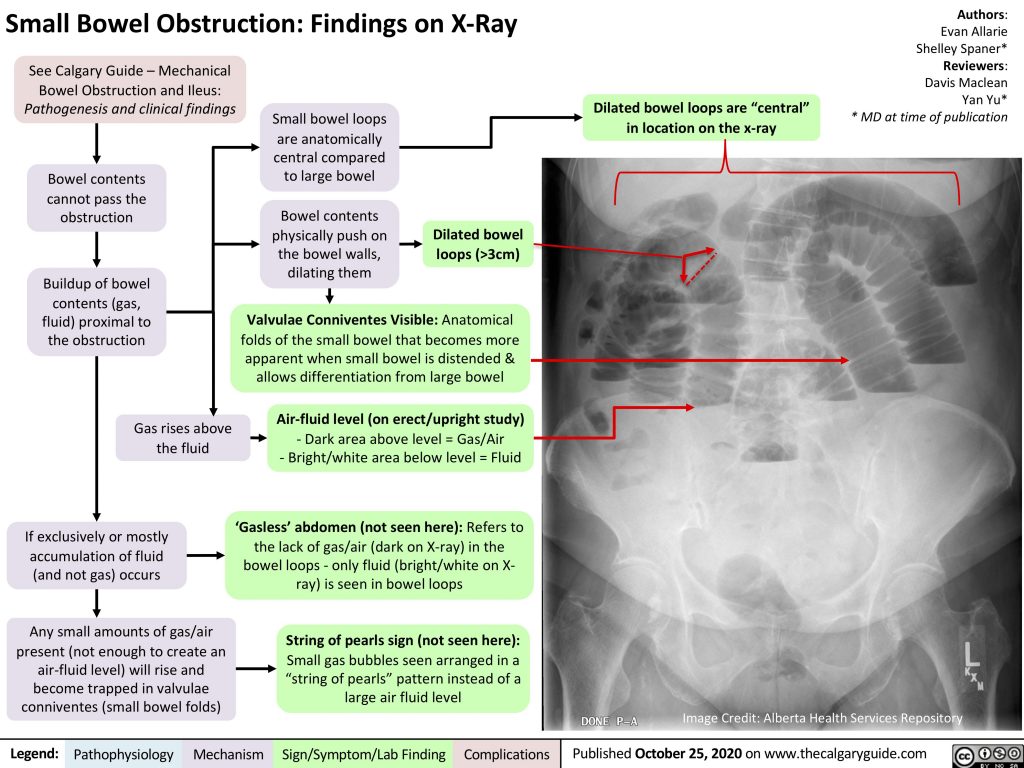
The first thing you need to know is that a plain film doesn't confirm the diagnosis. It tells you whether to worry and where to look next. I still rely on it heavily because it takes twenty seconds and costs almost nothing compared with CT, but I never let it override the clinical picture. Dilated small bowel loops are the starting point. The threshold most people use is greater than three centimeters for the small bowel lumen. If you see air-fluid levels on an upright or lateral decubitus view that are taller than two centimeters and stacked up more than three high in a single field of view, that is the classic pattern. The key is remembering that the small bowel is central and the colon is peripheral, and that valvulae conniventes cross the entire width of the loop whereas haustra do not. I once called a consult at 2 AM for what looked like a straightforward SBO on supine film. The patient had no surgical history, no prior obstructions, and was passing flatus. The CT showed a giant rectal fecaloma mimicking a transition point. Plain films overcalled obstruction in that case because the retained stool in the colon was pushing gas into the small bowel proximally. Do not skip the clinical correlation.
Technique that actually matters
Get the patient upright for a chest and abdominal view if they can stand. If they cannot, a left lateral decubitus with the right side up serves the same purpose for demonstrating air-fluid levels. Supine alone is insufficient for a complete evaluation. A KUB without upright or decubitus views misses about a third of the cases where air-fluid levels would change management. I tell the tech explicitly: if you only get one view, make it upright. The radiologist will thank you later. Use a low-kVp technique when possible. Better contrast resolution makes the valvulae conniventes visible, and that distinction between small and large bowel is where most mistakes happen. Modern digital systems compress the dynamic range aggressively, so the raw image often looks flat. Push the windowing manually before you call it normal.
Key findings and how to read them
Small bowel dilation above three centimeters is the headline finding. Look at the distribution. A mechanical obstruction usually has a transition zone where the bowel caliber changes abruptly. The proximal loops are dilated with air and fluid. The distal colon and rectum may be gasless or contain only a small amount of stool. In adynamic ileus, the dilation is more diffuse and involves both small and large bowel without a clear transition point. Air-fluid levels are best seen on upright views. The classic step-ladder pattern appears when multiple loops show different fluid levels at varying heights. This is not pathognomonic but it is highly suggestive when combined with dilated small bowel. On decubitus views, the fluid settles dependently and the air rises, making the levels horizontal regardless of patient positioning. Pneumatosis intestinalis changes everything. Gas within the bowel wall on plain film is a late and ominous sign indicating possible bowel ischemia or infarction. When I see this, I do not wait for the official radiology report. I page surgery immediately and tell them about the pneumatosis specifically. Time matters here more than any other finding on this exam.
Get the Full Details
Free intraperitoneal air under the diaphragm on an upright film is another finding that bypasses the queue. Even a small crescent of lucency under one hemidiaphragm in a patient with a suspected obstruction means you have a perforation until proven otherwise. A CT with oral contrast can confirm it, but you are not sending an acute abdomen to CT without a surgical consult already in progress.
Limits of plain film radiography
Plain films miss early partial obstructions regularly. The sensitivity for detecting a complete mechanical obstruction on KUB is roughly sixty to seventy percent in most series. Specificity is higher at around eighty percent, but that is only because the findings tend to be dramatic when present. Early or partial SBO frequently presents with normal or near-normal films. This is why the CT has replaced plain film as the definitive modality in most emergency departments, but plain film remains useful as an initial screening tool when CT access is delayed or when you need a rapid answer at the bedside in an unstable patient. The films also struggle to identify the cause of obstruction. A band adhesion, an internal hernia, a neoplasm, and a volvulus can all look identical on a KUB. You need CT with IV contrast, preferably with enteric contrast when the patient can tolerate it, to characterize the transition point and the etiology. I still order the plain film first in most protocols because it establishes a baseline and helps triage the urgency, but I do not let a normal film reassure me in a patient with a high clinical pretest probability.
Practical workflow I use
I request a supine KUB and an upright chest and abdomen for any adult presenting with vomiting, abdominal distension, and colicky pain who might have an SBO. If the supine film shows dilated small bowel loops with air-fluid levels on the upright view, I classify this as radiographic evidence supporting obstruction and move straight to CT for confirmation and characterization. If the film is equivocal but the clinical suspicion remains high, I still go to CT rather than repeating the film later. The turnaround for CT is usually shorter than the time you save by avoiding a second set of films. For postoperative patients, interpretation is harder because some small bowel dilation is expected after abdominal surgery. I use a narrower threshold of greater than two point five centimeters in the early postoperative period and look for progression on serial films rather than relying on a single study. Serial comparison is where plain film still has an edge over CT for monitoring known obstructions conservatively.
When to skip the X Ray Of Small Intestinal Obstruction entirely
If the patient has a known history of SBO and is presenting with a recurrence of similar symptoms, and the physical exam and basic labs are stable, some teams go straight to CT without a plain film. This is defensible and saves radiation. I prefer the film in new presentations because it guides the urgency of the CT order and helps communicate the initial impression to surgery before the cross-sectional imaging arrives. The bottom line is that abdominal radiography for small bowel obstruction remains a practical first step but a poor endpoint. It detects established obstruction reasonably well and identifies the complications that require immediate intervention. It misses early disease and rarely identifies the cause. Use it as a triage tool, not a diagnostic finish line.


