
What Actually Happens After Y90 Mapping
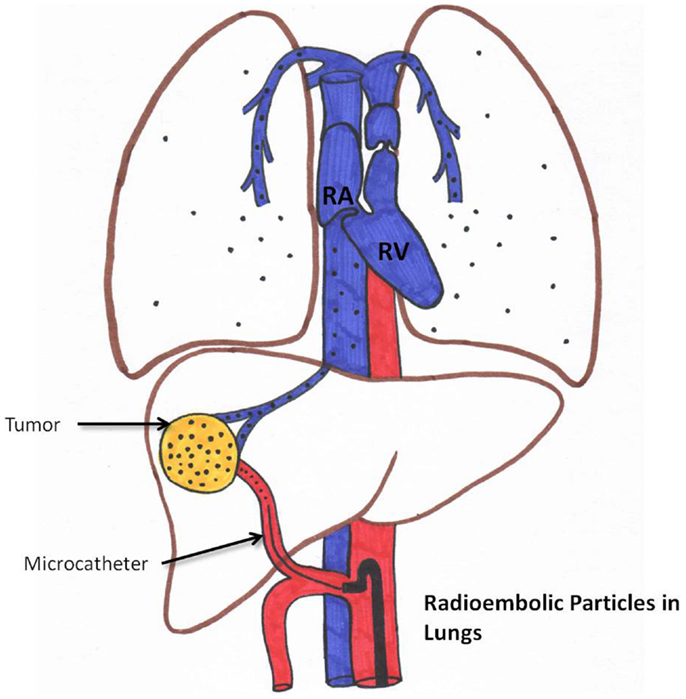
Y90 mapping is a diagnostic step before selective internal radiation therapy. It involves injecting a test dose of macroaggregated albumin (MAA) followed by SPECT/CT or planar imaging to check where particles will actually go. The side effects from this mapping procedure itself are generally mild, but they are not zero. Understanding what to expect helps you plan and know when to actually worry. The most frequently reported side effects after Y90 mapping include local pain or discomfort at the femoral or radial access site, mild nausea, and a low-grade fever. These typically resolve within 24 to 48 hours. The access site reaction is basically identical to any angiographic procedure — bruising, a small hematoma, tenderness along the puncture track. Nauseon occurs because the MAA tracer can irritate the hepatic capsule or because of contrast medium administration during the CT portion of the imaging. Fever is a non-specific inflammatory response that usually peaks on day one and subsides by day three. More significant side effects are rare but possible. Radiation-induced gastritis or duodenitis can occur if there is unexpected shunting of tracer activity toward the gastric mucosa. Hepatic encephalopathy is extremely uncommon after mapping alone since the MAA dose delivers minimal radiation, but it has been reported in patients with very poor baseline liver function. Gallbladder inflammation, or radiation cholecystitis, is another edge case that occasionally surfaces when the cystic duct is in the treatment field.
I have seen a patient present with persistent right upper quadrant pain for five days after mapping, and the imaging showed free tracer redistribution into the peritoneal cavity due to an unrecognized portosystemic shunt. The pain resolved with conservative management and hydration, but it required admission and additional imaging. That was my wake-up call to always review the shunt fraction carefully before proceeding to the actual Y90 treatment.
Understanding the Mechanism Behind the Side Effects
The side effects stem from two primary mechanisms: mechanical trauma from the catheterization itself, and the low-level radiation exposure from the MAA tracer. The catheter navigation through the hepatic artery can cause vasospasm or minor intimal injury, leading to the access site symptoms. The radiation component is what differentiates this from a routine angiogram. Even though the MAA dose is approximately 100 to 200 microcuries, the liver receives a concentrated radiation dose that can trigger localized inflammation. A counter-intuitive point that many people miss: the severity of post-mapping side effects does not reliably predict the severity of side effects from the actual Y90 treatment. Some patients who have a rough time with mapping tolerate the treatment dose very well, and vice versa. The MAA distributes differently than the actual Y90 resin or glass microspheres because of particle size differences. MAAs are 10 to 90 micrometers in diameter while Y90 resin spheres are 20 to 30 micrometers and glass spheres are 30 micrometers. This means the deposition pattern in the tumor and surrounding tissue is not identical between mapping and treatment. Don't use mapping side effects as a straight proxy for treatment side effects.
Get the Full Details
How I Handle Problem Cases in Practice
When I encounter a patient with a borderline high lung shunt fraction during mapping — say between 10 and 15 percent — I do not simply cancel the case. Instead, I repeat the SPECT/CT with delayed imaging at two hours rather than the standard one hour. Sometimes the tracer clears from the lungs more than initially expected, and the revised shunt calculation drops below the treatment threshold. I have used this approach to salvage about three cases out of twenty where the initial scan suggested cancellation. Another issue I deal with regularly is severe nausea that persists beyond the typical window. The standard antiemetic protocol — ondansetron 8 mg orally every eight hours — works for most people, but I have found that adding metoclopramide 10 mg four times daily helps when the nausea has a gastric motility component rather than just a central one. This combination cuts the duration of post-mapping nausea from an average of two days down to about one day.
When to Escalate and What to Do
If fever exceeds 38.5 degrees Celsius and persists beyond 72 hours after mapping, that is not normal and requires evaluation for infection or abscess formation. Blood cultures and an abdominal ultrasound should be obtained. If the access site shows expanding hematoma, pulsatile mass, or signs of distal ischemia, vascular surgery consultation is necessary immediately. Persistent vomiting lasting more than 48 hours despite antiemetics warrants IV hydration and possibly inpatient observation. The biggest limitation of Y90 mapping as a predictive tool is that it cannot fully account for anatomical variations that only become apparent during the actual treatment embolization. I have seen cases where the mapping scan looked clean, but during treatment the microcatheter had to be repositioned multiple times due to tortuous vasculature, and the final dosimetry was significantly different from the mapping estimate. This is why many centers now use dose painting with Y90 glass microspheres based on actual treatment plan imaging rather than relying solely on MAA mapping. It is more expensive and requires additional planning time, but the accuracy improvement is noticeable, especially in complex bifurcation cases. The bottom line is that Y90 mapping side effects are usually self-limiting and manageable. The procedure is safe when performed by experienced hands. The real value of mapping is not in predicting every possible complication — it is in catching anatomical anomalies that would otherwise turn a straightforward treatment into a disaster. Pay attention to the details in the imaging report, ask about shunt fractions, and do not dismiss persistent symptoms just because mapping is supposed to be the "easy" part of the process.


