What Zero Therapy Actually Means for Perioral Dermatitis
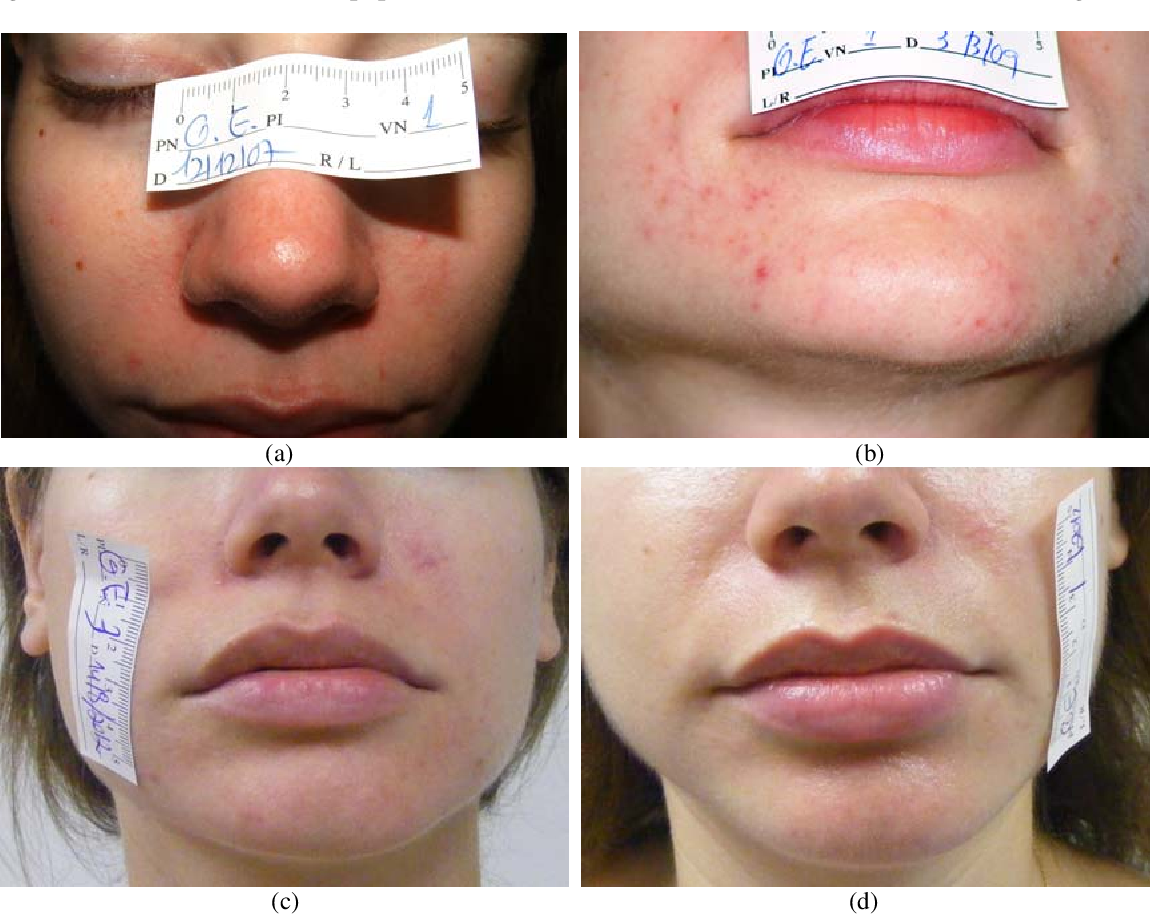
Perioral dermatitis is one of those conditions where doing nothing is genuinely the hardest thing to prescribe. The standard recommendation is Zero Therapy Perioral Dermatitis, which sounds absurd when you first hear it. You have a rash, bumps, redness around the mouth, and the prescription is essentially to strip everything off your face and wait. No moisturizer. No sunscreen. No actives. No steroid creams. Nothing except maybe a tiny amount of plain petrolatum if the skin cracks badly enough to bleed. I watched a patient go through this after years of being prescribed topical metronidazole, pimecrolimus, and a rotating cast of low-potency steroid creams that kept working until they didn't, then flared harder each time. We stopped everything on a Tuesday. By Thursday her face was visibly worse. She looked like she had a sunburn mixed with a contact allergy. She almost quit. That is the expected trajectory. The rebound phase typically lasts between 10 and 21 days depending on how long and how potently she had been using steroids beforehand. After day 21, the inflammation starts downshifting. Full clearance usually lands somewhere between 6 and 12 weeks. Some people get there faster. A minority never do without medication.
Zero Therapy Perioral Dermatitis: The Step-by-Step Process
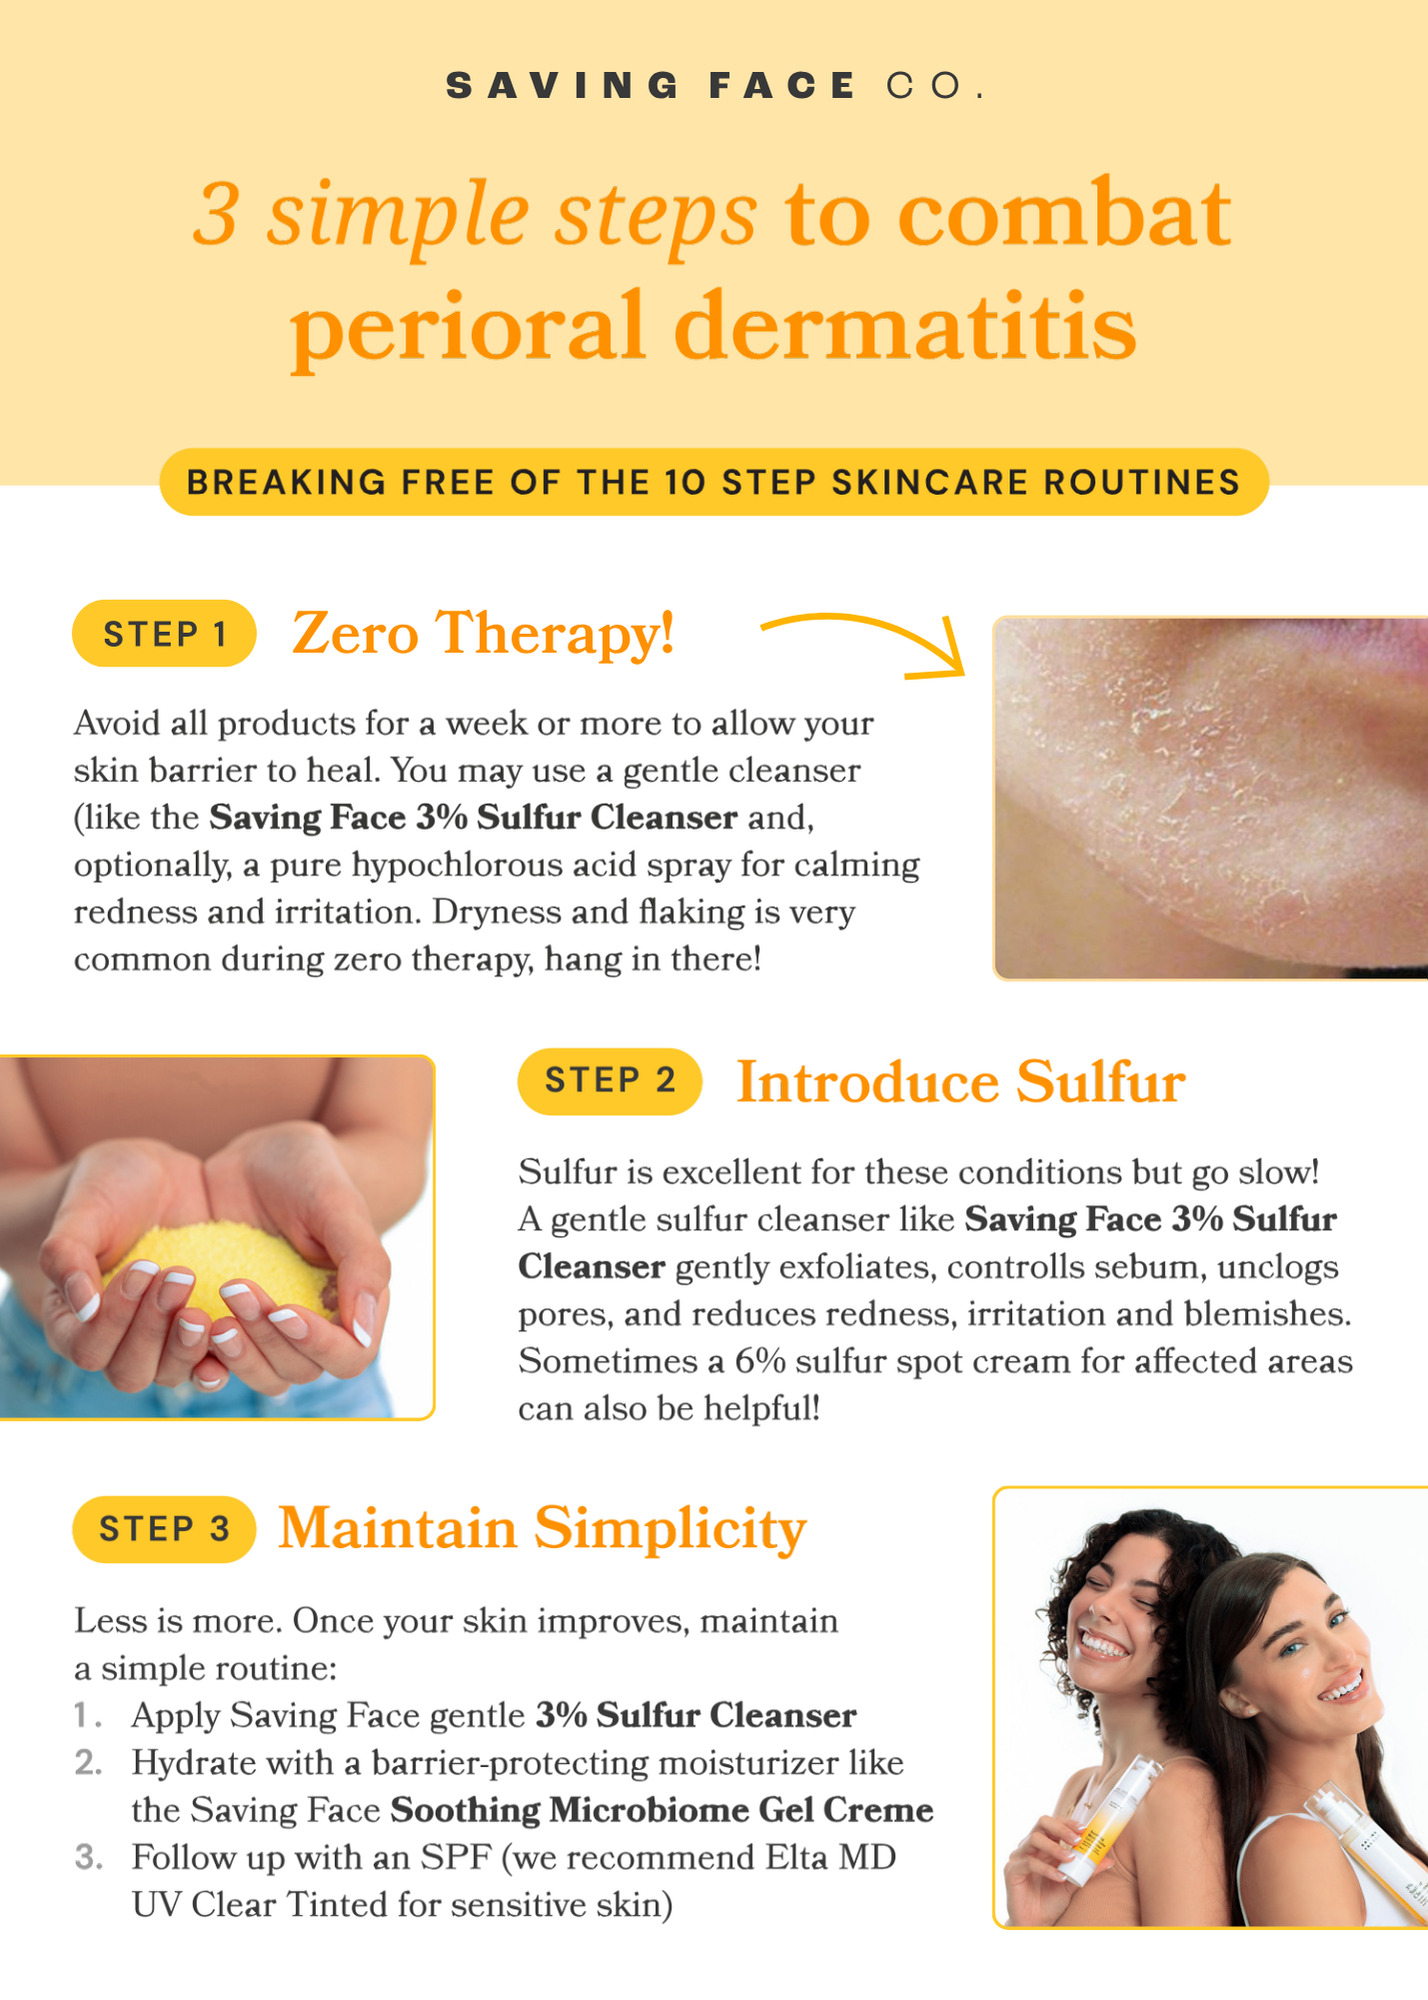
Here is how you actually execute it. You identify every product currently touching the perioral area and stop all of them except one plain emollient if needed. That means cleansers, toners, serums, moisturizers, sunscreens, makeup, lip balms, toothpaste with SLS, mouthwashes with alcohol, anything with fragrance or essential oils, anything with retinoids or acids. If your toothpaste is foaming, switch to a SLS-free version immediately. SLS is a documented trigger for a lot of these cases and nobody mentions it often enough. The application is strictly minimal. A thin layer of plain white petrolatum or a fragrance-free occlusive balm on affected areas twice daily if the skin is broken or uncomfortable. That is it. Nothing else goes on the face. If you must wear sunscreen outdoors, a mineral-only zinc oxide formula applied sparingly and rinsed off gently with water alone is the least irritating option. But even that can prolong the timeline. Most patients who commit fully skip the sunscreen during the initial weeks and accept the photosensitivity risk as a temporary tradeoff. Cleansing is the part people mess up. Do not use any face wash. Water only. Lukewarm, not hot. Pat dry, do not rub. If you cannot tolerate water alone because your skin feels greasy or uncomfortable, a single dilute solution of sodium chloride in distilled water used as a rinse once daily is acceptable and slightly less disruptive than introducing a surfactant. Keep the entire routine under two minutes total.
I had a patient who tried to ease into zero therapy by cutting back gradually instead of stopping cold. She replaced her cleanser with a gentle one, swapped her steroid for hydrocortisone once a day, and kept her moisturizer. She was still flaring at week six. The gradual reduction kept low-grade steroid exposure active in the skin, which perpetuates the dysbiosis and vascular reactivity that maintains perioral dermatitis. Cold turkey is counterintuitive but it is the cleaner path. The worse the rebound, the more likely gradual reduction has failed.
Get the Full Details

Why This Approach Works and Where It Fails
The mechanism behind perioral dermatitis is not fully settled but the leading theory involves disruption of the skin barrier combined with follicular microbiome alteration, often triggered or worsened by topical corticosteroids. Steroids suppress inflammation initially, which is why they look like they help, but they also cause perifollicular atrophy and alter Propionibacterium colonisation in a way that promotes papulopustular eruptions around the mouth. Zero therapy removes the iatrogenic driver and allows the barrier to recalibrate. The rebound worsening you see in the first two weeks is partly withdrawal from the steroid and partly the underlying dysbiosis expressing itself without suppression. Counter-intuitively, the severity of the rebound often predicts a better final outcome. Patients who have a brutal week two with intense redness and spreading bumps tend to clear more completely once past the threshold. Those with a mild or absent rebound sometimes stall out because the underlying trigger was never fully removed or because a second irritant quietly re-enters the routine. I once missed that a patient was still using a steroid-containing combined cream she had not disclosed. She had zero rebound, which sounded great, but she also never cleared. Finding out took three weeks of asking specific questions about every tube in her bathroom. She was on a compound with betamethasone and gentamicin disguised as a "multi-purpose ointment." Zero therapy is not universal. It fails in moderate to severe cases where the inflammatory cascade has established enough follicular involvement that spontaneous resolution is unlikely or excessively slow. It also fails when the primary trigger is something external that continues unabated, like a dental fluoridation issue, a habitual lip-licking pattern, or occupational exposure to irritants. In those situations, zero therapy reduces symptoms but the root cause remains active. Patients should understand this before committing. Expectation management matters more than most clinicians admit. Telling someone "just stop everything and wait three months" without explaining the rebound makes adherence collapse by day four.
Practical Details Most Guides Skip
Timing matters. Starting zero therapy right before a major social event or vacation is a mistake. The worst days usually fall between day seven and day fourteen. Plan for that. If you have an important presentation or wedding in three weeks, you are better off with a planned low-dose oral antibiotic course alongside a modified zero therapy approach than attempting full zero therapy cold turkey. Doxycycline 40mg delayed-release or 100mg standard dosed once daily for six to eight weeks is the most common bridge. It is anti-inflammatory at sub-antimicrobial doses and does not carry the rebound risk of topicals. The combination approach gets people through the acute phase while the skin begins recovering its baseline stability. Makeup is another failure point. Concealer on active perioral dermatitis traps heat and friction against compromised skin. If coverage is non-negotiable for work, use a minimal amount of non-comedogenic, fragrance-free product and remove it with water only. No makeup remover. The mechanical act of wiping with a cloth or cotton pad is itself an irritant. Dabbing with a damp cloth is marginally better. Most patients find that by week three the redness is manageable without coverage anyway. Dietary triggers are inconsistent but worth tracking. I keep patients on a brief elimination log for the first month. Common culprits I see are cinnamon-flavoured products, very spicy foods that cause perioral sweating, and high-histamine foods in patients who also have rosacea features. None of these affect everyone. The log is cheap insurance against missing a pattern. I had a case where the breakthrough came only after switching from a mint toothpaste to a plain baking-soda-and-salt paste. The menthol and cinnamal were the hidden triggers. The patient had stopped all topicals but kept brushing the same way. Two weeks later the perifollicular papules stopped producing new crops.
There is no download link for this because it is not a software tool. It is a behavioural protocol. The closest thing to a resource is a printed checklist of every product currently on your vanity, sorted by contact time and ingredient complexity, so you can identify what actually touches the perioral zone versus what stays on the rest of the face. A lot of people are surprised to learn their hand cream, hair conditioner, or facial sunscreen contains the same fragrances and preservatives that exacerbate perioral dermatitis, even though they apply those products well outside the affected area. Transfer happens through touching your face, washing your face, and general proximity. Everything that touches skin near the mouth counts. The bottleneck with zero therapy is adherence during the rebound window. Clinicians underestimate how much anxiety it generates. Patients interpret worsening as failure. They reopen the medicine cabinet. They start a new cream. They cycle back into the steroid dependency loop that created the problem in the first place. Setting a clear timeline upfront, providing a simple symptom tracker, and scheduling a follow-up at week two to reinforce the plan reduces abandonment rates significantly. People who make it past day eighteen have a high probability of meaningful improvement regardless of how bad it looks on day ten. This approach also has a demographic blind spot. It is studied most in adult women. Male patients, postmenopausal patients, and patients with darker skin tones sometimes present with atypical patterns where the diagnosis itself is delayed, and the zero therapy protocol needs adjustment for concomitant conditions like seborrhoeic dermatitis or tinea faciei, which mimic perioral dermatitis but respond to entirely different treatments. A KOH preparation before committing to zero therapy costs fifteen minutes and prevents months of wasted effort if the underlying issue is fungal rather than inflammatory.

Nothing dramatic happens after clearance either. The skin does not become permanently immune. Maintenance requires keeping the perioral zone free of potential triggers, which mostly means avoiding topical steroids on the face entirely and treating any recurrence early before it establishes a cycle. The first recurrence after successful zero therapy is usually milder and resolves faster if caught at the papule stage rather than waiting for plaque formation. A single night of plain petrolatum only, without any other product introduction, is enough to contain most early relapses.