Getting Actually Good at 12 Lead EKG Interpretation
Most people treat EKG practice like it's a memorization contest. It's not. You need pattern recognition, and pattern recognition only comes from doing hundreds of tracings until your brain stops lagging. I spent years watching techs and residents struggle with the same thing over and over, so here's what actually moves the needle. Start with the systematic approach. Don't eyeball it. Go lead by lead in a fixed order: I, II, III, aVR, aVL, aVF, V1 through V6. For each lead, check rhythm, rate, axis, intervals, hypertrophy, and ST-T changes. Write it down if you have to. The act of physically tracking your method forces you to slow down enough to catch things. Rushing this step is the single biggest reason people miss anterior wall MI's in practice tests and real life.
Free 12 Lead Ekg Practice Resources That Actually Work
There are some solid free banks out there. PubMed Central has a growing collection of teaching cases. The AMI Critical Values library from the American Heart Association is useful too. MDCalc has EKG cases scattered through their articles. For serious practice, grab some old patient data from a MIMIC-III or MIMIC-IV dump if you can get access — it's real data, not cartoons, and the tracings come with full clinical context. That context matters more than you'd think. When you're just starting out, do one tracing every day for a month. Not ten on Sunday. One every single day. Your brain needs the spacing effect. A tracing a day for thirty days beats twelve in one sitting any time. You'll start noticing subtle ST depressions in V4-V5 that you'd normally gloss over. That's the whole point. Here's something nobody tells beginners about axis calculation. You don't need to do the exact degree math every time. If lead I is positive and aVF is positive, the axis is normal. That's it. If lead I is negative and aVF is positive, that's right axis deviation. If lead I is positive and aVF is negative, left axis deviation. If both are negative, extreme right axis or a technically abnormal situation that deserves a second look. The formal method with all four quadrants is nice in theory but wastes time during an actual reading. I stopped calculating exact axes years ago and it made my reads faster and more accurate.
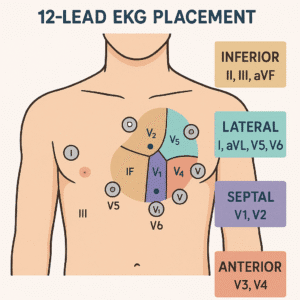
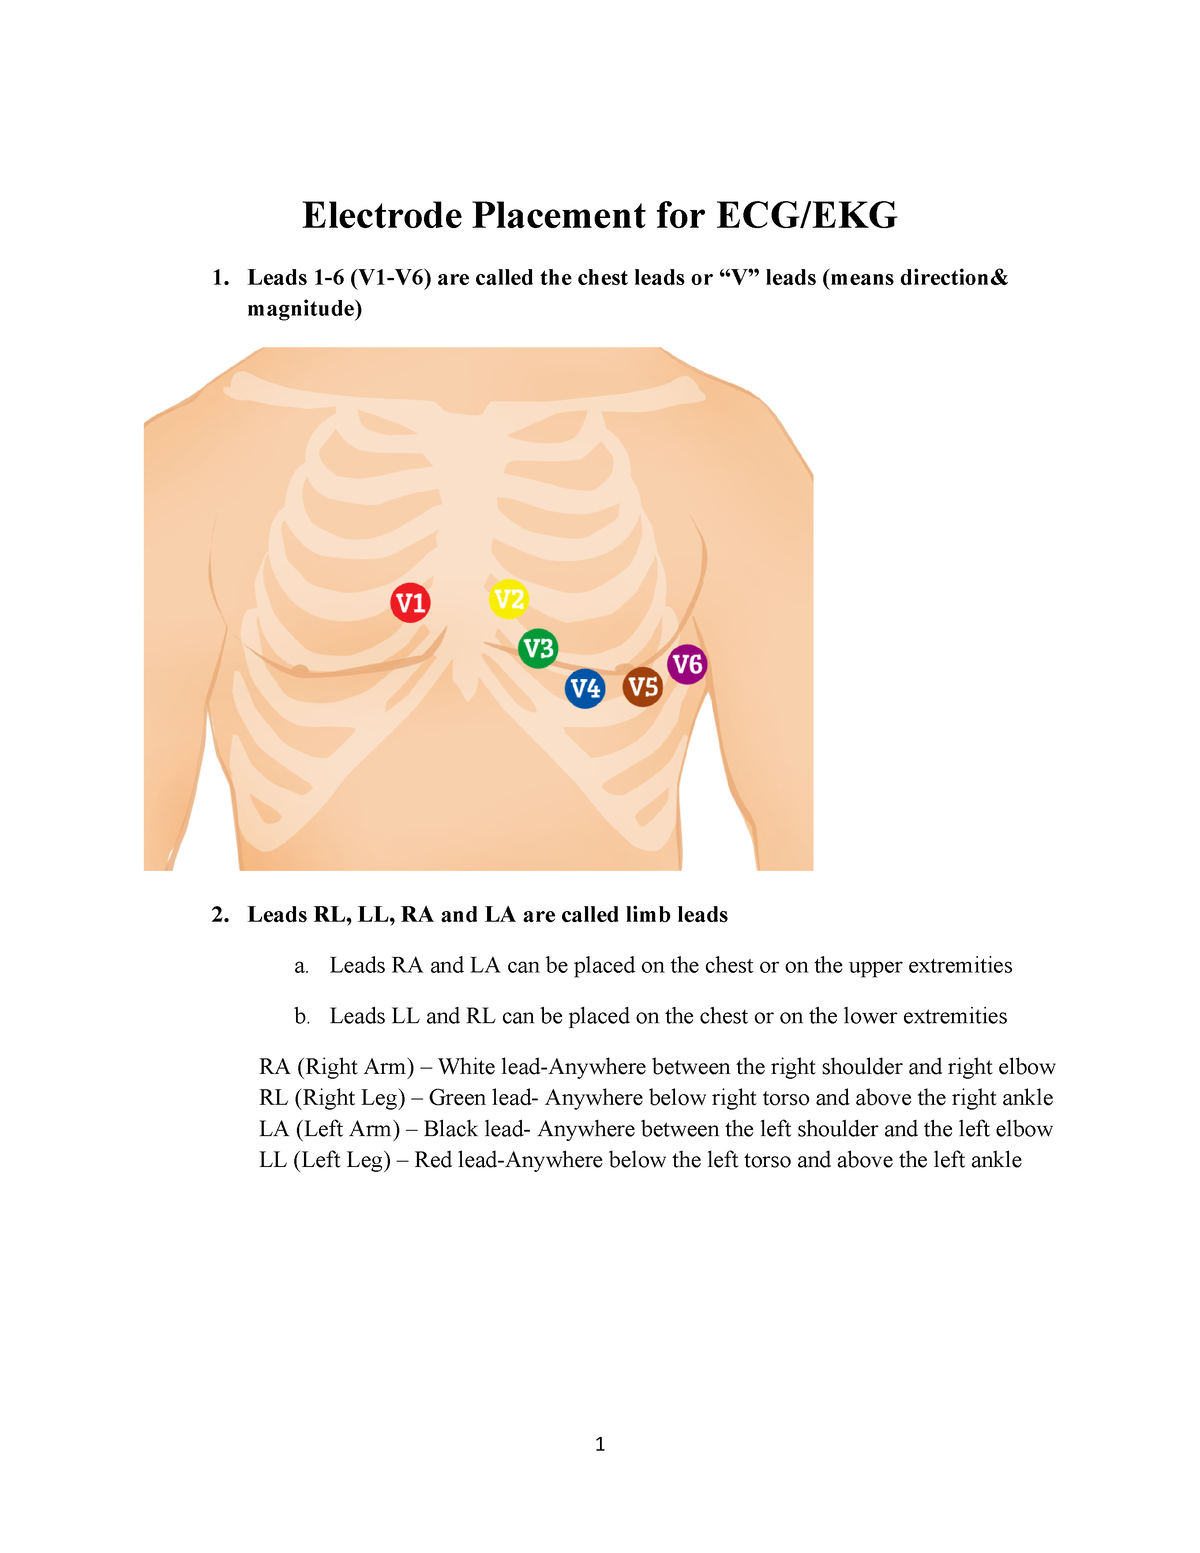
The trick most people miss is understanding what the precordial leads are actually telling you. V1 and V2 aren't just "right ventricle" — they're septal and anterior. V3 and V4 are anterior. V5 and V6 are lateral. When you see poor R-wave progression from V1 to V4, don't just label it and move on. Think about old anterior MI, lead placement error, cardiomyopathy, or just a normal variant in an elderly patient. The differential matters more than the label. I've seen too many people document "poor R-wave progression" without actually considering whether the patient had a prior MI or whether the tech put the leads one intercostal space too high. Speaking of lead placement, here's a concrete problem I ran into recently that illustrates why technique matters. A patient came in with inferior ST elevations in leads II, III, and aVF. Everything looked like an inferior MI. The treating team was already talking about cath lab activation. I rechecked the limb leads and noticed aVR was upside down relative to the others — not literally, but the waveform morphology was flipped compared to what I expected. The arm leads were switched. Left and right arm electrodes had been placed on the wrong limbs. When I mentally corrected for that, the "inferior" elevations disappeared. It was actually posterior involvement with reciprocal changes. Getting the lead placement right before you interpret the tracing saved that patient from a unnecessary workup and got them on the actual treatment path faster. This happens way more often than you'd expect. Limb lead reversal accounts for roughly 1 in 500 EKGs in some studies. Checking aVR first — it should be negative in sinus rhythm — catches most of these immediately. For hyperacute T waves, which signal early occlusion MI before ST segments even shift much, don't wait for the classic evolution. If a T wave looks absurdly tall and broad for the lead it's in, especially with a concordant QRS, treat it as a STEMI equivalent until proven otherwise. The window for intervention is measured in minutes, not hours. A 3mm T wave in V3 that looks symmetric and gigantic is worth a 12-lead repeat and a cardiology consult before you move on to the next case.
Get the Full Details

One more thing about practice methodology. Mix easy cases with hard ones. If you only ever read normal EKGs, you'll feel confident and you'll be completely wrong when something abnormal appears. A balanced practice set should be roughly 60 percent normal or borderline, 30 percent common abnormalities like LBBB, AFib, LVH, and inferior ischemia, and 10 percent rare or tricky cases. That distribution mirrors real clinical practice better than anything else I've seen. Interval measurements matter too. PR interval should be 3 to 5 small boxes. QTc above 450 milliseconds in men or 460 in women is prolonged and needs attention, especially if the patient is on any medications that affect repolarization. Don't rely on the machine's QTc measurement. Automated algorithms get it wrong constantly, particularly when the T wave is notched or there's a U wave present. Measure it yourself. Use Bazett's formula or just estimate — two large boxes is about 400 milliseconds, and you can count small boxes from there. The machine says what it says, but your eyes are still the gold standard. When you're ready to level up past the basics, start comparing sequential tracings from the same patient. A normal EKG from six months ago is worth more than ten random abnormal ones because you can see what change actually means in context. New ST depression in a patient whose baseline was normal yesterday is an emergency. Old stable ST depression in a patient with known coronary disease is just their baseline. Context is everything and it's something practice banks rarely give you.
Use whatever tool feels least friction for daily practice. Phone apps, browser-based banks, printed atlases — the medium doesn't matter as much as the consistency. The people who get good at EKG interpretation aren't the ones with the best resources. They're the ones who looked at one tracing every single day for a year and didn't skip when they were busy. Just keep doing the work.