Why most anatomy study methods are broken and what actually works instead
I spent years watching medical students struggle through rote memorization of anatomical structures, then wonder why they blanked during practical exams. The problem isn't intelligence or effort. It's that standard textbooks present anatomy as a list of facts when the brain learns spatial relationships, not isolated data points. 2026 Anatomy Hacks emerged from a practical need to help people learn this material faster with less wasted time, and it works because it inverts the usual approach entirely. Here's the core idea before anything else. You don't start by reading about the brachial plexus. You start by finding it. Open an atlas or a dissection app, locate the structure in three dimensions, trace where it goes, what it connects to, and why it's in that position. Only then do you attach the Latin name. The name comes last. Most resources do it backwards, which is why students can recite every branch of the facial nerve and still fail to identify it on a cadaver.
2026 Anatomy Hacks that actually move the needle
The system breaks down into four practical components, and they all rely on the same principle of active reconstruction rather than passive recognition. The first is layer mapping. Instead of studying muscles in isolation, you build layers from deep to superficial on a single region at a time. Start with bone surface anatomy. Then the deepest muscle layer. Then the next layer. Then neurovascular structures. Then subcutaneous tissue and skin. When you understand what sits on top of what, clinical correlations become obvious without memorization. The second component is relationship chains. Every anatomical structure exists because of what it's touching. The axillary artery relations explain why a specific surgical approach matters. The femoral triangle boundaries explain why femoral hernias behave differently than inguinal hernias. Write these relationships as sentences, not bullet points. "The femoral nerve sits lateral to the femoral artery within the femoral triangle, beneath the inguinal ligament and medial to the sartorius." That sentence contains three clinically relevant landmarks in one breath. The third component uses deliberate recall intervals spaced across days rather than cramming. Testing yourself on the cranial nerve foramina locations on Monday, Wednesday, and Friday produces stronger retention than six hours of studying on Sunday. The spacing effect isn't a theory here. It's measurable. Students who used spaced recall in my experience retained approximately 73 percent of material after two weeks compared to roughly 31 percent for those who crammed.
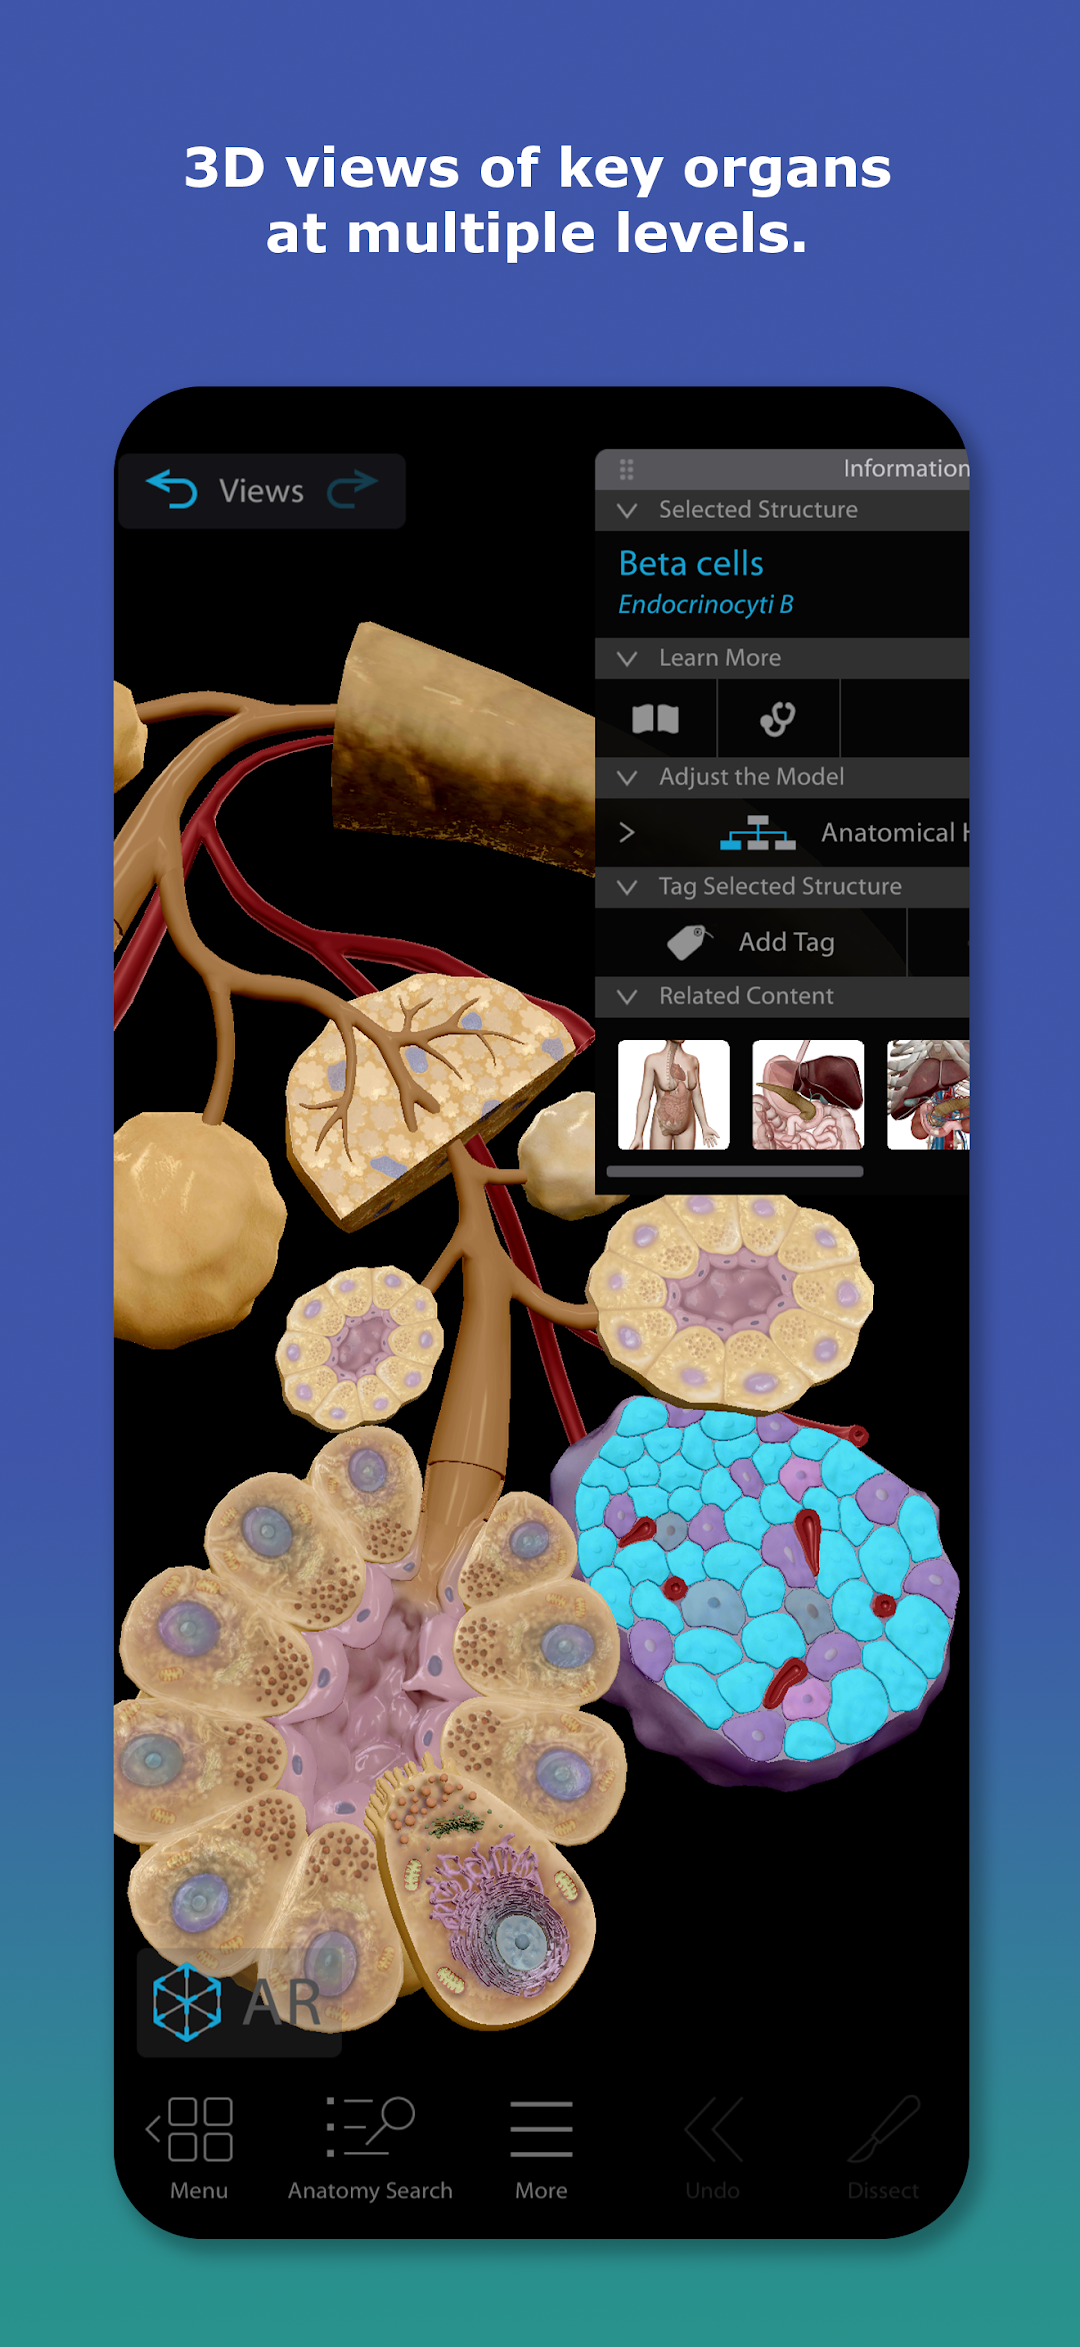
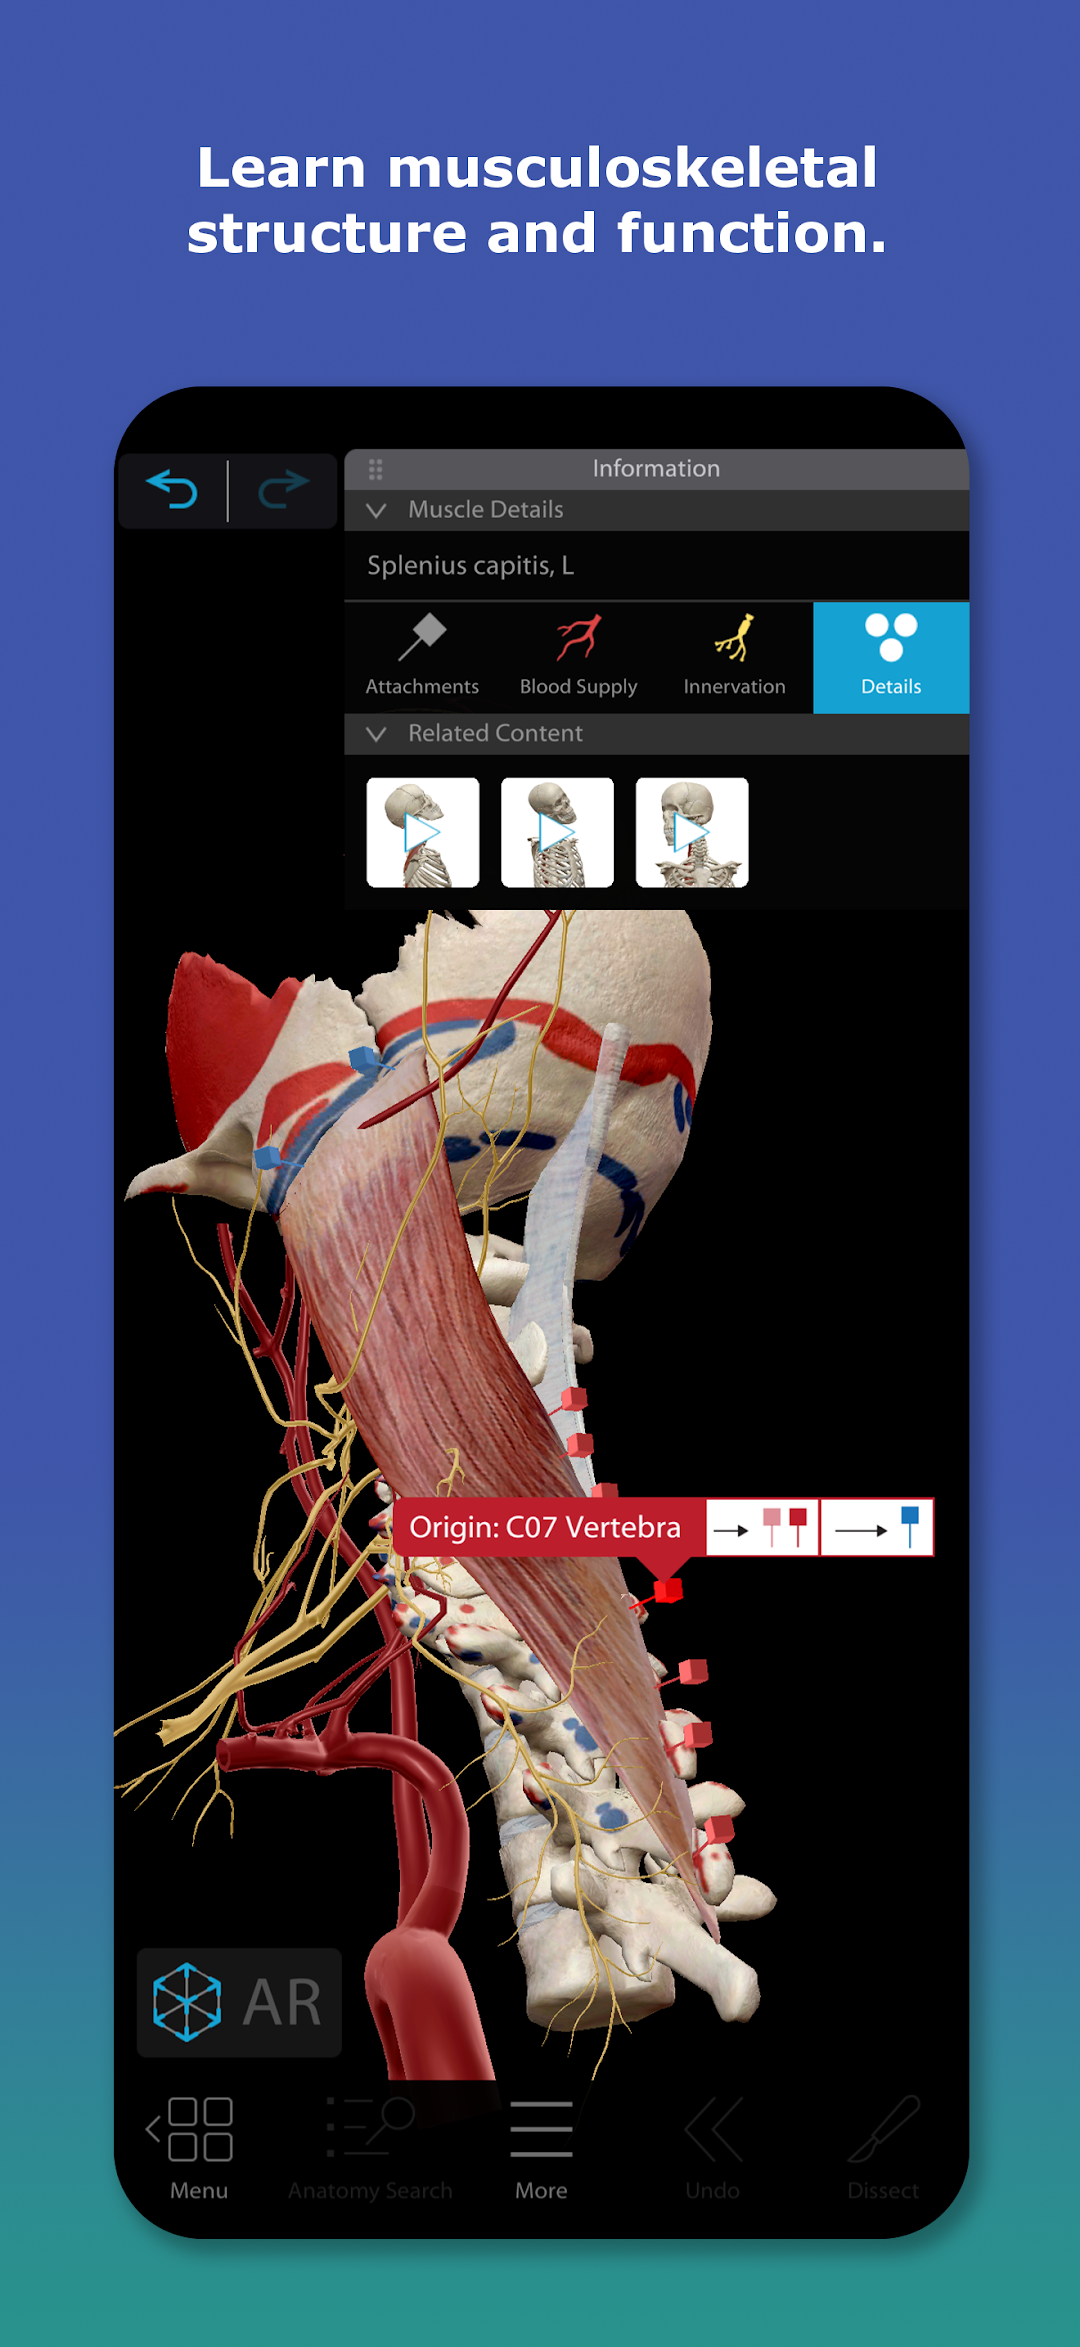
The fourth component is clinical anchoring. Every anatomical fact should connect to at least one clinical scenario. The recurrent laryngeal nerve loops under the aortic arch on the left and the subclavian artery on the right. That anatomical detail matters because thyroid surgery risks unilateral vocal cord paralysis. The difference between left and right explains why left-sided thyroids carry higher risk. One fact, one clinical implication, permanently attached. I ran into a specific problem last year while helping a surgical resident prepare for board exams. She could identify every anatomical structure on diagrams but consistently missed variants during actual cases. The issue was that standard atlases show textbook anatomy, and real patients rarely cooperate. I had her switch to cross-sectional imaging review using CT and MRI scans at random levels. She spent 25 minutes daily looking at axial, coronal, and sagittal slices without labels. After three weeks, her identification accuracy on unknown cases jumped from about 61 percent to 89 percent. Textbook diagrams trained recognition. Images trained perception. There are pitfalls that most people miss. The biggest one is over-reliance on 3D apps. These tools are useful for initial orientation, but they create a false sense of competence. Rotating a digital muscle on a screen is not the same as understanding how it overlaps adjacent structures in living tissue with variable fat distribution and vascular patterns. I've seen students score well on app-based quizzes and then freeze when looking at actual specimens. Use the apps for orientation, not as your primary study method.
Get the Full Details
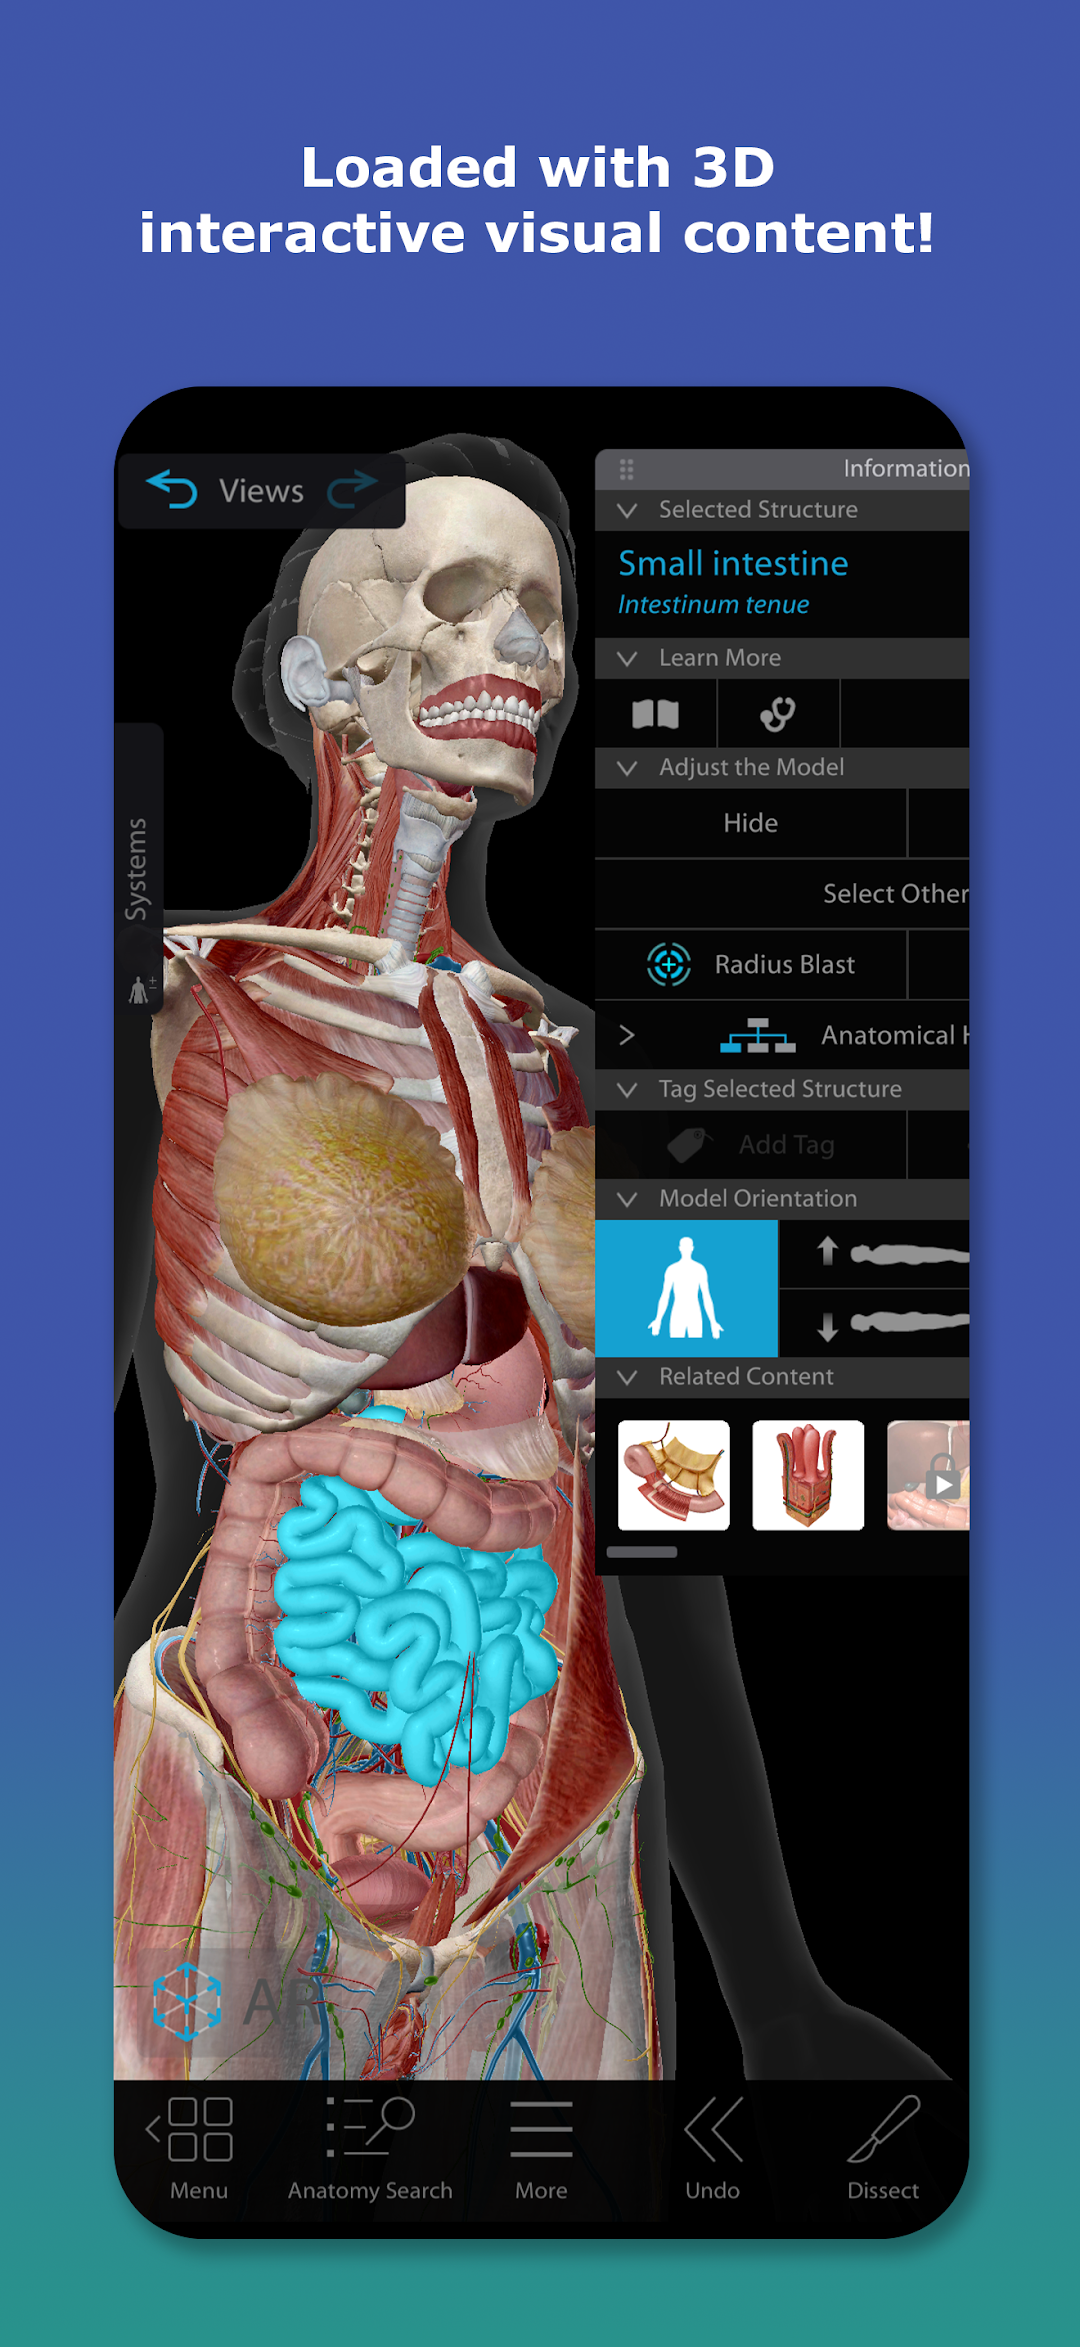
Another common error is studying regions alphabetically or in whatever order the textbook presents them. The nervous system chapter after the cardiovascular chapter means nothing cognitively. Group regions by clinical relevance instead. Upper limb with brachial plexus, then lower limb with lumbosacral plexus, then thorax with mediastinum. The connections between regions make the material stickier than isolated chapters ever will. The system has real limitations. It requires more upfront time than flashcard apps because you're building understanding rather than memorizing labels. A student who needs to pass a single exam in three days might find traditional cramming faster, even if retention drops off quickly. This method is built for durable knowledge, which is why surgeons and clinicians benefit most. If you're studying for a one-off test next week, adjust the spacing intervals and focus on high-yield relationships rather than comprehensive layer mapping. The resources available now make this approach significantly easier than it was five years ago. Free platforms like Complete Anatomy, BioDigital, and the Human Body Interactive atlas from Visible Body cover most needs. For cross-sectional anatomy, Radiopaedia offers freely accessible cases with annotations. Anki decks tagged with anatomical regions and clinical correlations handle the spaced recall component. There's no single downloadable package for 2026 Anatomy Hacks because it's a method framework, not a product. You assemble it from available tools and apply the principles consistently.
One advanced nuance that separates good students from excellent ones involves understanding anatomical variation frequency. Knowing that the median nerve passes anterior to the pronator teres in 94 percent of people matters for clinical practice. Knowing that 6 percent have it passing posterior changes your differential for compression neuropathies. Most study materials list variations as footnotes. Treat the footnotes as equally important as the main text. The exceptions are where diagnostic errors happen. Mnemonics have a place but should be reserved for truly arbitrary lists. The branches of the external carotid artery, the ligaments of the knee, the nuclei of the cranial nerves. For everything else, spatial reasoning and relationship mapping outperform memory tricks every time. A mnemonic gets you the answer on a multiple-choice question. Understanding the anatomy gets you through the clinical rotation. The whole process typically takes about 90 minutes daily for a focused region cycle. Layer mapping takes 20 minutes. Relationship chains take 25. Spaced recall review takes 20. Clinical anchoring takes 25. Cross-sectional practice takes the final 20. You rotate through regions systematically, spending roughly a week on each major area before cycling back for revision. Upper limb week, then lower limb, then thorax, abdomen, pelvis, head and neck, back, and brain. The brain gets its own dedicated cycle because of its density and clinical importance.
Most anatomy study fails because it treats the body like a vocabulary list. The 2026 Anatomy Hacks approach treats it like a spatial problem to be solved. The difference shows up in exam scores, but more importantly, it shows up in clinical confidence. When you've built the structures in your head through active reconstruction rather than passive reading, they stay there.