When a patient mentions they use alternative medicine, most clinicians wing it
I used to either ignore the comment or launch into a gentle debunking that went nowhere. That changed when I saw what actually happens if you get it right. Here is the thing nobody tells you in med school: A Patient Tells You They Practice Alternative Medicine is not a red flag that means you need to have a full worldview conversation. It is a clinical data point, and treating it like one saves you fifteen minutes and probably keeps the patient honest. The encounter follows a simple structure. You hear it. You ask two questions and write down three things. You decide whether there is an interaction risk. If there is, you address it directly. If not, you note it and move on. The first question is always specific: what exactly are they taking or doing, and at what dose? Not "herbal supplements" as a category. Ginkgo, not "memory herbs." Ashwagandha at three hundred milligrams, not "adaptogens." The second question is the timing: are they doing this alongside prescribed treatment, or did they stop something because of it? That second one is the one that catches people off guard in practice, because it flips the script from harmless hobby to potential nonadherence.
What you write down matters more than what you say in the moment. I keep a running list in the problem list: supplements, acupuncture, chiropractic, fasting protocols, anything outside the standard pharmacopeia. The EHR has a dedicated section for this in most systems. Use it. When the next prescriber pulls the chart, they need to see it, not guess at it. The interaction check is where most people fumble. St. John's wort induces CYP3A4 and CYP2C19, which means SSRIs, warfarin, and oral contraceptives all get metabolized faster. Garlic at supplemental doses affects platelet aggregation, which matters if the patient is on antiplatelet therapy. Grapefruit juice is not a supplement but patients forget to mention it because they think of it as food. These are not edge cases. They happen weekly in my clinic. One time I had a patient on dabigatran who also took ginseng for "energy." He was polite, compliant otherwise, and genuinely confused when I asked about it. The interaction literature is mixed on ginseng and anticoagulants, but I flagged it anyway and switched him to apixaban with a clearer supplement discussion. He stayed on it for eight months without a bleeding event. The point is not that every supplement is dangerous. The point is that you need to know what is in play before something goes wrong.
When you find an actual interaction risk, the workaround is straightforward: document it, discuss it, and offer a concrete alternative rather than just saying stop. "Stop taking that" without an alternative is advice most patients ignore within a week. "Here is a safer option and here is why" lands differently. If the patient is using something that has no proven benefit but no known harm either, the most honest thing you can say is "we do not have good evidence for that, and here is what we do have evidence for." That is not dismissive. It is accurate. The pitfalls are real and mostly come from one direction: either you overreact or you underreact. Overreacting means turning a benign multivitamin into a crisis conversation and wasting clinic time. Underreacting means missing the St. John's wort until the patient presents with breakthrough depression or a subtherapeutic warfarin effect. The middle ground is the two-question screen and the chart note. If both answers come back clean, you are done. You do not need to explore the patient's spiritual framework or have a philosophical debate about evidence-based medicine. There is also the communication trap where patients hesitate to tell you because they expect you to judge them. I stopped leading with "So tell me about any alternative remedies" and started asking "What do you take for sleep or anxiety?" instead. It gets different answers, and the answers tend to be more complete. Patients assume you already know about their green tea and will not mention it. They do not assume you know about the kava they bought online.
Get the Full Details

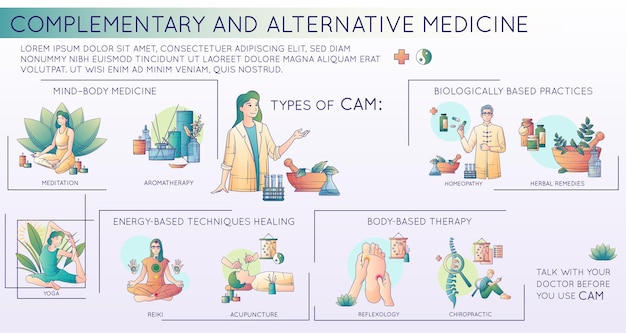
Acupuncture is another category where the risk is low but the documentation is still worth doing. If a patient is getting needling for chronic pain, you want to know who is doing it and whether they are coordinating with your team. There are case reports of pneumothorax from acupuncture, and while the incidence is low, you should not be the first person to hear about it when the patient shows up in the ER. Same with chiropractic neck manipulation and vertebral artery dissection. These are rare, but they are the exceptions that ruin years of good practice if you miss them entirely. The hardest cases involve patients who have stopped prescribed medication because of alternative therapy. That is not a supplement question anymore. That is an adherence question, and it requires a different conversation entirely. You do not need to be confrontational. You need to understand why they made the switch and whether there is a bridge you can offer. Sometimes the bridge is adjusting the prescription to reduce side effects. Sometimes it is simply listening long enough that the patient feels heard and goes back to taking the medication. Both outcomes are valid. Neither comes from a lecture. If you want a quick reference, the major interactions are manageable with a focused checklist. CYP3A4 inducers include St. John's wort, rifampin, and carbamazepine. CYP3A4 inhibitors include grapefruit, azole antifungals, and macrolide antibiotics. Antiplatelet effects come from garlic, ginkgo, ginseng, and fish oil at high doses. Renal toxicity is a risk with aristolochic acid–containing herbs, which still appear in some over-the-counter products. Knowing these four buckets covers roughly ninety percent of what you will encounter in a general practice setting.
I keep a printed card at my desk with this list. It takes five seconds to flip through it when a new supplement appears. The alternative is digging through Micromedex or Lexicomp, which takes about three minutes and interrupts the flow of the visit. In a busy clinic, three minutes adds up. Five seconds does not. The bottom line is practical, not philosophical. When a patient tells you they practice alternative medicine, you screen, you document, you check for interactions, and you move on. That is it. The patients who need the deeper conversation will signal it. The ones who do not will appreciate that you took it seriously without making it into something it is not.