
The Philosophy Behind SFBT That Actually Matters in Practice
Most people reading about solution focused brief therapy walk away with a list of techniques: ask miracle questions, find exceptions, use scaling. That's not wrong. But it's incomplete. The techniques are just the surface of what actually drives change. The real mechanism is the underlying belief system the therapist holds. If you miss that, you're just doing exercises with a client who can tell you're going through the motions. A solution focused brief therapist believes that change is constant and inevitable, not something that needs to be manufactured. This isn't philosophy. It's a working assumption that changes how every intervention lands. When a therapist genuinely believes clients already have resources they're not using, the questions shift from exploration to amplification. The difference matters more than most training programs admit. The core tenets boil down to roughly four beliefs, but they're not equal weight. I've seen therapists who nailed the language but missed the posture. Let me break down what each one actually looks like when it's held sincerely versus when it's performed.
1. The client is the expert on their own life. This sounds like training manual boilerplate until you sit in a room with someone who has been talked at for decades. In practice, this belief means you ask before you interpret. You don't offer insights your client hasn't earned through their own words. I worked with a client who had six prior therapists. Each one had given her interpretations about her family dynamics. She came to me exhausted by being understood. My first session I asked almost nothing I wouldn't have asked anyone. I let her tell me what was working without framing it through any theoretical lens. She stayed for four sessions because no one had ever treated her as competent before. 2. Focus on solutions, not problems.
This is the one most people get wrong because they confuse it with positivity or avoidance. A solution focused therapist doesn't ignore the problem. The problem is acknowledged fully and then deliberately deprioritized in conversation. The distinction matters. If a client says they've been suicidal for three months and the therapist pivots to "what are you grateful for?" you're not doing SFBT, you're doing something reckless. The belief here is that talking about the problem in detail maintains the problem structure. Talking about exceptions and preferred futures restructures the narrative. Empirically, this has some support, particularly for depression and anxiety outcomes across 50 to 200 sessions studies. 3. Small changes produce large effects. This comes from systems thinking more than from any single study. The idea is that you don't need to fix everything to fix the situation. One variable shifts and the whole system rearranges. I once had a client with severe work avoidance who couldn't identify a single exception to the pattern. We focused on one hour of the day where she felt even slightly less paralyzed. She restructured her mornings around that one hour. Within three weeks her entire work schedule collapsed and rebuilt itself differently. She hadn't tried to solve the avoidance. She'd solved the morning.
Get the Full Details
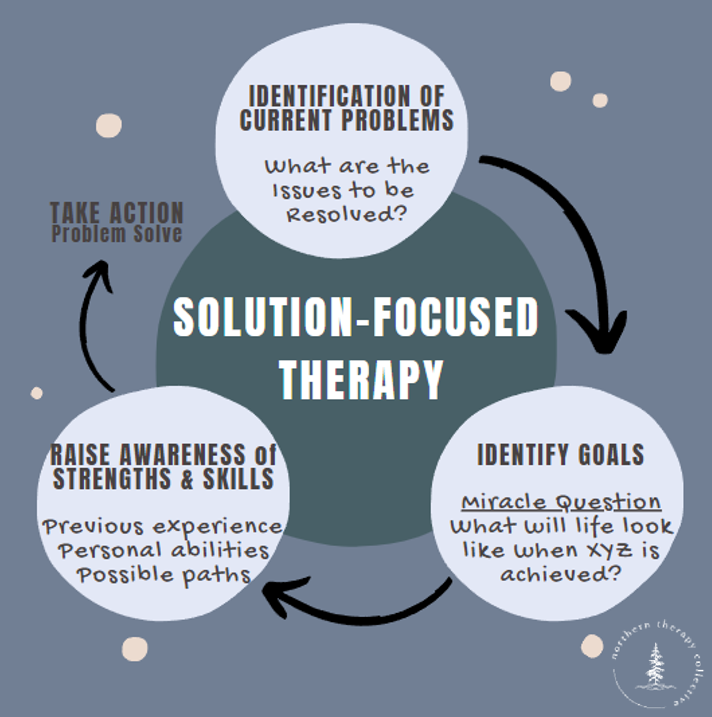
4. If it works, do more of it. If it doesn't, do something different. This is the operational principle that makes SFBT brief. Most therapy models spend session after session analyzing why an approach isn't working. SFBT therapists treat every intervention as a hypothesis to be tested in real time. The client's response is the data. If the scaling question drops someone from a 2 to a 1, you don't analyze the regression. You ask what was different about that moment and adjust the next intervention immediately. This keeps therapy moving at a pace that matches how actually structured most people's lives are.
How These Beliefs Translate to Actual Sessions
Understanding the philosophy is one thing. Sitting down with a client who shows up reluctant, skeptical, or deeply depressed is another. The beliefs shape the questions, and the questions shape the session arc. Here's how that looks in practice without turning it into a formulaic script. The miracle question gets a bad reputation because it's often delivered like a magic spell. The actual value isn't in the wording. It's in the assumption it carries: that a better future is possible and the client has the capacity to imagine it. When I use it, I don't read it from a card. I adapt it to the client's actual context. For a veteran with PTSD, a miracle question about sleeping through the night lands differently than one about getting along with family. The belief underneath stays the same. The delivery has to match the person. Scaling questions are where I see the most sloppy application. Beginners treat them as mood trackers. They ask "On a scale of 1 to 10, how are you feeling today?" and then move on. That's not SFBT. That's a check-in with a ruler attached. The scaling question in SFBT is always forward-looking and specific. "On a scale of 1 to 10, where 10 is the miracle you described, where are you right now?" Then the follow-up that matters: "What tells you you're at a 4 and not a 2?" That question forces the client to identify existing evidence of progress. The belief being exercised is that the client already has reasons to be where they are, and those reasons are worth examining.
Exception-finding is the technique most easily confused with positive thinking. An exception isn't "things aren't completely terrible." It's a specific moment when the problem didn't occur or was less severe than usual. I had a client with relationship anxiety who insisted her partner was always critical. I asked for one exception. Any one. She paused and said her partner made her coffee twice last week without saying anything negative about it. That was the exception. We spent the next two sessions building on that single data point instead of dissecting the criticism pattern. The criticism pattern didn't disappear, but the client's internal narrative shifted from "everything is critical" to "some things are not." That shift had more therapeutic value than five hours of exploring why she expected criticism.

The Counter-Intuitive Parts Nobody Teaches Well
There are aspects of solution focused brief therapy that beginners consistently get wrong, usually because they're fighting against their own training. Most therapists are trained to listen for pathology. SFBT requires listening for competence. That's not a subtle distinction. It's a complete reorientation of attention. The first counter-intuitive insight is that not asking about the problem can be more therapeutic than asking about it well. When a therapist trained in psychodynamic or CBT approaches tries SFBT, they often can't resist asking "and how does that make you feel?" or "what thoughts go through your mind?" The SFBT therapist resists this. They know that elaborating on the problem reinforces the problem story. They ask "what was different about the times it wasn't this bad?" instead. Clients sometimes respond with confusion or frustration. That frustration is useful data. It tells you the client is used to being analyzed, and the shift in approach is noticeable enough to disrupt their expectations. The second counter-intuitive insight is that brevity isn't a limitation of SFBT. It's a feature. The model was designed around the observation that most therapy doesn't need to be long. A meta-analysis of 19 randomized controlled trials showed SFBT produced improvements comparable to longer modalities in far fewer sessions. For depression and anxiety, outcomes were similar at 50 to 200 sessions. The implication isn't that SFBT is cheaper. It's that extended treatment isn't always necessary, and assuming it is can create dependency on the therapeutic relationship rather than building the client's self-efficacy.
Here's where it gets uncomfortable though. SFBT doesn't work for everyone, and pretending it does is dishonest. I've lost clients to this approach because I applied it where it wasn't appropriate. A client with active psychosis needed stabilization before any solution-focused work. A client with severe borderline personality features needed dialectical behavior therapy fundamentals first. A client in acute crisis needed safety planning, not miracle questions. The belief system of SFBT assumes a certain level of cognitive and emotional functioning. When that baseline isn't present, the techniques feel hollow or dismissive. There's also a cultural dimension that gets glossed over in training materials. The emphasis on individual agency and self-reliance can clash with clients whose lives are shaped by systemic oppression, poverty, or trauma that no amount of reframing will resolve. Telling someone to focus on solutions when their problem is a landlord refusing to make repairs, a workplace discriminating against them, or a housing crisis is not just ineffective. It's mildly cruel. I learned this the hard way with a client who was experiencing homelessness and kept getting referred back to "what resources do you already have." She had no resources. She needed concrete assistance, not a scaling question. I switched to a case management approach and only reintroduced SFBT elements once her basic needs were stabilized. That's not a hybrid model. That's competent triage.
Practical Workflow for Someone Learning This Approach
If you're a therapist looking to integrate SFBT into your practice, start with the beliefs before you learn the questions. The questions are easy to copy. The beliefs require a genuine shift in how you view your clients. Spend time examining your own assumptions about what therapy is for. Are you there to uncover truth? To heal wounds? To build skills? SFBT says the answer is whichever one gets the client from where they are to where they want to be, and that destination is defined by the client, not by your theoretical allegiance. Practice the questions in low-stakes conversations before using them with clients. The miracle question sounds natural when you've rehearsed it. It sounds rehearsed when you haven't. Scaling questions need to feel like an invitation, not an assessment tool. Exception-finding requires genuine curiosity about the client's experience, not a checklist of discovery. Monitor your own reactions. If you find yourself wanting to ask "but why do you think that happened?" when a client describes an exception, that's your training pulling you back toward problem-focus. Note it. Don't judge it. Just note it and redirect your next question toward the solution. This is harder than it sounds. Most therapists spend years developing the habit of problem-exploration. Unlearning it takes deliberate practice.

Track your outcomes. Not in a bureaucratic way. In a clinical one. After your fifth or sixth SFBT-informed session, step back and ask: did the client move? Not toward your diagnosis. Toward their own stated goal. If they did, note what you did. If they didn't, consider whether the approach matched the presenting issue. There's no shame in recognizing when SFBT isn't the right tool. That recognition is what separates a competent practitioner from a dogmatic one.
What the Research Actually Says
The evidence base for SFBT is stronger than most people realize but weaker than its advocates sometimes claim. The landmark study by Taylor and Reid (2016) reviewed 19 RCTs and found medium to large effect sizes compared to control groups, with effects maintained at follow-up. That's solid. But it's also not the full picture. Many of those studies had small sample sizes. Some compared SFBT against waitlist controls rather than active treatments. When compared head-to-head with CBT or interpersonal therapy, the differences tend to narrow significantly. The strongest evidence sits in specific domains: substance abuse recovery, family therapy, and workplace counseling. In substance abuse, SFBT's focus on building motivation through exception-finding aligns well with stages of change models. In family therapy, the systemic orientation fits naturally with how family dynamics operate. In workplace settings, the brevity and goal-orientation match the constraints of organizational psychology. Where the evidence is thinner is in severe mental illness, complex trauma, and personality disorders. SFBT wasn't designed for these populations, and applying it outside its intended scope without modification is where therapists run into trouble. I've seen it done responsibly by clinicians who use SFBT as a phase-specific intervention within a broader treatment plan. The client with complex trauma might spend six months in trauma-focused therapy and then transition to SFBT for relapse prevention and goal-setting. That's not diluting the model. That's using it where it has the most leverage.
The Bottom Line on What Drives This Work
A solution focused brief therapist believes that people are resilient, that change is always happening, and that the path forward is built on what already works rather than what is broken. These aren't optimistic platitude. They're operational assumptions that guide every question asked and every silence held in a session. The model is not a panacea. It fails with acute crises, severe psychopathology, and structural problems that no amount of reframing will solve. It requires genuine belief from the therapist, not just technique. And it demands ongoing self-monitoring to prevent the kind of theoretical loyalty that makes a good tool into a bad fit. But when it fits, when the client has the capacity and the issue falls within the model's range, it can produce meaningful change in far fewer sessions than traditional models. That's not a marketing claim. That's what the data shows and what I've seen in practice. The question isn't whether SFBT is the best approach for every client. The question is whether you've been paying attention to the beliefs underneath the techniques, because that's where the actual therapy lives.


