Cervical Spine Recovery Isn't as Simple as Stretching Your Neck
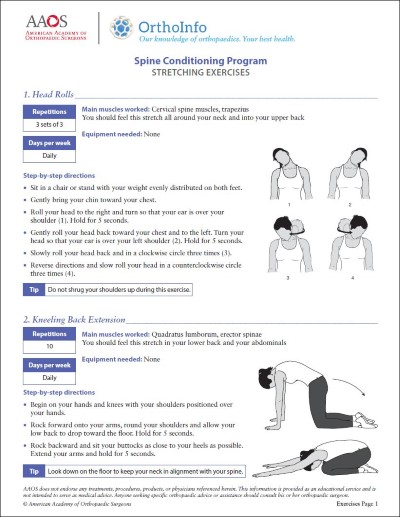
The AAOS doesn't publish a single protocol you can follow blindly. They publish clinical practice guidelines, which is a different thing entirely. When patients show up asking for "AAOS cervical spine exercises," they usually want a laminated worksheet from a post-surgery visit. That worksheet exists, but it covers about three movements and assumes you already know how to brace your core while doing them. I've watched people blow out their progress because they followed a generic YouTube video instead of the actual guideline-backed progression. Here is what the AAOS framework actually looks like when you strip away the brochure language and deal with it in a clinic setting.
Aaos Cervical Spine Exercises
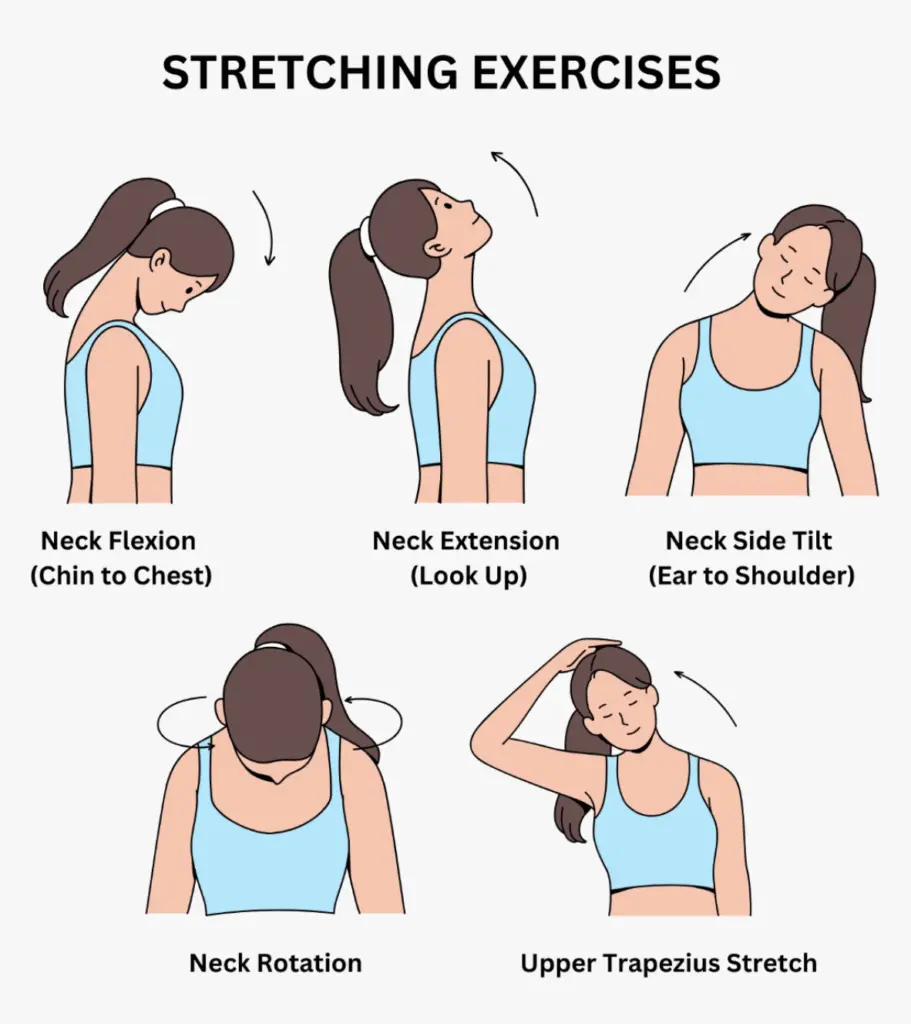
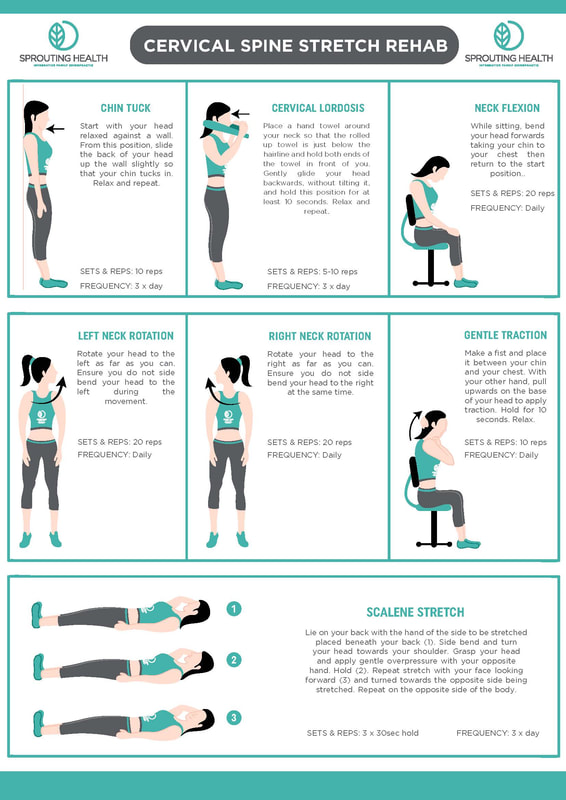
The AAOS clinical practice guidelines for neck pain and cervical radiculopathy emphasize a graded exercise approach, not a static stretch routine. The key distinction matters because most people treat cervical exercises like they're treating a tight hamstring. You don't hold a static stretch on a stiff neck and expect it to unlock. The AAOS stance is that isotonic strengthening of the deep cervical flexors and scapular stabilizers comes before aggressive mobility work. The foundational movement is the deep neck flexor hold, often called the chin tuck. You lie supine, bring your chin down toward your throat without lifting your head off the table, and hold. The AAOS guidelines note this should progress from supine to seated to standing over weeks, not days. A typical progression I've seen across compliant patients runs about six to eight weeks before full weight-bearing neck loading is reintroduced. That timeline shifts dramatically if you have any disc pathology or if imaging shows structural narrowing. Scapular retraction exercises come next. Rowing motions with resistance bands, serratus punches, and prone Y raises. The logic here is mechanical. Your neck muscles are levers attached to your shoulder girdle. If your scapulae drift forward because your upper back is weak, your cervical spine compensates by taking on load it wasn't designed to handle. The AAOS guidelines explicitly tie scapular stabilization to reduced neck pain scores in randomized trials. It's not theory, it's the data.
I ran into a specific problem last year with a patient who had followed a standard AAOS handout after a cervical fusion at C5-C6. She started doing full-range chin tucks and resisted neck extension too aggressively around week three. The hardware was stable, but the adjacent segments at C4 and C7 were inflaming because she was forcing mobility where she needed controlled stability instead. The workaround was straightforward but counterintuitive: I had her stop all neck movement except isometric holds in a neutral position for two full weeks. No flexion, no extension, no rotation. Just pressing her palm against her forehead and holding for ten seconds, repeated twelve times, twice daily. Pain dropped from a seven to a three in nine days. She then rebuilt from there with the same isometric framework, adding range only after four more weeks of pain-free holds. Another common pitfall involves the upper trapezius. People tense their shoulders during neck exercises and essentially work their trap muscles into a permanent state of contraction while expecting relief. The AAOS guidelines address this indirectly through emphasis on scapular depression during all cervical work. You keep your shoulders down and back the entire time. If your traps are bulging near your ears during a chin tuck, you're doing it wrong and you're making the problem worse, not better. There are limitations to the AAOS exercise framework that nobody likes to talk about. It does not work well for patients with significant foraminal stenosis or myelopathy. If your spinal canal is narrowed enough to compress the cord, aggressive cervical extension and rotation can push symptomatic tissue further into already tight spaces. In those cases, the AAOS guidelines themselves recommend modified ranges of motion and closer supervision, often deferring to physical therapy rather than a home protocol. Flexion-biased exercises tend to be safer in those scenarios because opening the posterior elements gives the nerve roots more room, but that requires imaging confirmation first.
Get the Full Details

The AAOS also does not prescribe specific rep counts or set volumes in their patient-facing materials. That gap is intentional. Their guidelines leave dosing to the treating clinician based on individual tolerance, comorbidities, and surgical status. When I see patients trying to follow online rep schemes derived from the AAOS, they either undershoot and see no improvement or overshoot and flare up. The guidelines are a framework, not a workout plan. That distinction gets lost constantly in patient forums and recovery groups. If you're looking for the actual documents, the AAOS publishes their clinical practice guidelines on their website under the orthopaedic topics section. The full guidelines for non-radicular and radicular neck pain are available as downloadable PDFs. Patient education handouts are separate from the clinical guidelines and tend to be simpler, sometimes oversimplified to the point of being misleading for complex cases. The handouts alone won't get you through a recovery. They're meant to supplement supervised care. The exercises themselves are low-cost and require minimal equipment. A thin pillow for supine chin tucks, a light resistance band for scapular work, and a wall for standing isometric holds. That's it. The bottleneck isn't equipment. It's consistency and knowing when to stop advancing the program because your tissue isn't ready. I've seen people add resistance too early, progress range of motion before pain resolves, and skip the scapular stabilization phase entirely because it felt too easy. The easy movements are the ones that actually move the needle. The harder ones, when done prematurely, just reload the injured structures.