What an Aba Social Skills Assessment Actually Looks Like
The term "Aba Social Skills Assessment" doesn't refer to one specific standardized test. It's a catch-all phrase for a handful of structured observation and interview protocols that BCBAs and RBTs use to evaluate social behavior in clients, usually children, who are receiving applied behavior analysis treatment. The real work happens across a few different tools depending on the clinic, and most practitioners end up mixing pieces together. The most common instruments you'll encounter are the Social Skills Improvement System (SSIS), the VB-MAPP social domains, the Social Responsiveness Scale (SRS-2), and direct behavioral observation checklists built from baseline data. Each one measures different things. The SSIS gives norm-referenced percentile scores from caregiver and teacher ratings. The VB-MAPP breaks social behavior into milestones tied to verbal operants. The SRS-2 is more focused on autistic social communication patterns. Direct observation is what actually tells you what's happening in the room versus what a parent thinks is happening at home.
How to Conduct an Aba Social Skills Assessment
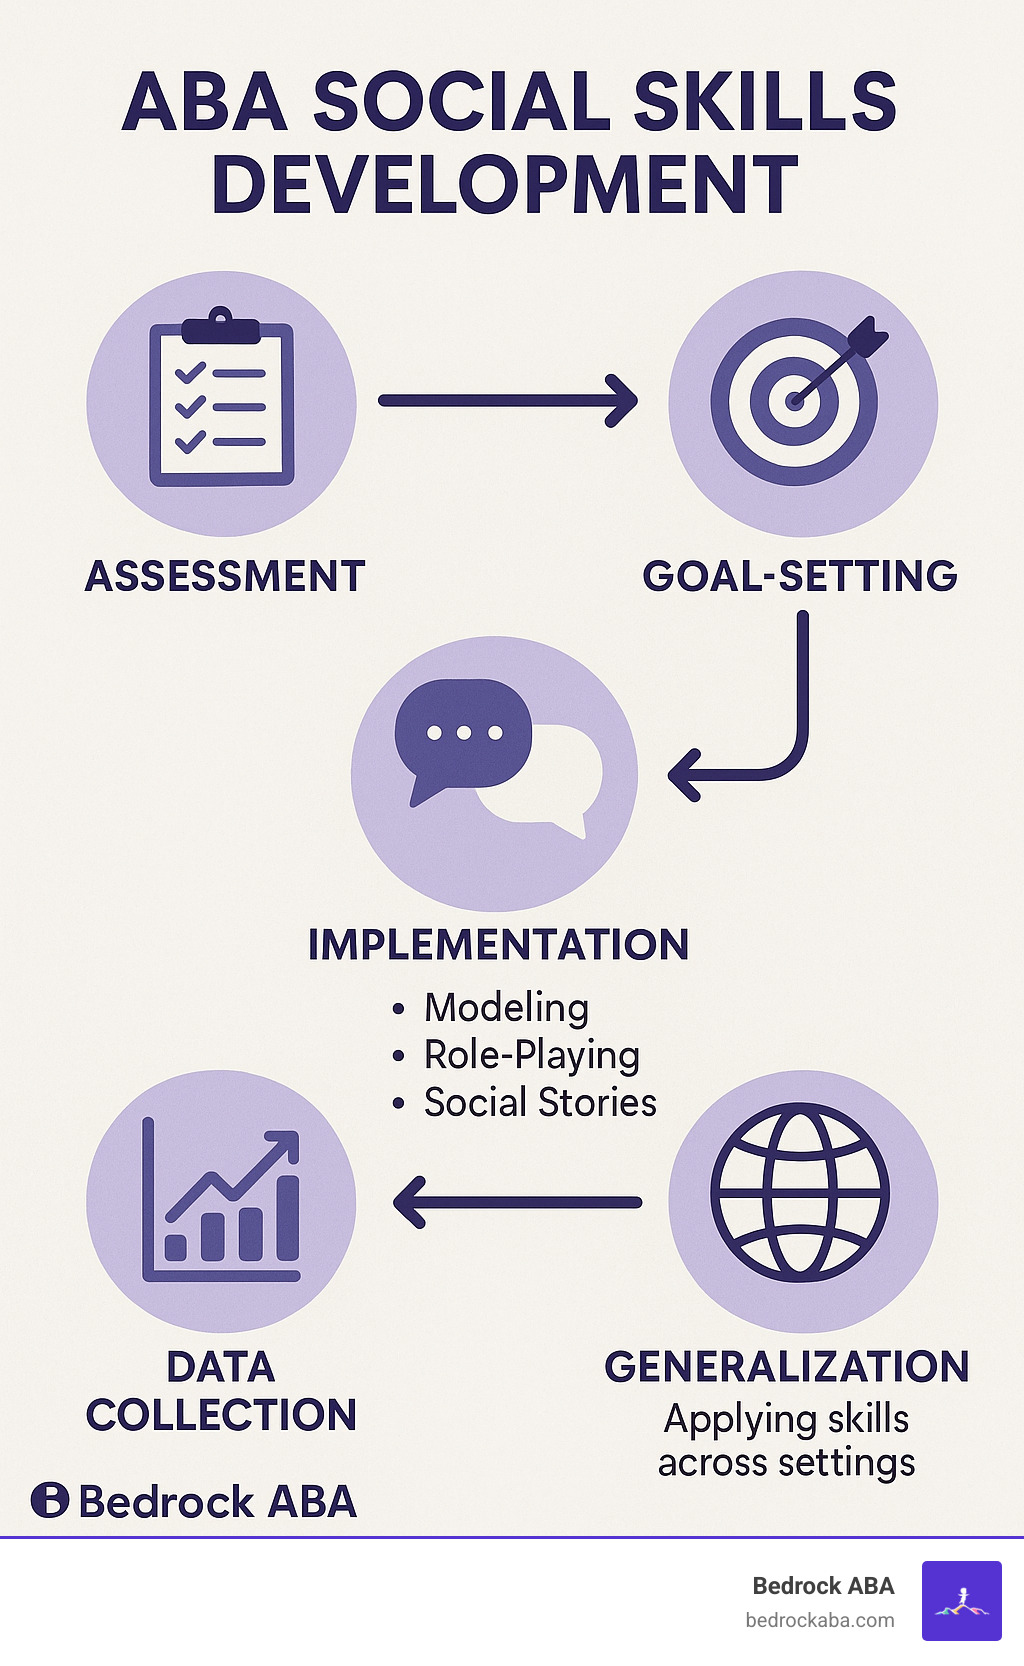
Here is the practical sequence I use, stripped of the textbook version. Step one is gathering existing data. Pull the client's current treatment plan, any prior assessments, and ask the parents and teachers to fill out rating scales before you show up. This takes about 20 minutes of coordination and saves you from reinventing the wheel during observation. If you walk in cold, you're wasting the first session just figuring out what already exists. Step two is direct observation across at least two settings. I do one session in a structured therapy environment and one in a naturalistic setting like a classroom or playgroup. During each session I'm tracking specific social behaviors: joint attention initiations, response to name, turn-taking during play, requesting help appropriately, handling mild frustration without escape behavior, and imitating peer models. I record frequencies and durations, not impressions. Impressions get you sued. Data gets you meaningful treatment changes. Step three is the clinical interview. This is where most people rush. I spend 15 to 20 minutes with caregivers asking targeted questions about social interactions at home, with siblings, at extracurricular activities, and during unstructured time. The pattern of where social breakdowns happen is usually more informative than the total score on any single questionnaire. A kid who can recite social scripts in the clinic but refuses to engage with peers at recess is showing you something specific about generalization, not about overall social ability.
Step four is scoring and synthesis. You compile the rating scale results, your observation notes, and the interview findings into a summary that identifies strengths, deficits, and maintaining variables. The output isn't a letter grade. It's a list of target behaviors with baseline measurements and suggested interventions. If you can't write a measurable objective from the assessment, you didn't assess properly. I once had a client whose SSIS scores came back solidly in the average range across all social domains. Parents and teachers both reported nothing concerning. The direct observation told a completely different story. During unstructured play, the child would approach peers with a loud vocalization, grab toys without asking, and when redirected, would immediately move to the next child and repeat the same pattern. The rating scales were measuring the absence of aggression, not the presence of appropriate social initiation. I flagged this as a generalization deficit masked by norm-referenced scores and recommended a stimulus control protocol paired with incidental teaching during free play. The treatment plan shifted from "social skills group" to specific contingency management in natural environments. That client made more progress in six weeks than they had in eighteen months of generic group therapy.
Get the Full Details

Counter-Intuitive Things Nobody Tells You
One of the most overlooked aspects is that high compliance during structured assessment conditions often correlates with low social competence in unstructured settings. A child who follows every directive and responds perfectly to adult prompts during a clinical observation is demonstrating rule-governed behavior, not necessarily social skill. The real measure is spontaneous, unprompted social initiation. I always build at least one unstructured observation block into my protocol specifically for this reason. It usually reveals something the structured data misses entirely. Another thing: the VB-MAPP social milestones assume a typical developmental trajectory that simply doesn't match many of the kids in ABA practice. A child might have mastered the early milestones but stall completely on the later ones because the later skills require more complex antecedent conditions like peer availability and community access. Scoring strictly by milestone sequence can make a child look less skilled than they actually are. I treat the VB-MAPP social domains as a guide, not a ladder. I look at which skills are present across environments and which are absent, regardless of their assigned milestone number.
Where This Breaks Down
The biggest limitation I deal with is that none of these tools adequately capture neurodivergent social communication styles that aren't autistic or AD H.D.-related. Kids with social pragmatics disorders that don't fit the autism profile often get misclassified. Their scores look fine on standard instruments but they still struggle in real social settings because the instruments aren't calibrated for that population. In those cases, I supplement with the Pragmatic Language subscale from the Clinical Evaluation of Language Fundamentals and rely more heavily on direct naturalistic observation than on any questionnaire. Another hard limit is generalization. An assessment tells you what a child can do under specific conditions at a specific time. It does not tell you whether those skills will transfer to new people, new places, or new times of day. That has to be measured separately through follow-up probes across environments, usually at 30-day intervals after intervention begins. Skipping the follow-up is the same as not doing the assessment at all, because you never actually know if the treatment worked outside the room where it was taught. If you're looking for a downloadable template or scoring sheet for a basic ABA-aligned social skills assessment, the Association for Behavior Analysis International website has free forms and the University of Florida’s VB-MAPP resources include the social domain checklists. Those are the most practical starting points before you build your own observation protocol.