What PROM Actually Looks Like In Practice
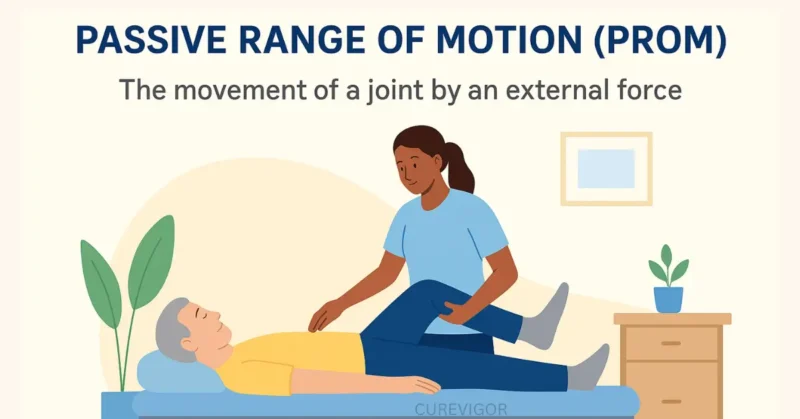
Passive Range Of Motion is when someone or something moves your joint for you. You don't fire a single muscle in that limb. A therapist, a machine, or even your other hand does all the work. That is the textbook version. The real version is messier than that because most people confuse passive motion with stretching, and those are two different things with different purposes. I used to run rehab programs for athletes coming off shoulder surgery. One of the first mistakes we saw was patients pushing too hard into passive motion and thinking they were being productive. They were just inflaming the joint capsule. We had to literally take the goniometer out of their hands and do the measurements ourselves because they couldn't tell the difference between a hard stop and a damaging stretch.
How To Get It Right With Passive Range Of Motion
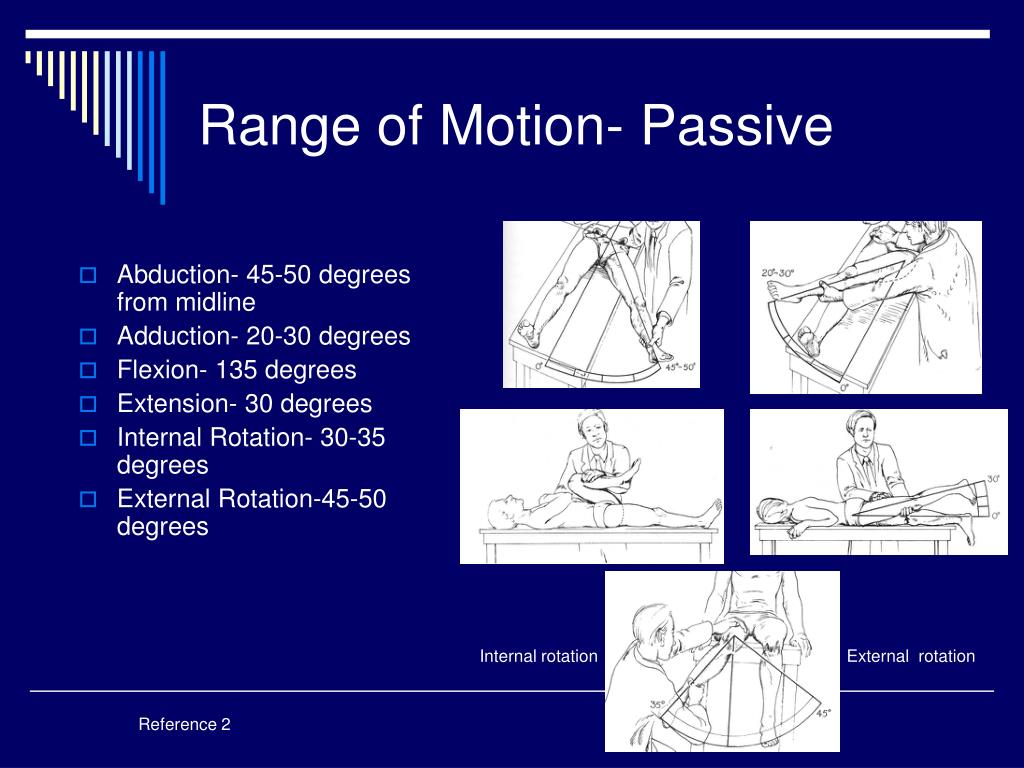
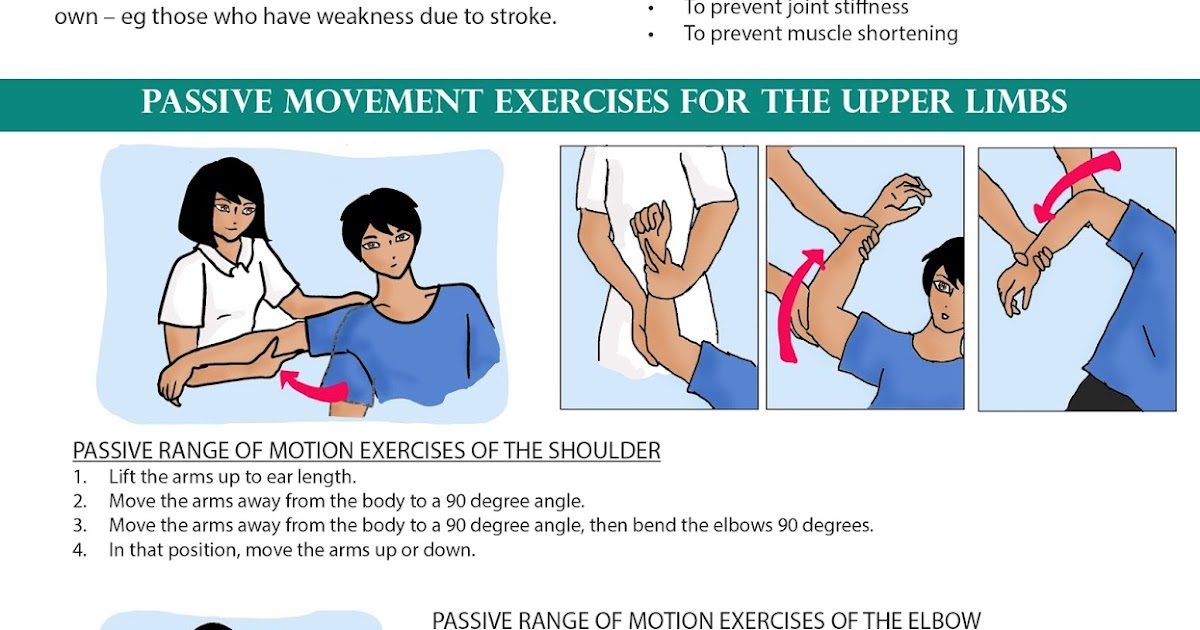
Start by identifying which joint you are working. The principle is the same across joints but the end-feel changes. Shoulder, elbow, hip, knee, ankle — each has a different neutral starting position. For a knee, the leg rests on a table, hip slightly flexed so the hamstring is offloaded. For a shoulder, the person lies supine and the arm is supported the entire time so gravity isn't doing half the work secretly. The person performing the motion holds the joint proximal and distal to the target joint. Two hands, never one. One hand stabilizes, the other moves. You move through the available arc until you feel the end-feel. There are three normal end-feels: soft, firm, and hard. A soft end-feel is muscle or fat giving way, like flexing a bicep. A firm end-feel is capsular or ligamentous tension, like closing a door on a spring hinge. A hard end-feel is bone hitting bone, like trying to fully straighten an already straight elbow. Anything other than those three is abnormal and usually means you went too far. The speed matters more than people realize. Move slowly, roughly one degree per second. Fast passive motion triggers the stretch reflex and the muscles guard. You think you are getting more range but you are actually fighting the patient's own nervous system. Slow motion bypasses that reflex and gives you a truer measurement.
I ran into a specific problem with a post-stroke patient who had what looked like a stiff shoulder on paper. Passive flexion stopped at about 90 degrees. Every therapist who tried it assumed capsular tightness. The workaround was to roll the patient onto their side first, let gravity take over, and then gently bring the arm back. The shoulder actually went to 130 degrees once you removed the weight of the arm pulling on the capsule. Positioning changed the reading by 40 degrees. Most people would have written that patient off as having a frozen shoulder if they didn't try the side-lying approach. Hold the end range for three to five seconds. Do not pump or bounce. Bouncing is active motion disguised as passive and it triggers protective spasm. Three to five seconds lets the proprioceptors settle and the tissue actually relax. Then return slowly. Do not drop the limb.
Get the Full Details

Where People Get This Wrong
The biggest mistake is treating passive range of motion as a stretching protocol. It is not. Stretching creates tension in the muscle-tendon unit and aims to lengthen it over time. PROM aims to maintain or restore joint play without loading the musculature. If the goal is muscle lengthening, you need sustained static stretching or PNF, not PROM. Using PROM for that purpose is like using a screwdriver to hammer a nail. It might work once or twice. You will strip the screw eventually. Another misconception is that more range is always better. It is not. There is a difference between physiological range and para-physiological range. Physiological range is the normal arc of motion a joint is built for. Para-physiological range is the small extra bit you can get past that using joint play techniques. For most clinical purposes you stay within physiological range. Pushing into para-physiological range without proper training and clear indication will irritate ligaments and create hypermobility, which causes more problems than it solves. People also forget that PROM does nothing for strength. If someone is doing PROM because they cannot move a joint actively, that is fine for the short term. But relying on it long-term without adding active-assisted or full active motion leads to muscle atrophy and neural inhibition. The joint might move passively through a good arc and still be useless functionally. I saw this repeatedly in hip replacement patients who could get their leg to 110 degrees of flexion passively but couldn't lift it themselves past 60 degrees because the glute medius had gone to sleep. PROM gave a false sense of recovery.
Equipment And Setup
You do not need much. A flat treatment table with a pillow for positioning, a goniometer for measurement, and a watch with a second hand or a timer on your phone. That is it. Machines exist for continuous passive motion, usually called CPM machines, and they are useful in specific post-surgical protocols like knee arthroplasty or rotator cuff repair where early controlled motion prevents adhesions. But a CPM machine is not a substitute for manual PROM and should not be used as one. Studies show CPM reduces early stiffness by about two to three degrees on average compared to manual therapy alone, which is statistically significant but clinically marginal for most patients. It is a tool, not a solution. When using a goniometer, align the stationary arm with the proximal segment and the moving arm with the distal segment. The axis goes over the joint's anatomical landmark. Shoulder flexion axis is the lateral humeral epicondyle. Knee flexion axis is the lateral femoral condyle. Ankle dorsiflexion axis is the lateral malleolus. Get the alignment right or your numbers are garbage. I have seen people measure shoulder flexion with the goniometer axis over the acromion instead of the humeral epicondyle and get readings that were five to ten degrees off. That sounds small until you are tracking progress week to week and your data says the patient lost range when they actually gained it.
Documenting Passive Range Of Motion
Write down the starting position, the direction of motion, the degrees achieved, and the end-feel. Example: "Right shoulder passive flexion, supine, 120 degrees, firm end-feel." Do not just write "good ROM" or "improved." Those are useless notes. Ten weeks from now you or another clinician will look at that and learn nothing. Specificity costs three extra seconds and saves hours of confusion later. Record both sides even if you are only treating one. Asymmetry tells you more than absolute numbers. A knee at 135 degrees of flexion sounds normal until you see the other knee goes to 145. That 10-degree gap is meaningful.
When PROM Fails You
Passive range of motion will not help if the restriction is intra-articular pathology like osteophytes, loose bodies, or advanced cartilage loss. Bone on bone stops motion physically. No amount of gentle passive movement will change that. In those cases you are measuring the limitation, not correcting it. Be honest about that. Tell the patient and document it. Pushing PROM into a hard bony end-feel repeatedly can cause synovitis and make things worse. It also fails in acute inflammatory states. If a joint is hot, swollen, and painful on even light touch, passive motion is contraindicated until the inflammation subsides. I had a gout flare in a patient's first MTP joint where the podiatry team wanted to do PROM for rehabilitation. The joint was visibly inflamed and the patient winced when the table cloth brushed it. We held off for ten days, switched to isometric contractions of the surrounding musculature, and then resumed PROM with full pain-free range. Starting PROM during that acute phase would have been a mistake. Psychological factors matter too. Fear of pain can restrict passive range just as much as tissue tightness. A patient who is anxious about shoulder movement after surgery may clamp down subconsciously even during passive motion. You can see it in the resistance against your hands. In those cases you slow down, reduce the arc to what is tolerable, and build from there. Forcing through fear-based guarding just reinforces the avoidance pattern.
PROM is a maintenance and measurement tool first, a therapeutic intervention second. It keeps joints moving when active movement is not possible. It gives you objective data on where a patient stands. It is not a cure for anything on its own. Used correctly alongside active rehabilitation, it buys time and provides information. Used in isolation or with unrealistic expectations, it is just someone waving a limb around and calling it progress.