Writing session notes that don't make you want to quit
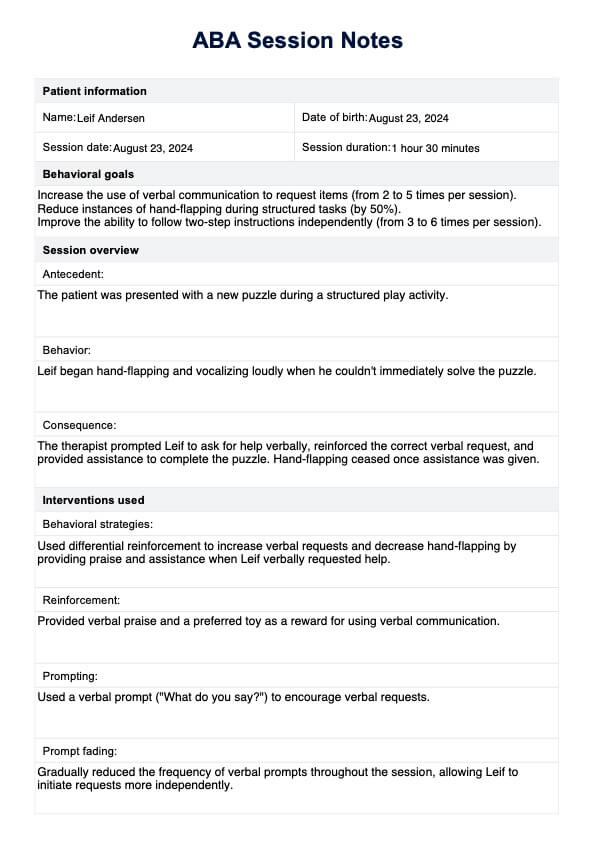
Most people thinkABA therapy session notes are just a compliance checkbox. They're not. They're the single most important tool you have for tracking whether a treatment plan is actually moving or just coasting. I've seen therapists spend thirty minutes on a note that documented nothing useful, and I've seen good notes written in under five minutes because the structure was built right from the start. The fundamental problem with session notes is that they're usually written retrospectively. You're trying to recall data points from a session that ended twenty minutes ago while also thinking about what's coming up next. That's why the format matters more than the content at first glance.Aba Therapy Session Notes Examples
Example 1 – Brief Data Note: Date: 03/15/2026 | Client: J.D. | Target Skill: mand for break using PECS | Trial count: 20 | Correct: 18 (90%) | Prompt level: Full physical prompt on 2 trials, gestural on 0, independent on 18 | Reinforcer: 2-minute video access | Notes: Client initiated break request independently 3x during unstructured time. Continued to use "all done" verbatim when frustrated with math worksheet. Recommended fading to partial physical prompt over next 2 sessions. Example 2 – Comprehensive Session Note:
Date: 04/02/2026 | Client: M.T. | Age: 7 | Service: 60 min ABA | Location: Clinic | Staff: RBT #442 | Target Programs: 1. Emotion identification (20 trials) – 16/20 correct | Visual prompt fading in progress, currently using point-to-photo prompt on 4 errors | Transfer stimulus control to intrinsic cues remains the priority. 2. Parallel play with peer (15 min structured) – Client remained in proximity for 12 of 15 minutes | Required 2 verbal prompts to initiate joint attention | Matched previous session performance. No change to program intensity needed.
3. Toileting routine (2 attempts) – Independent on steps 1-3 | Needed modeling for step 4 (handwashing) | Added visual schedule to bathroom with photo sequence. Behavior: Noelopment occurred. Client displayed 1 episode of vocal stereotypy (hand-flapping) during math task at approximately 25-minute mark. Duration: 45 seconds. Applied differential reinforcement of alternative behavior (DRA) – reinforced book-flipping instead. Episode resolved within 90 seconds total. Plan: Continue current programming. Increase anti-establishment practice to 10 minutes per session if vocal stereotypy persists beyond 5 more sessions. Parent training scheduled for next week.
Get the Full Details

The structure most people get wrong
The standard format that actually works across providers and payers looks like this: Client identifying information | Date and duration | Staff credential | Target programs with trial data | Behavioral observations | Reinforcement details | Next session plan That's it. Nothing fancy. The reason this works is because every single payer I've dealt with – Medicaid, private insurers, school districts – expects to find the same data points in roughly the same order. Deviating from this causes unnecessary back-and-forth during claims review.
Here's a counter-intuitive thing: writing your notes during the session, not after, produces better data and faster documentation. I know this sounds impossible if you're the one running the trials. But I keep a notes app open on a second device or a clipboard in the corner and jot trial results in shorthand as they happen. Something like "T1-T5: 4/5 FP -> G" takes three seconds and prevents the catastrophic memory loss that happens when you try to recall twenty minutes of data at once. The workaround I use is abbreviated coding. I don't write "Full Physical prompt" every time. I use FP, G for gestural, I for independent, VP for verbal prompt. Once you internalize these abbreviations you're writing at the speed of thought. Most billing systems accept the abbreviated format as long as the meaning is unambiguous.
Common pitfalls that sink your notes
The biggest mistake I see is vague language. "Client made good progress today" is useless. What did he do? How many trials? What was the accuracy? What prompt level? If you can't answer those three questions from a note, the note failed. Another one: not recording the absence of target behaviors. If the skill was practiced and didn't occur at all, document that. "0/20 correct, required full physical prompt on all trials" tells a different story than "Worked on emotion ID." Both are valid data. One is informative. There's also the prompt dependency trap. Beginners often don't distinguish between the type of prompt and the level of prompt. A gestural prompt is a category. Pointing to a picture is the specific implementation. Your notes should capture both because they inform the intervention differently. If you only write "gestural prompt used" the next therapist has no idea whether you pointed, modeled, or gave a verbal cue.

When session notes aren't enough
Some situations require more than a standard note. If a client has a behavioral emergency, a significant regression, or a change in medication that affects treatment, a regular session note won't capture the necessary detail. In those cases I write an addendum. It's a separate document attached to the session record that goes into depth on what happened, what was done, and what the plan is. Insurance often requires these addenda for certain CPT code reviews. The downside of detailed session notes is time. Even with shorthand, comprehensive notes take longer than lazy ones. If you're seeing six to eight clients a day the math is brutal. I handle this by batching note-writing at the end of the day rather than doing it between sessions. Your brain switches context constantly otherwise and you end up doing both tasks worse. Thirty focused minutes after your last session beats forty-five scattered minutes spread throughout the day. Some platforms try to automate this with template-driven note-taking. They work for basic documentation but they strip out the clinical nuance that makes a note actually useful for treatment planning. I use templates as a skeleton but I always write the substance by hand. The templates handle the formatting compliance and the manual writing handles the clinical accuracy.
Data entry errors are another real problem. I once had a client's accuracy rate recorded as 90% when it was actually 40%. I'd written "4/5" in shorthand and misread it as "9/10" when transcribing later. Two different data sets, completely different clinical implications. This is why I cross-check every number before finalizing a note. Takes ten extra seconds. Worth every second. The bottom line is that session notes are a clinical tool first and a billing tool second. If you treat them as a billing checkbox you'll produce notes that satisfy auditors but don't help your clients. If you treat them as a treatment planning document the billing part takes care of itself.



