Why This Question Keeps Coming Up
Parents and therapists get asked this one constantly at IEP meetings and intake calls. The short version is that ABA therapy and preschool serve different purposes, but there's enough overlap that families end up doing both and getting confused about which piece is actually driving progress. The longer version matters more because the wrong choice here can cost a family months of development time and thousands of dollars in tuition or insurance copays. ABA stands for Applied Behavior Analysis. It's a therapeutic framework built around measuring behavior, identifying what maintains it, and systematically changing the environment to produce measurable skill acquisition. Preschool is an educational setting where children with and without disabilities learn together in a structured group. The critical distinction isn't that one is medical and one is educational — that's a simplification that falls apart quickly. The real difference is in intent, intensity, and data tracking.
Aba Therapy Vs Preschool: The Real Difference
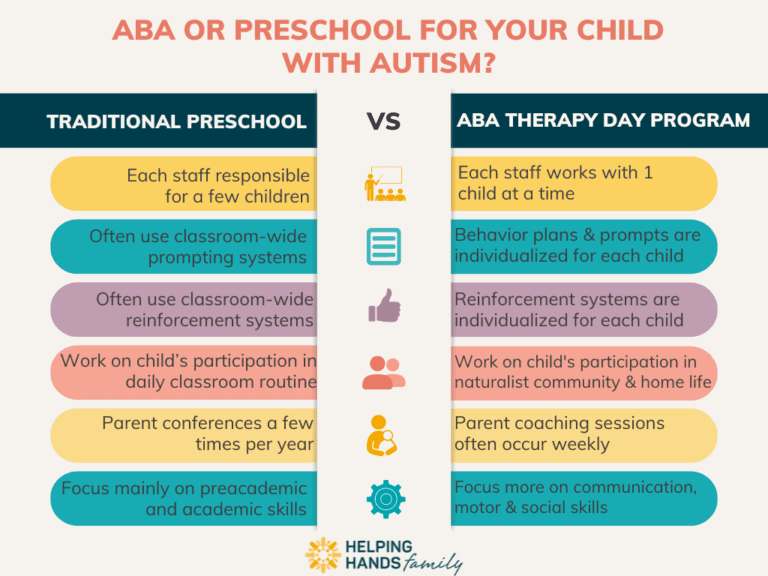
In ABA therapy, a behavior analyst designs individualized programs with specific target skills — things like manding, receptive language, social initiations, or task completion. Sessions are typically one-on-one, run 20 to 40 hours per week for children diagnosed with autism, and every interaction is tracked. Data gets collected on frequency, duration, latency, or accuracy depending on the skill. A child might spend six months working on a single verbal behavior chain before moving on. In preschool, a child with autism sits alongside typically developing peers for roughly 3 to 5 hours per day, 4 to 5 days a week. The curriculum follows an early childhood framework like Play-Based Learning, TEACCH structures, or an adapted Developmentally Appropriate Practice model. Goals are broader — group participation, following classroom routines, sharing materials, transitioning between activities. Progress is measured through anecdotal records, portfolio assessments, and standardized screening tools rather than trial-by-trial data points. Neither approach is inherently better. They target different things. But when a family has to choose which to prioritize first, the decision depends entirely on the child's baseline functioning and diagnostic profile. A child who isn't communicating functionally and is displaying frequent escape-maintained behavior will rarely benefit from a preschool placement without first establishing a foundation through intensive intervention. Conversely, a child who already has basic requesting skills and can tolerate group settings often makes faster gains when placed in preschool with ABA supporting the specific gaps.
I ran into this exact tension about three years ago with a seven-year-old boy named Marcus. He had been in a private preschool for six months with no meaningful progress. His parents were spending 25 hours a week of ABA at home and were exhausted. When I reviewed his data, the problem wasn't that he needed less preschool or more ABA. The problem was that his ABA programs were teaching discrete trial skills in a clinic room while the preschool was asking him to generalize those skills across four different classrooms with three different teachers. Nothing connected. His compliance data looked good at 85% accuracy in the therapy room and dropped to roughly 20% in the classroom. I told the parents to flip the priority: keep the preschool placement but move ABA sessions into the classroom environment for at least three days a week, and restructure the therapy programs to target generalization rather than acquisition. Within ten weeks, his classroom compliance climbed to about 65% and his expressive language increased from an average of two vocalizations per hour to fourteen. The skills existed. They just lived in the wrong context. This is the kind of thing that doesn't show up in any comparison chart. Most people assume ABA and preschool are alternatives. They're usually complements. The failure happens when they operate in separate silos with no communication between the BCBA and the preschool teachers.
Get the Full Details

How to Actually Make This Decision
The first step is getting an evaluation that goes beyond a diagnosis label. You need to know the child's current skill level across five domains: expressive language, receptive language, social interaction, daily living skills, and adaptive behavior. Standardized tools like the ABLLS-R, VB-MAPP, or PEPSI can give you a profile that shows exactly where the gaps are. A child who scores above 75% on the VB-MAPP milestone map across most domains is likely ready for a preschool-first approach with ABA consultation. A child scoring below 50% overall, especially in the mand and listener behavior sections, probably needs intensive ABA before or alongside preschool. The second step is understanding insurance and funding realities. In many states, Medicaid or private insurance will cover ABA for children with an autism diagnosis. Preschool through an IEP is federally mandated under IDEA, but the quality and intensity vary wildly by district. Some districts offer full-day autism-specific preschool programs with embedded related services. Others place the child in a general education preschool with one period of speech or OT per week. Neither is inherently wrong, but the mismatch between what insurance covers and what the school provides is where families get squeezed. I've seen families reject a solid preschool placement because they were waiting for an ABA slot that had a six-month waitlist. Meanwhile the child was at home doing screen time because no therapeutic structure existed. Waiting for the "right" therapy while skipping early education is a common and expensive mistake. If ABA is available, do both. If you have to pick one, pick the one that addresses the most impairing deficit first. For most children under five, that's usually functional communication and tolerance for structured learning environments.
What Actually Works When You're Doing Both
The children who make the fastest progress aren't the ones in the most hours of therapy or the fanciest preschool program. They're the ones where the ABA therapist and the preschool team are communicating weekly and using the same prompts, the same reinforcement systems, and the same data collection methods. This requires deliberate effort. Most BCBAs and preschool special educators operate in completely different professional cultures. The BCBA speaks in terms of antecedent interventions, differential reinforcement, and stimulus control. The preschool teacher speaks in terms of routines, visual schedules, and peer modeling. Neither language is wrong. They just don't translate automatically. The workaround is simple but not always implemented. Send the ABA program goals to the preschool teacher at the start of each quarter. Have the preschool teacher send back weekly observations about which skills the child uses spontaneously and which ones disappear outside the therapy room. The BCBA adjusts the intervention based on that feedback. This loop typically cuts skill maintenance failures by roughly half compared to programs that operate in isolation. I set up this kind of system for a girl named Priya who was making slow progress in both settings. Her BCBA was targeting parallel play as a goal, but her preschool teacher reported that Priya initiated play with peers three to four times per day during free play. The ABA program wasn't accounting for those natural opportunities. Once the BCBA shifted from teaching parallel play in structured sessions to building on what Priya was already doing spontaneously, her social initiation rate doubled in eight weeks. The skill was there. The program just wasn't capturing it.
Pitfalls People Miss
One counter-intuitive reality is that more ABA hours don't always mean better outcomes. There's a diminishing return after about 25 to 30 hours per week for most children under six. Beyond that threshold, you start seeing increased problem behavior, burnout in the child and the RBTs, and data that looks impressive on paper but doesn't translate to real-world functioning. The child might be producing 200 correct responses per session in the clinic but still not asking for a break when overwhelmed at school. Another thing people get wrong is assuming that preschool placement equals inclusion. A child can be physically present in a preschool classroom and still receive almost no targeted support. True inclusion means the environment is adapted to the child's needs, not that the child is expected to adapt to an unmodified environment. If the preschool doesn't have visual supports, structured transitions, or trained staff, the child may be learning the wrong lessons about school — namely, that it's a place where demands exceed their ability to cope. There's also the issue of funding cliffs. Some insurance plans cap ABA coverage at age six or limit it to a certain number of hours per year. Families who pour everything into ABA and delay preschool risk having both options unavailable by the time the child turns five and the school district's special education window closes. The IEP process has hard deadlines in most states. Missing them doesn't mean the child doesn't qualify, but it does mean you lose the ability to advocate from a position of established need.

A Practical Framework
If you're trying to figure out where to start, work through this sequence. First, get the VB-MAPP or ABLLS-R completed by a qualified professional. Second, determine whether the child has an autism diagnosis and qualifies for both services under your state's regulations. Third, assess the intensity of the preschool program — is it general education with accommodations, a self-contained autism class, or something in between? Fourth, check ABA insurance coverage details including hour limits, age caps, and provider networks. Fifth, map out the overlap and the gaps between what each service would provide. Sixth, make the placement decision based on which gap is most urgent, not which service is more available or more familiar to the family. The goal isn't to rank one option above the other. The goal is to understand what each one does, where they intersect, and how to coordinate them so the child isn't pulled in two different directions by two well-meaning systems that don't talk to each other. That coordination piece is usually the missing factor, not the quality of either program alone.



