The ABC framework isn't a theory. It's how you keep people alive when they come through the door.
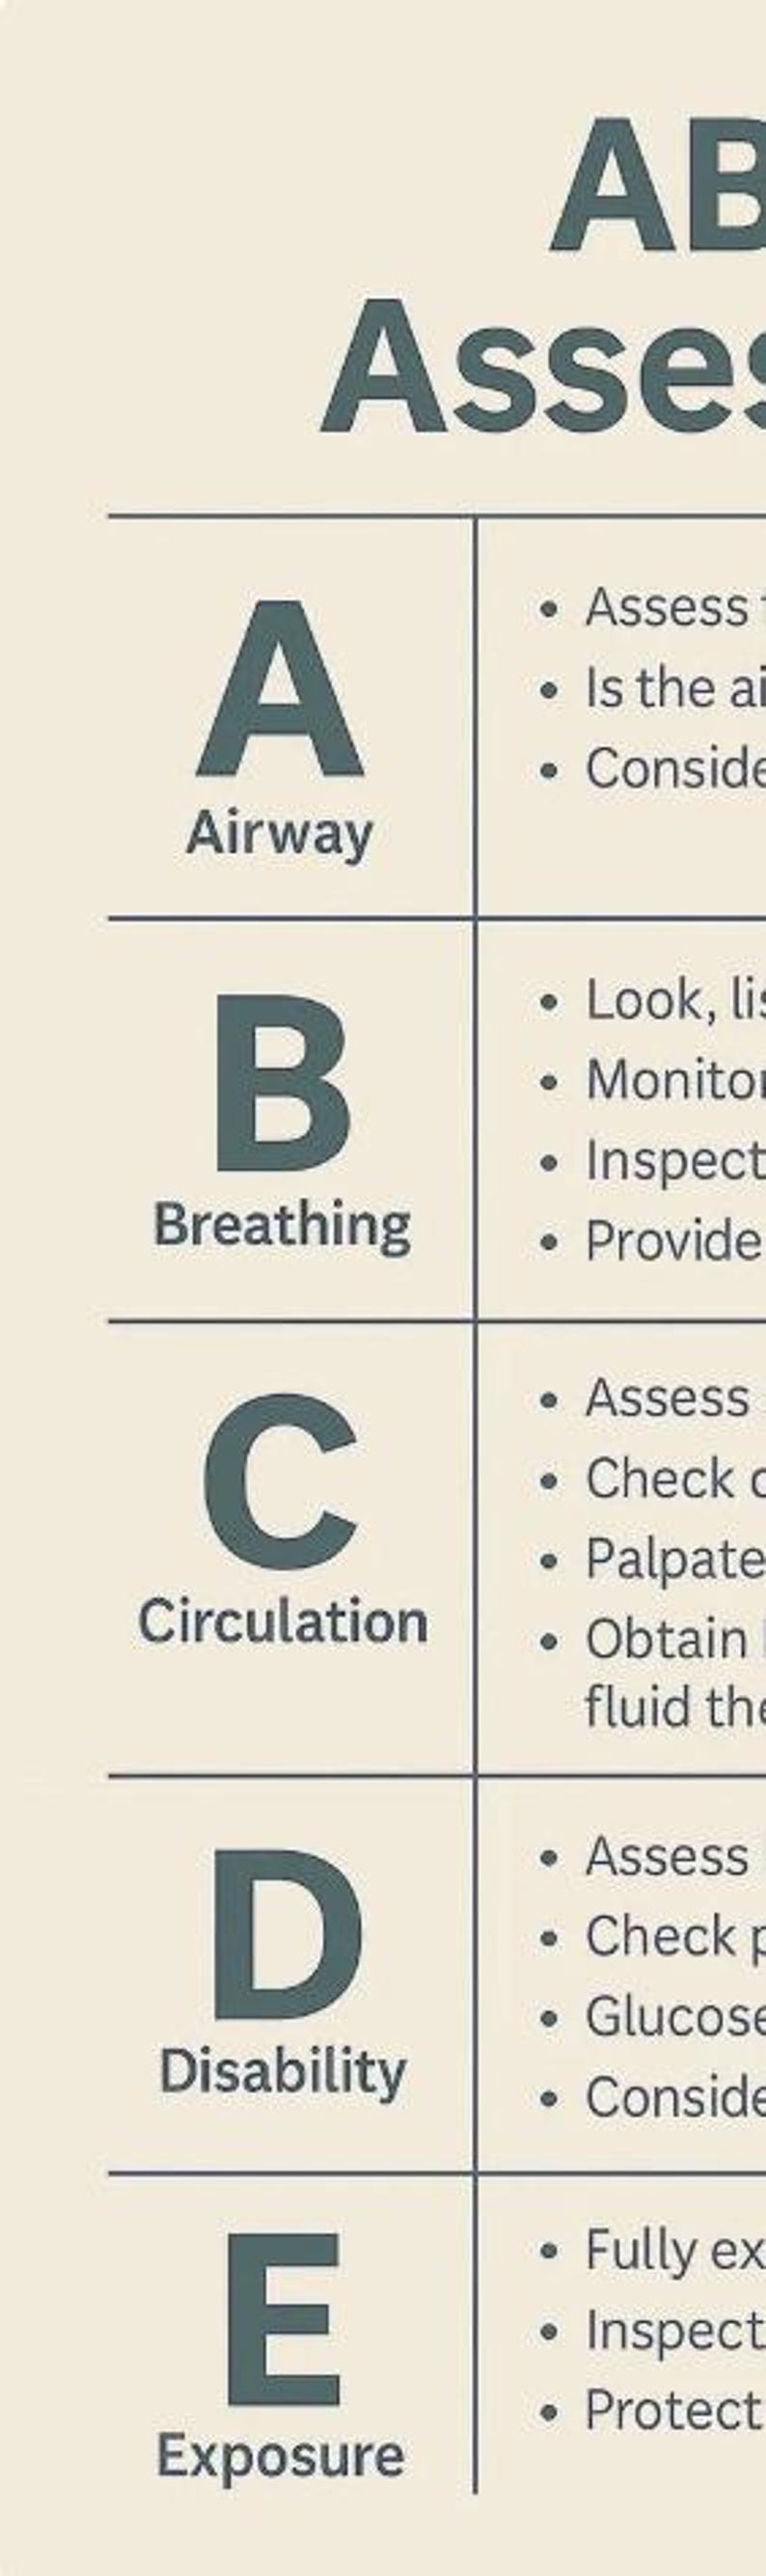
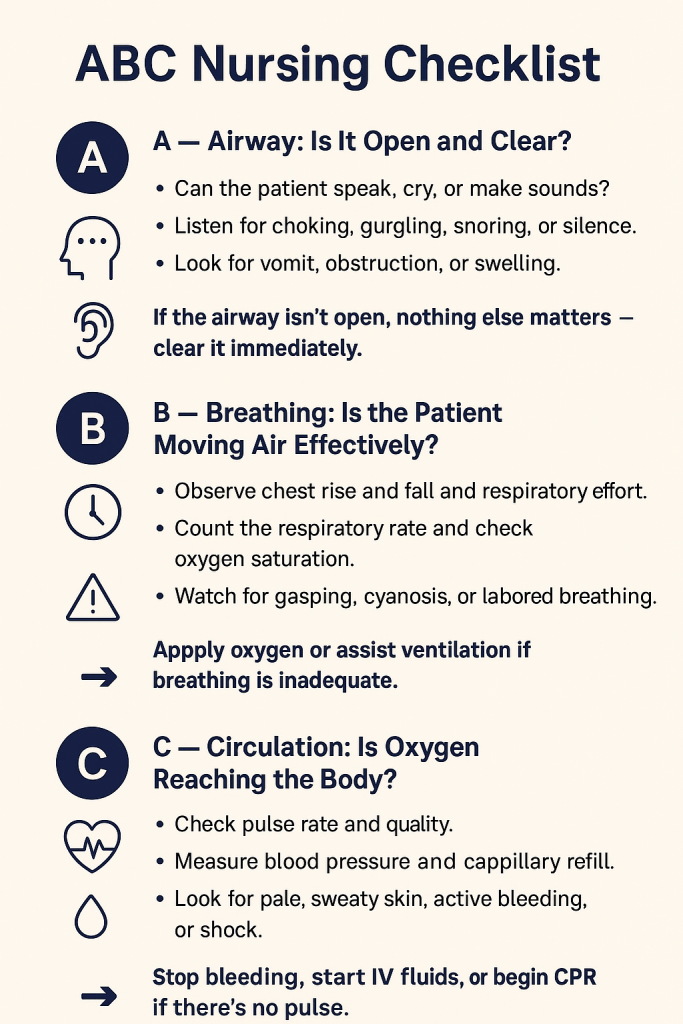
Nursing assessment is basically the art of figuring out what is wrong with someone before they get worse. The ABC of Nursing Assessment breaks it down into Airway, Breathing, and Circulation. You check them in that order because if the airway is blocked, none of the other stuff matters. You start there every single time. I learned this the hard way in my second year on a med-surg floor. A patient came in with what looked like a stomach bug. Nausea, vomiting, maybe food poisoning. I spent twenty minutes checking their abdomen while their oxygen saturation ticked down from 96 to 88. They had a massive aspiration event. The nausea was a red herring. The ABC of Nursing Assessment would have caught the airway compromise first if I had stuck to the sequence instead of going in the wrong direction because the presenting complaint was misleading.
Abc Of Nursing Assessment in Practice
Here is how you actually do it, not how the textbook describes it. Airway comes first. You look at the person. Is their voice normal? Are they speaking in full sentences? If they are stridor — that high-pitched sound on inhalation — the airway is narrowing and you move fast. If they are gurgling, something is in the way. Check for foreign bodies, vomit, blood, tongue swelling. Anaphylaxis patients can close their airway in minutes. I once had a patient with a shellfish allergy who went from mild hives to needing a cricothyrotomy kit in under eight minutes. The key is watching the work of breathing, not just asking if they can breathe. Breathing is the second step. Look at chest rise and fall. Count the respiratory rate for a full minute, not fifteen seconds multiplied by four. That multiplication trick hides things. A patient at twenty-eight breaths per minute with shallow tidal volumes is in far more trouble than someone at eighteen with deep, regular breaths. Use pulse oximetry. Capnography if you have it. The numbers matter, but the pattern matters more. Tripoding, accessory muscle use, nasal flaring — these are your early warning signs before the SpO2 drops.
Circulation is where most people rush. Heart rate, blood pressure, capillary refill, skin temperature, moisture. A tachycardic patient with cool, clammy skin is compensating for poor perfusion. They look fine until they don't. I had a trauma patient in the ER whose blood pressure was 118 over 76 and his heart rate was 112. The chart says "stable." The capillary refill was three seconds and his hands were cold. He was bleeding internally. I flagged it as a concern, got a STAT ultrasound, and he ended up with a spleen laceration that needed embolization. If I had stopped at "normal blood pressure," he could have crashed on the floor. There are limits to the ABC of Nursing Assessment that nobody tells you. It works brilliantly for acute deterioration. It is much less useful for chronic conditions. A diabetic patient with long-standing neuropathy might have a resting heart rate of 100 and blood pressure of 105 over 68 their entire stay, and that might be their baseline. Rigidly applying ABC thresholds without context leads to false alarms and alarm fatigue. You need to know what normal looks like for that individual patient. Another blind spot is pediatric assessment. Kids compensate until they abruptly decompenate. The ABC framework still applies, but the signs are different. A child with airway compromise might not have stridor — they might have grunting and nasal flaring. Their respiratory rates run higher. Their blood pressure is a late sign of shock. If you use adult norms on a pediatric patient, you will miss things until it is too late.
Get the Full Details

The full assessment doesn't stop at ABC. After you confirm the airway is patent, breathing is adequate, and circulation is stable, you move into the rest of the nursing assessment — pain, neurological status, history, head-to-toe exam. The ABC gives you the priority sequence. It doesn't replace the rest of the work. What helps most is deliberate practice. Run through the ABC sequence mentally before you walk into every patient room. Not every day. Every shift. The framework takes about two minutes for a quick sweep and eight to ten minutes for a thorough assessment, depending on acuity. In a stable unit that might seem excessive. In an acute one, it is the difference between catching deterioration early and calling a code team at 2 AM because someone flatlined on the toilet. Document what you find. Not just that the airway was patent, but how you determined that. Not just that pulses were strong, but which ones and what the quality was. Documentation is your legal protection and your communication tool for the next nurse. If the next person reads "airway clear" and you checked it by listening to breath sounds versus visually inspecting and asking the patient to speak, they are getting different information.
The ABC of Nursing Assessment is simple in theory and fickle in practice. It requires you to know when the rules apply and when you need to look past them. Stick to the sequence. Question the easy answers. And never let a normal blood pressure make you complacent.