Primary Assessment in the Real World
How I actually use the Abcde Model Of Primary Assessment at the bedside
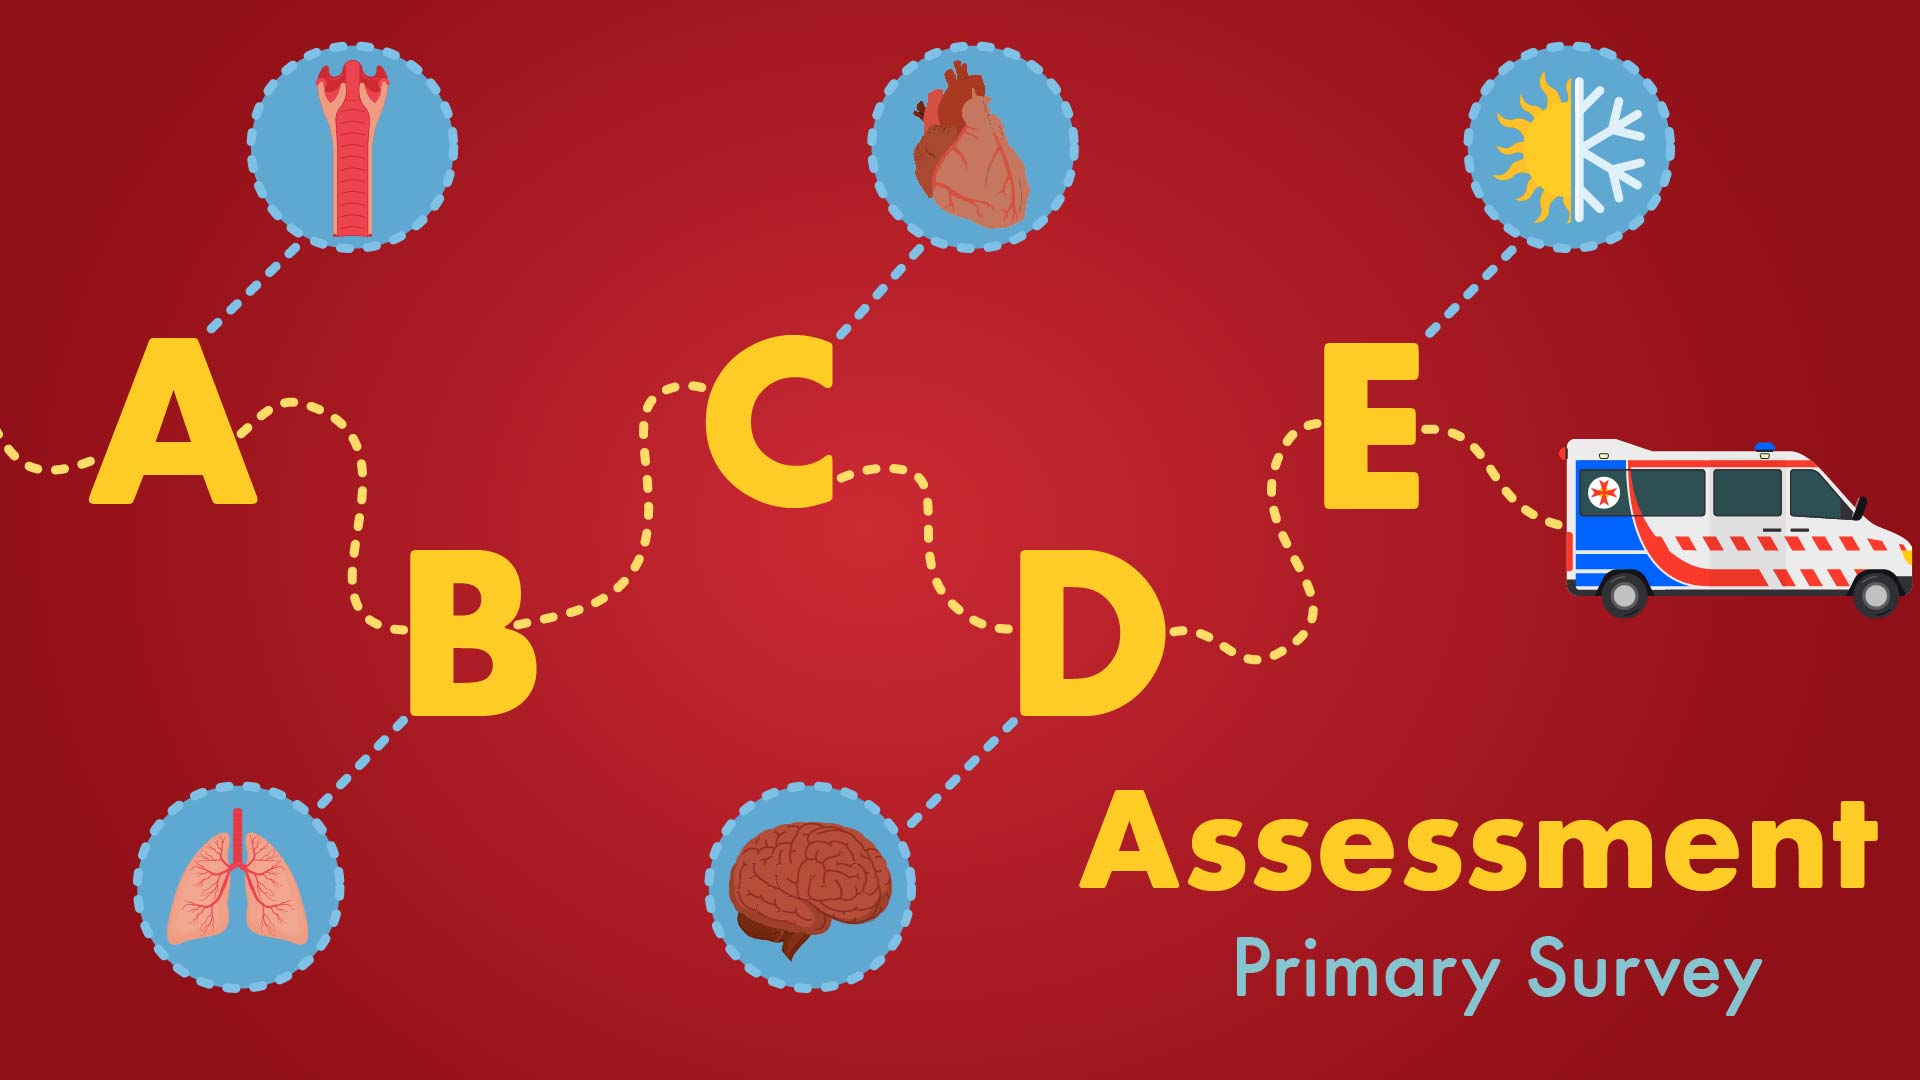
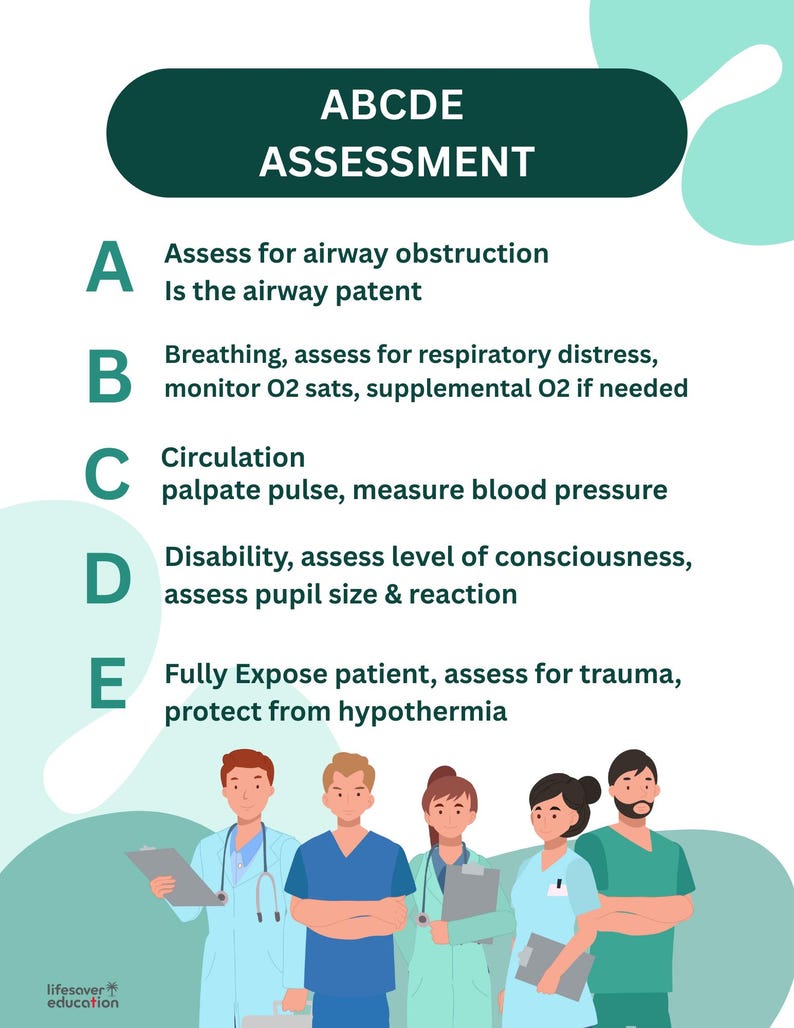
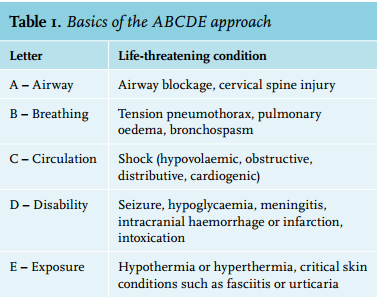
The ABCDE model is a structured approach to assessing and managing a deteriorating patient. It stands for Airway, Breathing, Circulation, Disability, and Exposure. You go through each letter in order, identify problems, treat them before moving on, and reassess. That is the textbook version. The actual version involves someone shouting different instructions while you are trying to remember what you checked last. I have used this model in A&E, on the ward, and during emergency calls. It is not glamorous. It is also one of the few things that reliably keeps you from missing the obvious when things get loud. The problem most people have is not understanding the model. It is applying it under pressure without turning it into a rigid checklist that slows you down.
How the model actually works in practice
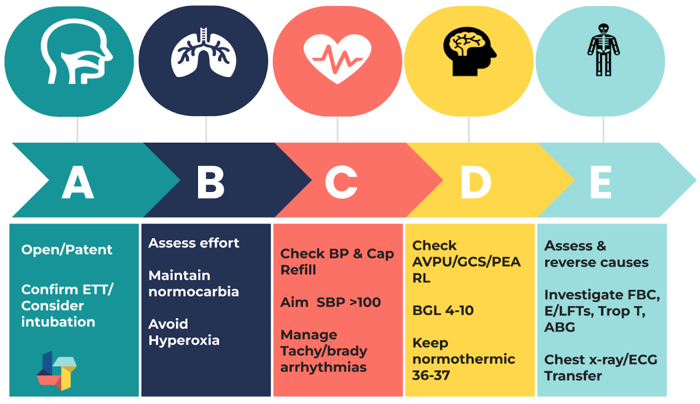
Start with airway. Not by looking at the throat. By listening. If the patient is talking to you, the airway is patent. That is the first thing most junior clinicians miss because they immediately go for manual manoeuvres or suction when nothing is wrong. Speak to the patient. If they can form sentences, move on. If they are groaning or gurgling, that is your signal. Gurgling means blood or fluid in the upper airway. Suction first. Head tilt and chin lift second. OPA or NPA depending on whether they have a gag reflex. Breathing comes next. Look at the chest. Watch the rate, the depth, the use of accessory muscles. Listen. Palpate if you need to. Check oxygen saturations, but do not let the number dictate everything. A saturations of 96 percent on room air is fine. A saturations of 94 percent on four litres of oxygen through a non-rebreathe mask is not fine. It means the patient is working hard to maintain that number and is likely to crash soon. I had a patient once who maintained 95 percent on high flow oxygen while becoming progressively less responsive. The numbers looked acceptable. The clinical picture said otherwise. We intubated before they went full arrest. Circulation is where people rush. Check pulse, check capillary refill, check skin temperature, check blood pressure. That order matters. A blood pressure of 110 over 70 means nothing if the pulse is thready and the hands are cold. Perfusion matters more than the number on the monitor. I remember a trauma call where the BP was stable but the patient was frankly shocked. Cold, clammy, tachycardic at 130. The monitor showed 105 over 68. We treated the patient, not the number. Two units of blood later and they stabilized. The lesson was simple but easy to forget when the monitor is beeping happily.
Disability. AVPU. Airway open? Breathing? Circulating? Responds to voice? Responds to pain? Unresponsive. That is the quick version. Then pupil size and reaction if you have time. Blood glucose if you can get it. A missed hypoglycaemic patient is a terrible way to spend a Tuesday. I once spent ten minutes trying to find a cause for unilateral dilated pupil in a trauma patient before remembering to check the sugar. It was 1.8. The pupil was a red herring caused by shock and catecholamines. Fixed dose of dextrose and they woke up. Lesson learned. Exposure is the final step. Fully expose the patient to find hidden injuries or rashes or tracks or whatever else is going on. Then warm them back up. Hypothermia kills. It also messes with coagulation and cardiac rhythm. Do not leave a patient half-covered in a resus bay while you debate whether you really need to check under their back. Check everything. Dry them. Warm blankets. Warm the room if you can.
Get the Full Details
Where the model breaks down
The biggest issue with the Abcde Model Of Primary Assessment is that it assumes a linear progression. Real patients do not follow the script. You will find a breathing problem while checking the airway. You will find a circulation problem while assessing disability. The model still works, but you have to loop back. Treat what you find. Reassess. Move forward when you are ready. Another problem is cognitive load. When you are new to this, doing five things in sequence while everything around you is chaotic takes mental energy that you do not have. The workaround is repetition until it becomes automatic. Practice on manikins. Practice on colleagues. Practice on real patients when the situation allows. Eventually you stop thinking about the order and just think about the patient. The model also fails in patients with chronic conditions. A COPD patient may have a baseline oxygen saturation of 88 percent. Telling them they need 94 to 98 percent will make you chase a number that does not apply to them. Know your patients. Adjust targets. The model gives you the framework. Your judgment fills in the details.
A quick note on documentation
Write things down as you go. Not after. Not when you remember. During. I use a simple system: A done at 14:32, B done at 14:35 with O2 at 15 litres via non-rebreathe, C done at 14:37 with IV access gained, D done at 14:40 with GCS 14, E done at 14:42. Time stamps matter when you hand over to the next team. They also matter if anything goes wrong and you need to reconstruct what happened. The model itself is not complicated. Applying it well is what takes time. Most people get through one full cycle in about three to five minutes if the patient is straightforward. If the patient is not straightforward, expect to spend twenty minutes or more going back and forth between categories. That is normal. It does not mean you are doing it wrong. It means the patient is sick and the model is doing its job by making you look systematically instead of randomly. There is no downloadable version of this. No app replaces the actual practice. What you can download are assessment tools and observation charts that map onto the model. Most hospitals provide these. Use them. But do not let the paper become the priority over the patient.
When to stop using it
There is no formal point at which you stop. You keep going until the patient is stable or until you hand over to someone who will keep going. If you are working alone and the patient deteriorates further, you call for help. The model does not replace a senior clinician. It replaces panic. Those are two different things. I have seen senior doctors skip straight to circulation when the patient presents in obvious respiratory distress. I have seen juniors spend seven minutes checking pupils while the airway was partially obstructed. The model exists to prevent exactly those mistakes. Follow it in order. Deviate only when you have a good clinical reason. Document the deviation. Reassess frequently. That is basically how it works. The rest is experience and repetition.