Understanding Your Diastolic Readings
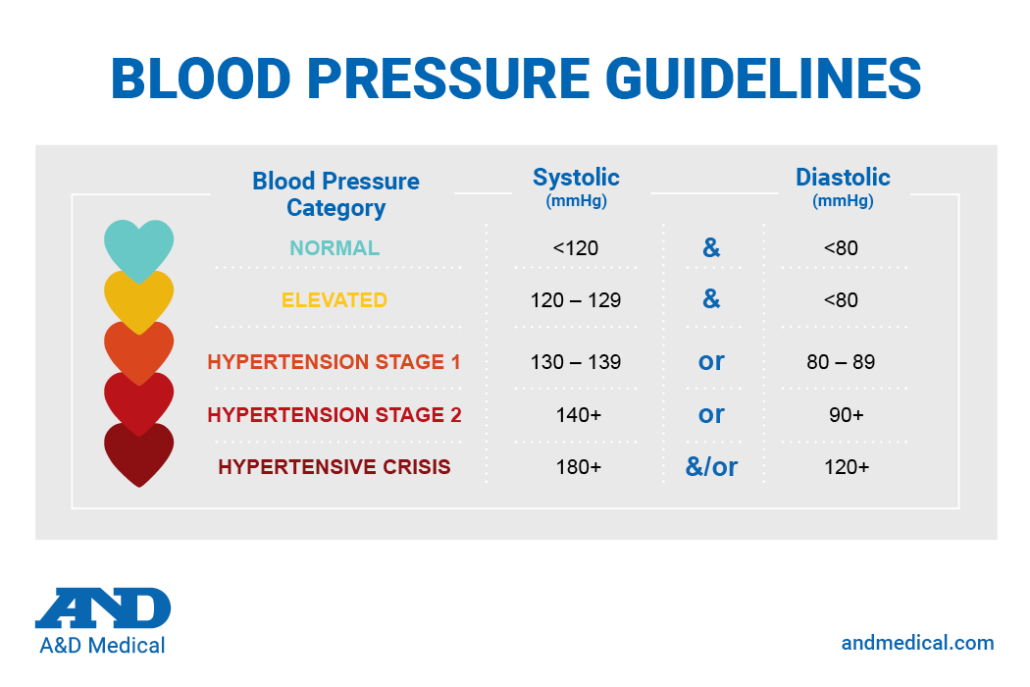
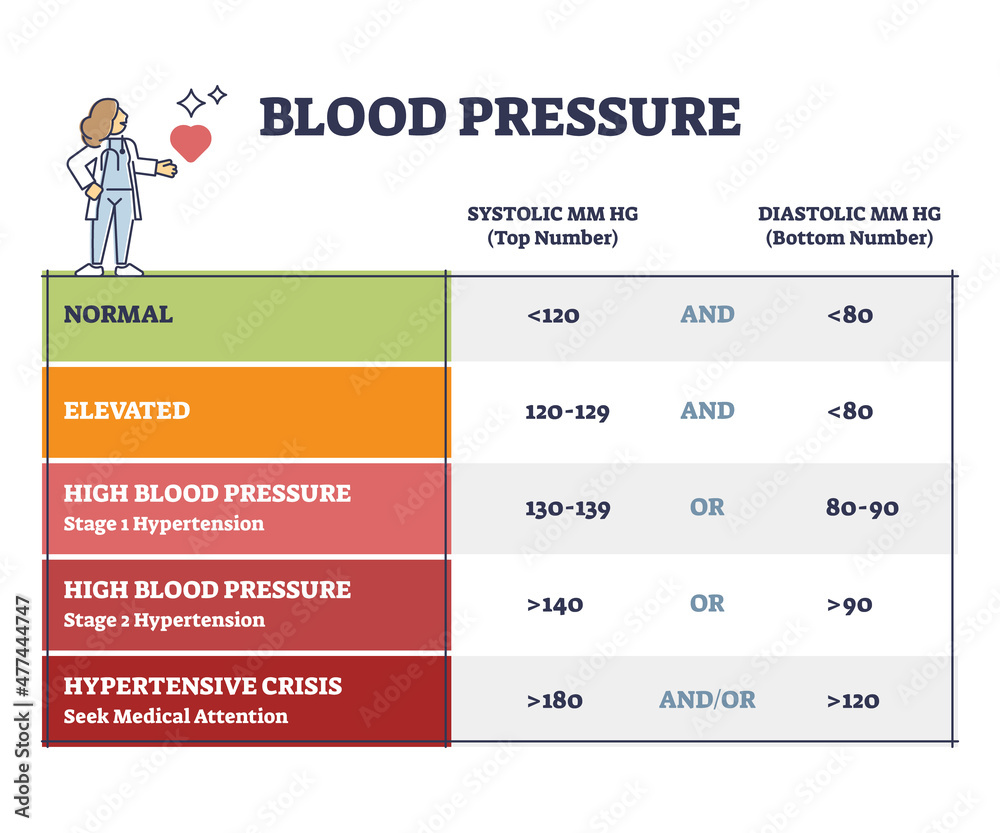
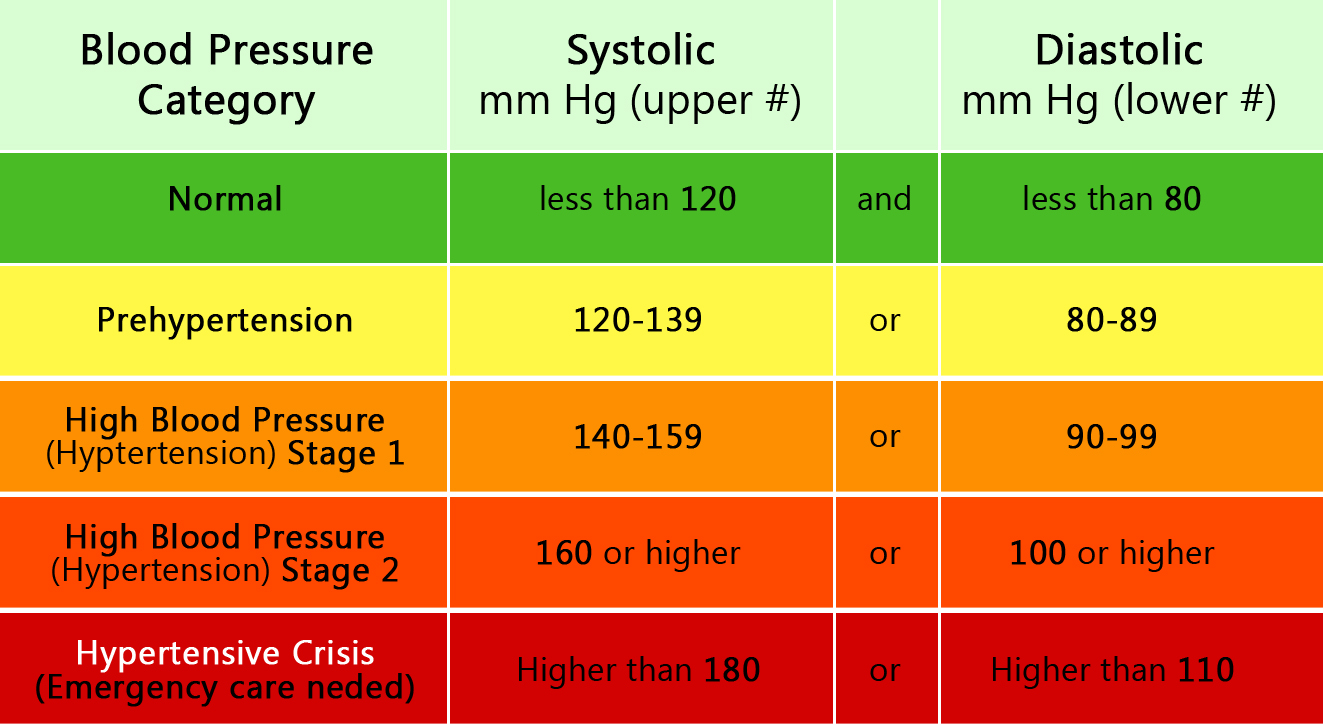
The bottom number on your blood pressure cuff isn't just a detail. It's what your arteries are under when your heart rests between beats. Most people I talk to in clinics know the top number but skip right past the second one. That's a mistake. Normal diastolic sits under 80 mmHg for most adults. Eighty to 89 is stage one hypertension territory. Ninety and up is stage two. That's where you start talking to a doctor about intervention. Anything below 60 can matter too if you're getting dizzy or faint — that's not normal for active people, though it's common in elderly patients on certain medications. I spent three years running a home blood pressure monitoring clinic. One pattern I saw constantly: people obsessed over the systolic because it looked scarier, but the diastolic was the one actually rising first. A patient of mine, 52-year-old male, kept his top number at 138 for months while his bottom number crept from 76 to 94. He didn't notice because he only checked once a week in the evening after work. When he switched to morning readings before coffee, the trend became obvious.
How to Measure It Right
Cuff placement matters more than most people realize. Sit with your back supported, feet flat, arm at heart level. Wrap the cuff on bare skin — over a shirt sleeve compresses the arm tissue and adds five to ten millimeters artificially. Wait five minutes before reading. Don't talk during the measurement. Take two readings thirty seconds apart and average them. I made this mistake early in my career. A patient's diastolic read 92 on one arm and 78 on the other. The high reading was on the arm with a wider cuff than recommended. We switched to the correct size and got the true number. Wrong cuff size inflates readings by roughly ten percent. That single error could have started someone on medication they didn't need.
Why Diastolic Gets Ignored
The top number gets all the press. Headlines shout about 180 over 100. But diastolic pressure reflects peripheral resistance — how constricted your small arteries are. When your diastolic stays above 80 for months, those vessels are under constant strain. The damage happens slowly. Kidneys don't complain until function drops significantly. Heart muscle thickens without symptoms until stages later. Here's something most guides miss: isolated diastolic hypertension — high bottom number with normal top number — peaks in younger and middle-aged adults under forty. By sixty, systolic usually takes over as the dominant concern. If you're thirty-five with a diastolic of 88, that's not nothing. It's your body sending an early signal.
Get the Full Details
When to Worry and What To Do
Track your numbers for two weeks before making conclusions. One bad reading means nothing. Lifestyle changes move the needle faster on diastolic than systolic in many cases. Weight loss of five kilograms typically drops diastolic by four to eight millimeters. Sodium reduction helps, though less dramatically than people expect. Exercise three times weekly showing measurable improvement in four to six weeks. Medication becomes necessary when lifestyle doesn't bring it below 80 after three months, or if you have kidney disease, diabetes, or existing heart conditions. ACE inhibitors and ARBs work particularly well for diastolic elevation because they target the vascular resistance component directly. One edge case: white coat diastolic hypertension. Some patients present with consistent 90+ diastolic at the clinic but 75 at home. Ambulatory monitoring catches this. I had a nurse who nearly started lisinopril based on office readings alone. Home logs showed her diastolic hovering around 72 all week. The medication would have caused unnecessary fatigue and potassium elevation for no real benefit.
The Real Problem With Normal Ranges
Guidelines keep shifting. Twenty years ago, 85 was acceptable. Now it's not. Younger patients especially get told their numbers are fine when they're sitting at 84 diastolic. That's technically within some older parameters but clinically suboptimal. The arterial wall doesn't care about guideline committees — it responds to sustained pressure. I've seen patients in their forties with diastolic consistently at 88 who dismissed it because they felt fine. Two years later, both had renal impairment. Not directly attributable, but the timeline was clear. Early intervention on diastolic in the high-eighties range reduces downstream complications significantly. Another oversight: nighttime dipping. Your diastolic should drop ten to twenty percent during sleep. Non-dippers — people whose numbers stay elevated overnight — face higher cardiovascular risk even with normal daytime readings. A simple home test: check your pressure right before bed and again first thing in the morning. If the morning number isn't lower, mention it to your provider.
The bottom line (pun unintentional): don't let anyone dismiss an elevated diastolic because your systolic is fine. They're different problems requiring different attention. The vessel health story lives in that second number.