Why Most Practices Get Aetna CCM Wrong on the First Try
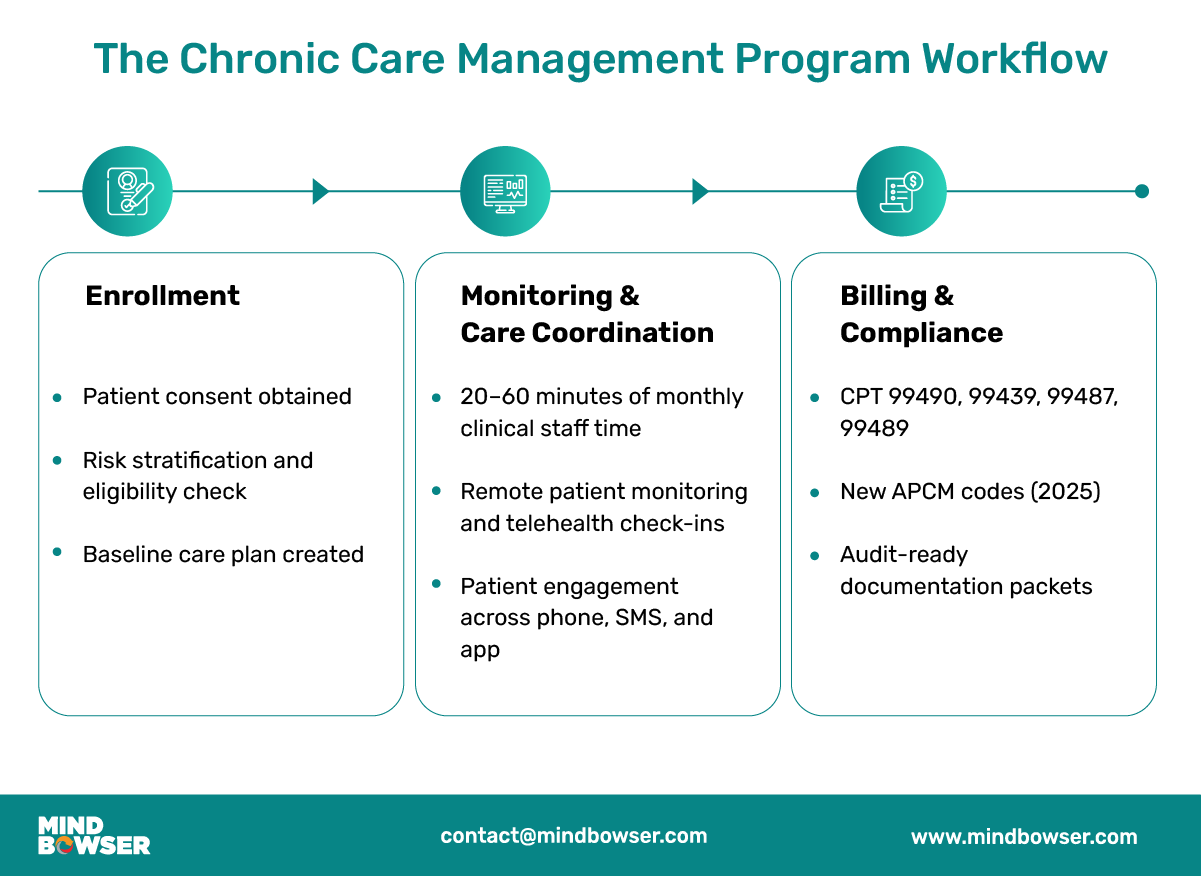
I spent about three years billing chronic care management codes across a mid-size multi-specialty group before I figured out what actually works with Aetna's claims system. The official guidance makes it look straightforward. The reality involves a lot of failed claims, frustrating denials, and some genuine quirks in how their clinical review team interprets the documentation. Let me walk through how this actually functions in practice, starting with what most people overlook. Aetna Chronic Care Management falls under the CPT codes 99490, 99439, and 99487, though they also recognize the add-on 99488 for prolonged services. The baseline requirement is a patient with two or more chronic conditions expected to last at least 12 months or until death of the patient, and those conditions place the patient at significant risk of death, acute exacerbation, or functional decline. That much is standard across almost every payer. Where Aetna gets particular is in how they validate that you actually provided the qualifying minutes and that the care plan was properly established before the clock started running. The workflow looks like this on paper. You identify eligible patients, obtain written consent, establish a comprehensive care plan, deliver at least 20 minutes of non-face-to-face clinical services per calendar month, and then bill accordingly. The non-face-to-face time includes phone calls, care coordination, electronic messaging, and review of outpatient records. Face-to-face visits during that same month don't count toward the 20-minute threshold, and this trips up a lot of practices. A patient can have an office visit and still qualify for CCM that month, but only if you're tracking and documenting the separate non-face-to-face minutes independently.
Here's a specific problem I ran into repeatedly. Aetna's clinical review sometimes denies a claim when the care plan element appears to be created after the first billable service date. They treat the timing of the care plan documentation as a causal question rather than a paperwork one. If your EHR timestamps the care plan creation at 11:47 PM on the same day you first started the phone call, the reviewer will likely deny it. The workaround is simple but easy to miss: create and sign the initial comprehensive care plan at least one business day before the first minute of billable CCM service. Keep a clear audit trail showing the care plan date precedes the CCM service start date. This isn't a rule in the code descriptor, but it's how Aetna's clinical adjudicators are evaluating these claims right now.
The Billing Mechanics That Actually Work
For 99490, you need 20 minutes of clinical staff time in a calendar month. That's the floor. For 99487, you need 60 minutes and the patient must have multiple significant chronic conditions plus high risk of hospitalization or decline. The 99439 add-on code accounts for each additional 20-minute increment beyond the base 60. You can bill 99490 and 99487 in the same month only if you're billing different patients, not stacking them for the same person. Aetna will flag that as a duplicate service during claims processing. The consent form is another area where Aetna catches people. Their preferred form asks for acknowledgment that the service is not required for treatment and that the patient will be responsible for cost-sharing. You can use your own consent form if it covers the same required elements, but Aetna's reviewers cross-reference against a checklist. Missing the cost-sharing acknowledgment line on a custom form has caused denied claims in my experience, even though the code itself doesn't explicitly require that wording. Include it verbatim to avoid the back-and-forth. One thing beginners consistently get wrong is the staffing model. Aetna counts time from qualified clinical staff, which means RNs, LCNPs, LMHCs, MTMs, and other delegated personnel under physician supervision. But the time has to be tracked in a way that links the staff member's credentials to the specific minutes billed. If you're using a centralized nursing team that handles CCM calls for ten providers, you need a system that attributes each call to the correct supervising provider and documents who actually delivered the service. Spreadsheet-based tracking almost never satisfies an audit. I've seen claims pulled years later because the supporting documentation couldn't connect the billed minutes to a specific staff member's schedule.
Get the Full Details

Pitfalls and When Aetna CCM Just Doesn't Make Sense
Chronic care management is not a reliable revenue stream for every practice. It depends heavily on patient population, staff availability, and your EHR's ability to track minutes accurately. In my experience, the break-even point sits around 30 to 45 active CCM patients per full-time clinical coordinator, depending on your local reimbursement rates and overhead. Below that threshold, the administrative burden usually exceeds the revenue. Aetna also tends to have higher prior authorization and documentation request rates compared to Medicare or some commercial plans, which adds to the operational friction. Another limitation: Aetna does not allow combining CCM with care management codes like 99487 (the condition-specific one, not the CCM one) for the same patient in the same month. Some practices try to bill both for patients with complex needs, assuming the codes complement each other. They don't. Aetna will deny one or both and may flag the account for further review. Stick to CCM alone or switch to the appropriate disease-specific management code, but don't double-dip. If your practice is small, under twenty providers, and doesn't already have a dedicated care coordination function, you might be better served exploring Aetna's care management programs through their partnership networks rather than building an in-house CCM operation from scratch. They sometimes offer bundled support or reduced administrative requirements for smaller groups entering the space. The tradeoff is less control over scheduling and patient selection, but the startup cost and denial risk drop significantly.
The core issue with Aetna Chronic Care Management billing isn't complexity. It's consistency. The codes are straightforward. The documentation standards are public. What makes it difficult is maintaining the daily discipline of minute tracking, timely care plan creation, proper consent, and accurate staff attribution across an entire patient panel. Practices that treat CCM as a monthly billing event rather than a continuous operational workflow almost always end up with a high denial rate and burned-out staff. Start small, validate your tracking process with a dozen patients for two months before scaling, and keep your documentation timeline airtight. That's where the actual work lives.