What You Actually Need to Know About AAT Augmentation
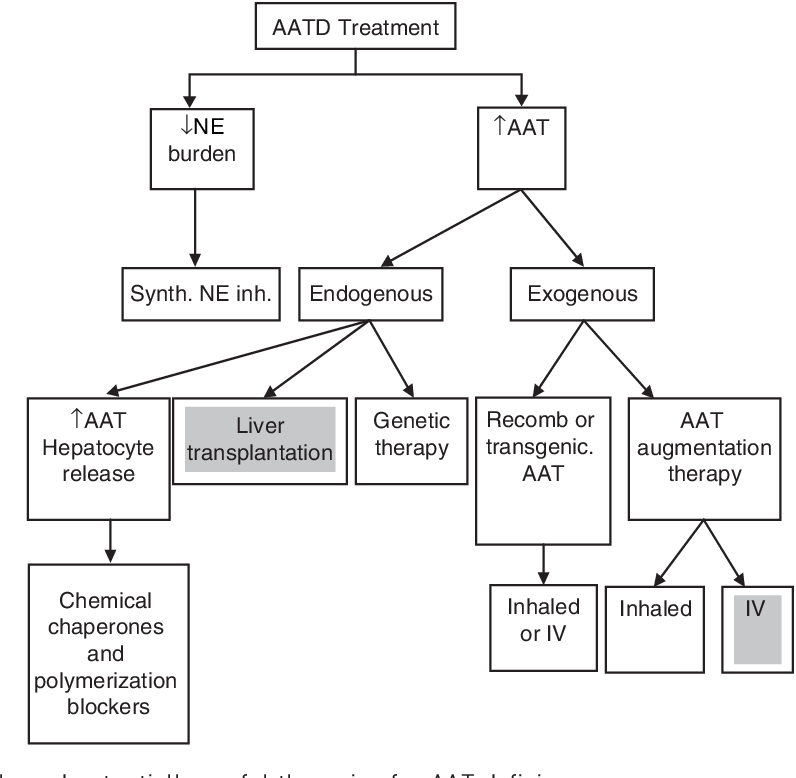
Most people coming into this therapy for the first time read the brochure version: you get weekly infusions, it slows lung damage, and everyone goes home happy. That version exists, but it leaves out the parts that actually matter when you are dealing with it day to day. Let me explain what I have seen over the years. Augmentation therapy means replacing the missing or dysfunctional alpha-1 antitrypsin protein through intravenous infusions of purified human alpha-1 antitrypsin concentrate. The two most commonly used products in the United States are Cryzaffinity and Pangendase, with some regions using other brands depending on availability. The standard dosing schedule is once weekly, typically between 60 milligrams per kilogram of body weight per week, split into either one larger session or divided across two days. Clinicians base the exact dose on local guidelines and insurance requirements more than anything else, which means the regimen can vary noticeably from patient to patient.Alpha 1 Antitrypsin Deficiency Augmentation Therapy in Practice
The actual experience of getting treatment is fairly mundane. You walk into a clinic or infusion center, the nurse starts an IV line, and you sit there for about two to three hours while the medication infuses. Most of those hours are uneventful. You bring a book. You scroll on your phone. You go home. The real complications usually happen in the moments before or after the infusion itself. One thing that catches people off guard is the reaction profile. I saw a patient recently who developed a mild but persistent fever and body aches after their second consecutive weekly dose. Their pharmacist adjusted the premedication protocol—adding acetaminophen and diphenhydramine about thirty minutes before the infusion instead of just relying on the standard approach—and the next round was clean. That kind of tweaking is straightforward once you know to ask for it, but first-timers often assume side effects are just something they have to endure silently. They do not need to do that. Another overlooked detail is IV access. AAT products have a specific viscosity and osmolarity that can be harder on peripheral veins than typical IV medications. I counseled a patient with fragile forearm veins to request a midline catheter rather than fighting with standard peripheral sticks every week. It reduced their infusion time significantly because the rate could run faster without phlebitis risk, and it cut down the number of failed sticks from three per visit to roughly one. Insurance approved it after we submitted a prior authorization citing recurrent phlebitis. Standard paperwork process.
How It Actually Works in the Body
The mechanism is simple enough on paper: alpha-1 antitrypsin is a protease inhibitor that neutralizes neutrophil elastase in the lungs. Without enough of it, elastase destroys alveolar walls unchecked, which is what causes the emphysema associated with AAT deficiency. The replacement therapy raises serum levels of the protein, buying time for the lungs. It does not regenerate tissue that is already gone. That distinction matters more than most patients understand going in. Clinical studies like the PRODEPI trial showed meaningful reductions in the annual rate of low-attenuation area measurements on CT scans. AAT deficiency augmentation therapy meaningfully slows progression when started early. Once emphysema is advanced, the benefit becomes much harder to quantify on an individual basis. That is not a criticism of the therapy—it is just the reality of pulmonary structural changes. Monitoring usually involves measuring trough AAT levels before each infusion to ensure the minimum concentration stays above 11 micromolar per liter, which is the generally accepted protective threshold. Some centers check peak levels too, but the trough is the one that drives clinical decisions about dose adjustments.
Common Pitfalls and Things the Literature Does Not Emphasize
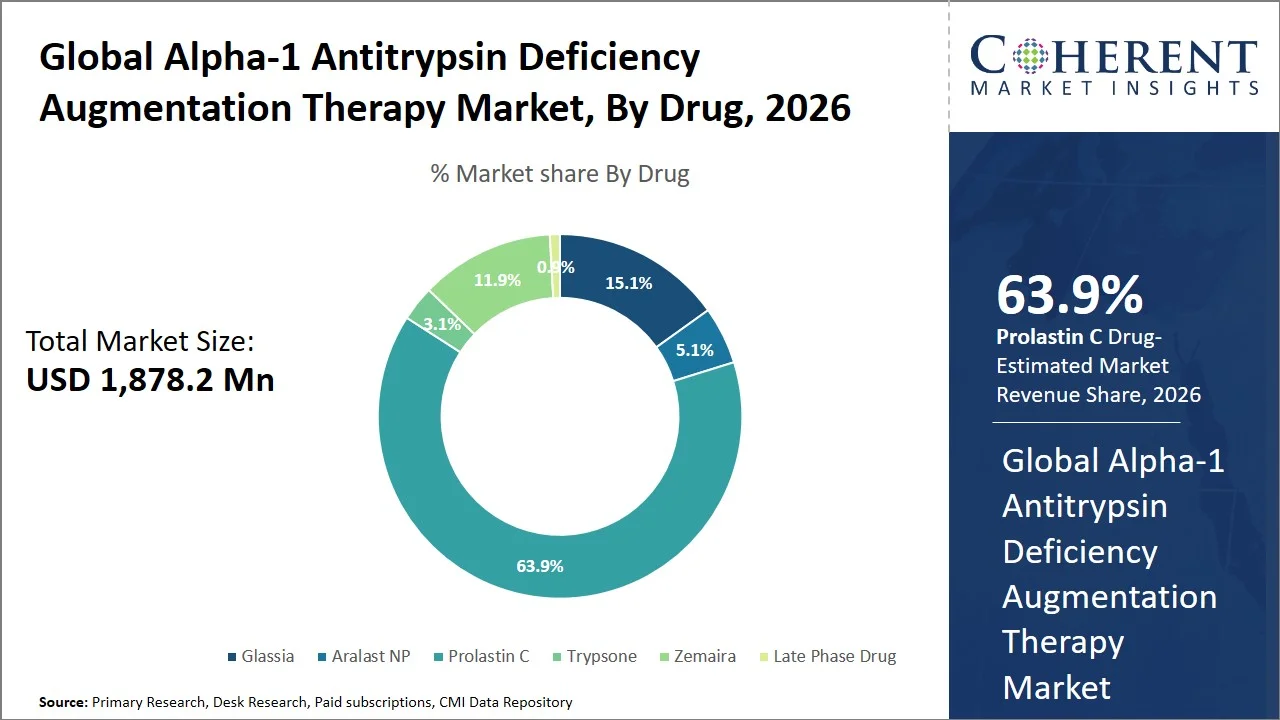
The first pitfall is assuming that augmentation therapy replaces the need to manage other factors. Stopping smoking remains the single most impactful intervention for someone with AAT deficiency who still smokes. No amount of weekly infusions fully compensates for continued inflammatory lung injury from cigarette smoke. Patients sometimes treat the therapy as a shield and feel permitted to keep smoking. It does not work that way. The second pitfall is the assumption that brand switching is automatic. The two main FDA-approved products are not interchangeable milligram for milligram in every insurance plan. Some payers require a trial of one product before approving the other. Switching also requires re-education for the patient on infusion site rotation and potential differences in reaction profiles. I had a case where a patient switched from one brand to another due to formulary changes and started experiencing more prominent headaches and chills. Reverting to the original product resolved the issue, but it took six weeks of prior authorization back-and-forth to get there. Documenting the prior reaction profile from day one helps speed that process if you ever need to switch again. A third practical issue is infusion logistics. The supply chain for AAT products has experienced intermittent shortages over the past few years. Some patients reported waiting two to three months for a shipment to be restocked at their local infusion center. Having a backup infusion site identified in advance, preferably at a different pharmacy network, is worth doing before you actually need it. You will forget to think about this when you are already behind on your dose schedule.
Get the Full Details

When Augmentation Is Not the Right Move
Liver disease associated with AAT deficiency does not respond to augmentation therapy in a meaningful way. The problem in the liver is accumulation of misfolded protein inside hepatocytes, not a systemic deficiency that infusions can correct. Patients with significant fibrosis or cirrhosis related to AAT should be managed by a hepatologist independently of their pulmonary care team. Augmentation will not slow liver disease progression. There are also rare but documented cases of anaphylaxis to AAT products, usually in patients who have very low baseline levels or who have developed inhibitory antibodies. This is uncommon but serious. Any patient with a history of severe allergic reaction to AAT concentrates should be managed in a setting equipped for anaphylaxis, not at a routine outpatient infusion center. Skin testing and graded challenge protocols exist for these situations, but they require specialized coordination. For advanced emphysema, lung transplantation or endobronchial valve placement may be more appropriate depending on anatomy and overall health status. Augmentation therapy is a disease-modifying treatment, not a substitute for surgical intervention when structural options exist. The decision should involve a multidisciplinary team including a pulmonologist, a transplant surgeon if applicable, and the infusion pharmacy team.
Practical Takeaways
Get your trough levels checked regularly and know what your target range is. Discuss premedication strategies upfront if you have ever had a reaction. Make sure you have a backup infusion location documented. Quit smoking if you smoke, regardless of how consistent you are with infusions. Keep records of every product lot number and any adverse events, because you will need them for prior authorizations and insurance appeals. Those details are easier to reconstruct from notes than from memory after the fact. The therapy works. It is not a cure, and it does not fix everything associated with AAT deficiency, but for the right patient at the right stage of disease, it changes the trajectory. The people who get the most out of it are the ones who treat it as one part of a broader management plan rather than the entire plan.