Understanding Pdpm and the MDS Assessment Process
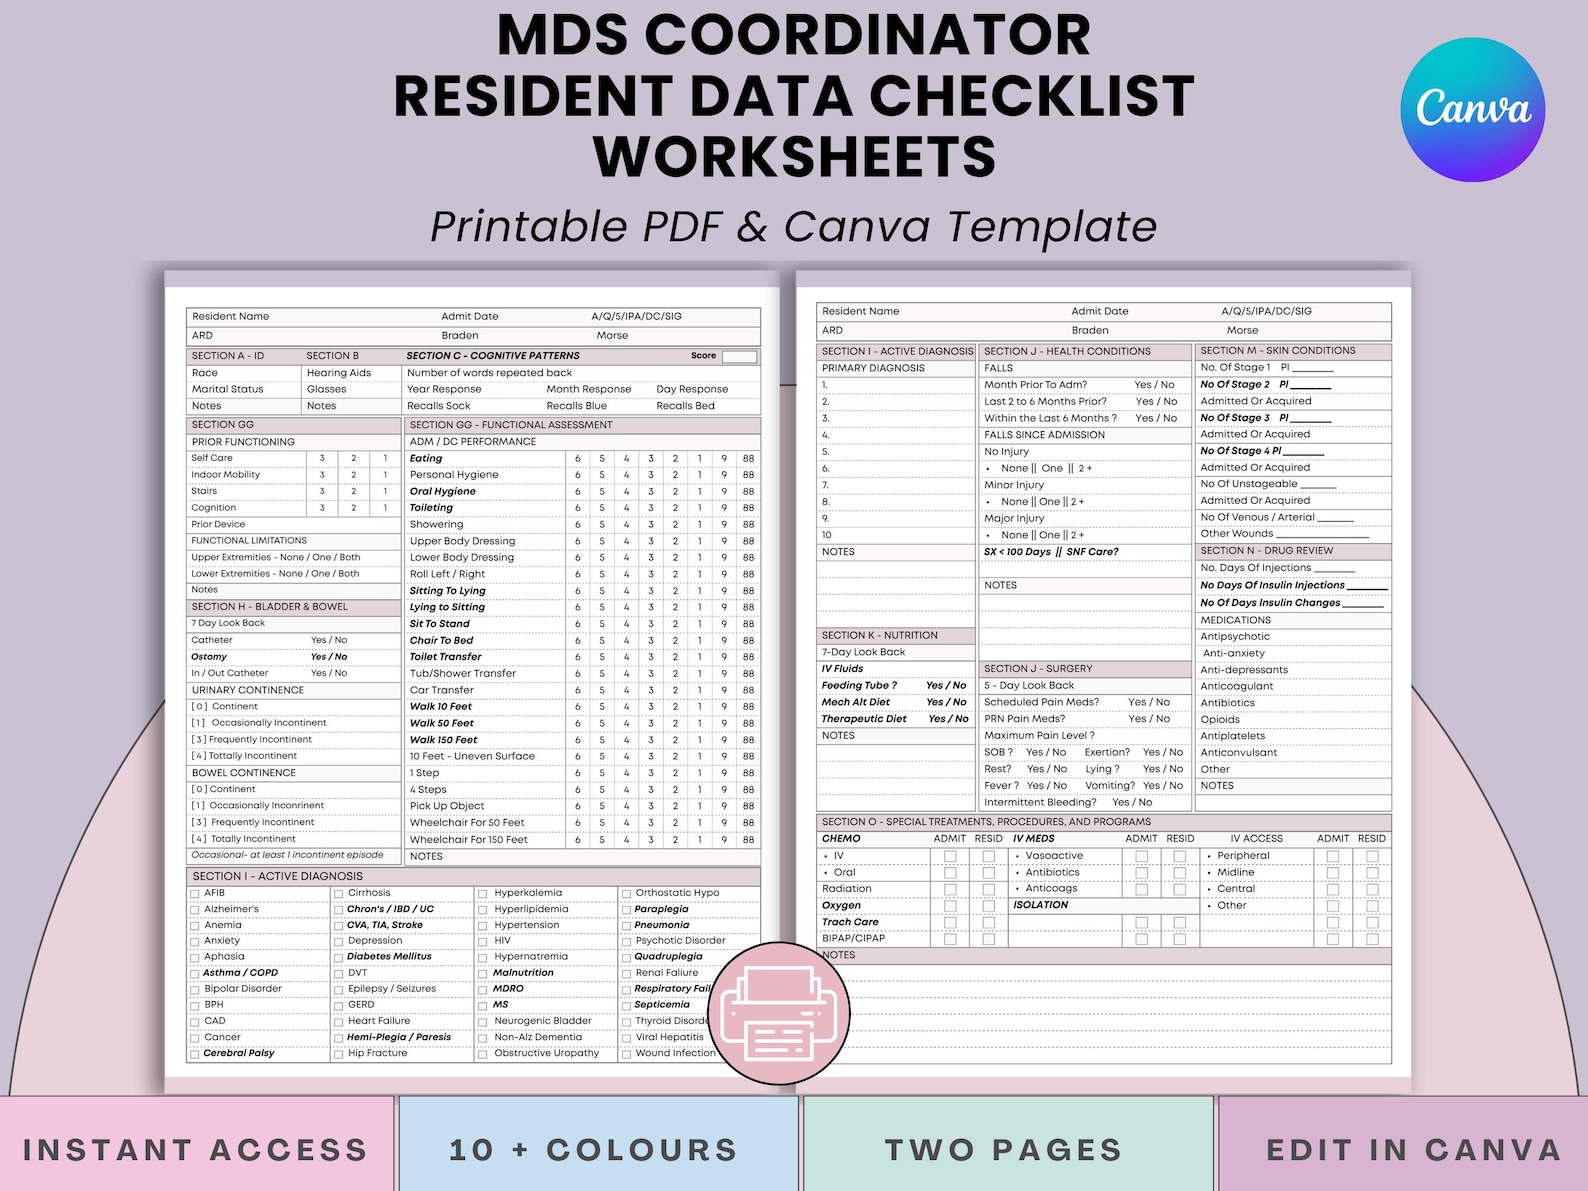
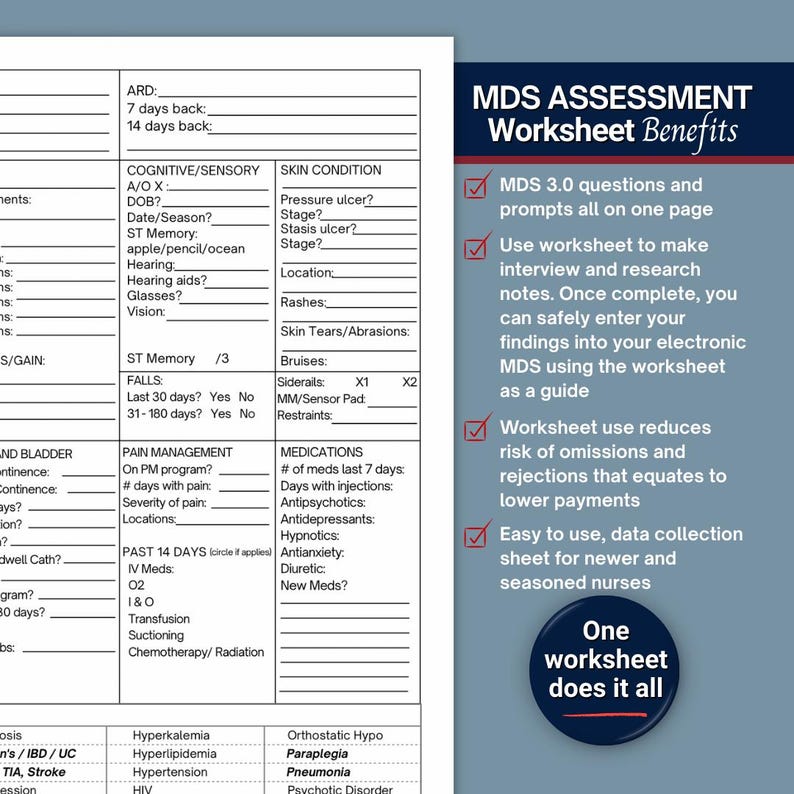
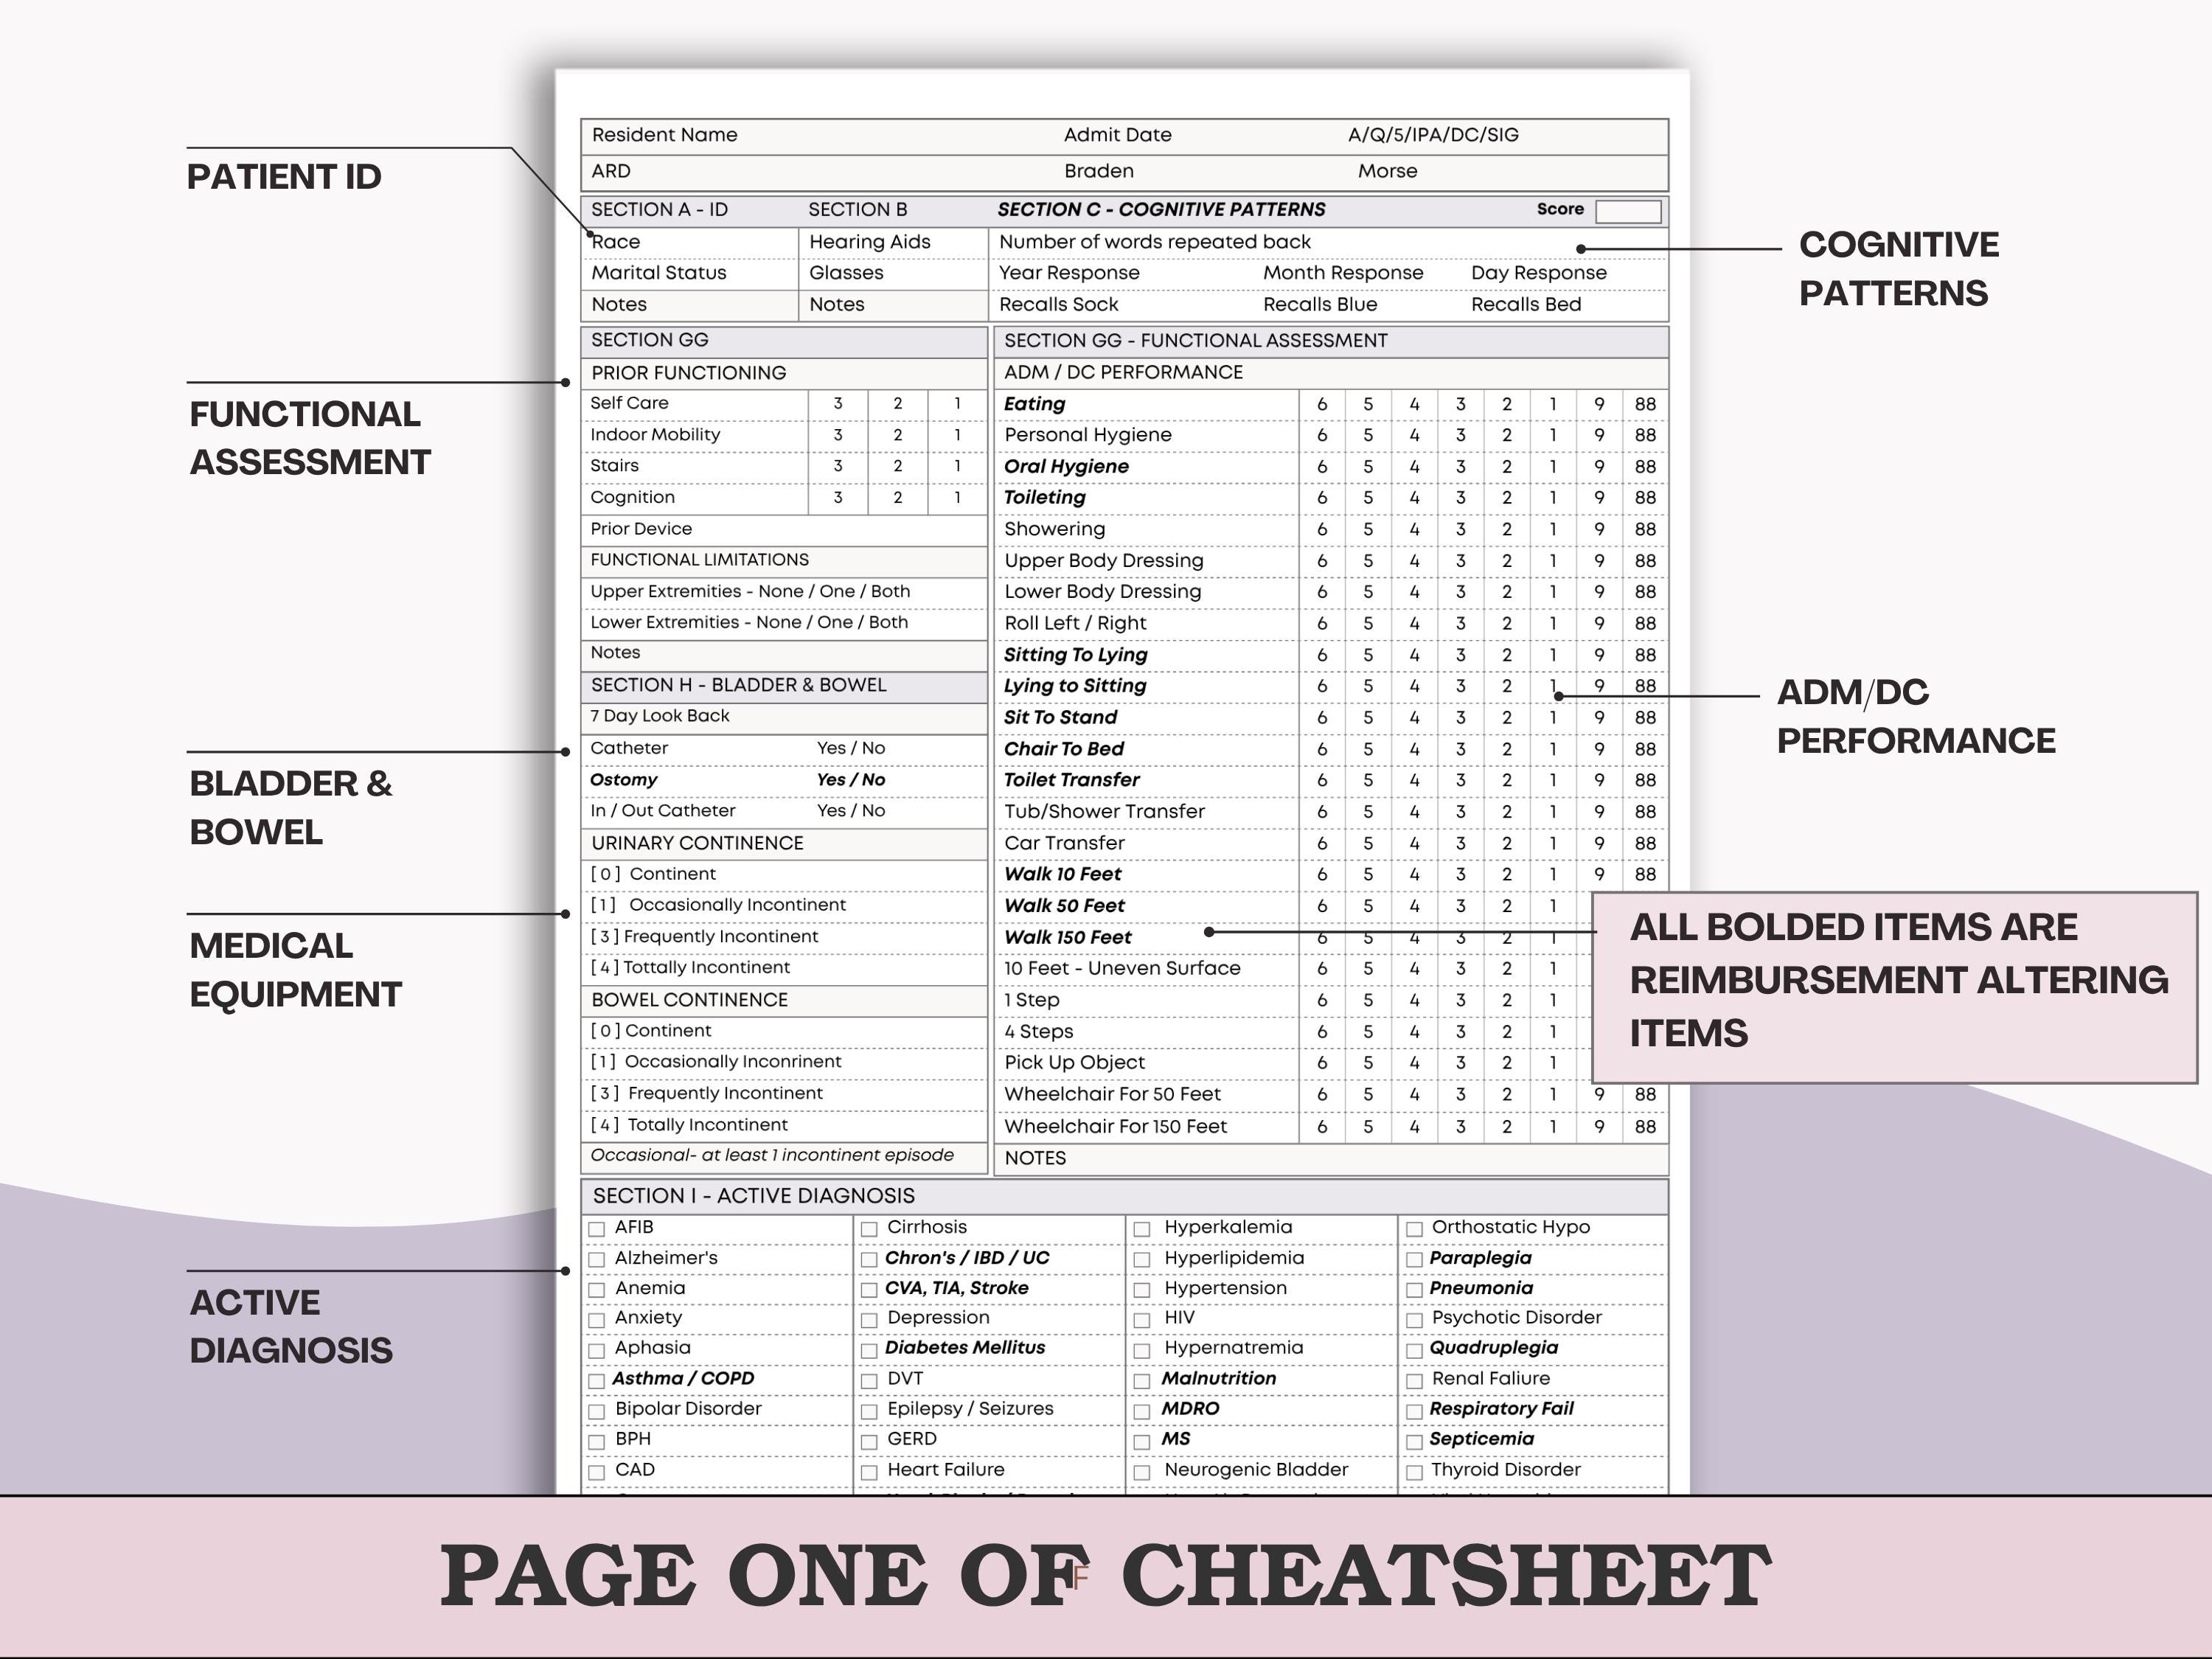
Pdpm stands for Patient Driven Payment Model. It replaced RUGs in November 2019 and fundamentally changed how Medicare reimburses skilled nursing facilities. Under Pdpm, payment is driven by clinical characteristics documented on the MDS rather than therapy minutes alone. The MDS 3.0 assessment instrument captures resident clinical information across multiple domains, and those data elements directly determine the payment category. A Pdpm Printable Mds Assessment Cheat Sheet is a condensed reference that maps MDS data elements to their corresponding Pdpm payment drivers. It typically shows which sections of the MDS feed into which Pdpm categories, highlights key decision points, and notes the timing rules for assessments. The most useful versions are organized by the seven Pdpm groups: nursing, therapy, SNB, OTR, SLP, ILD, and EAC. I have spent years building and refining assessment workflows, and the cheat sheets I see people actually using in practice tend to share certain features. They are not comprehensive textbooks. They are single-page or two-page references that a clinical reviewer can scan during an active assessment without getting lost in the manual. The best ones include trigger questions like whether the resident had a hospital stay within the lookback period, because that single question determines whether IPD or OPPD rules apply and completely changes the payment calculation.
Here is a practical reality that most cheat sheets gloss over. The lookback period under Pdpm is different from the lookback under RUGs. It runs 60 days prior to the assessment start date for hospital stays, not the assessment reference date. I ran into this exact issue when a facility I consulted for was submitting assessments with the wrong lookback window and the RRT-PCA wasn't aligning because the underlying hospital stay dates were being pulled from the wrong timeframe. The workaround was to pull the discharge dates directly from the hospital portal and cross-reference them against the MDS data submission date before opening the RUGS-to-Pdpm calculator. Takes about ten minutes and prevents a costly resubmission.
How the Cheat Sheet Actually Works in Practice
When you are building an assessment, the cheat sheet serves as a verification tool more than a learning tool. You fill in the MDS, run it through a Pdpm estimator, and then check your work against the reference. The critical fields to verify first are the comorbidity list, the therapy diagnoses, the cognitive pattern classification, and the functional level assignment. Those four areas drive the majority of payment variance between otherwise similar residents. The comorbidity section is where most errors creep in. The Pdpm model uses a specific list of clinically defined comorbidities from the MDS data elements, and not every diagnosis a resident carries qualifies. I once reviewed a batch where a facility was documenting type 2 diabetes for comorbidity purposes when the resident's coding actually reflected insulin-dependent diabetes, which falls under a different MDS item and does not trigger the same comorbidity adjustment. The fix was straightforward but required going back to the physician documentation and correcting the diabetes severity indicators before resubmitting. Another area that consistently causes problems is the therapy diagnosis grouping. Under Pdpm, not all therapy diagnoses are created equally. Only specific ICD-10 codes map to the therapy PDGs, and some common diagnoses like general muscle weakness do not qualify for separate therapy payment even though they appear frequently on therapy referral orders. If your cheat sheet does not include a crosswalk of qualifying ICD-10 codes to their Pdpm therapy groups, you will miss these edge cases repeatedly. I keep a separate reference document listing every code that maps to OTR, SLP, and PT/OT combined PDGs because the official manuals bury this information across multiple appendices.
Get the Full Details
Building Your Own Assessment Reference
Most printable cheat sheets available online are either too generic to be useful or overly complex with information that slows down a working reviewer. The approach that works best for me is building a custom one based on your facility's actual assessment volume and error patterns. Start by pulling your last twelve months of Pdpm estimates and MDS submissions. Identify the top three categories where your payment accuracy is lowest. Most facilities I have analyzed show their biggest variances in the nursing PDG and the ILD comorbidity section. Focus your cheat sheet on those problem areas first. Include the exact MDS item numbers, the lookback windows, and the decision trees that determine which comorbidities are counted. A well-built reference for just the nursing PDG alone can reduce assessment build time by roughly 40 percent because you are not flipping between multiple documents or guessing at coding rules. There are several free resources worth consulting. CMS publishes the Pdpm implementation guide, which contains the full comorbidity list and therapy diagnosis mappings. The State Operations Library also has surveyor guidance that explains how Medicaid and Medicare assessments interact during the concurrent review process. Some vendors offer printable versions, but they often include outdated thresholds since Pdpm adjustments occur annually. Always verify the fiscal year dates against the current CMS guidance before relying on a downloaded sheet.
Common Mistakes That Void Payment Accuracy
The assessment period start date is where everything can go wrong. If you select the wrong start date, every lookback calculation shifts and the entire payment estimate changes. I have seen facilities use the discharge date from a hospital stay that occurred outside the 60-day window and still apply it to the comorbidity section. That is not how the model works. The hospital must be within the lookback period relative to the assessment start date, not the MDS completion date or the discharge date of a prior admission. Another frequent error involves the therapy therapy diagnosis. Some facilities assume that any therapy diagnosis listed on the physician order automatically qualifies for the therapy PDG under Pdpm. It does not. Only diagnoses that appear in the MDS therapy diagnosis field and map to a qualified ICD-10 code count. Physical therapy and occupational therapy are grouped together for most payment calculations unless the resident meets the specific OTR criteria, which requires an orthopedic condition with related impairments. If you do not have that structure clearly outlined in your reference materials, you will misclassify a significant number of assessments. The cognitive pattern classification is the third area where small documentation gaps create large payment differences. MDS items C0100 through C0200 determine whether a resident is classified as minimal, mild, moderate, or severe cognitive impairment, and each level triggers different payment adjustments within the nursing PDG. A single missed question about cueing frequency for communication can shift a resident from moderate to severe and change the payment by several hundred dollars per month. Your cheat sheet should include the exact scoring thresholds for each cognitive pattern level so you are not relying on memory during a busy assessment period.
When a Cheat Sheet Is Not Enough
Printable references are useful for routine assessments, but they break down when you encounter complex residents with multiple hospitalizations, overlapping therapy diagnoses, or behavioral conditions that affect functional coding. In those situations, you need to consult the full Pdpm algorithm documentation or work with a certified coder who understands the nuances of the MDS-Pdpm crossover rules. I encountered a case where a resident had three hospital admissions within the lookback period, each with different primary diagnoses, and the standard cheat sheet provided only a simplified one-hospital-stay model. The payment calculation was wrong until I manually traced each admission through the full algorithm using the CMS reference guide. The honest limitation of any printable cheat sheet is that it cannot replace ongoing education. Pdpm guidelines are updated annually with new comorbidity additions, revised therapy classifications, and occasional modeling changes. A sheet printed in fiscal year 2023 may contain outdated thresholds for fiscal year 2025 and beyond. Check the publication date before relying on it, and always cross-reference the current year's CMS fee schedule notice for the official changes. If you are building a reference document for your team, I recommend starting with a blank template, populating it with the current year's comorbidity list and therapy code mappings, adding your facility's most frequent assessment error cases from the previous quarter, and printing it on a single sheet of paper in a format that fits in an assessment workstation drawer. Anything larger gets ignored. Anything smaller leaves out critical details and forces you to keep going back to the manual anyway.