How to Navigate the Ambulatory Referral To Physical Therapy Process Without Losing Your Mind
You need a referral to get a patient into physical therapy, or rather, you need the right kind of referral. This sounds straightforward until you hit the wall of insurance prior authorizations, varying state direct access laws, and the occasional physician who forgets they need to sign something specific for a chronic back pain case. I have spent enough years doing this to know the friction points, so let me walk you through what actually happens versus what the flowcharts say should happen. An ambulatory referral to physical therapy is simply a formal order from a qualified healthcare provider — typically a physician, physician assistant, or nurse practitioner — that authorizes a patient to receive outpatient physical therapy services. The ambulatory distinction matters because it separates this from inpatient or skilled nursing facility referrals. You are dealing with someone who walks in, gets treated, and walks out. That sounds simple. It is not always simple depending on where the patient lives and what their insurance plan looks like. The actual process starts with identifying whether your state has direct access laws and how far they go. Some states allow physical therapists to evaluate and treat patients without any referral at all. Others require a referral within a set number of days — 10 days, 30 days, sometimes longer. I worked with a clinic in a state with a 30-day referral window once where we got burned. We started treatment based on direct access, built out a solid plan of care, and then the patient could not produce a referral before the 30-day mark because their primary care physician had moved out of network and could not be reached. The insurance denied the entire episode. We ate the cost on about twelve active cases. After that, we changed our workflow. Now we verify referral status before the first session, not after.
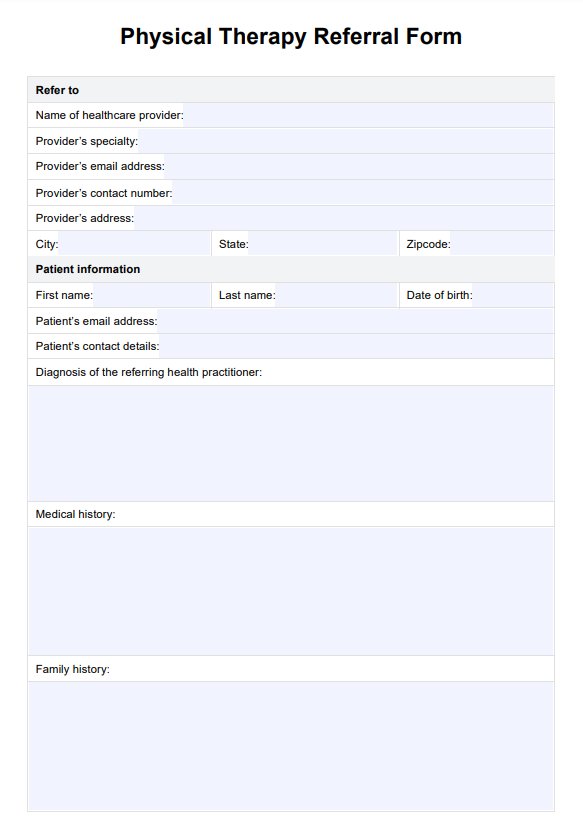
Here is what the referral itself needs to contain, and this is where people slip up. You need a date of service, the diagnosis with the appropriate ICD-10 code, the number of visits authorized, the specific type of therapy services — physical therapy, occupational therapy, or speech-language pathology depending on what applies — and the prescribing provider's signature. Some payers also require the provider's NPI number and sometimes a attestation that the patient is under their care. Missing any of those elements will cause a denial, and denials stack up fast when you are processing twenty referrals a week.
Handling Ambulatory Referral To Physical Therapy Documentation Correctly
Getting the referral onto paper is only half the battle. You need to verify it. And I do not mean flipping through an email and nodding. I mean calling the payer or using their online portal to confirm that the referral is active, that the diagnosis codes match what you have on file, and that the visit authorization covers the timeframe you are planning. A lot of clinics skip this step. They take the referral at face value and then spend three weeks fighting a denial that could have been caught in five minutes. There is also a nuance with concurrent conditions. Say your patient has both a lumbar strain and a post-surgical knee condition. The referring physician might only have the lumbar issue on the referral form. If you treat the knee and the payer sees a diagnosis code that is not on the referral, they will deny that portion. I learned this the hard way when a sports medicine physician referred a patient for shoulder issues but only listed rotator cuff tendinopathy. The patient also had a labral tear that was surgical but not yet operated on. We coded it as we saw clinically, the claim came back with a missing referral diagnosis, and we had to go back to the physician for an amended order. That added two weeks to the patient's treatment timeline. Now I ask referring providers upfront to list every diagnosis that might come up during the episode of care, not just the primary one. Another thing nobody really talks about is the difference between a referral and an authorization. They are not the same thing. A referral comes from the provider. An authorization comes from the insurance company. You can have both, one, or neither depending on the payer and the state. Some insurance plans require their own authorization even when the physician has written a proper referral. I have seen PT offices get turned away because they assumed the referral was enough. It is not. Always check with the payer separately.
Get the Full Details

For the actual submission side, most referrals today go through electronic channels. Some payers have their own referral management platforms, others use clearinghouses, and some small regional plans still want faxed or mailed paperwork. This inconsistency is a real pain point. I recommend building a quick-reference matrix for every payer you work with that lists their preferred referral method, turnaround time, and any special documentation requirements. It takes about an afternoon to compile and will save you hours of phone tag over the following months. One more edge case that catches people off guard. When a patient transitions from acute care to an outpatient setting, the referral source changes. A hospitalist or attending physician may have initiated something, but the ambulatory referral needs to come from the outpatient provider who is managing the patient's ongoing care. I had a case where a patient was discharged from the hospital with a recommendation for PT but no formal outpatient referral. The hospital's order was not accepted by the outpatient clinic's billing system because it lacked the proper ambulatory encounter reference. The patient was stuck for nearly a week while we sorted it out. The fix was to have the patient's new PCP issue a clean ambulatory referral referencing the hospital discharge summary as supporting documentation. That satisfied both the clinical and billing requirements. If you are setting this up from scratch and need a template or a tracking spreadsheet to manage referrals across multiple payers, I use a basic Google Sheets tracker that flags expiring authorizations thirty days out and color-codes referrals by verification status. It is nothing fancy. Free templates exist online if you search for "physical therapy referral tracking spreadsheet." The structure is simple: patient name, referral date, prescribing provider, diagnosis codes, authorized visits, expiration date, verification status, and payer contact notes. The best ones I have seen include a column for direct access eligibility by state, which helps when patients move or when you have a multi-state practice.
The bottom line here is that ambulatory referral to physical therapy is less about the paperwork itself and more about understanding the ecosystem around it. The referral is just one piece. Insurance rules, state laws, payer quirks, and clinical documentation all intersect. If you treat it like a simple checkbox, you will get hit with denials and delays. If you build systems around verification and proactive communication with referring providers, the whole process becomes routine instead of a constant fire drill.
.png "Physical Therapy Referral Form & Template | Free PDF Download")



