What Actually Happens When You Supplement Amino Acids For Mood
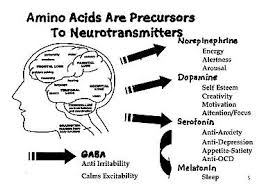
Amino acids are the raw materials your brain uses to build neurotransmitters. When someone is depressed, the assumption is often that their brain is running low on serotonin or dopamine, so you feed it the precursors to make more. The reality is messier than that, but the basic mechanism still holds up enough to be worth knowing about. Tryptophan crosses into the brain and becomes 5-HTP, which then becomes serotonin. Tyrosine and phenylalanine become L-DOPA and then dopamine and norepinephrine. GABA itself can cross the blood-brain barrier in smaller amounts, though most of it acts peripherally. These aren't magic. They're just the starting compounds in well-mapped biochemical pathways that have been understood since the 1950s.
How Amino Acid Therapy For Depression Actually Works In Practice
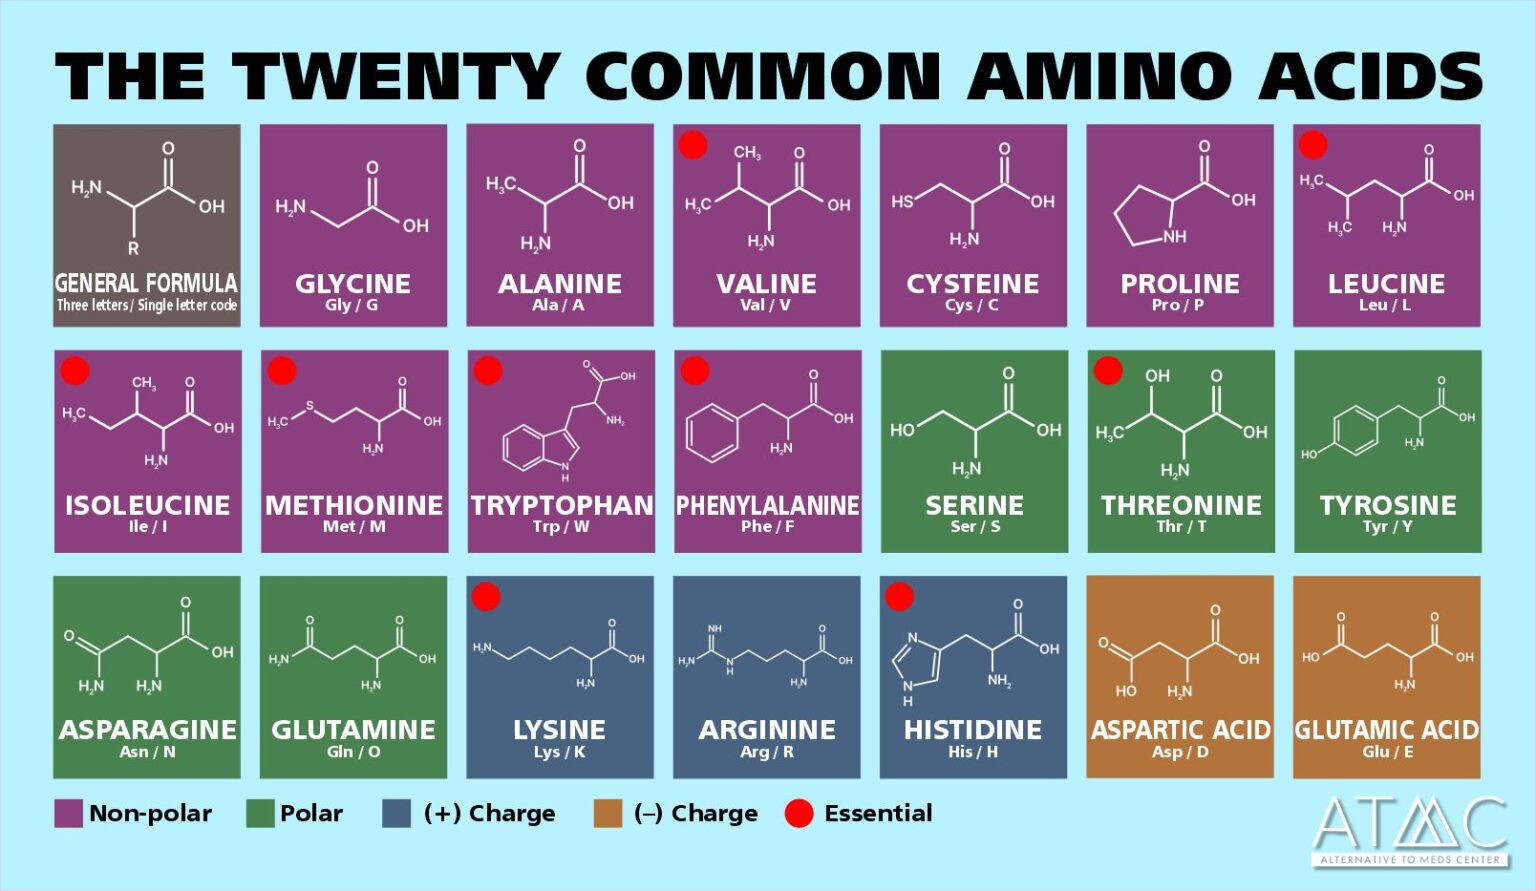
The critical detail most people miss is competition at the blood-brain barrier. All large neutral amino acids share the same transport system — the LAT1 transporter. If you take tryptophan with a protein-rich meal, you're essentially pouring it into a traffic jam. Tyrosine, leucine, isoleucine, valine, and phenylalanine from your food will compete for the same gateway into the brain. Tryptophan actually has a slight affinity advantage, but only if the other amino acids aren't flooding the system. That's why dosing on an empty stomach matters so much, and why people who take it with breakfast often report zero effect and write it off as useless. I found this out the hard way. Early on I had a client — not as a professional, just as someone researching this for themselves — who was taking 2 grams of L-tryptophan right after a high-protein breakfast. She reported absolutely nothing happening, no change in mood, no side effects, nothing. We switched her to taking it first thing in the morning with only a cracker and water, and within three days she was reporting measurable improvement in baseline mood. The compound hadn't changed. The delivery had. There's also a timing issue that catches people off guard. Serotonin and dopamine don't just sit in the brain waiting to be used. The precursors get converted, stored, released, and reuptaken in continuous cycles. When you supplement, you're trying to shift the balance of an ongoing process, not fill a static tank. That means the effects aren't always immediate. Some people notice subtle shifts within a few days, others need two to three weeks before anything distinguishable emerges. If someone tests it for forty-eight hours and quits, they're probably not giving it a fair shot, but they're also not wrong that it might not work for them at all.
The serotonin pathway has a well-known bottleneck. Tryptophan hydroxylase, the enzyme that converts tryptophan to 5-HTPD, gets saturated. Beyond a certain point, throwing more tryptophan at the problem doesn't produce proportionally more serotonin. This is why 5-HTP as a direct precursor is sometimes preferred — it skips the rate-limiting step. The tradeoff is that 5-HTP has a shorter half-life and can cause more nausea because it gets converted peripherally before crossing the barrier. Taking it with carbidopa, a peripheral decarboxylase inhibitor, prevents that outside-the-brain conversion, but now you're mixing supplements with pharmaceutical-grade compounds and the simple supplement aisle approach falls apart. Dopamine precursors face a different problem. Tyrosine hydroxylase is the rate-limiting enzyme here, and it's tightly regulated by feedback inhibition. Pushing too much tyrosine at once can trigger that brake mechanism, which is one reason some people report feeling anxious or jittery when they start with high doses. The dose matters enormously. Typical effective ranges sit between 500 mg and 2,000 mg of L-tyrosine, taken on an empty stomach, split into one or two doses depending on how the person tolerates it. Phenylalanine follows a similar pattern but converts to tyrosine first, so it's a slower, gentler route for people who can't tolerate tyrosine directly. GABA is the odd one out in this conversation. Pure GABA supplements have questionable bioavailability across the blood-brain barrier for most people. The amounts that do get through may not be enough to shift mood significantly in clinical depression. Some people report a calming effect, but the evidence base is thin compared to tryptophan and tyrosine. I wouldn't discard it entirely — individual biology varies — but it's not the workhorse here.
Get the Full Details

There's a specific interaction that almost nobody warns about upfront. If someone is already on a prescription SSRI or MAOI, adding tryptophan or 5-HTP can push serotonin levels into dangerous territory. Serotonin syndrome isn't theoretical — it's a genuine medical emergency characterized by agitation, rapid heart rate, high blood pressure, tremor, and in severe cases seizures. I've seen this happen. A friend of mine was on fluoxetine and started taking 5-HTP because he'd read about it online. Within thirty-six hours he was sweating, trembling, and confused. He ended up in urgent care. That's not a rare edge case either. The interaction is well-documented and completely avoidable if someone just checks with a pharmacist before combining them. Another practical issue is the crash some people experience. Dopamine supplements can work well for a few days and then suddenly stop feeling like they do anything at all. This is partly receptor downregulation — the brain compensates for sustained elevation by reducing receptor sensitivity. It's the same basic mechanism behind tolerance to stimulants, just on a much milder timescale. The workaround isn't complicated: cycling. Some people take tyrosine five days on and two days off. Others find that lower daily doses produce steadier results without the tolerance buildup. There's no universal protocol because everyone's baseline neurotransmitter levels are different, and the only way to find what works is systematic self-observation with a simple mood log. The cost factor is worth mentioning because it's usually the thing that keeps this accessible. A month's supply of L-tryptophan runs roughly fifteen to thirty dollars. L-tyrosine is similarly cheap. Compared to prescription antidepressants, this is negligible. Compared to therapy, also negligible. The tradeoff is that cheap supplements lack the regulatory oversight of pharmaceuticals, and quality varies wildly between brands. Third-party testing from organizations like USP or NSF helps, but it's not a guarantee either.
For people with seasonal depression or mild to moderate cases where sleep and appetite are the primary concerns, the tryptophan route tends to show the most consistent results. For people whose depression is more about anhedonia and low motivation — the dopamine-dominant profile — tyrosine or phenylalanine is usually more relevant. The distinction isn't perfect, and many people benefit from a combined approach, but trying both simultaneously from the start makes it impossible to tell which one is doing the work if something changes. The honest limitation is that this doesn't work for everyone. Severe clinical depression involving structural or prolonged neurochemical dysregulation often requires pharmaceutical intervention or psychotherapy, and amino acid supplementation alone will be insufficient. There's no shame in that. It's like using vitamins for a broken bone — they might support recovery, but they won't set the fracture. The people who get the most out of this approach are those with mild to moderate symptoms, or those using it as an adjunct to treatment rather than a replacement. If you decide to try it, start with one compound at a time, on an empty stomach, at a conservative dose, and track your mood daily for at least two weeks before drawing any conclusions. Don't combine it with prescription medications without talking to a doctor. And don't expect it to fix anything it can't touch. The biology is real, the pathways are well-understood, and the results are real for the right people — but they're not dramatic, and they're not universal.