What You Actually Need to Know About Female Abdominal Anatomy
The abdomen isn't a simple box with organs jammed inside. The female abdominal cavity has structural differences from the male version that matter when you're reading imaging, doing surgery, or even just trying to understand a patient's symptoms. Most people skip over these details because textbooks group them together, but the distinctions show up constantly in practice. Layer by layer, the anterior abdominal wall is the same basic recipe: skin, subcutaneous fat (Camper's and Scarpa's fascia), the rectus sheath, the transversalis fascia, extraperitoneal fat, and the peritoneum. But in women, the subcutaneous fat layer tends to be substantially thicker, especially in the suprapubic region. That changes everything about palpation, surgical incisions, and ultrasound penetration. I once had a resident try to palpate the ovaries on a patient with a BMI around 28 and basically give up after ten minutes. A transvaginal ultrasound took three minutes and showed exactly what was going on. Don't underestimate how much soft tissue absorbs your diagnostic effort.
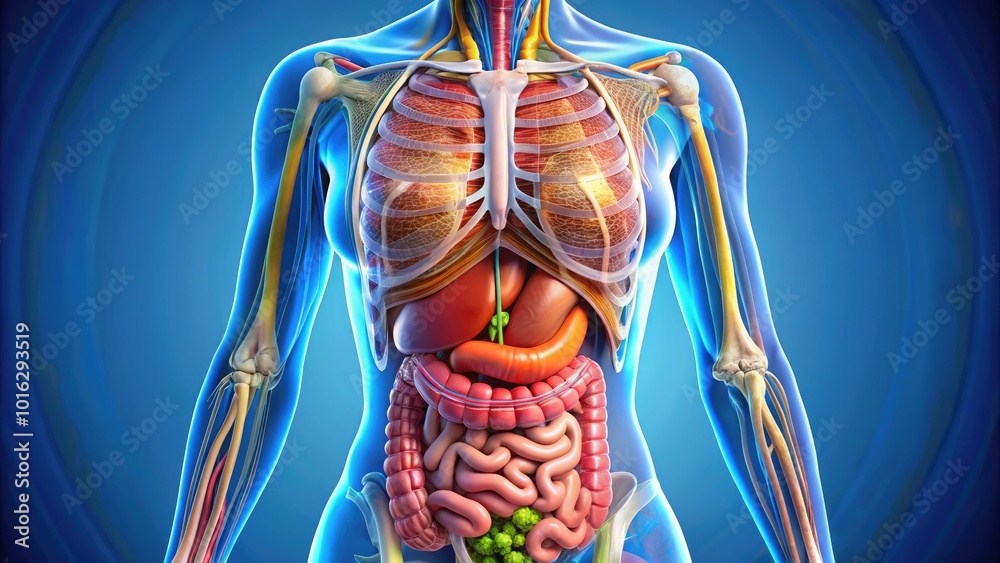
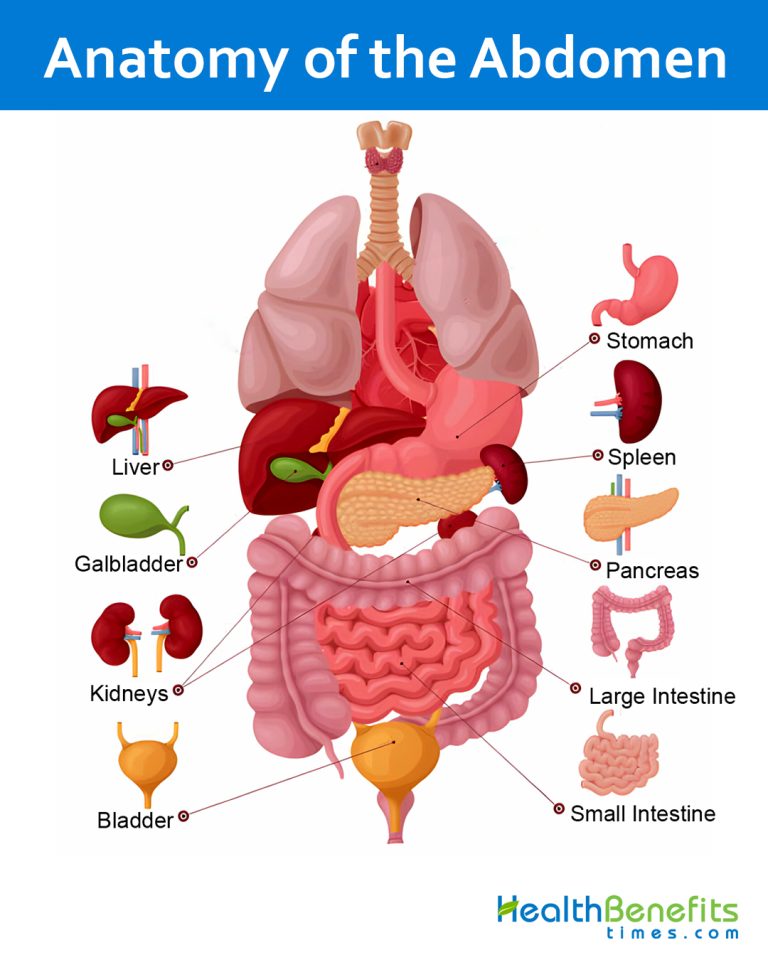
Anatomy Of Abdomen Woman
The Peritoneal Cavity and Space Allocation
In women, the peritoneal cavity is essentially open to the outside world through the reproductive tract. The uterine tubes, uterus, and vagina create a continuous pathway from the peritoneal cavity to the vaginal introitus. This anatomical fact is why pelvic inflammatory disease can become a serious problem and why free fluid in the pelvis on ultrasound is such a common finding. The pouch of Douglas (rectouterine pouch) is the most dependent part of the peritoneal cavity in a standing or supine woman, which means blood, pus, or ascitic fluid collects there first. I've seen this misread on CT scans more times than I care to admit. People forget that fluid tracks downward and pool in the cul-de-sac before showing up anywhere else. The broad ligament, mesosalpinx, mesovarium, and mesometrium are folds of peritoneum that suspend the uterus, tubes, and ovaries. They're not just decorative. These structures contain blood vessels, lymphatics, and nerves that surgeons need to identify and preserve. The uterine artery runs above the ureter through the base of the broad ligament — the classic "water under the bridge" relationship. During a hysterectomy, clamping the uterine artery without identifying the ureter first is one of the most common surgical errors I've encountered in case reviews. The ureter is right there, running medially along the lateral pelvic wall, and it's easy to mistake for a vessel or ligament if you're not paying attention.
Blood Supply and Venous Drainage
The ovarian arteries arise directly from the abdominal aorta, just below the renal arteries. They travel through the infundibulopelvic ligament to reach the ovaries. The uterine arteries come from the internal iliac system. This dual blood supply to the uterus is clinically important because collateral circulation between the ovarian and uterine arteries can maintain uterine viability even if one source is compromised. That's relevant during complex pelvic surgeries and in cases of vascular occlusive disease. The venous drainage mirrors the arterial supply but with a practical difference worth noting. The left ovarian vein drains into the left renal vein, while the right ovarian vein drains directly into the inferior vena cava. This asymmetry matters for understanding the spread of pathology and for interventional radiology procedures. I had a case where a patient presented with left-sided flank pain and the workup revealed a renal vein compression syndrome compounded by ovarian vein varicosities. The anatomy explained everything once you connected the dots.
Get the Full Details

Lymphatic Drainage Patterns
Ovarian lymphatics follow the ovarian vessels retroperitoneally to the lumbar (aortic) lymph nodes. Uterine body lymphatics drain primarily to the external iliac nodes, with some drainage to the para-aortic nodes through the round ligament. The cervix drains to the internal iliac and sacral nodes. These pathways determine where metastatic disease shows up first and guide surgical staging decisions. When you're evaluating a gynecologic malignancy, the lymph node mapping isn't theoretical — it directly affects whether you're doing a pelvic exenteration or a targeted resection. The abdominal wall innervation comes from the lower six thoracic nerve roots (T7-T12) and the first lumbar nerve (L1) via the iliohypogastric and ilioinguinal nerves. These nerves supply the skin, muscles, and parietal peritoneum. Pain referral patterns here are predictable but often misinterpreted. Appendicitis starts as visceral pain around the umbilicus (T10 dermatome) before localizing to the right lower quadrant. Shingles in the T10-T12 distribution can mimic acute abdominal pathology. I've seen both present as emergency visits where the initial diagnosis was completely wrong. The pelvic viscera receive autonomic innervation from the sympathetic and parasympathetic systems. Sympathetic fibers from T10-L1 travel through the hypogastric plexus to the pelvic organs. Parasympathetic input comes from S2-S4 via the pelvic splanchnic nerves. Visceral pain from the uterus and ovaries follows the sympathetic pathways back to the spinal cord, which is why uterine cramping refers to the T10-L1 dermatomal distribution in the lower abdomen and back. This isn't academic — it's why epidural analgesia at the T10-L1 level is effective for labor and why certain neuropathic conditions cause what feels like abdominal pain when the actual pathology is elsewhere.
Common Variations and Anatomical Pitfalls
Müllerian duct anomalies are more common than most clinicians encounter in general practice. A bicornuate uterus, septate uterus, or unicornuate uterus changes the spatial relationships of pelvic structures and complicates both imaging interpretation and surgical planning. I spent two hours on a laparoscopy trying to figure out why the uterine artery wasn't where it should be. Turned out the patient had a rudimentary horn on the left side with its own vascular supply entering from a completely different direction. Preoperative MRI would have saved the entire operating time. Ovarian position varies significantly between individuals. While textbooks show the ovaries in the ovarian fossa against the lateral pelvic wall, they can migrate superiorly into the paracolic gutter, especially after pregnancy or in cases of ovarian enlargement. On abdominal CT, I've found ovary masses mistaken for kidney pathology because the organ had shifted out of the pelvis entirely. Always trace the infundibulopelvic ligament back to its origin to confirm you're looking at the right structure.
Imaging Approaches and Practical Considerations
Ultrasound remains the first-line imaging modality for female abdominal and pelvic evaluation. Transabdominal ultrasound requires a full bladder to serve as an acoustic window, pushing the bowel loops out of the way and allowing visualization of the uterus and adnexa. Transvaginal ultrasound provides higher resolution imaging of the endometrium, ovarian follicles, and early pregnancy structures but has a limited field of view. Using both approaches in sequence usually takes about 20 minutes and provides complementary information that neither method can deliver alone. CT imaging of the female abdomen and pelvis requires attention to protocol. Contrast-enhanced studies with both intravenous and oral contrast give the best anatomical detail, but the radiation dose is significant, especially for younger patients. MRI avoids ionizing radiation entirely and provides superior soft tissue contrast for evaluating uterine pathology, ovarian masses, and deep infiltrating endometriosis. A dedicated pelvic MRI protocol typically takes 30 to 45 minutes and costs considerably more than CT, but it's the right choice when you need to distinguish between adenomyosis and leiomyomas or assess the depth of endometrial invasion in suspected malignancy.

What Most People Get Wrong
The most persistent misconception is that the female reproductive organs are "inside" the abdominal cavity in the same way the liver or spleen are. Most of the uterus, fallopian tubes, and ovaries are actually in the true pelvis, below the level of the ileal brim. Only the fundus of the uterus and the superior portions of the tubes extend into the abdominal cavity proper. This anatomical distinction affects everything from where you make an incision to how you interpret referred pain patterns. A mass originating in the ovary might not cause abdominal symptoms until it grows large enough to herniate through the pelvic brim and irritate the parietal peritoneum. Another frequent error is assuming that the peritoneal reflections are symmetric. The broad ligament creates a complex three-dimensional arrangement that isn't mirrored perfectly on each side. The right ovary often sits slightly lower than the left because the ascending colon occupies space on the left side. Surgical and imaging interpretations that assume perfect symmetry miss real pathology about as often as you'd expect.