Understanding The Front Teeth You Clean Every Day
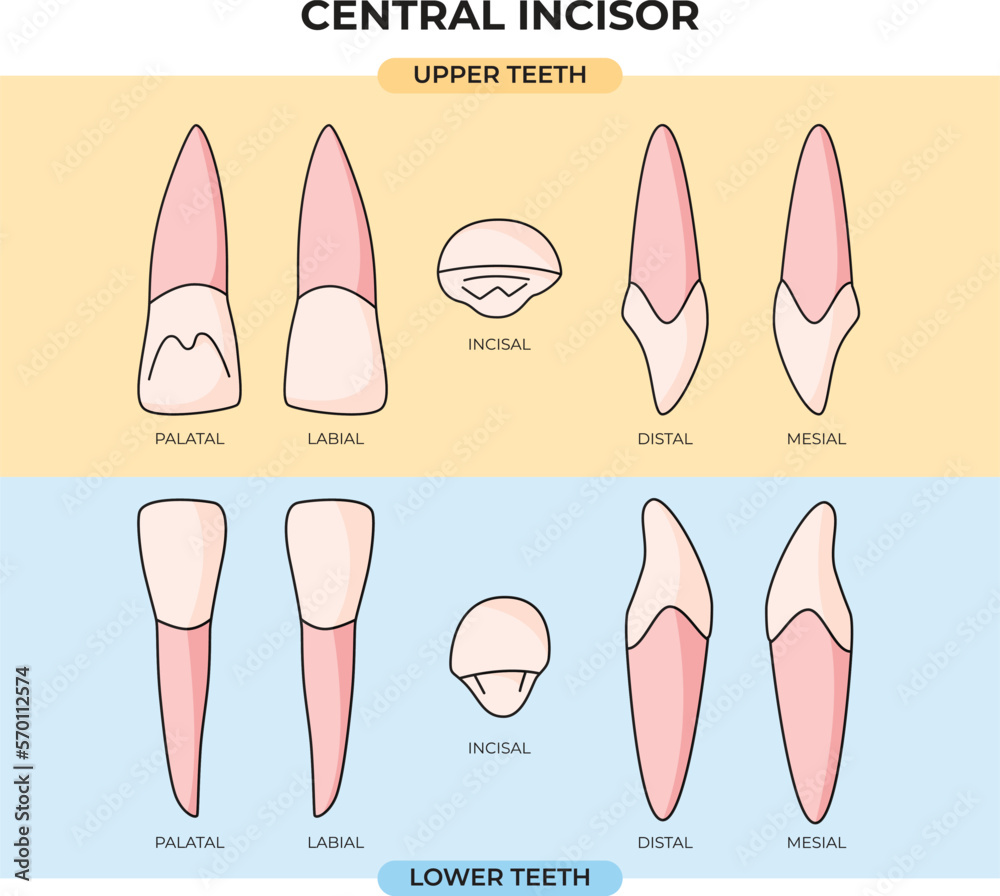
Most people don't actually look closely at their incisors until something goes wrong with them. The central incisors are the two teeth right in the middle of your upper or lower jaw, and they have a very specific set of features that matter when you're studying them for a restorative procedure, a forensic identification, or just trying to understand why your floss keeps getting stuck in weird places.Anatomy Of Central Incisor
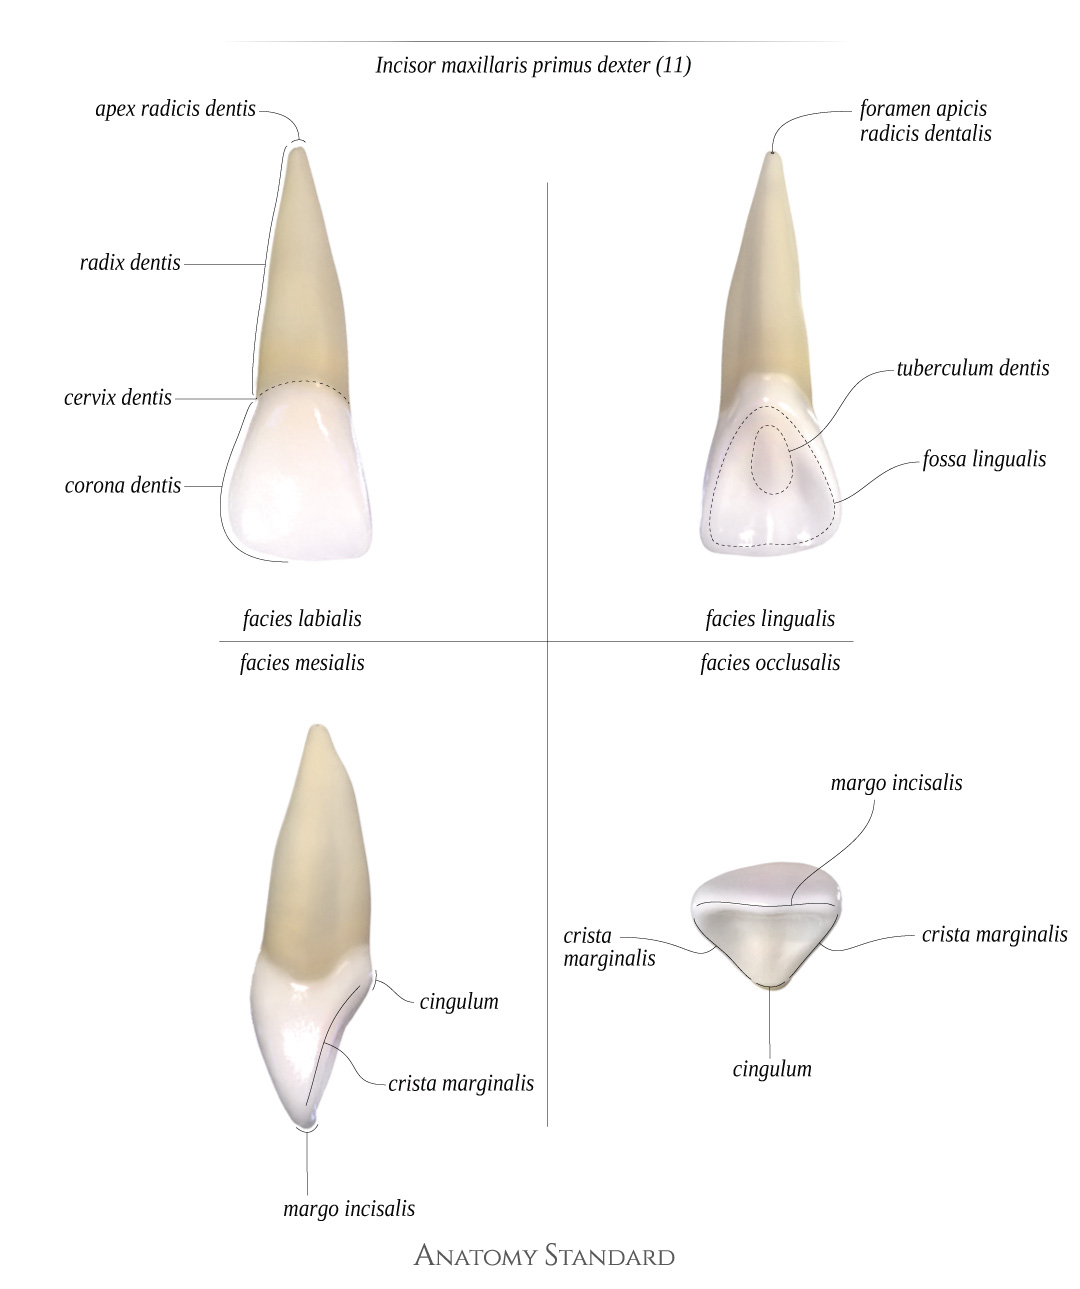
The maxillary central incisor is the largest tooth in the permanent dentition, and it dominates the smile line because it sits front and center. It has a single rooted structure, meaning there's one root going into the bone, usually about 13 millimeters in length while the clinical crown—the part you can actually see—ranges from 10 to 11 millimeters. The crown itself is broadly trapezoidal when viewed from the facial side, with the mesial outline being relatively straight and the distal outline showing a more pronounced curve from the contact area down to the cervical line. Look at the incisal edge and you will notice it is not a straight horizontal line like a chisel. It crosses the long axis of the tooth at a slight angle, with the mesioincisal angle being sharply defined and the distoincisal angle being noticeably more rounded. This asymmetry matters a lot if you are carving a wax pattern or prepping a crown margin. I learned that the hard way when I spent three hours troubleshooting why a laminate veneer on a maxillary central kept looking off-center under different lighting angles, only to realize I had symmetrized the proximal contours instead of preserving the natural mesial-distal disproportion. The lingual surface has a concavity called the cingulum area, and around it runs the marginal ridges that form the boundaries of the lingual fossa. The depth of that fossa varies significantly between individuals, and in some cases it can be extremely shallow, almost flat, while in others it forms a deep scoop-like depression that collects plaque if you are not meticulous about brushing technique. The cervical cross-section of a maxillary central incisor is roughly triangular with rounded corners, which is different from the mandibular counterpart where the cross-section is more oval or ovoid.
Practical Details That Come Up In Real Work
The labial surface is smooth with subtle vertical grooves that run from the cervical third toward the incisal edge. These are called developmental lobes and you can typically count five of them on a well-formed central incisor. The junctions between these lobes create faint vertical lines that become more pronounced with age and attrition. When you are doing a clinical examination and you want to assess the health of the enamel surface, those lines are important landmarks because early caries tends to initiate in the developmental grooves rather than on the smooth inter-lobar surfaces. Mesial contact area sits at the junction of the incisal and middle thirds when viewed from the facial, while the distal contact area is positioned slightly more cervically, usually at the level of the middle third. This difference in contact height is something you need to account for when placing matrix bands during Class V restorations, because if you get the contour wrong on the distal side the overhang will be a persistent irritant to the gingiva. I had a case where a student dentist kept having patients complain about gum soreness around tooth 11, and after reviewing the radiographs we found a tiny distal overhang from a composite build-up that had been placed months earlier without proper matrix adaptation. The root is conical and tapers toward the apex, which is curved slightly toward the distal. This apical curvature is clinically relevant during endodontic procedures because you have to account for it when determining working length. A file that appears to be at the correct length on the radiograph may actually be short of the true apical terminus if the root curves distally beyond what the two-dimensional image shows. The typical root length is 13 to 14 millimeters and the cervical pulp chamber is roughly triangular in cross-section, narrowing as you move apically into the single root canal.
When you measure the mesiodistal width of a maxillary central incisor at the contact area, it averages around 8.5 millimeters, but this can vary from 7 to 10 millimeters depending on the population and individual genetics. The faciolingual dimension at the cervix is about 7 millimeters. These measurements are the ones you will reference most often when selecting an artificial tooth for a prosthetic case, so having them memorized saves you from flipping through charts every time.
Get the Full Details
What Beginners Get Wrong
The most common mistake I see is treating the central incisor as a symmetric structure. It is not. The mesial side is sharper, straighter, and more angular while the distal side is more convex and rounded at every level—crown margin, contact area, and root outline. If you replicate the distal anatomy on the mesial side when teaching students to draw teeth or when fabricating provisional crowns, the result will look unnatural and the occlusal relationships will feel slightly off to anyone with a trained eye. Another thing that causes problems is underestimating the importance of the cingulum in determining the phonetic function of the tooth. The position and prominence of the cingulum affects how the tongue interacts with the anterior teeth during speech, particularly for sibilant sounds like s and z. If a patient has a severely worn cingulum from bruxism and you restore it without paying attention to its original spatial relationship with the tongue, you can introduce speech impediments that take weeks to adapt out of. I once had a prosthodontist colleague who replaced a worn cingulum on a maxillary central with a flat, featureless surface and the patient came back three weeks later complaining of a persistent lisp that had not been present before the procedure. Pulp chamber size is another area where assumptions lead to errors. In younger patients the pulp chamber is large and easily located, but as the tooth ages secondary dentin deposition narrows the chamber and canals. By the time a patient reaches their fifth decade, the pulp of a maxillary central incisor may have minimal space remaining, and aggressive cavity preparation can lead to unexpected exposure. This is why I always take a fresh radiograph before starting any endodontic access on a central incisor in a patient over 40, even if one was taken recently, because the anatomy changes subtly and those changes are easy to miss.
Tools And References That Actually Help
If you are studying this for academic purposes, the standard anatomical diagrams from Wheeler's Dental Anatomy give you a reliable baseline, but they do not capture the variation you will see in clinical practice. What helped me most was using actual extracted teeth and running my fingernail along the developmental grooves to feel the topography directly. Visual diagrams flatten three-dimensional structures into two dimensions and that loses a lot of useful information. The depth of the lingual fossa, the angle of the incisal edge relative to the root axis, the way the root curves distally—these are all spatial relationships that are much clearer when you can hold the tooth and rotate it. For digital reference, there are 3D dental anatomy applications and atlases available online that let you rotate and section virtual teeth. The quality of these varies considerably, and some of the freely available models have anatomical inaccuracies that come from poor scan resolution or incorrect segmentation. I recommend cross-referencing whatever digital tool you use with a physical specimen whenever possible. The extra few minutes it takes to verify a detail can save you from building your understanding on a flawed foundation. If you need a downloadable reference chart that covers the key morphological landmarks of the maxillary and mandibular central incisors side by side, the standard dental anatomy resource packages from university dental departments usually include high-resolution line drawings and measurement tables that are suitable for study purposes. Look for versions that include both facial and lingual views along with cervical cross-sections, since those cross-sections are where most of the clinically relevant variation is encoded.
The anatomy itself does not change between individuals in fundamental ways, but the degree of development of each feature—the sharpness of the mesial angle, the depth of the lingual fossa, the curvature of the root apex—varies enough that you need to approach each tooth as a unique structure rather than a template copy. That is the main thing I wish more people understood when they first start studying dental anatomy. The general patterns are consistent, but the specific expression of those patterns is what determines how a tooth behaves in a clinical situation.