Palpating the Hand and Wrist: A Field Guide
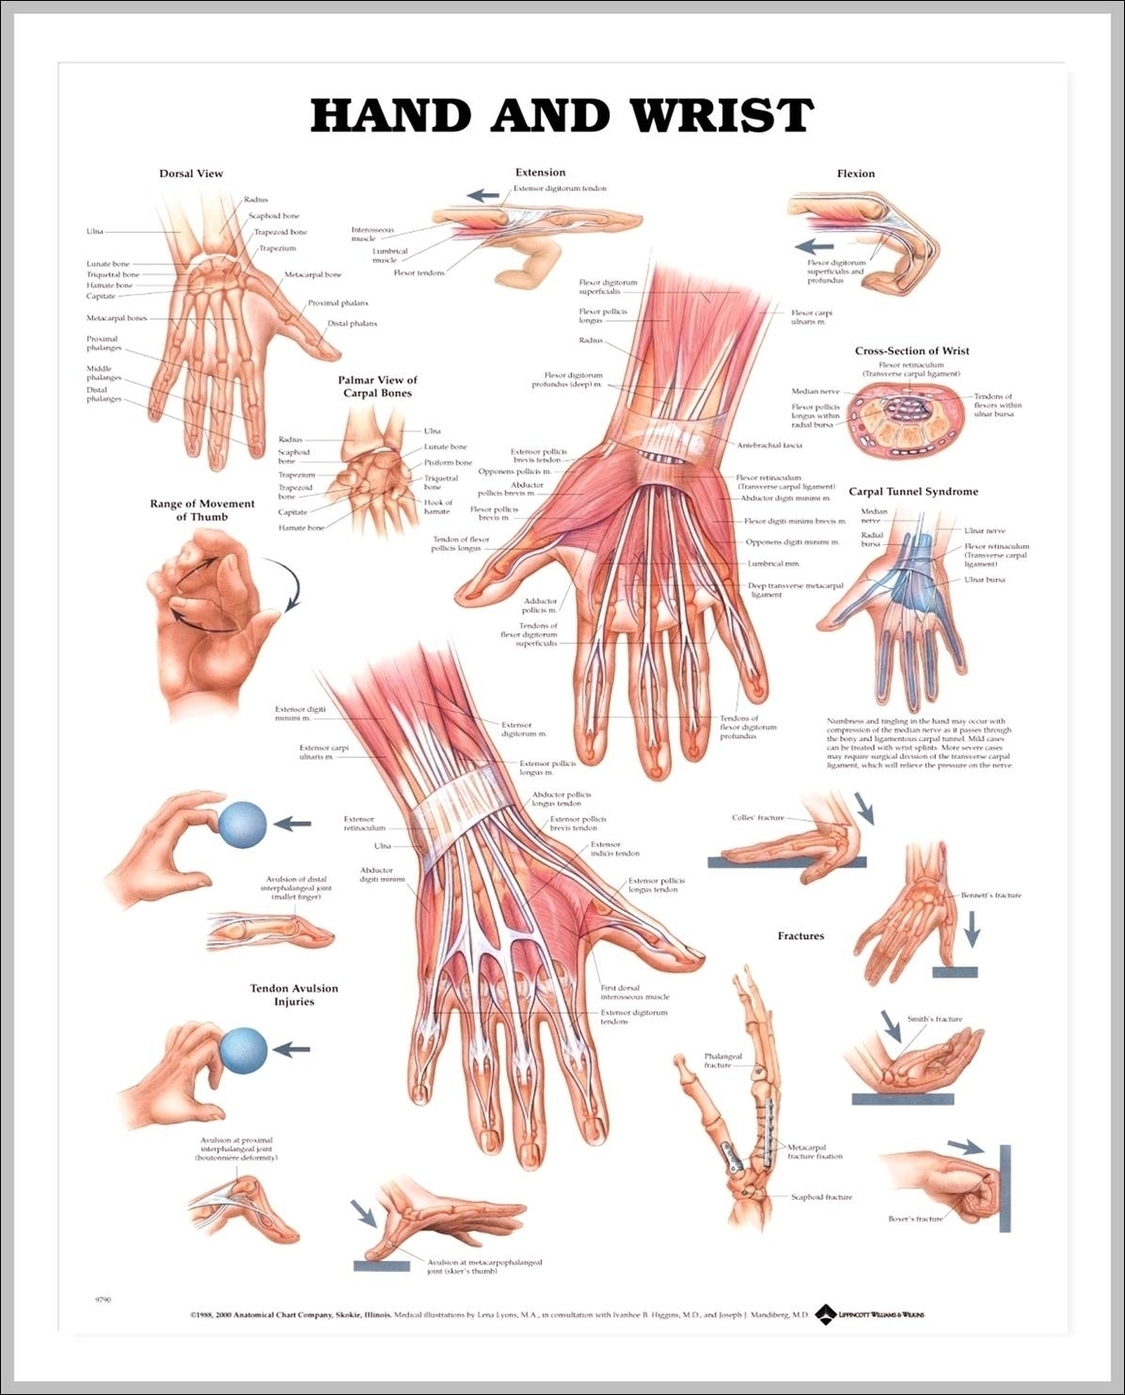
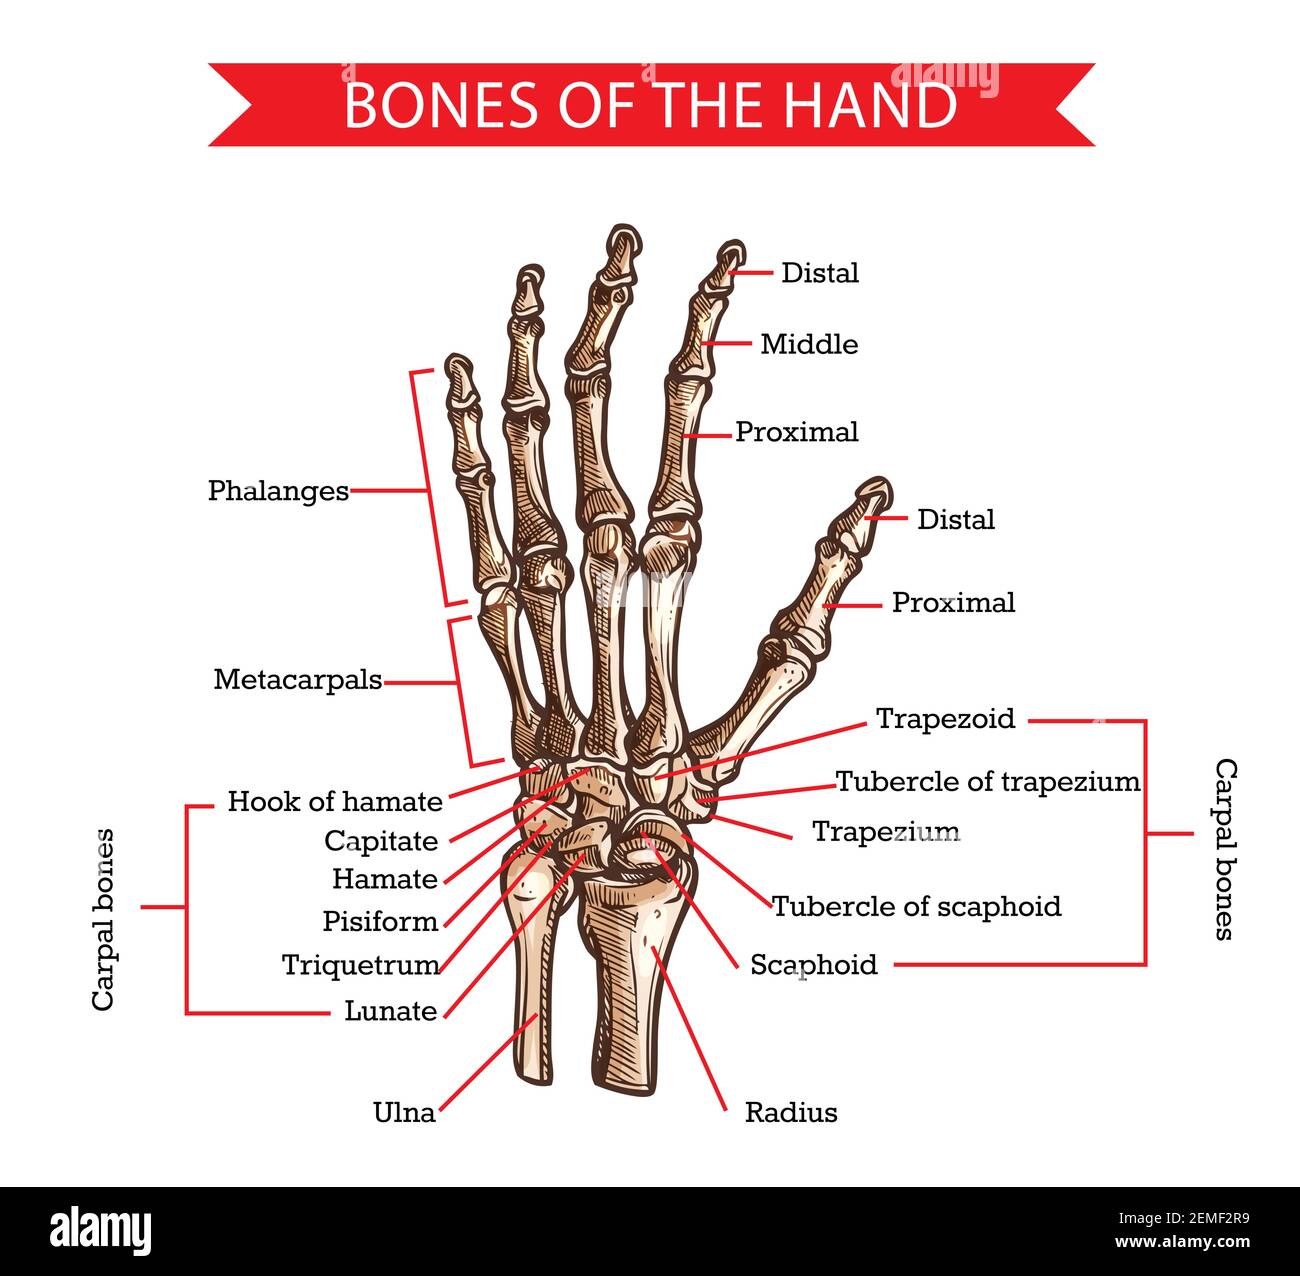
The hand is one of those areas where every textbook drawing looks deceptively simple until you actually put your fingers on a living person. Bone, tendon, and nerve are packed into a space most people think of as "flesh," and understanding what sits where matters whether you are doing manual work, giving injections, or just trying to figure out why someone's pinky keeps going numb at 2 PM. Start with the wrist joint itself. The distal radius and ulna form the proximal column. Between them sits the triangular fibrocartilage complex, or TFCC, which most people either ignore completely or treat as some vague soft-tissue band. It is both a shock absorber and the primary stabilizer between the radius and ulna during rotation. When someone has ulnar-sided wrist pain after lifting something heavy, the TFCC is frequently the culprit, not the ligaments everyone blames first. The carpal bones arrange themselves in two rows. Proximally you have the scaphoid, lunate, triquetrum, and pisiform from radial to ulnar. Distally you have the trapezium, trapezoid, capitate, and hamate. The scaphoid is the largest proximal bone and the most commonly fractured. Its blood supply enters from the distal end and travels retrograde proximally, which means a undisplaced scaphoid fracture can look fine on an initial X-ray and still develop avascular necrosis if you cast it and forget to follow up.
Through the carpal tunnel run four flexor digitorum superficialis tendons, four flexor digitorum profundus tendons, and one flexor pollicis longus tendon. The median nerve shares that space. The tunnel itself is rigid. The floor is formed by the palmar radiocarpal ligament and the interosseous membrane, and the roof is the flexor retinaculum. There is almost no room for expansion. That is why swelling from anything — tenosynovitis, a ganglion cyst, even repetitive fraying of the flexor tendons — compresses the median nerve before you see obvious external signs. On the dorsal side you get the extensor compartments, numbered one through six from radial to ulnar. Compartment one contains the abductor pollicis longus and extensor pollicis brevis. Compartment six contains the extensor indicis and extensor digiti minimi. De Quervain tenosynovitis is inflammation in compartment one. It is nearly always misdiagnosed initially because the pain referral pattern overlaps with basal joint arthritis of the thumb. The ulnar nerve passes through Guyon's canal on the palmar side of the wrist, not through the carpal tunnel. It splits into a superficial branch that supplies sensation to the ulnar one and a half digits and a deep motor branch that innervates most of the intrinsic hand muscles. Compression here causes a different pattern than median nerve entrapment. Ulnar clawing at the ring and little fingers without thenar wasting is a classic sign that the problem is at the wrist, not the neck.
My first real lesson in this anatomy came from a friend who kept complaining of thumb pain. We tried everything — rest, ice, anti-inflammatories, even a thumb spica brace. Nothing moved the needle. I finally had him make a tight fist with his thumb tucked inside and then deviate his wrist ulnarly. Positive Finkelstein test. The diagnosis was clear. What surprised me was how quickly the pain disappeared once we stopped treating it like general wrist strain and aimed at the actual inflamed tendons in the first dorsal compartment. It took about three weeks of targeted immobilization and one corticosteroid injection. He was back to normal lifting within six weeks. The delay was entirely because the initial assessment had been wrong.
Get the Full Details

Practical Palpation Map
Learning to feel these structures takes repetition. Here is how I approach it systematically on any subject. Ask the person to make a gentle fist. The knuckles that protrude are the metacarpal heads. Trace down each to the proximal phalanx base. These are your anchors. From there, move to the wrist. On the palmar side, locate the wrist crease. Just radial to that crease you can feel the radial artery pulse. Slightly ulnar to the artery lies the palmaris longus tendon if the person has it — about fourteen percent of the population does not. With the thumb extended and wrist slightly extended, you can feel the flexor carpi radialis tendon radial to the palmaris and the flexor carpi ulnaris tendon on the far ulnar border.
Flip the hand over. Extend the fingers. Three prominent tendons appear along the dorsal surface. From radial to ulnar they are the extensor pollicis longus, the extensor digitorum communis tendons, and the extensor carpi ulnaris. The EPL crosses a bony landmark called Listers tubercle on the distal radius. It acts as a pulley. When EPL tears — usually from a distal radius fracture or rheumatoid erosion — the person loses the ability to extend the thumb IP joint. The hand still looks fine at rest. You only notice when asked to make a fist and then extend the thumb against resistance. The scaphoid is palpable in the anatomical snuffbox. Ask the person to extend the thumb and abduct it slightly. The depression between the two tendons you see is the snuffbox. Press gently into its floor. That is the scaphoid. Tenderness here is a fracture until proven otherwise. Do not wait for the second X-ray. Cast and refer. The lunate sits just proximal and slightly ulnar to the scaphoid. It is deeper and harder to isolate individually. The triquetrum sits ulnar to that and is more superficial. The pisiform is the small oval bone you can roll under your thumb at the base of the hypothenar eminence. It is actually a sesamoid bone embedded in the flexor carpi ulnaris tendon, which is why it moves so freely.
Common Misreads and Where People Go Wrong
The biggest mistake I see is treating all wrist pain as generic strain. The hand and wrist contain thirty-three bones, over one hundred ligaments, thirty-four tendons, and five major nerves. "Wrist pain" narrows to maybe six or seven plausible diagnoses after a proper exam. The rest are red herrings. Carpal tunnel syndrome is the most common entrapment neuropathy in the extremities, but it is frequently overdiagnosed. Many people with tingling in the thumb and index finger have cervical radiculopathy at C6. The differentiation is straightforward. Perform a Spurling test. If neck extension and rotation reproduce the hand symptoms, the problem is likely proximal. If Phalen's maneuver and the nerve conduction study point to the wrist, then it is carpal tunnel. Do both. Do not pick one and stop. Another frequent error is assuming that weakness in grip always means muscle or tendon damage. It often means nerve involvement. The median nerve supplies the thenar muscles including the opponens pollicis, abductor pollicis brevis, and flexor pollicis brevis. The ulnar nerve supplies the interossei and the medial two lumbricals. Weakness in finger abduction and adduction points to ulnar nerve. Weakness in thumb opposition and abduction points to median nerve. Grip strength testing alone cannot distinguish between them.
I ran into a case last year involving a guitar player who could not hold a chord for more than thirty seconds. His symptoms pointed toward carpal tunnel. Nerve conduction was borderline. I asked him to play for twenty minutes and then retest. The median nerve latency had worsened noticeably after sustained flexion. The issue was not a structural compression in the tunnel. It was dynamic compression caused by sustained wrist flexion during playing. The workaround was changing his playing posture and using a wrist brace only during sleep, not during practice. Surgery would not have helped and probably would have made things worse.
When Imaging Helps and When It Does Not
X-rays show bone. They do not show ligaments, tendons, nerves, or the TFCC. If you suspect a scaphoid fracture and the X-ray is negative, order an MRI or a bone scan within ten days. CT is useful for characterizing fracture patterns before surgical fixation but is less sensitive than MRI for occult fractures. Ultrasound is increasingly useful for dynamic assessment of tendons. You can watch the flexor and extensor tendons glide in real time. It catches tenosynovitis and partial tears that static MRI sometimes misses. The limitation is operator dependency. A poor-quality scan is worse than no scan because it gives false reassurance. MRI arthrogram is the gold standard for TFCC pathology. Standard MRI underestimates TFCC tears by about twenty percent compared to arthrography. If clinical suspicion is high and treatment planning depends on confirming a tear, skip the plain MRI and go straight to the arthrogram.
Key Takeaways for Working With This Anatomy
Localize before you label. Find the exact structure involved before committing to a treatment path. The difference between median nerve compression at the wrist and C6 radiculopathy changes the entire management plan. The difference between EPL tendon rupture and radial nerve palsy changes whether you operate or rehabilitate. Palpation beats assumption every time. Spend time learning the surface landmarks. Know where the scaphoid sits. Know where Lister's tubercle is. Know the boundaries of Guyon's canal. These are not trivia. They are the difference between accurate diagnosis and guessing. Dynamic testing reveals what static testing hides. Most hand and wrist conditions involve movement. Assess function under load, not just at rest. The guitar player case I mentioned is not unusual. Many tendon and nerve issues in the hand present normally at rest and only become apparent under repetitive stress.

Do not rely on a single diagnostic test. Nerve conduction studies have false negatives. X-rays miss early fractures. Clinical tests have varying sensitivity depending on the examiner. Combine at least two methods before committing to invasive treatment. The hand is compact. There is very little margin for error in diagnosis because the structures are so close together and share innervation and vascular supply. A careful, methodical approach saves time and prevents unnecessary procedures. Rushing through the exam because the symptoms look familiar is how you miss the actual problem and end up treating the wrong thing for months.


