How The Digestive Tract Actually Works In Practice
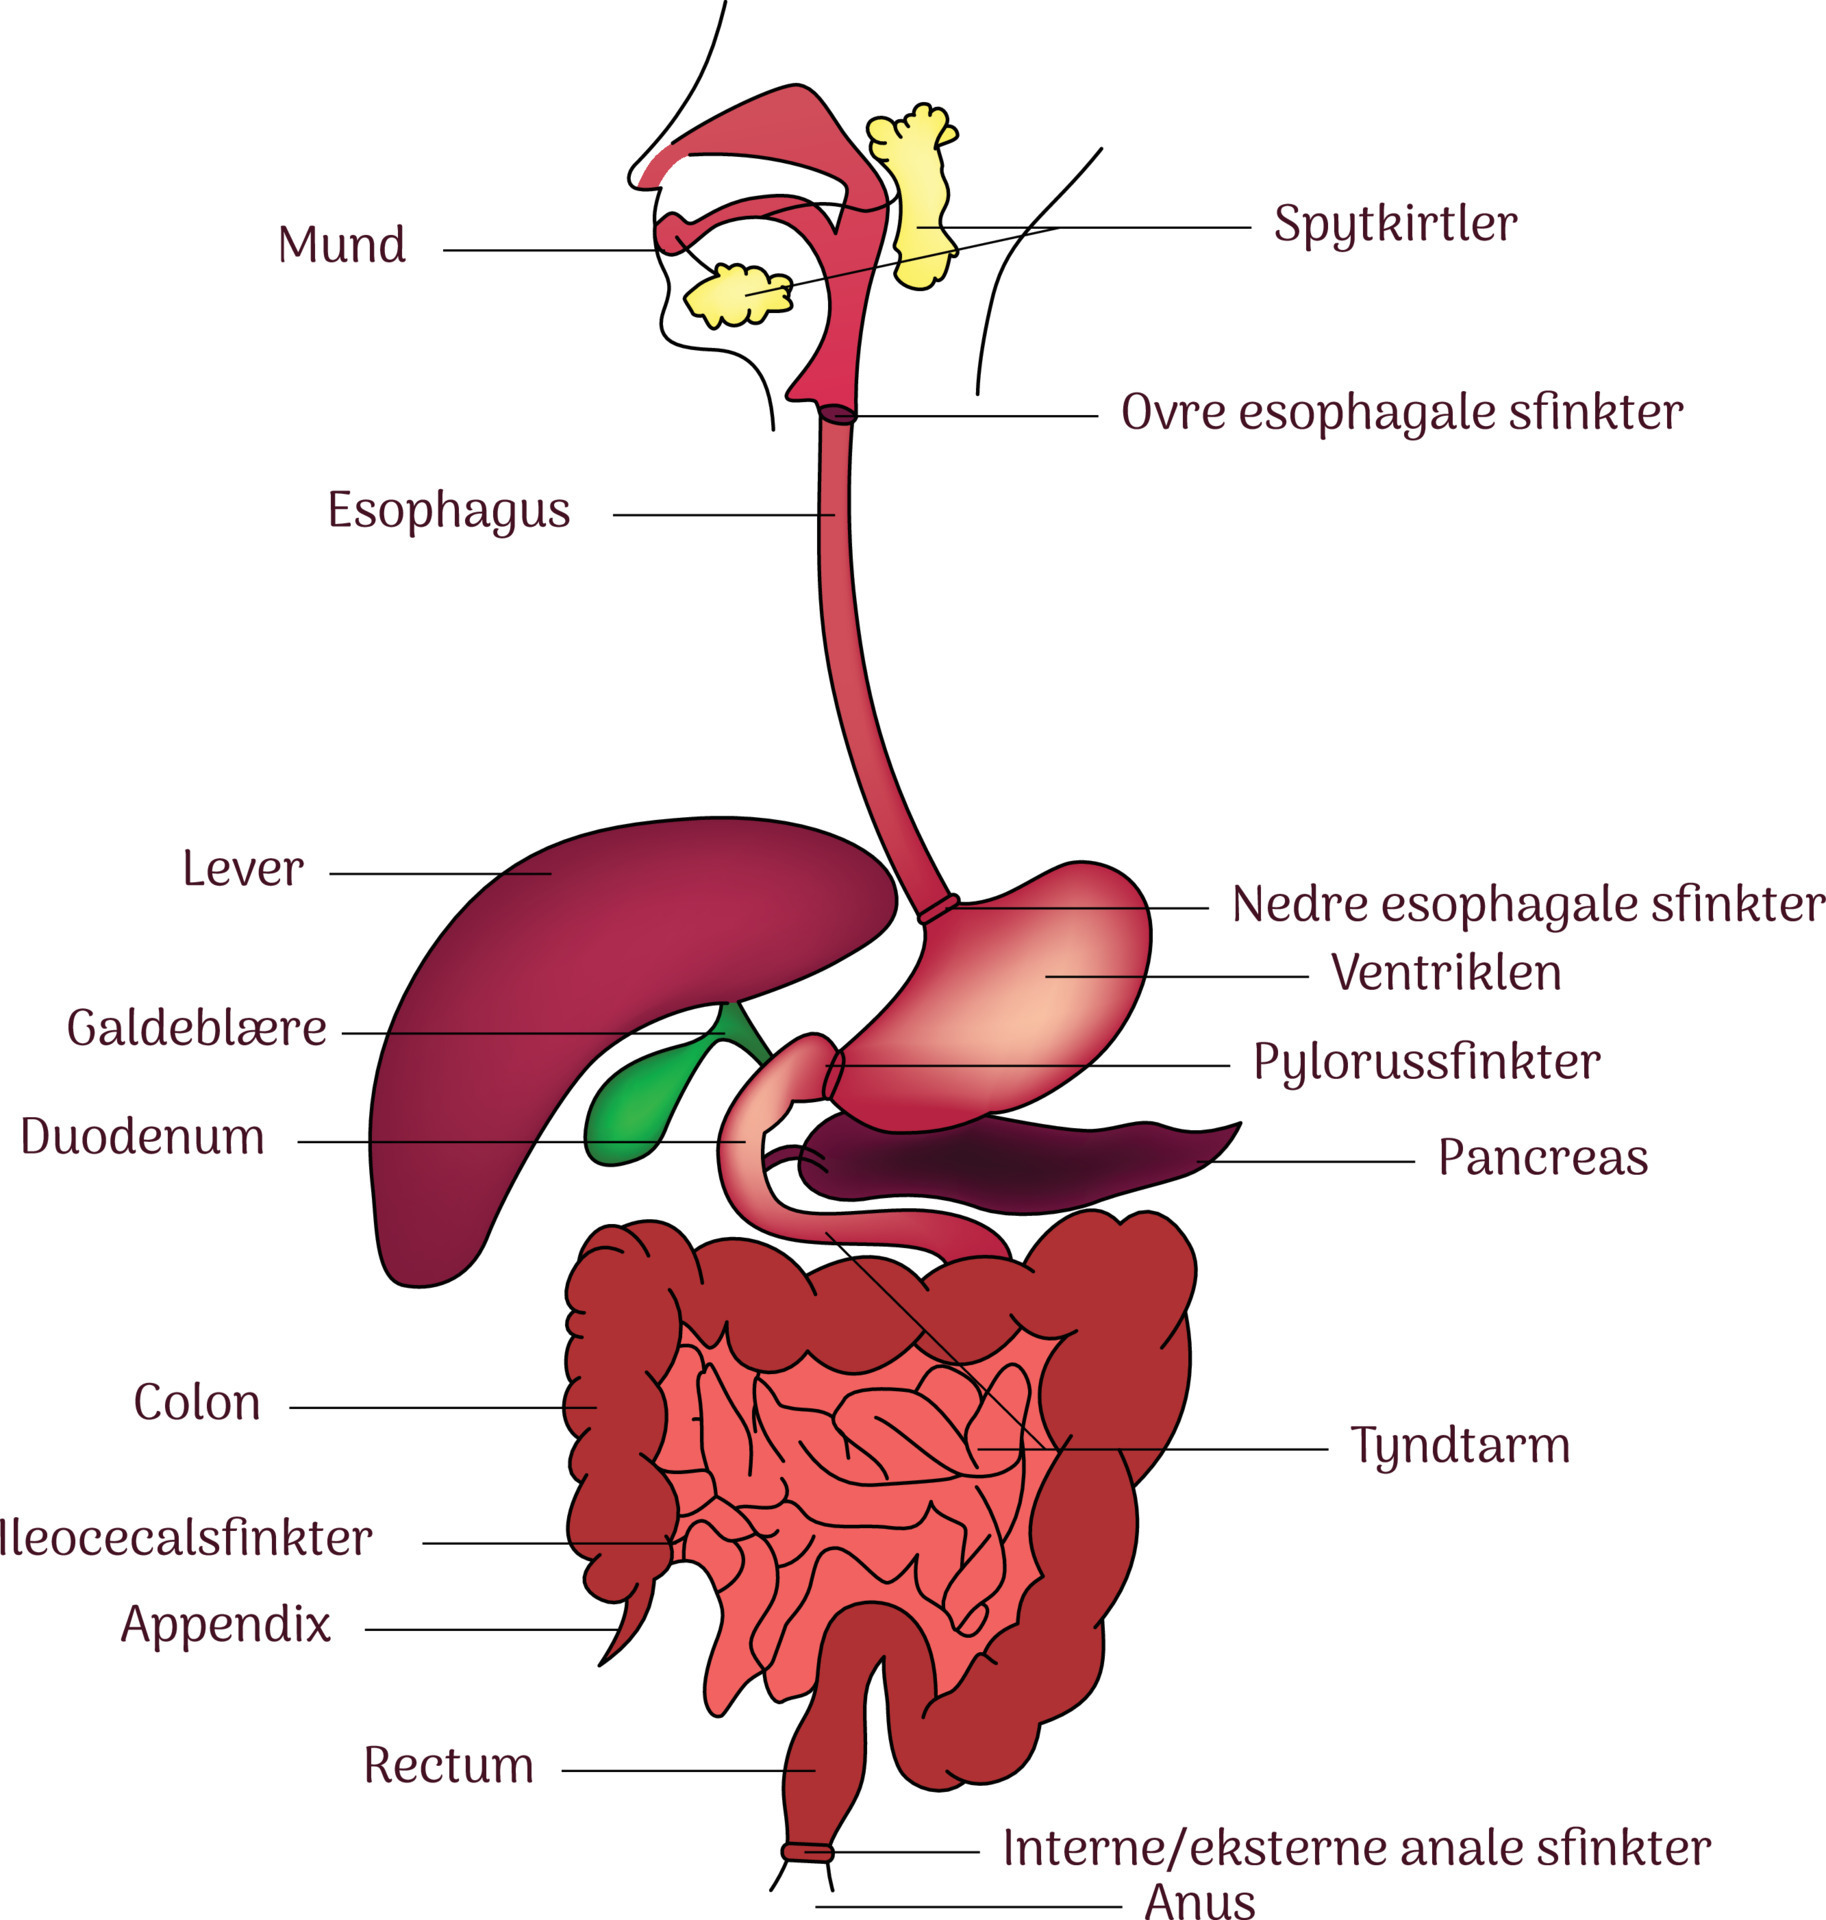
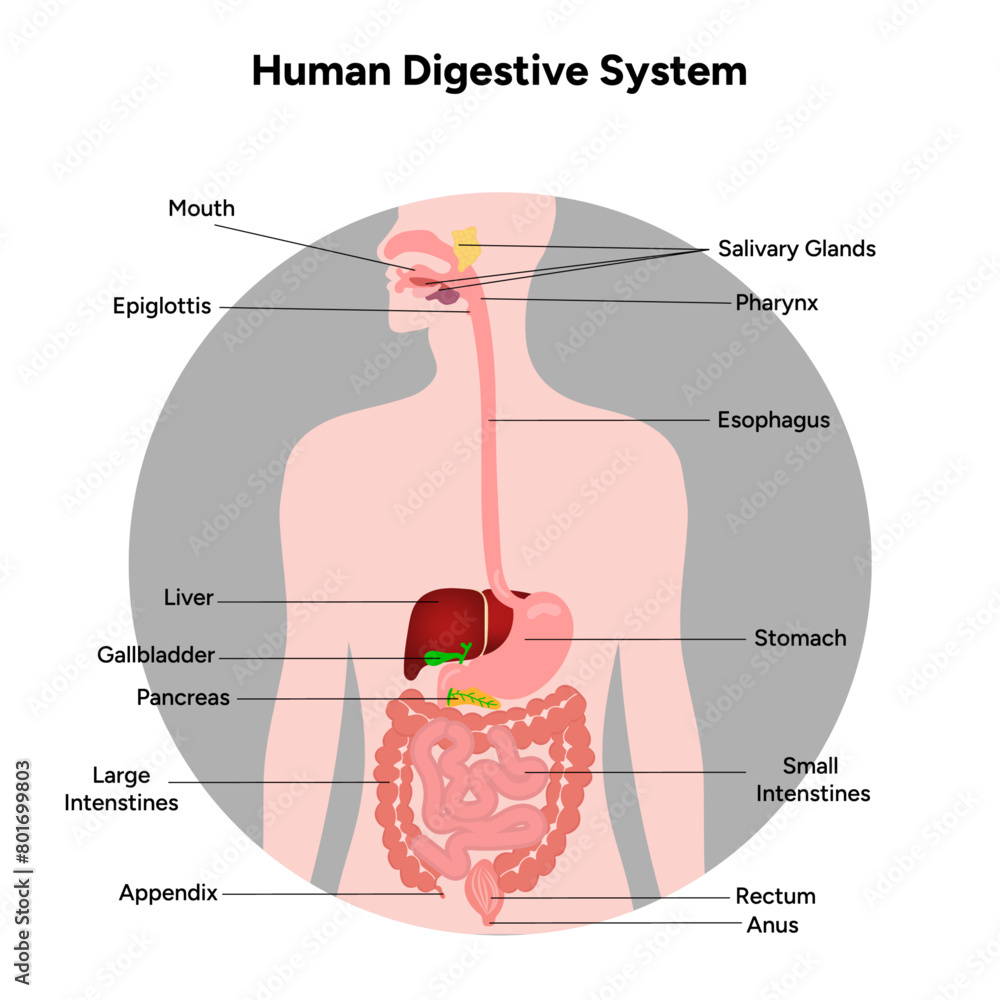
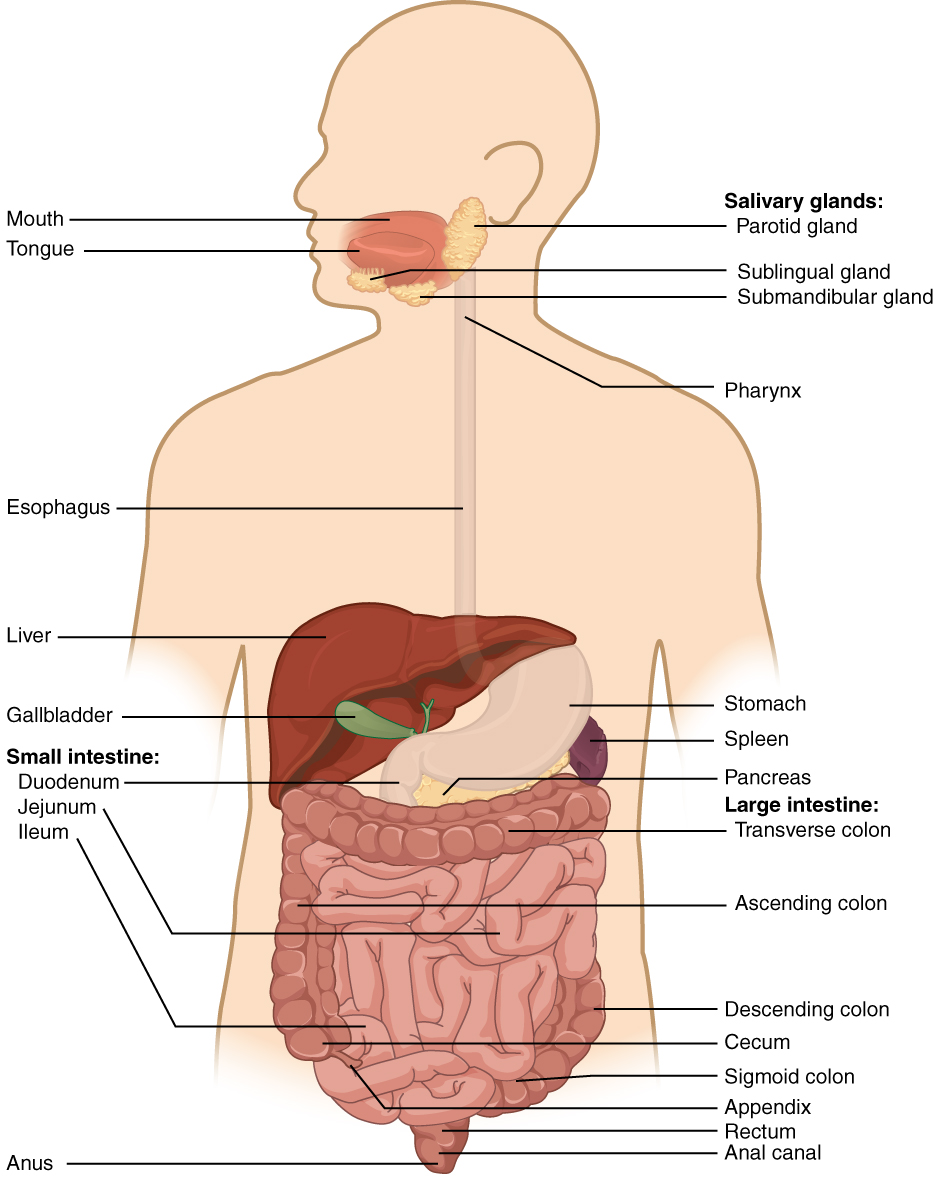
Most people think digestion is straightforward. Swallow something, it goes down, waste comes out. That's not even close to accurate. The anatomy of the digestive system is a series of muscular tubes, enzymatic reactions, and regulatory feedback loops that run constantly whether you're aware of them or not. I've spent years watching how this system functions under different conditions, and there are details most guides skip over entirely.The GI tract stretches roughly nine meters from mouth to anus. It's not a simple hose. Each section has distinct histological layers and specialized functions that don't always work in sync. When someone describes the digestive system as one continuous tube, they're technically right but functionally misleading. The stomach doesn't just sit there soaking food in acid. It coordinates with the pyloric sphincter, the duodenum, and the pancreas in real time, adjusting gastric emptying rate based on what's actually in the chyme. The oral cavity begins mechanical breakdown through mastication and chemical breakdown through salivary amylase, which starts starch hydrolysis before food even reaches the stomach. The esophagus uses peristaltic waves—primary and secondary—to move the bolus downward. Primary peristalsis is the initial wave. Secondary peristalsis kicks in when residual food remains and triggers reflexive contractions to clear it out. The lower esophageal sphincter maintains a resting tone of about 15-30 mmHg to prevent reflux, but this isn't a rigid valve. It's a functional sphincter that relaxes during swallowing via inhibitory neurons releasing nitric oxide and vasoactive intestinal peptide. The stomach has three major regions: the fundus, body, and antrum. The fundus handles receptive relaxation, allowing the stomach to accommodate large volumes without a significant pressure increase. This is called adaptive relaxation and it's mediated by vagal pathways. The antrum is where mechanical grinding happens, creating particles small enough to pass through the pylorus—usually less than 2 millimeters. Food larger than that gets sent back into the body for further breakdown. This is called sieving, and it's a critical mechanism most people don't know about.
The small intestine is divided into the duodenum, jejunum, and ileum. The duodenum receives chyme along with bile from the gallbladder and pancreatic juice from the pancreas. Bicarbonate neutralizes the acidic chyme, raising the pH to around 6-7, which is necessary for pancreatic enzymes to function optimally. The jejunum and ileum are where the majority of nutrient absorption occurs, thanks to the massive surface area created by plicae circulares, villi, and microvilli. The total absorptive surface area is approximately 250 to 300 square meters—roughly the size of a tennis court. The large intestine doesn't digest much. Its main roles are water reabsorption, electrolyte balance, and housing the colonic microbiome. The ascending colon, transverse colon, descending colon, sigmoid colon, and rectum each have slightly different functions. The right colon absorbs more fluid. The left colon stores and formats feces. The rectum's role is primarily sensory and evacuative, with internal and external anal sphincters working in coordination.
What Goes Wrong And How To Fix It
Here's something most anatomy textbooks won't tell you: the anatomy of the digestive system is highly variable between individuals, and standard diagrams are averages, not rules. I once dealt with a case where a patient had persistent postprandial bloating and early satiety that standard motility tests couldn't explain. The issue was a congenitally short mesocolon causing intermittent volvulus of the transverse colon. Standard imaging missed it because the volvulus resolved on its own between episodes. We caught it using a dedicated CT enterography with neutral oral contrast and positional imaging—prone and supine views showed the colon shifting between positions. Without that specific protocol, it would have been dismissed as functional dyspepsia. This is important because it shows why understanding the anatomy isn't just about memorizing parts. It's about understanding spatial relationships, attachments, and the dynamic nature of these structures. The digestive system moves. It changes position during respiration, digestion, and even throughout the day. A structure that looks normal on a static image might be causing significant problems when you account for motion. Another overlooked aspect is the enteric nervous system, often called the second brain. It contains roughly 500 million neurons—more than the spinal cord. This network operates largely independently of the central nervous system, though the two communicate bidirectionally. When someone has anxiety and reports stomach issues, it's not all in their head. The gut-brain axis is a real physiological pathway involving the vagus nerve, serotonin signaling, and inflammatory mediators. About 90% of vagal fibers are afferent, carrying information from the gut to the brain, not the other way around. This is a common misconception in both clinical and lay settings.
Get the Full Details
Practical Considerations For Understanding This System
If you're studying this for medical or clinical purposes, don't rely solely on diagrams. Spend time with cadaver dissections or high-resolution cross-sectional anatomy. The relationships between the liver, gallbladder, pancreas, and duodenum are three-dimensional, and flat images can't convey the surgical and clinical significance of those spatial relationships. The gastroduodenal artery runs posterior to the first part of the duodenum. A posterior duodenal ulcer can erode into this vessel and cause life-threatening hemorrhage. This isn't something you grasp fully from a labeled diagram. You need to understand the anatomical planes and the layers involved. For self-study, I recommend starting with the gross anatomy, then layering in the histology, then the physiology. Jumping straight into physiology without understanding the structural basis leads to confusion. You can't understand why gastrin stimulates acid secretion if you don't know where G cells are located, what mucosa they're in, and how they're regulated by pH feedback. The anatomy precedes the function. Always. The vascular supply is another area where people rush through too quickly. The foregut, midgut, and hindgut each have distinct arterial supply from the celiac trunk, superior mesenteric artery, and inferior mesenteric artery respectively. This classification matters because it determines lymphatic drainage, venous return, and referred pain patterns. Foregut structures refer pain to the epigastrium. Midgut to the periumbilical region. Hindgut to the hypogastrium. If you're trying to diagnose abdominal pain, this anatomical framework is essential. Skipping it means relying on symptoms alone, which is unreliable.
One more thing that rarely gets emphasized: the lymphatic drainage of the GI tract. Lacteals in the villi absorb dietary fats and transport them into the intestinal lymphatics, which eventually drain into the thoracic duct. This is why fat malabsorption causes steatorrhea and why certain cancers metastasize through lymphatic channels. The mesenteric lymph nodes are the first site of potential metastasis for many gastrointestinal malignancies. Understanding this anatomy has direct clinical implications for staging and treatment planning. The digestive system is far more complex than most introductory materials suggest. The interactions between neural, endocrine, immune, and microbial systems create a dynamic environment that responds to everything from stress to diet to medication. Learning the anatomy is the foundation, but the real understanding comes from seeing how these systems interact in real clinical situations. That's where the gaps in standard education tend to show.