The Basics of ADH Production
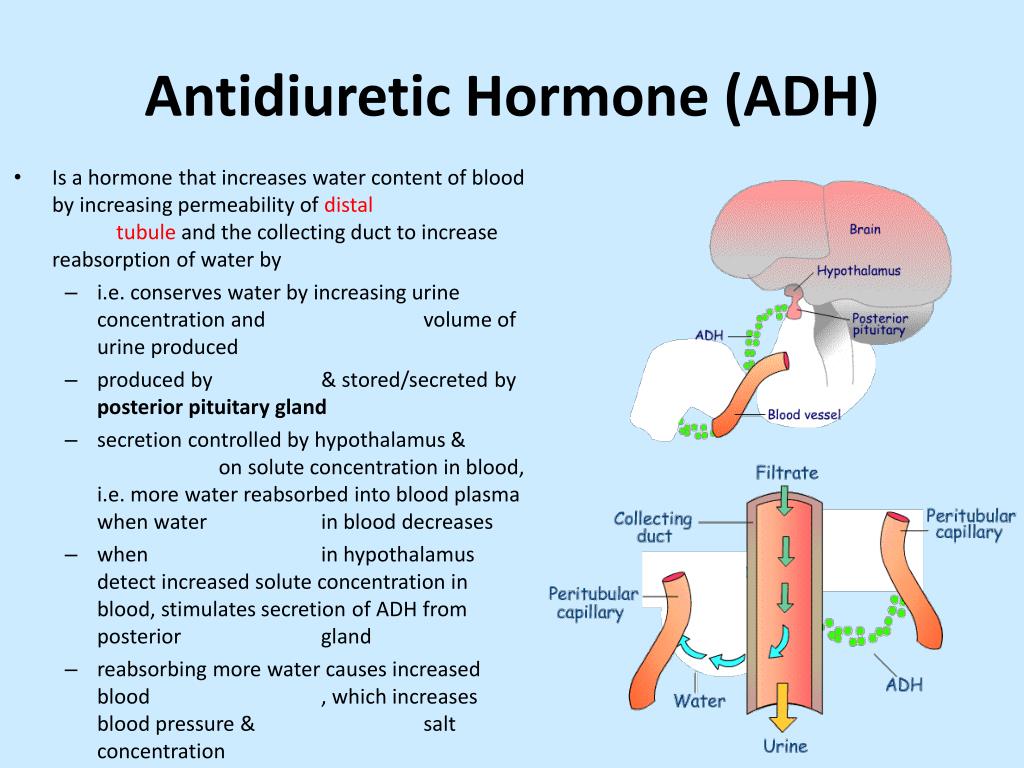
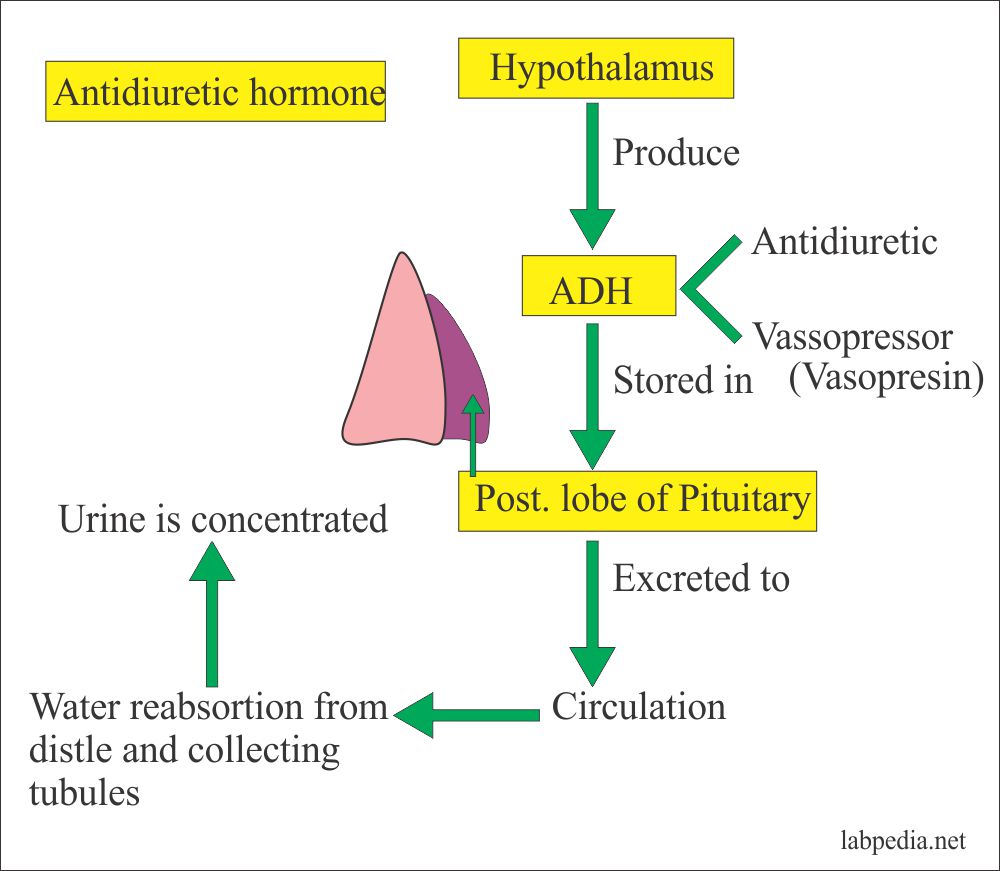
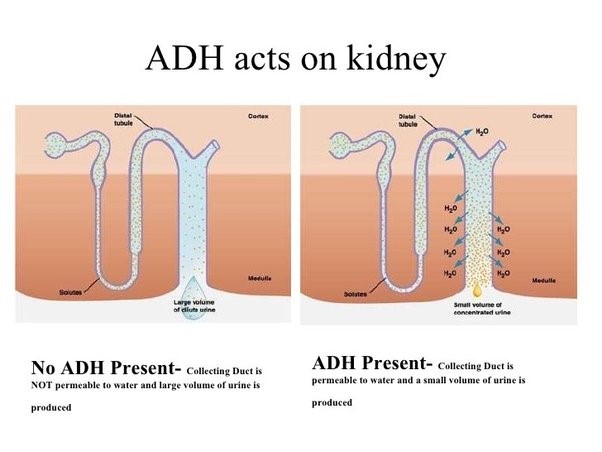
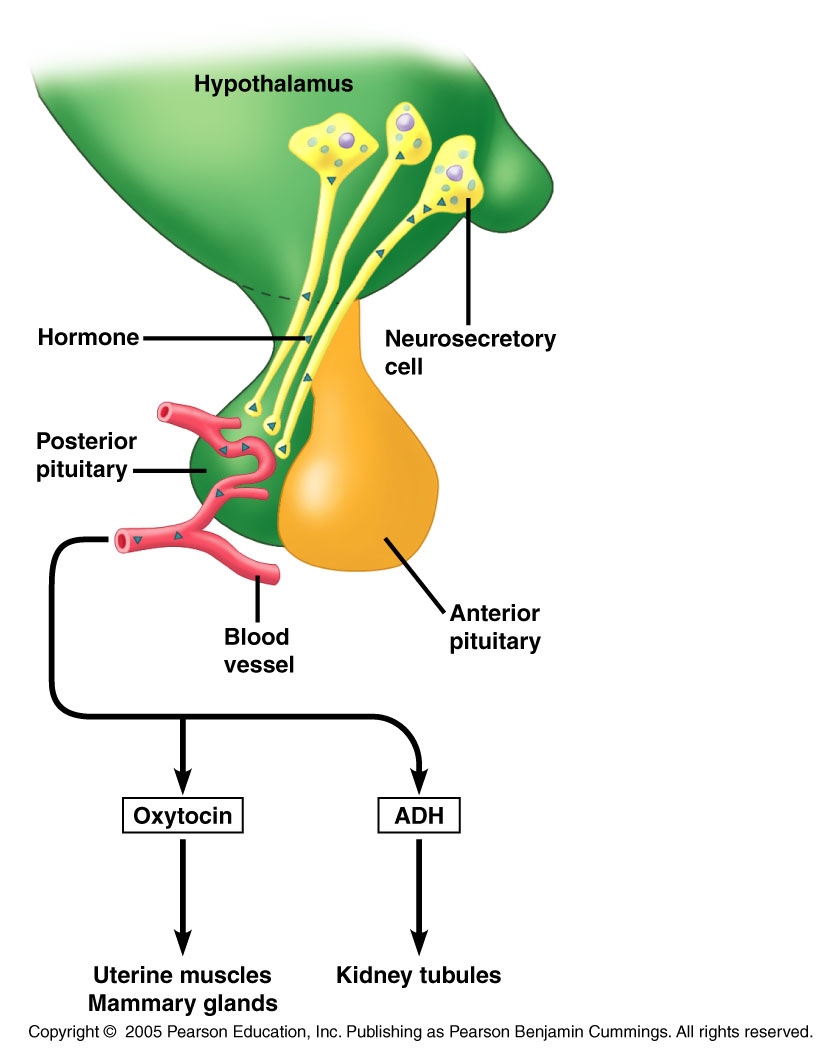
Antidiuretic hormone, or ADH, is made in the hypothalamus. Specifically, it's synthesized in the cell bodies of neurons located in the supraoptic and paraventricular nuclei. From there, it gets packed into vesicles and transported down the axons through the pituitary stalk to the posterior pituitary gland, where it's stored until the body needs it. Here's the part people usually get confused about: the posterior pituitary isn't actually where ADH is produced. It's more like a warehouse. The hormone is manufactured in the hypothalamus and shipped down neuronal axons for storage. When your body detects dehydration or a drop in blood volume, those neurons fire, and ADH gets released from the posterior pituitary into the bloodstream. That's the release site, not the production site. Mixing those two up will cost you points on any exam, and it'll confuse you when you're reading clinical literature. ADH's main job is making your kidneys reabsorb water. It inserts aquaporin-2 channels into the collecting ducts of the nephrons, so instead of peeing out a liter of dilute urine, you concentrate it and keep the water. Under normal conditions, this keeps your osmolality around 275-295 mOsm/kg. Once you push past that threshold, ADH secretion ramps up quickly.
I ran into a weird case a few years back when a patient with a small pituitary adenoma was being worked up for what looked like SIADH — inappropriate ADH secretion. Their sodium was 124, they were euvolemic, and the urine osmolality was inappropriately concentrated. Standard workup said central diabetes insipidus wasn't the issue. But the MRI showed the lesion was compressing the stalk, which actually impaired the normal pulsatile release of ADH in a way that mimicked SIADH intermittently. The workaround was stopping desmopressin temporarily, checking fasting plasma osmolality against urine osmolality in a controlled setting, and doing a water deprivation test with more frequent sampling than the textbook protocol suggests. Turns out the gland was producing fine, but the release pattern was erratic because of the mechanical compression. Treating it as straightforward SIADH would've been a mistake. There are other triggers beyond osmolality. Significant blood loss or a drop in blood pressure around 5% or more will stimulate ADH release through baroreceptors in the carotid sinus and atria. That response is much more sensitive than the osmoreceptor pathway. You can have near-normal sodium levels and still be dumping ADH if your volume is low. This is one of those nuances that matters clinically but doesn't get enough emphasis in introductory courses. Also worth noting: ADH has a very short half-life, roughly 10 to 20 minutes in circulation. The kidneys clear it quickly, and hepatic metabolism plays a role too. This means the hormone levels can swing fast, which is why transient issues like nausea, pain, or certain medications can cause brief spikes in ADH that resolve on their own.
Certain drugs affect ADH production and release. SSRIs, carbamazepine, and cyclophosphamide are known to stimulate secretion, while alcohol and glucocorticoids suppress it. If you're evaluating someone with abnormal water balance, the medication history is usually where you start looking before you order more expensive testing. On the production side, the synthesis itself happens at the ribosomes in the hypothalamic neurons. The precursor is preprovasopressin, which gets cleaved into vasopressin, neurophysin II, and a glycoprotein called copeptin. Copeptin is now used as a surrogate marker for ADH because it's more stable in blood samples. If you're ordering labs and your institution only measures copeptin, don't assume it's a inferior test — in many cases it's actually more practical. Conditions like craniosurgical trauma, subarachnoid hemorrhage, or infiltrative diseases of the hypothalamus can damage the production sites directly. In those situations, you see true central diabetes insipidus — the body stops making ADH, and patients present with polyuria and hypernatremia. The treatment is desmopressin replacement, but the dose has to be carefully titrated because the remaining functionality can vary day to day in the early post-injury period.
Get the Full Details